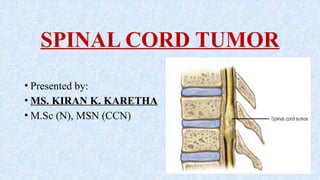
SPINAL CORD TUMOR
• Presented by:
• MS. KIRAN K. KARETHA
• M.Sc (N), MSN (CCN)
INTRODUCTION
•The spinal cord is a part of the central nervous system
that carries nerve impulses between the brain and the
body.
•A tumor in the spinal cord can compress the spinal
cord or spinal nerves, leading to pain, weakness,
sensory loss, and paralysis.
•Early diagnosis and treatment are essential to prevent
permanent neurological damage.
DEFINITION
•Spinal cord cancer is a malignant neoplasm that
develops within the spinal cord or its surrounding
tissues, or spreads to the spinal cord from another part
of the body, resulting in compression or destruction of
neural structures and causing neurological dysfunction.
CLASSIFICATION
•1. According to Origin
•A. Primary spinal cord tumors
•Originate in the spinal cord or its coverings.
•Less common.
•May be benign or malignant.
CONTI..
•B. Secondary (Metastatic) spinal tumors
•Spread from another cancer.
•More common than primary tumors.
•Common primary sites:
• Lung cancer
• Breast cancer
• Prostate cancer
• Kidney cancer
• Thyroid cancer
CONTI..
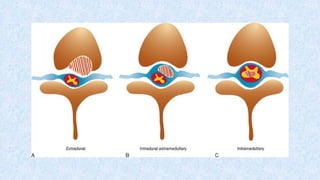
• According to Location
• 1. Intramedullary Tumors
• Intramedullary tumors arise within the spinal cord tissue. They
originate from the cells of the spinal cord and are usually primary
tumors.
• Common Types
• Ependymoma: Most common in adults; develops from ependymal cells
lining the central canal of the spinal cord.
• Astrocytoma: Arises from astrocytes (glial cells); more common in
children and young adults.
CONTI..
• 2. Intradural-Extramedullary Tumors
• These tumors are located inside the dura mater but outside
the spinal cord. They compress the spinal cord without
invading it.
• Common Types
• Meningioma: Arises from the meninges; usually benign and
slow-growing.
• Schwannoma: Develops from Schwann cells of the spinal
nerve roots; usually benign.
•3. Extradural Tumors
•Extradural tumors are located outside the dura mater,
usually involving the vertebrae.
•Most are metastatic (secondary) tumors.
CAUSES AND RISK FACTORS
• The exact cause is often unknown.
• Risk factors include:
• Previous cancer (lung, breast, prostate, kidney)
• Genetic disorders
• Exposure to radiation
• Family history of tumors
• Increasing age
• Weakened immune system (rare cases)
GRADES
•For primary spinal cord cancer (spinal cord tumors),
there is no internationally accepted Stage I–IV or
TNM staging system.
•Instead, authoritative sources such as the National
Cancer Institute (NCI) and the World Health
Organization (WHO) classify these tumors by WHO
grade, which reflects how aggressive the tumor is.
WHO Grading of Primary Spinal Cord Tumors
• Grade I (Low-Grade Tumor)
• Grade I tumors are slow-growing and well-defined. They rarely
spread and can often be cured with complete surgical removal.
• Characteristics
• Slow-growing
• Well-circumscribed
• Minimal invasion into surrounding tissue
• Low risk of recurrence after complete excision
• Excellent prognosis
CONTI..
• Grade II (Low-Grade Infiltrative Tumor)
• Grade II tumors are slow-growing but infiltrate normal spinal
cord tissue, making complete surgical removal more difficult.
• Characteristics
• Relatively slow-growing
• Invade nearby spinal cord tissue
• Higher chance of recurrence than Grade I
• May progress to a higher grade over time
CONTI..
• Grade III (High-Grade Malignant Tumor)
• Grade III tumors are Malignant & rapidly growing. They invade
surrounding tissue and are more likely to recur after treatment.
• Characteristics
• Rapid growth
• Significant invasion of spinal cord tissue
• Increased cell division (high mitotic activity)
• Requires surgery followed by radiotherapy and/or chemotherapy
• Moderate to poor prognosis
CONTI..
• Grade IV (Highly Malignant Tumor)
• Grade IV tumors are the most aggressive and malignant spinal cord tumors.
They grow rapidly, destroy surrounding tissue, and have the poorest
prognosis.
• Characteristics
• Very rapid growth
• Extensive invasion
• Tissue necrosis and abnormal blood vessel formation
• High risk of recurrence
• Poor survival despite treatment
CLINICAL MANIFESTATIONS
•Early Symptoms
•Persistent back or neck pain
•Pain worse at night
•Pain not relieved by rest
•Radiating pain to arms or legs
CONTI..
•Neurological Symptoms
•Muscle weakness
•Numbness or tingling
•Loss of sensation
•Difficulty walking
•Poor balance
•Muscle spasms
CONTI..
•Advanced Symptoms
•Paralysis
•Loss of bladder control
•Loss of bowel control
•Sexual dysfunction
DIAGNOSTIC EVALUATION
•History and Neurological Examination
•MRI with Contrast (Gold Standard)
•CT Scan Evaluates vertebral bone involvement and is
useful when MRI cannot be performed.
•CT Myelography Detects spinal cord or nerve root
compression when MRI is contraindicated.
CONTI..
•Biopsy
•CSF Examination
•PET-CT/Bone Scan Identifies metastatic disease and
helps locate the primary cancer.
•Blood Tests Includes CBC, liver and kidney function
tests, and other investigations to assess overall health
before treatment.
MANAGEMENT
•Tumor Resection (Tumor Excision)
•Tumor resection is the surgical removal of the spinal
cord tumor.
•The aim is to remove as much tumor as possible while
preserving neurological function.
CONTI..
•Depending on the tumor, the resection may be:
•Gross Total Resection (GTR): Complete removal of
all visible tumor.
•Subtotal Resection (STR): Partial removal when
complete excision may cause neurological damage.
CONTI..
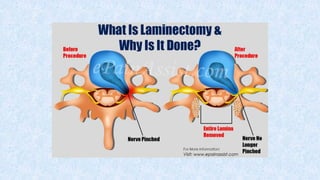
• Laminectomy
• Laminectomy is the removal of the lamina (posterior part
of the vertebral arch).
• It provides access to the spinal canal for tumor removal.
• It also relieves pressure on the spinal cord and nerve roots
caused by the tumor.
• This procedure is commonly performed for extradural and
intradural-extramedullary tumors.
CONTI..
•Laminoplasty
•Laminoplasty involves cutting and reconstructing the
lamina instead of removing it completely.
•It preserves spinal stability and reduces the risk of
postoperative spinal deformity.
•It is particularly useful in children and younger adults
requiring multilevel spinal surgery.
CONTI..
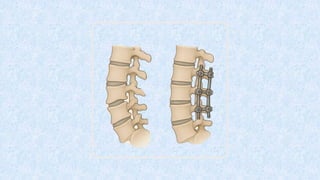
•Spinal Stabilization (Spinal Fusion)
•Spinal stabilization is performed when tumor removal
weakens the vertebral column.
•Metal screws, rods, plates, and bone grafts are used to
stabilize the spine.
•This procedure prevents spinal instability, deformity,
and pathological fractures while maintaining spinal
alignment.
CONTI..
• 2. Radiation Therapy
• Residual tumor after surgery
• Inoperable tumors
• Metastatic spinal tumors
• Pain relief
• Types
• External Beam Radiation Therapy (EBRT)
• Stereotactic Radiosurgery (CyberKnife) for selected lesions
CONTI..
• 3. Chemotherapy
• Used for tumors that are sensitive to anticancer drugs or when the
disease has spread.
• Common drugs
• Temozolomide (selected gliomas)
• Carboplatin
• Cisplatin
• Vincristine
• Etoposide
CONTI..
•4. Targeted Therapy
•Used when specific molecular targets are present.
•Examples
•Bevacizumab
•Imatinib (selected tumors)
CONTI..
•5. Immunotherapy
•Used only in selected advanced or metastatic cancers
involving the spine.
•Examples
•Pembrolizumab
•Nivolumab
SPINAL CORD TUMOR created by KIRAN K. KARETHA