SOURCES OF ERROR IN MEDICAL
LABORATORY INVESTIGATIONS
AND IT’S PREVENTION
PRE-ANALYTICAL
ANALYTICAL
POST-ANALYTICAL
by
JAMES A. HODEY
27TH JUNE, 2023
1
OUTLINE
• INTRODUCTION
• CLASSIFICATION OF PRE-ANALYTICAL VARIABLES
• OVERVIEW OF VARIABLES, THEIR EFFECTS AND
CORRECTIVE ACTIONS
• ANALYTICAL ERRORS
• POST ANALYTICAL ERRORS
• CONCLUSION
• REFERENCES
2
INTRODUCTION 1/4
• Medical Laboratory Service plays a pivotal role
in; diagnosis, clinical decision making, patient
management and follow-up, surveillance and
disease control, planning, monitoring and
evaluation, and budgeting.
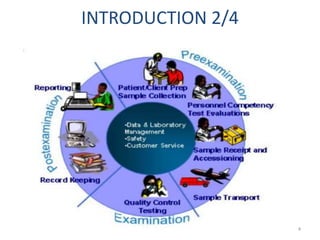
• Laboratory practice is divided into 3 phases
(pre-analytical, analytical and post-analytical) all
targeted for quality improvement.
• Total testing process begins with test Ordering,
Reporting of test results up to clinical decision
making, these encompasses the 3 phases. 3
INTRODUCTION 2/4
4
INTRODUCTION 3/4
• Laboratory errors as defined by Bonini et al. is
“a diagnosis that is missed, wrong, or delayed, as
detected by some subsequent definitive test or
finding”.
• This has been further acknowledged and
adopted by the ISO technical report 22367,
• as “ a defect occurring at any part of the
laboratory cycle, from ordering test to reporting,
interpreting and reacting to results”.
5
INTRODUCTION 4/4
• Among the phases, pre-analytical errors currently
accounts for about 75% of all the errors (Lippi et al;
Plebani and Carraro et al).
• Sadly, most activities in the pre-analytical phase is
neither performed entirely in the clinical laboratory
nor under the control of laboratory personnel,
hence difficult to monitor and improve.
• Most laboratories often leave pre-analytical
activities to other health care personnel who have
little to no formal training in Medical Laboratory
practice.
6
CLASSIFICATION OF PRE-ANALYTICAL
VARIABLES
• Pre-analytical processes includes all steps that
occur from test ordering until right before
sample analysis.
• Pre-analytical variables is classified into:
Controllable factors
Non-controllable factors
7
CONTROLLABLE FACTORS
• Request and test sample factors
• Physiological factors
Posture/Recumbency
Circadian variations
Physical fitness, exercise and Training
Travels
• Lifestyle factors
 Food and fasting state
Diet
Herbal preparations
Recreational substances
Stimulants
Drugs and medications 8
NON-CONTROLLABLE FACTORS
• Age
• Sex
• Race
• Environmental
• Medical conditions / co-morbidity
9
REQUEST AND TEST SAMPLE FACTORS 1/2
• Test ordering
• Patient identification
• Patient preparation
• Site selection and preparation
• Tourniquet Application and time
• Venipuncture Technique
• Use of appropriate sample bottles
• Order of draw
10
REQUEST AND TEST SAMPLE FACTORS 1/2
• Right / appropriate specimen
• Right / appropriate sample tube(s)
• Correct specimen volume
• Proper sample Handling and specimen processing
• Serum or plasma samples
• Centrifugation/ sample separation
• Proper handling of blood samples
• Stability and storage for whole Blood,
serum/plasma, stool, urine, CSF, Swabs, etc.
• Proper packaging and transport of specimen. 11
TEST ORDERING
• Filling of test request form. Test requisition form
should contain a min. of patient’s name, age, sex,
Hospital number, location, Prescribers name and
contact, clinical diagnosis and brief clinical
information including any initial treatment.
• Ordering of wrong test. This could be due to:
 Confusion over tests with similar names (such
as 25- hydroxyvitamin D vrs 1,25-
dihyroxyvitamin D).
Transcription errors and misinterpreted verbal
orders, which occurs when physicians do not
place test orders themselves. 12
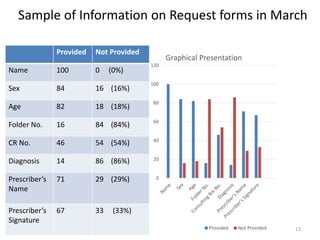
Sample of Information on Request forms in March
Provided Not Provided
Name 100 0 (0%)
Sex 84 16 (16%)
Age 82 18 (18%)
Folder No. 16 84 (84%)
CR No. 46 54 (54%)
Diagnosis 14 86 (86%)
Prescriber’s
Name
71 29 (29%)
Prescriber’s
Signature
67 33 (33%)
0
20
40
60
80
100
120
Graphical Presentation
Provided Not Provided 13
CORRECT SAMPLE BOTTLE AND SAMPLE
VOLUME
• Use of appropriate sample bottle as indicated for the
test to be carried out.
• Collect adequate sample quantity as labelled on tube,
unless in peculiar situations ,e.g. neonates.
• Use of the appropriate tube e.g pediatric tubes for
neonates and babies.
• Order of Draw;
• Blood culture
• Serum tubes
• Heparin tubes
• EDTA tubes
• Fluoride oxalate tubes
14
PROPER SAMPLE HANDLING AND
SPECIMEN PROCESSING
• No vigorous shaking of blood samples, avoid hemolysis.
• Gently rock blood tube to mix with anticoagulant.
• Samples collected into one type of tube should never be
transferred into another tube.
• If blood collection site is distant from the laboratory,
specimen should be collected into evacuated tubes
containing thixotropic polymer gel and should be
centrifuge on site.
• The gel forms an effective barrier between the
separated serum/plasma and cells, so that no leakage of
cellular constituent into the supernatant above the gel.
15
RIGHT SPECIMEN FROM APPROPRIATE SITE
• Plasma allows for more rapid processing of specimen
for clinical test.
• But anticoagulants may interfere with some analytical
methods E.g. K+ and phosphate.
• Type of urine specimen needed for different tests vary.
• Early morning urine for UPT and microscopic
examination of cells,
• Fresh urine for cytology,
• Collection of 24hrs urine for quantitative
measurement,
• Mid-stream urine for c/s
• Terminal urine for S. haematobium.
16
PHYSIOLOGICAL FACTORS 1/2
Prolong bed rest can dramatically affects body
constituents.
• Plasma volume and ECF vol. decrease within few
days
• Hematocrit increase by up to 10% .
• Creatinine kinase increases from muscle release.
• Plasma protein concentration reduces.
• Protein- bound constituents decreases.
• Serum potassium, reduces by 0.5mmol/L.
• Hydrogen ion excretion decreases.
17
PHYSIOLOGICAL FACTORS 2/2
• Calcium: Hypercalcemia, hypercalciuria , from
bone resorption
• The amplitude of circadian variation of cortisol is
reduced with prolonged immobilization.
• As a result some hospitalized patients should be
delay certain tests until after they leave the
hospital and resume normal activity.
• When an individual becomes active after a
period of bedrest, longer than 3 weeks is
required before calcium balance is achieved.
18
LIFESTYLE
DIET:
• Plasma urea conc. doubles, within 4 days of change
of diet to high protein diet, along with increase in
urinary excretion. Serum cholesterol, phosphate,
urate and NH3 conc. also increases concomitantly.
• A high fat diet increases serum TG conc., but depletes
the nitrogen pool because of nitrogen requirement
for excretion of ammonium ions to maintain acid-
base homeostasis.
• A high carbohydrate diet decreases the serum
concentrations of LDL- cholesterol, triglycerides,
cholesterol and protein. 19
FOOD AND FASTING STATE
• Food ingestion is a significant source of pre-
analytical variability. This effect varies based on
analyte and time between meal ingestion and
blood collection.
• e.g, glucose and TGs significantly increases after
meals with high carbohydrates and fat respectively.
• An overnight fasting period of 10 to 12 hours
prior to blood collection is optimal for minimizing
variations.
• Glugacon and insulin secretions are stimulated by
protein meal, and insulin alone is stimulated by
carbohydrate meal. 20
DRUGS
• Opiates– increases pancreatic enzymes
• Oral contraceptives– reduces HDL and increases
LDL
• Thiazides – Hypokalemia, hyperglycaemia,
hyperuricemia, prerenal azotemia, increased LDL-
Chol, total- Chol and TGs
• Phenytoin - Reduces calcium and phosphate
conc. (with risk of osteomalacia), increases ALP
activity and induces synthesis of Bilirubin
conjugating enzymes in the liver.
• Also causes hyperglycemia and glycosuria. 21
VENDOR SELECTION AND PROCUMENT
• Vendor qualification and selection
• Inspection of vendor premises for conditions of
Storage, Packaging and transport of reagents and
consumables.
• Use of GSA and FDA approved products
• Pre testing and validation of samples (before
award and acceptance during delivery)
• Verification, Stores receipt and acceptance
• Storage conditions in facility and stock taking
• Laboratory structural design and work flow
22
CORRECTIVE ACTION
• Correct and adequate information on request.
• Proper client preparation prior to sample collection.
• Education on proper sample tubes, order of draw and
blood to anticoagulant ratio.
• Proper sample storage, packaging and transport.
• Introduction and education on Sample acceptance
and rejection criteria manual.
• Development and introduction to laboratory
handbook.
• Laboratory's advice is sort and adhered to during
procurement. 23
ANALYTICAL ERRORS
1. Systemic error- indicates poor accuracy
 Poor calibration
 Incorrect procedure
 Wrong standard
2. Random errors- indicates poor precision
 Pipetting error
 Incorrect sample numbering
 Transcript error
 Reader fluctuation
2. Inherent errors
 Power fluctuations
 Machine precision errors
24
POST ANALYTICAL ERRORS
1.Data entry errors.
2.Hand written results
3.Verbal miscommunication of results
4.Reporting delays
5.Lapse in communicating critical results
6.Report issued but not used for immediate
clinical dicision
25
CONCLUSION
• Prevention of laboratory errors is a shared
responsibility, starting from the client, relations,
prescribers, nurses, laboratory staff, stores and
procurement, administration, accounts, orderlies
and all health workers.
• Actions to control laboratory error is a journey.
• Never relax or overlook it.
• Enjoy analyzing and implementing CAPA.
• This is the only way for continuous quality
improvement for better patient care.
26
REFERENCES
• Tietz Clinical Chemistry and Molecular
Diagnostics, 5th Ed.
• Bishops Clinical Chemistry- Principles, Techniques,
Correlations, 7th Ed
• Bonini P, Plebani, Cerrioti F, Rubboli F. Errors in
Laboratory medicine. Clin. Chem 2002:48:691-8.
• Carraro P, Plebani M. Errors in stat laboratory
Types and frequencies 10 years later. Clin Chem
2007:53:1338-42.
• Young DS. Effects of pre-analytical variables on
clinical laboratory tests. 3rd ed. Washington,
DC:AACCP Press, 2007. 27
28
THANKS FOR
YOUR ATTENTION
29