Sacro Iliac Joint Pain
(SI joint Pain)
Tasrif Hamdi
Study Program/Department of
Anesthesiology and Intensive Care, Faculty
of Medicine, Universitas Sumatera Utara /
RSUP H. Adam Malik, Indonesia, Medan
Prevalenceof SI Joint Pain
• Pain arising from the sacroiliac joint is one of the
important causes of axial low back pain.
• Overall, about 85% of people will experience low back
pain at some point in their lifetime.
• Among these patients, approximately 25% have low back
pain that primarily originates from the sacroiliac joint.
Anatomy
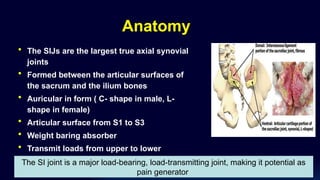
• The SIJs are the largest true axial synovial
joints
• Formed between the articular surfaces of
the sacrum and the ilium bones
• Auricular in form ( C- shape in male, L-
shape in female)
• Articular surface from S1 to S3
• Weight baring absorber
• Transmit loads from upper to lower
The SI joint is a major load-bearing, load-transmitting joint, making it potential as
pain generator
Composition of the SIJ
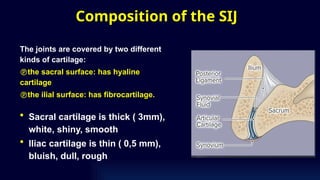
The joints are covered by two different
kinds of cartilage:
the sacral surface: has hyaline
cartilage
the ilial surface: has fibrocartilage.
• Sacral cartilage is thick ( 3mm),
white, shiny, smooth
• Iliac cartilage is thin ( 0,5 mm),
bluish, dull, rough
LIGAMENTS
Sacroiliac joint stability is primarily provided by strong ligamentous support rather than joint motion.
These ligaments create a self-locking mechanism
Ligament weakness increases mechanical stress on the SI joint, leading to inflammation, pain, and early
degeneration
SI JOINT MUSCLE
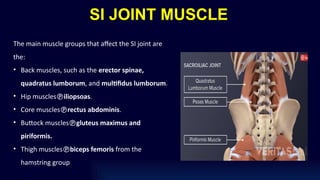
The main muscle groups that affect the SI joint are
the:
• Back muscles, such as the erector spinae,
quadratus lumborum, and multifidus lumborum.
• Hip musclesiliopsoas.
• Core musclesrectus abdominis.
• Buttock musclesgluteus maximus and
piriformis.
• Thigh musclesbiceps femoris from the
hamstring group
Muscle and Ligaments
• SI joint pain is not always purely a “joint” problem, often
influenced by muscle and ligament problems around the
pelvis and core.
• Imbalance can increase mechanical stressPain
Innervation
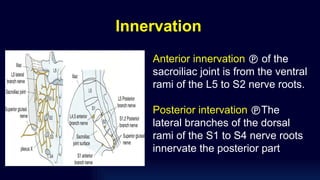
Anterior innervation  of the
sacroiliac joint is from the ventral
rami of the L5 to S2 nerve roots.
Posterior intervation The
lateral branches of the dorsal
rami of the S1 to S4 nerve roots
innervate the posterior part
Etiology
The traumatic causes of pain are:
• Pelvic ring fractures,
• Soft tissue injury from fall onto
the buttock
• Indirect injury from motor
vehicle collision and
• Sudden / repeated heavy
lifting/strain or torsion
The atraumatic causes
• Spondyloarthropathy
• Enthesopathy
• Osteoarthritis
• Infection
• Previous lumbar fusion
• Pregnancy
• Leg length discrepancy and
• Scoliosis.
Pathophysiology
• The SI joint is a large joint designed to bear weight,
not to move.
• When the load is uneven or the surrounding muscles
are not working properly, the joint and its ligaments
can easily become irritated and cause pain, even
though the joint itself moves very little.
• due to poor posture, leg-length differences,
pregnancy, or weak and tight muscles the joint and
its ligaments can become irritatedPain.
Diagnosis
• History
• Physical examination
• Additional tests
• Differential diagnosis
Pain radiation
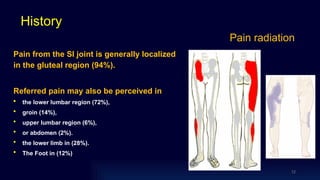
Pain from the SI joint is generally localized
in the gluteal region (94%).
Referred pain may also be perceived in
• the lower lumbar region (72%),
• groin (14%),
• upper lumbar region (6%),
• or abdomen (2%).
• the lower limb in (28%).
• The Foot in (12%)
12
History
Pain History
Aggravating
• Sitting
• Sit to stand
• Prolonged walking
• Stairs
• Rolling on to affected side
Relieving
• Lying on unaffected side
• Weight bearing on unaffected
side
Physical Examination and provocative maneuvers
(clinical tests)
The 7 most important clinical tests which are
positive when patient has typical SI joint pain:
1. Compression test (approximation test):
2. Distraction test (gapping test):
3. Patrick’s sign (flexion abduction external rotation test):
4. Gaenslen test (pelvic torsion test):
5. Thigh thrust test (posterior shear test):
6. Fortin’s finger test:
7. Gillet test:
14
Compression test
• The patient lies on the side with hips
and knees flexed to about a right
angle.
• The examiner applies a force
vertically downward on the
uppermost iliac crest.
• The presumed action is a
compression force to both SIJs
Distraction test
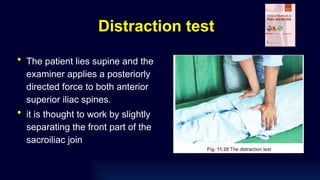
• The patient lies supine and the
examiner applies a posteriorly
directed force to both anterior
superior iliac spines.
• it is thought to work by slightly
separating the front part of the
sacroiliac join
Faber’s test or Patrick’s sign
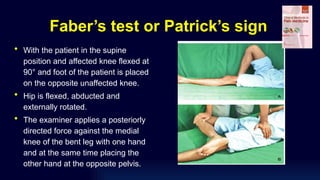
• With the patient in the supine
position and affected knee flexed at
90° and foot of the patient is placed
on the opposite unaffected knee.
• Hip is flexed, abducted and
externally rotated.
• The examiner applies a posteriorly
directed force against the medial
knee of the bent leg with one hand
and at the same time placing the
other hand at the opposite pelvis.
Gaenslen’s Test
• The patient lies supine on the
exam table.
• Flex the contralateral hip and knee
towards the patient's chest while
the opposite leg is allowed to drop
off the table's side.
• Pain in the sacroiliac joint region of
the lowered leg suggests sacroiliac
joint dysfunction.
Thigh thrust test
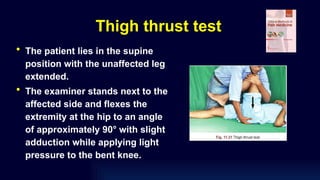
• The patient lies in the supine
position with the unaffected leg
extended.
• The examiner stands next to the
affected side and flexes the
extremity at the hip to an angle
of approximately 90° with slight
adduction while applying light
pressure to the bent knee.
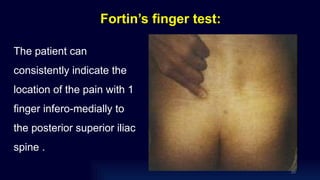
Fortin’s finger test:
The patient can
consistently indicate the
location of the pain with 1
finger infero-medially to
the posterior superior iliac
spine .
20
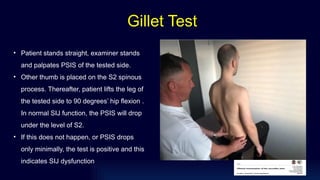
• Patient stands straight, examiner stands
and palpates PSIS of the tested side.
• Other thumb is placed on the S2 spinous
process. Thereafter, patient lifts the leg of
the tested side to 90 degrees’ hip flexion .
In normal SIJ function, the PSIS will drop
under the level of S2.
• If this does not happen, or PSIS drops
only minimally, the test is positive and this
indicates SIJ dysfunction.
Gillet Test
Positive of SIJ Pain
Investigation; Medical Imaging
23
Abnormal imaging does not necessarily mean the SI joint is the source
of pain, and normal imaging does not exclude SI joint pain.
The gold standard
for confirmation of pain generator in BACK PAIN
Diagnostic Block/Intervention
What if we are in doubt about
the diagnosis?”
Diagnostic injection
According to the IASP criteria, the diagnosis of sacroiliac joint pain can only
be confirmed if the pain disappears after an intra-articular SI joint injection
with a local anesthetic.
Potential causes of inaccurate blocks include
• The local anesthetic may spread to nearby pain-generating structures such
as muscles, ligaments, or nerve roots, leading to false-positive results.
• Excessive use of superficial anesthesia or sedation can also mask the
patient’s pain response.
• failure to adequately infiltrate the entire SI joint complex may result in
false-negative findings.
25
IASP criteria for diagnosing SI joint
pain
• Pain present in the region of
the SIJ
• +ve Clinical SI joint stress
tests (painful).
• +ve diagnostic interventional
procedure (completely
relieves the pain)
26
IASP International Association for the Study of Pain
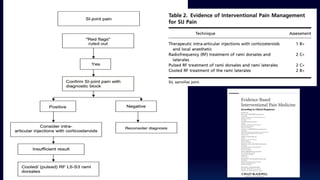
Algorithm for diagnosis of LBP
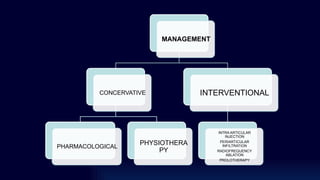
MANAGEMENT
CONCERVATIVE
PHARMACOLOGICAL
PHYSIOTHERA
PY
INTERVENTIONAL
INTRA ARTICULAR
INJECTION
PERIARTICULAR
INFILTRATION
RADIOFREQUENCY
ABLATION
PROLOTHERAPY
CONCLUSION
• SI joint is a very common cause of low back pain, particularly in
elderly patients.
• Clinically, the symptoms are often very similar to other causes of
low back pain, which makes diagnosis challenging.
• Therefore, it is important to first rule out red flag conditions, as
well as other diseases such as ankylosing spondylitis.
• Special provocation tests and diagnostic interventions are the
most important tools to achieve an accurate diagnosis.
Sacroiliac Joint Pain: Clinical Diagnosis, Provocation Tests, and SI Joint Block by Dr Hamdi