Role of Chemotherapy, Targeted therapy and
Immunotherapy in treatment of Non-Small Cell Lung
cancer (NSCLC) (Part II)
Mohammed Fathy Bayomy, MSc, MD
Lecturer
Clinical Oncology & Nuclear Medicine
Faculty of Medicine
Zagazig University
Treatment of ALK Translocation–Positive NSCLC
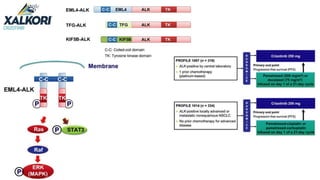
ALK Rearrangement: Context
 Found in ~ 5% of NSCLC patients[1]
 Occurs more frequently in younger patients, light or never-smokers,
males, and those with the adenocarcinoma subtype[1,2]
 Predominantly a fusion of ALK with partner oncogenes, particularly
EML4[3]
 Occurs in similar subgroups as patients with EGFR mutations, but EGFR
mutations and ALK rearrangements are predominantly mutually
exclusive[1-4]
1. American Cancer Society. Targeted therapy drugs for non-small cell lung cancer. 2. Shaw.
J Clin Oncol. 2009;27:4247. 3. Hofman. Cancers (Basel). 2017;9:107. 4. Soda. Nature. 2007;448:561.
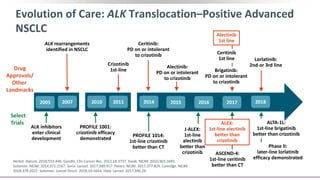
Alectinib:
PD on or intolerant
to crizotinib
ALTA-1L:
1st-line brigatinib
better than crizotinib
J-ALEX:
1st-line
alectinib
better than
crizotinib ASCEND-4:
1st-line ceritinib
better than CT
ALK rearrangements
identified in NSCLC
Evolution of Care: ALK Translocation–Positive Advanced
NSCLC
PROFILE 1001:
crizotinib efficacy
demonstrated
2007 2010 2011 2014 2015 2018
Herbst. Nature. 2018;553:446. Gandhi. Clin Cancer Res. 2012;18:3737. Kwak. NEJM. 2010;363:1693.
Solomon. NEJM. 2014;371:2167. Soria. Lancet. 2017;389:917. Peters. NEJM. 2017;377:829. Camidge. NEJM.
2018;379:2027. Solomon. Lancet Oncol. 2018;19:1654. Hida. Lancet. 2017;390.29.
Drug
Approvals/
Other
Landmarks
Select
Trials
Ceritinib
1st line
ALEX:
1st-line alectinib
better than
crizotinib
2017
PROFILE 1014:
1st-line crizotinib
better than CT
2016
Crizotinib
1st-line
Alectinib
1st line
Brigatinib:
PD on or intolerant
to crizotinib
Ceritinib:
PD on or intolerant
to crizotinib
Phase II:
later-line lorlatinib
efficacy demonstrated
ALK inhibitors
enter clinical
development
2005
Lorlatinib:
2nd or 3rd line
First-line Treatment With ALK Inhibitors in ALK-
Rearranged NSCLC: Phase III Trials
 Alectinib, crizotinib, and ceritinib are FDA approved for newly
diagnosed ALK+, metastatic NSCLC[6-8]
1. Solomon. NEJM. 2014;371:2167. 2. Soria. Lancet. 2017;389: 917. 3. Hida. Lancet. 2017;390:29.
4. Peters. NEJM. 2017;377:829. 5. Camidge. NEJM. 2018;[Epub]. 6. Crizotinib PI. 7. Ceritinib PI. 7. Alectinib PI.
Agent/Study N Study Design ORR, % Median PFS, Mos
Crizotinib
 PROFILE 1014[1] 343
Crizotinib vs
pemetrexed + cis or carbo 74 vs 45 10.9 vs 7.0
Ceritinib
 ASCEND-4[2] 376
Ceritinib vs
pemetrexed + cis or carbo 72.5 vs 26.7 16.6 vs 8.1
Alectinib
 J-ALEX[3]
 ALEX[4]
207
303
Alectinib vs crizotinib
92 vs 79
82.9 vs 75.5
NR vs 10.2
NR vs 11.1
Brigatinib
 ALTA-1L[5] 275 Brigatinib vs crizotinib 71 vs 60 NR vs 9.8
First-line ALK Translocation–Positive NSCLC
 Alectinib is preferred treatment in this setting
‒ Effective in patients with CNS metastases and leptomeningeal disease
 Biomarker testing for all patients with newly diagnosed nonsquamous
NSCLC is essential
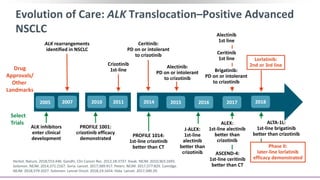
Alectinib:
PD on or intolerant
to crizotinib
ALTA-1L:
1st-line brigatinib
better than crizotinib
J-ALEX:
1st-line
alectinib
better than
crizotinib ASCEND-4:
1st-line ceritinib
better than CT
ALK rearrangements
identified in NSCLC
Evolution of Care: ALK Translocation–Positive Advanced
NSCLC
PROFILE 1001:
crizotinib efficacy
demonstrated
2007 2010 2011 2014 2015 2018
Herbst. Nature. 2018;553:446. Gandhi. Clin Cancer Res. 2012;18:3737. Kwak. NEJM. 2010;363:1693.
Solomon. NEJM. 2014;371:2167. Soria. Lancet. 2017;389:917. Peters. NEJM. 2017;377:829. Camidge.
NEJM. 2018;379:2027. Solomon. Lancet Oncol. 2018;19:1654. Hida. Lancet. 2017;390.29.
Drug
Approvals/
Other
Landmarks
Select
Trials
Ceritinib
1st line
ALEX:
1st-line alectinib
better than
crizotinib
2017
PROFILE 1014:
1st-line crizotinib
better than CT
2016
Crizotinib
1st-line
Alectinib
1st line
Brigatinib:
PD on or intolerant
to crizotinib
Ceritinib:
PD on or intolerant
to crizotinib
Phase II:
later-line lorlatinib
efficacy demonstrated
ALK inhibitors
enter clinical
development
2005
Lorlatinib:
2nd or 3rd line
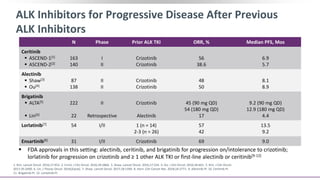
ALK Inhibitors for Progressive Disease After Previous
ALK Inhibitors
1. Kim. Lancet Oncol. 2016;17:452. 2. Crinò. J Clin Oncol. 2016;34:2866. 3. Shaw. Lancet Oncol. 2016;17:234. 4. Ou. J Clin Oncol. 2016;34:661. 5. Kim. J Clin Oncol.
2017;35:2490. 6. Lin. J Thorac Oncol. 2018;[Epub]. 7. Shaw. Lancet Oncol. 2017;18:1590. 8. Horn. Clin Cancer Res. 2018;24:2771. 9. Alectinib PI. 10. Ceritinib PI.
11. Brigatinib PI. 12. Lorlatinib PI.
N Phase Prior ALK TKI ORR, % Median PFS, Mos
Ceritinib
 ASCEND-1[1]
 ASCEND-2[2]
163
140
I
II
Crizotinib
Crizotinib
56
38.6
6.9
5.7
Alectinib
 Shaw[3]
 Ou[4]
87
138
II
II
Crizotinib
Crizotinib
48
50
8.1
8.9
Brigatinib
 ALTA[5]
 Lin[6]
222
22
II
Retrospective
Crizotinib
Alectinib
45 (90 mg QD)
54 (180 mg QD)
17
9.2 (90 mg QD)
12.9 (180 mg QD)
4.4
Lorlatinib[7] 54 I/II 1 (n = 14)
2-3 (n = 26)
57
42
13.5
9.2
Ensartinib[8] 31 I/II Crizotinib 69 9.0
 FDA approvals in this setting: alectinib, ceritinib, and brigatinib for progression on/intolerance to crizotinib;
lorlatinib for progression on crizotinib and ≥ 1 other ALK TKI or first-line alectinib or ceritinib[9-12]
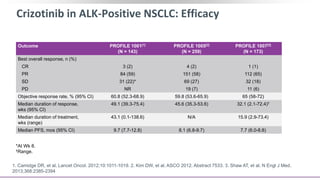
Crizotinib in ALK-Positive NSCLC: Efficacy
1. Camidge DR, et al. Lancet Oncol. 2012;10:1011-1019. 2. Kim DW, et al. ASCO 2012. Abstract 7533. 3. Shaw AT, et al. N Engl J Med.
2013;368:2385-2394
*At Wk 8.
†Range.
Outcome PROFILE 1001[1]
(N = 143)
PROFILE 1005[2]
(N = 259)
PROFILE 1007[3]
(N = 173)
Best overall response, n (%)
CR 3 (2) 4 (2) 1 (1)
PR 84 (59) 151 (58) 112 (65)
SD 31 (22)* 69 (27) 32 (18)
PD NR 19 (7) 11 (6)
Objective response rate, % (95% CI) 60.8 (52.3-68.9) 59.8 (53.6-65.9) 65 (58-72)
Median duration of response,
wks (95% CI)
49.1 (39.3-75.4) 45.6 (35.3-53.6) 32.1 (2.1-72.4)†
Median duration of treatment,
wks (range)
43.1 (0.1-138.6) N/A 15.9 (2.9-73.4)
Median PFS, mos (95% CI) 9.7 (7.7-12.8) 8.1 (6.8-9.7) 7.7 (6.0-8.8)
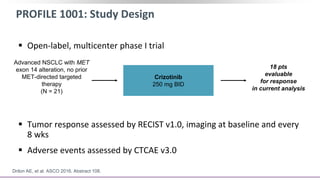
PROFILE 1001: Study Design
 Open-label, multicenter phase I trial
 Tumor response assessed by RECIST v1.0, imaging at baseline and every
8 wks
 Adverse events assessed by CTCAE v3.0
Advanced NSCLC with MET
exon 14 alteration, no prior
MET-directed targeted
therapy
(N = 21)
Crizotinib
250 mg BID
Drilon AE, et al. ASCO 2016. Abstract 108.
18 pts
evaluable
for response
in current analysis
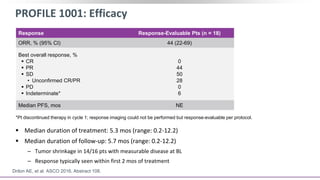
PROFILE 1001: Efficacy
 Median duration of treatment: 5.3 mos (range: 0.2-12.2)
 Median duration of follow-up: 5.7 mos (range: 0.2-12.2)
‒ Tumor shrinkage in 14/16 pts with measurable disease at BL
‒ Response typically seen within first 2 mos of treatment
Drilon AE, et al. ASCO 2016. Abstract 108.
*Pt discontinued therapy in cycle 1; response imaging could not be performed but response-evaluable per protocol.
Response Response-Evaluable Pts (n = 18)
ORR, % (95% CI) 44 (22-69)
Best overall response, %
 CR
 PR
 SD
• Unconfirmed CR/PR
 PD
 Indeterminate*
0
44
50
28
0
6
Median PFS, mos NE
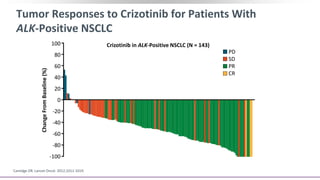
Tumor Responses to Crizotinib for Patients With
ALK-Positive NSCLC
Camidge DR. Lancet Oncol. 2012;1011-1019.
Crizotinib in ALK-Positive NSCLC (N = 143)100
80
60
40
20
0
-20
-40
-60
-80
-100
ChangeFromBaseline(%)
PD
SD
PR
CR
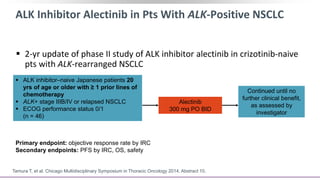
ALK Inhibitor Alectinib in Pts With ALK-Positive NSCLC
 2-yr update of phase II study of ALK inhibitor alectinib in crizotinib-naive
pts with ALK-rearranged NSCLC
Tamura T, et al. Chicago Multidisciplinary Symposium in Thoracic Oncology 2014. Abstract 10.
 ALK inhibitor–naive Japanese patients 20
yrs of age or older with ≥ 1 prior lines of
chemotherapy
 ALK+ stage IIIB/IV or relapsed NSCLC
 ECOG performance status 0/1
(n = 46)
Alectinib
300 mg PO BID
Continued until no
further clinical benefit,
as assessed by
investigator
Primary endpoint: objective response rate by IRC
Secondary endpoints: PFS by IRC, OS, safety
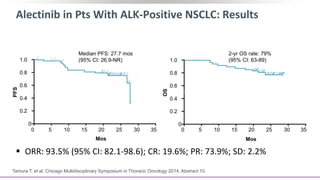
Alectinib in Pts With ALK-Positive NSCLC: Results
 ORR: 93.5% (95% CI: 82.1-98.6); CR: 19.6%; PR: 73.9%; SD: 2.2%
Tamura T, et al. Chicago Multidisciplinary Symposium in Thoracic Oncology 2014. Abstract 10.
1.0
0.8
0.6
0.4
0.2
0
0 5 10 15 20 25 30 35
Mos
PFS
Median PFS: 27.7 mos
(95% CI: 26.9-NR) 1.0
0.8
0.6
0.4
0.2
0
0 5 10 15 20 25 30 35
Mos
OS
2-yr OS rate: 79%
(95% CI: 63-89)
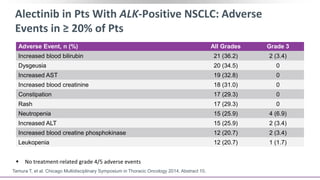
Alectinib in Pts With ALK-Positive NSCLC: Adverse
Events in ≥ 20% of Pts
 No treatment-related grade 4/5 adverse events
Tamura T, et al. Chicago Multidisciplinary Symposium in Thoracic Oncology 2014. Abstract 10.
Adverse Event, n (%) All Grades Grade 3
Increased blood bilirubin 21 (36.2) 2 (3.4)
Dysgeusia 20 (34.5) 0
Increased AST 19 (32.8) 0
Increased blood creatinine 18 (31.0) 0
Constipation 17 (29.3) 0
Rash 17 (29.3) 0
Neutropenia 15 (25.9) 4 (6.9)
Increased ALT 15 (25.9) 2 (3.4)
Increased blood creatine phosphokinase 12 (20.7) 2 (3.4)
Leukopenia 12 (20.7) 1 (1.7)
Alectinib in Pts With ALK-Positive NSCLC: Conclusions
 Alectinib effective and safe in progressive ALK inhibitor–naive ALK+ NSCLC
– ORR: 93.5%
– Median PFS: 27.7 mos (95% CI: 26.9-NR)
– PFS unaffected by baseline brain metastases
– No treatment-related grade 4/5 AEs; 3.4% had grade 3 AST/ALT elevation
– 31/46 patients progression free and remain on treatment
 Alectinib may offer a new therapeutic option for ALK+ NSCLC pts
– Ongoing phase III J-ALEX study aims to confirm phase II results
– Other phase II and III studies are evaluating alectinib in a wider population
Tamura T, et al. Chicago Multidisciplinary Symposium in Thoracic Oncology 2014. Abstract 10.
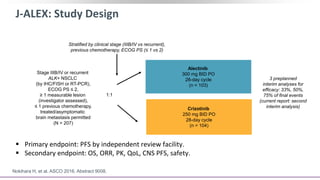
J-ALEX: Study Design
Alectinib
300 mg BID PO
28-day cycle
(n = 103)
Crizotinib
250 mg BID PO
28-day cycle
(n = 104)
Stage IIIB/IV or recurrent
ALK+ NSCLC
(by IHC/FISH or RT-PCR),
ECOG PS ≤ 2,
≥ 1 measurable lesion
(investigator assessed),
≤ 1 previous chemotherapy,
treated/asymptomatic
brain metastasis permitted
(N = 207)
Stratified by clinical stage (IIIB/IV vs recurrent),
previous chemotherapy, ECOG PS (≤ 1 vs 2)
1:1
Nokihara H, et al. ASCO 2016. Abstract 9008.
3 preplanned
interim analyses for
efficacy: 33%, 50%,
75% of final events
(current report: second
interim analysis)
 Primary endpoint: PFS by independent review facility.
 Secondary endpoint: OS, ORR, PK, QoL, CNS PFS, safety.
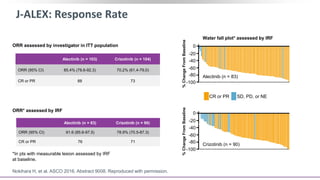
J-ALEX: Response Rate
Nokihara H, et al. ASCO 2016. Abstract 9008. Reproduced with permission.
ORR* assessed by IRF
ORR assessed by investigator in ITT population
*In pts with measurable lesion assessed by IRF at baseline.
0
-20
-40
-60
-80
-100
0
-20
-40
-60
-80
-100
Water fall plot* assessed by IRF
%ChangeFromBaseline%ChangeFromBaseline
0
-20
-40
-60
-80
-100
0
-20
-40
-60
-80
-100
Crizotinib (n = 90)
Alectinib (n = 83)
Water fall plot* assessed by IRF
%ChangeFromBaseline%ChangeFromBaseline
CR or PR SD, PD, or NE
ORR* assessed by IRF
ORR assessed by investigator in ITT population
*In pts with measurable lesion assessed by IRF
at baseline.
Alectinib (n = 103) Crizotinib (n = 104)
ORR (95% CI) 85.4% (78.6-92.3) 70.2% (61.4-79.0)
CR or PR 88 73
Alectinib (n = 83) Crizotinib (n = 90)
ORR (95% CI) 91.6 (85.6-97.5) 78.9% (70.5-87.3)
CR or PR 76 71
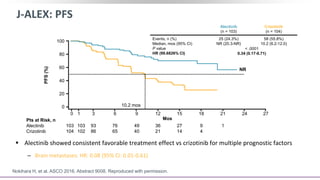
J-ALEX: PFS
 Alectinib showed consistent favorable treatment effect vs crizotinib for multiple prognostic factors
– Brain metastases: HR: 0.08 (95% CI: 0.01-0.61)
Nokihara H, et al. ASCO 2016. Abstract 9008. Reproduced with permission.
6
60
100
80
40
20
0
272421181512930 1
Mos
76
65
19
4
27
14
36
21
49
40
93
86
103
104
103
102
10.2 mos
PFS(%)
Pts at Risk, n
Alectinib
Crizotinib
Events, n (%)
Median, mos (95% CI)
P value
HR (99.6826% CI)
25 (24.3%)
NR (20.3-NR)
58 (55.8%)
10.2 (8.2-12.0)
< .0001
0.34 (0.17-0.71)
Alectinib
(n = 103)
Crizotinib
(n = 104)
NR
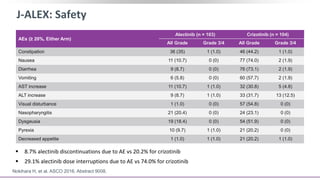
J-ALEX: Safety
 8.7% alectinib discontinuations due to AE vs 20.2% for crizotinib
 29.1% alectinib dose interruptions due to AE vs 74.0% for crizotinib
Nokihara H, et al. ASCO 2016. Abstract 9008.
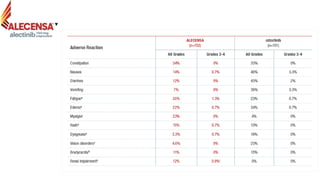
AEs (≥ 20%, Either Arm)
Alectinib (n = 103) Crizotinib (n = 104)
All Grade Grade 3/4 All Grade Grade 3/4
Constipation 36 (35) 1 (1.0) 46 (44.2) 1 (1.0)
Nausea 11 (10.7) 0 (0) 77 (74.0) 2 (1.9)
Diarrhea 9 (8.7) 0 (0) 76 (73.1) 2 (1.9)
Vomiting 6 (5.8) 0 (0) 60 (57.7) 2 (1.9)
AST increase 11 (10.7) 1 (1.0) 32 (30.8) 5 (4.8)
ALT increase 9 (8.7) 1 (1.0) 33 (31.7) 13 (12.5)
Visual disturbance 1 (1.0) 0 (0) 57 (54.8) 0 (0)
Nasopharyngitis 21 (20.4) 0 (0) 24 (23.1) 0 (0)
Dysgeusia 19 (18.4) 0 (0) 54 (51.9) 0 (0)
Pyrexia 10 (9.7) 1 (1.0) 21 (20.2) 0 (0)
Decreased appetite 1 (1.0) 1 (1.0) 21 (20.2) 1 (1.0)
ALEX: Alectinib vs Crizotinib in Untreated ALK-Positive
NSCLC
 Randomized, open-label phase III trial
Peters. NEJM. 2017;377:829.
 Primary endpoint: investigator-assessed PFS
 Secondary and other endpoints: IRC-assessed PFS, time to CNS progression, response, OS,
safety
Patients with advanced ALK-positive
NSCLC, ECOG PS 0-2, no prior
systemic tx for advanced NSCLC,
measurable disease, asymptomatic
brain or leptomeningeal mets
permitted, CNS RT permitted if
≥ 14 days before enrollment
(N = 303)
Until PD, unacceptable
toxicity, or withdrawal;
no crossover permitted*
Alectinib 600 mg BID PO
(n = 152)
Crizotinib 250 mg BID PO
(n = 151)
Stratified by ECOG PS (0/1 vs 2), race
(Asian vs non-Asian), CNS mets (yes vs no)
*Patients in crizotinib arm may have received alectinib after PD in countries where alectinib available.
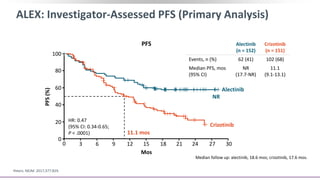
ALEX: Investigator-Assessed PFS (Primary Analysis)
Peters. NEJM. 2017;377:829.
Mos
Median follow up: alectinib, 18.6 mos; crizotinib, 17.6 mos.
Alectinib
(n = 152)
Crizotinib
(n = 151)
Events, n (%) 62 (41) 102 (68)
Median PFS, mos
(95% CI)
NR
(17.7-NR)
11.1
(9.1-13.1)
HR: 0.47
(95% CI: 0.34-0.65;
P < .0001)
PFS
PFS(%)
0
20
40
60
80
100
0 3 6 9 12 15 18 21 24 27 30
11.1 mos
Alectinib
NR
Crizotinib
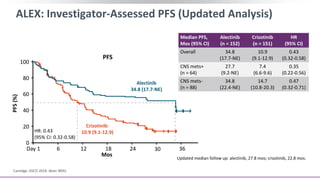
ALEX: Investigator-Assessed PFS (Updated Analysis)
Camidge. ASCO 2018. Abstr 9043.
HR: 0.43
(95% CI: 0.32-0.58)
Alectinib
34.8 (17.7-NE)
Crizotinib:
10.9 (9.1-12.9)
Median PFS,
Mos (95% CI)
Alectinib
(n = 152)
Crizotinib
(n = 151)
HR
(95% CI)
Overall 34.8
(17.7-NE)
10.9
(9.1-12.9)
0.43
(0.32-0.58)
CNS mets+
(n = 64)
27.7
(9.2-NE)
7.4
(6.6-9.6)
0.35
(0.22-0.56)
CNS mets-
(n = 88)
34.8
(22.4-NE)
14.7
(10.8-20.3)
0.47
(0.32-0.71)
PFS
Updated median follow up: alectinib, 27.8 mos; crizotinib, 22.8 mos.
PFS(%)
Mos
100
80
60
40
20
0
Day 1 12 18 24 36306
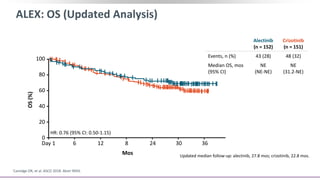
ALEX: OS (Updated Analysis)
OS(%)
Mos
Camidge DR, et al. ASCO 2018. Abstr 9043.
Alectinib
(n = 152)
Crizotinib
(n = 151)
Events, n (%) 43 (28) 48 (32)
Median OS, mos
(95% CI)
NE
(NE-NE)
NE
(31.2-NE)
HR: 0.76 (95% CI: 0.50-1.15)
Updated median follow-up: alectinib, 27.8 mos; crizotinib, 22.8 mos.
Day 1 6 12 8 24 30 36
100
80
60
40
20
0
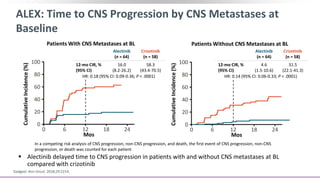
ALEX: Time to CNS Progression by CNS Metastases at
Baseline
 Alectinib delayed time to CNS progression in patients with and without CNS metastases at BL
compared with crizotinib
Patients With CNS Metastases at BL Patients Without CNS Metastases at BL
Gadgeel. Ann Oncol. 2018;29:2214.
CumulativeIncidence(%)
Mos
Alectinib
(n = 64)
Crizotinib
(n = 58)
12-mo CIR, %
(95% CI)
16.0
(8.2-26.2)
58.3
(43.4-70.5)
Alectinib
(n = 64)
Crizotinib
(n = 58)
12-mo CIR, %
(95% CI)
4.6
(1.5-10.6)
31.5
(22.1-41.3)
HR: 0.18 (95% CI: 0.09-0.36; P < .0001) HR: 0.14 (95% CI: 0.06-0.33; P < .0001)
In a competing risk analysis of CNS progression, non-CNS progression, and death, the first event of CNS progression, non-CNS
progression, or death was counted for each patient
6 12 18 24
100
80
60
40
20
0
0
CumulativeIncidence(%)
Mos
6 12 18 24
100
80
60
40
20
0
0
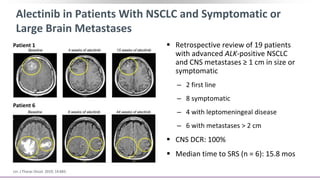
Alectinib in Patients With NSCLC and Symptomatic or
Large Brain Metastases
 Retrospective review of 19 patients
with advanced ALK-positive NSCLC
and CNS metastases ≥ 1 cm in size or
symptomatic
‒ 2 first line
‒ 8 symptomatic
‒ 4 with leptomeningeal disease
‒ 6 with metastases > 2 cm
 CNS DCR: 100%
 Median time to SRS (n = 6): 15.8 mos
Lin. J Thorac Oncol. 2019; 14:683.
Patient 1
Patient 6
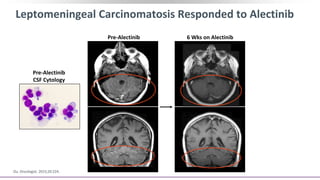
Pre-Alectinib 6 Wks on Alectinib
Pre-Alectinib
CSF Cytology
Leptomeningeal Carcinomatosis Responded to Alectinib
Ou. Oncologist. 2015;20:224.
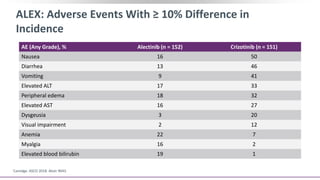
ALEX: Adverse Events With ≥ 10% Difference in
Incidence
AE (Any Grade), % Alectinib (n = 152) Crizotinib (n = 151)
Nausea 16 50
Diarrhea 13 46
Vomiting 9 41
Elevated ALT 17 33
Peripheral edema 18 32
Elevated AST 16 27
Dysgeusia 3 20
Visual impairment 2 12
Anemia 22 7
Myalgia 16 2
Elevated blood bilirubin 19 1
Camidge. ASCO 2018. Abstr 9043.
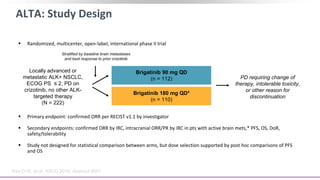
ALTA: Study Design
 Randomized, multicenter, open-label, international phase II trial
 Primary endpoint: confirmed ORR per RECIST v1.1 by investigator
 Secondary endpoints: confirmed ORR by IRC, intracranial ORR/PR by IRC in pts with active brain mets,* PFS, OS, DoR,
safety/tolerability
 Study not designed for statistical comparison between arms, but dose selection supported by post hoc comparisons of PFS
and OS
Locally advanced or
metastatic ALK+ NSCLC,
ECOG PS ≤ 2, PD on
crizotinib, no other ALK-
targeted therapy
(N = 222)
PD requiring change of
therapy, intolerable toxicity,
or other reason for
discontinuation
Brigatinib 90 mg QD
(n = 112)
Brigatinib 180 mg QD*
(n = 110)
Kim D-W, et al. ASCO 2016. Abstract 9007.
*After 7-day lead-in at 90 mg.
Stratified by baseline brain metastases
and best response to prior crizotinib
*Lesions with no previous RT or investigator-assessed PD after prior RT.
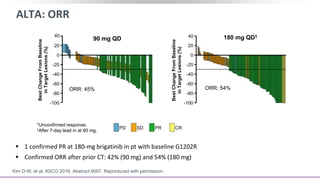
ALTA: ORR
 1 confirmed PR at 180-mg brigatinib in pt with baseline G1202R
 Confirmed ORR after prior CT: 42% (90 mg) and 54% (180 mg)
Kim D-W, et al. ASCO 2016. Abstract 9007. Reproduced with permission.
*Unconfirmed response.
†After 7-day lead in at 90 mg.
ORR: 45% ORR: 54%
90 mg QD 180 mg QD†
20
0
-20
-40
-60
-80
-100
BestChangeFromBaseline
inTargetLesions(%)
* *
20
0
-20
-40
-60
-80
-100
*
*
PD SD PR CR
BestChangeFromBaseline
inTargetLesions(%)
40 40
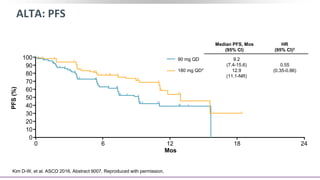
ALTA: PFS
Kim D-W, et al. ASCO 2016. Abstract 9007. Reproduced with permission.
*After 7-day lead in at 90 mg.
†Post hoc analysis, not designed to compare arms statistically.
Mos
240 6 12 18
PFS(%)
100
90
80
70
60
50
40
30
20
10
0
90 mg QD
180 mg QD*
Median PFS, Mos
(95% CI)
HR
(95% CI)†
9.2
(7.4-15.6)
12.9
(11.1-NR)
0.55
(0.35-0.86)
ALTA: Adverse Events
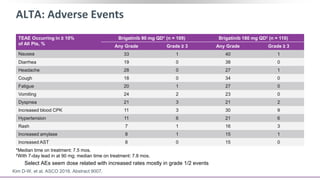
Kim D-W, et al. ASCO 2016. Abstract 9007.
*Median time on treatment: 7.5 mos.
†With 7-day lead in at 90 mg; median time on treatment: 7.8 mos.
 Select AEs seem dose related with increased rates mostly in grade 1/2 events
TEAE Occurring in ≥ 10%
of All Pts, %
Brigatinib 90 mg QD* (n = 109) Brigatinib 180 mg QD† (n = 110)
Any Grade Grade ≥ 3 Any Grade Grade ≥ 3
Nausea 33 1 40 1
Diarrhea 19 0 38 0
Headache 28 0 27 1
Cough 18 0 34 0
Fatigue 20 1 27 0
Vomiting 24 2 23 0
Dyspnea 21 3 21 2
Increased blood CPK 11 3 30 9
Hypertension 11 6 21 6
Rash 7 1 16 3
Increased amylase 8 1 15 1
Increased AST 8 0 15 0
Brigatinib vs Crizotinib in ALKi-Naive Patients With
Advanced ALK-Positive NSCLC (ALTA-1L): Background
 In patients with ALK-positive NSCLC, phase III PROFILE 1014 trial demonstrated
significantly superior median PFS with first-line crizotinib vs platinum–pemetrexed
doublet CT (10.9 vs 7.0 mos; P < .001)[1]
 Brigatinib: next-generation ALK/ROS1 inhibitor
‒ Activity reported against ALK inhibitor–resistance mutations and EGFR mutations in
in vitro and mouse models[2,3]
 Phase I/II trials evaluating brigatinib after crizotinib treatment have reported high
rates of response systemically and in the CNS with a prolonged median PFS of
~ 16 mos[4,5]
 Current prespecified first interim analysis compares efficacy and safety of brigatinib
vs crizotinib in ALK inhibitor–naive patients with advanced ALK-positive NSCLC[6]
1. Solomon BJ, et al. N Engl J Med. 2014;371:216 7-2177. 2. Uchibori K, et al. Nat Commun. 2017;8:14768.
3. Huang WS, et al. J Med Chem. 2016;59:4948-4964. 4. Huber RM, et al. ASCO 2018. Abstract 9061.
5. Camidge DR, et al. J Clin Oncol. 2018;36:2693-2701. 6. Camidge DR, et al. WCLC 2018. Abstract PL02.03.
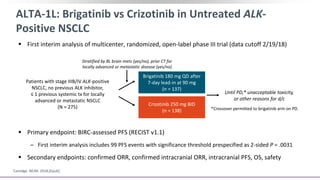
ALTA-1L: Brigatinib vs Crizotinib in Untreated ALK-
Positive NSCLC
 First interim analysis of multicenter, randomized, open-label phase III trial (data cutoff 2/19/18)
Camidge. NEJM. 2018;[Epub].
 Primary endpoint: BIRC-assessed PFS (RECIST v1.1)
‒ First interim analysis includes 99 PFS events with significance threshold prespecified as 2-sided P = .0031
 Secondary endpoints: confirmed ORR, confirmed intracranial ORR, intracranial PFS, OS, safety
Patients with stage IIIB/IV ALK-positive
NSCLC, no previous ALK inhibitor,
≤ 1 previous systemic tx for locally
advanced or metastatic NSCLC
(N = 275)
Until PD,* unacceptable toxicity,
or other reasons for d/c
Brigatinib 180 mg QD after
7-day lead-in at 90 mg
(n = 137)
Crizotinib 250 mg BID
(n = 138)
Stratified by BL brain mets (yes/no), prior CT for
locally advanced or metastatic disease (yes/no)
*Crossover permitted to brigatinib arm on PD.
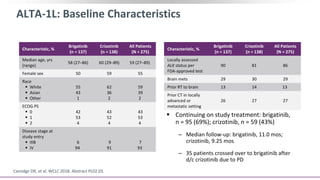
ALTA-1L: Baseline Characteristics
 Continuing on study treatment: brigatinib,
n = 95 (69%); crizotinib, n = 59 (43%)
‒ Median follow-up: brigatinib, 11.0 mos;
crizotinib, 9.25 mos
‒ 35 patients crossed over to brigatinib after
d/c crizotinib due to PD
Camidge DR, et al. WCLC 2018. Abstract PL02.03.
Characteristic, %
Brigatinib
(n = 137)
Crizotinib
(n = 138)
All Patients
(N = 275)
Median age, yrs
(range)
58 (27–86) 60 (29–89) 59 (27–89)
Female sex 50 59 55
Race
 White
 Asian
 Other
55
43
1
62
36
2
59
39
2
ECOG PS
 0
 1
 2
42
53
4
43
52
4
43
53
4
Disease stage at
study entry
 IIIB
 IV
6
94
9
91
7
93
Characteristic, %
Brigatinib
(n = 137)
Crizotinib
(n = 138)
All Patients
(N = 275)
Locally assessed
ALK status per
FDA-approved test
90 81 86
Brain mets 29 30 29


Prior RT to brain 13 14 13
Prior CT in locally
advanced or
metastatic setting
26 27 27
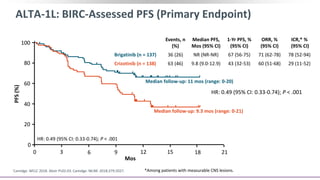
ALTA-1L: BIRC-Assessed PFS (Primary Endpoint)
Camidge. WCLC 2018. Abstr PL02.03. Camidge. NEJM. 2018;379:2027.
0
20
40
60
80
100
0 3 6 9 12 15 18 21
Mos
PFS(%)
Events, n
(%)
Median PFS,
Mos (95% CI)
1-Yr PFS, %
(95% CI)
ORR, %
(95% CI)
ICR,* %
(95% CI)
Brigatinib (n = 137) 36 (26) NR (NR-NR) 67 (56-75) 71 (62-78) 78 (52-94)
Crizotinib (n = 138) 63 (46) 9.8 (9.0-12.9) 43 (32-53) 60 (51-68) 29 (11-52)
Median follow-up: 11 mos (range: 0-20)
Median follow-up: 9.3 mos (range: 0-21)
HR: 0.49 (95% CI: 0.33-0.74); P < .001
*Among patients with measurable CNS lesions.
HR: 0.49 (95% CI: 0.33-0.74); P < .001
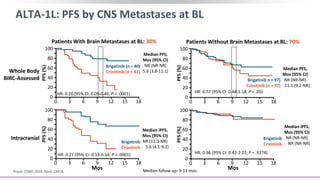
Patients With Brain Metastases at BL: 30%
ALTA-1L: PFS by CNS Metastases at BL
Popat. ESM0 2018. Abstr LBA58. Median follow-up: 9-11 mos.
Whole Body
BIRC-Assessed
Intracranial
Patients Without Brain Metastases at BL: 70%
HR: 0.27 (95% CI: 0.13-0.54; P < .0001) HR: 0.96 (95% CI: 0.42-2.22; P = .9274)
Brigatinib (n = 40)
Crizotinib (n = 41)
Median PFS,
Mos (95% CI)
NR (NR-NR)
5.6 (3.8-11.1)
Brigatinib n = 97)
Crizotinib (n = 97)
Median PFS,
Mos (95% CI)
NR (NR-NR)
11.1 (9.2-NR)
Brigatinib
Crizotinib
Median iPFS,
Mos (95% CI)
NR (11.0-NR)
5.6 (4.1-9.2)
Brigatinib
Crizotinib
Median iPFS,
Mos (95% CI)
NR (NR-NR)
NR (NR-NR)
Mos Mos
183 6 9 12 150
PFS(%)
100
80
60
40
20
0
183 6 9 12 150
PFS(%)
100
80
60
40
20
0
183 6 9 12 150
PFS(%)
100
80
60
40
20
0
183 6 9 12 150
PFS(%)
100
80
60
40
20
0
HR: 0.20 (95% CI: 0.09-0.46; P < .0001) HR: 0.72 (95% CI: 0.44-1.18; P < .20)
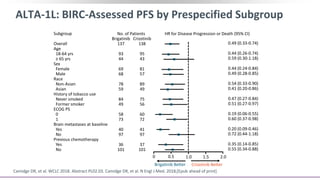
ALTA-1L: BIRC-Assessed PFS by Prespecified Subgroup
Camidge DR, et al. WCLC 2018. Abstract PL02.03. Camidge DR, et al. N Engl J Med. 2018;[Epub ahead of print].
Subgroup
Overall
Age
18-64 yrs
≥ 65 yrs
Sex
Female
Male
Race
Non-Asian
Asian
History of tobacco use
Never smoked
Former smoker
ECOG PS
0
1
Brain metastases at baseline
Yes
No
Previous chemotherapy
Yes
No
Brigatinib
137
93
44
69
68
78
59
84
49
58
73
40
97
36
101
Crizotinib
138
95
43
81
57
89
49
75
56
60
72
41
97
37
101
No. of Patients HR for Disease Progression or Death (95% CI)
0.49 (0.33-0.74)
0.44 (0.26-0.74)
0.59 (0.30-1.18)
0.44 (0.24-0.84)
0.49 (0.28-0.85)
0.54 (0.33-0.90)
0.41 (0.20-0.86)
0.47 (0.27-0.84)
0.51 (0.27-0.97)
0.19 (0.06-0.55)
0.60 (0.37-0.98)
0.20 (0.09-0.46)
0.72 (0.44-1.18)
0.35 (0.14-0.85)
0.55 (0.34-0.88)
0 0.5 1.0 1.5 2.0
Brigatinib Better Crizotinib Better
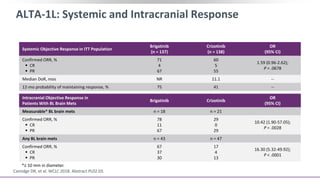
ALTA-1L: Systemic and Intracranial Response
Camidge DR, et al. WCLC 2018. Abstract PL02.03.
Systemic Objective Response in ITT Population
Brigatinib
(n = 137)
Crizotinib
(n = 138)
OR
(95% CI)
Confirmed ORR, %
 CR
 PR
71
4
67
60
5
55
1.59 (0.96-2.62);
P = .0678
Median DoR, mos NR 11.1 --
12-mo probability of maintaining response, % 75 41 --
Intracranial Objective Response in
Patients With BL Brain Mets
Brigatinib Crizotinib
OR
(95% CI)
Measurable* BL brain mets n = 18 n = 21
Confirmed ORR, %
 CR
 PR
78
11
67
29
0
29
10.42 (1.90-57.05);
P = .0028
Any BL brain mets n = 43 n = 47
Confirmed ORR, %
 CR
 PR
67
37
30
17
4
13
16.30 (5.32-49.92);
P < .0001
*≥ 10 mm in diameter.
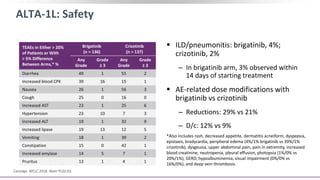
ALTA-1L: Safety
 ILD/pneumonitis: brigatinib, 4%;
crizotinib, 2%
‒ In brigatinib arm, 3% observed within
14 days of starting treatment
 AE-related dose modifications with
brigatinib vs crizotinib
‒ Reductions: 29% vs 21%
‒ D/c: 12% vs 9%
Camidge. WCLC 2018. Abstr PL02.03.
TEAEs in Either > 20%
of Patients or With
> 5% Difference
Between Arms,* %
Brigatinib
(n = 136)
Crizotinib
(n = 137)
Any
Grade
Grade
≥ 3
Any
Grade
Grade
≥ 3
Diarrhea 49 1 55 2
Increased blood CPK 39 16 15 1
Nausea 26 1 56 3
Cough 25 0 16 0
Increased AST 23 1 25 6
Hypertension 23 10 7 3
Increased ALT 19 1 32 9
Increased lipase 19 13 12 5
Vomiting 18 1 39 2
Constipation 15 0 42 1
Increased amylase 14 5 7 1
Pruritus 13 1 4 1
*Also includes rash, decreased appetite, dermatitis acneiform, dyspepsia,
epistaxis, bradycardia, peripheral edema (4%/1% brigatinib vs 39%/1%
crizotinib), dysgeusia, upper abdominal pain, pain in extremity, increased
blood creatinine, neutropenia, pleural effusion, photopsia (1%/0% vs
20%/1%), GERD, hypoalbuminemia, visual impairment (0%/0% vs
16%/0%), and deep vein thrombosis.
ALTA-1L: Conclusions
 In ALK inhibitor–naive patients with ALK-positive NSCLC, first interim analysis showed
significantly improved PFS with brigatinib vs crizotinib
‒ Median PFS: NR vs 9.8 mos (HR: 0.49; log-rank P = 0.0007)
‒ PFS benefit observed across most subgroups except those aged 65 yrs or older or with brain mets
at BL
‒ Short median follow-up may account for CNS progression driving PFS events in those with BL CNS disease
 Brigatinib was well tolerated with most trial-mandated dose reductions due to asymptomatic
laboratory abnormalities
 Early-onset ILD/pneumonitis observed in 3% of brigatinib-treated patients
 Investigators concluded that brigatinib a promising first-line treatment option for patients
with ALK-positive NSCLC.
Camidge DR, et al. WCLC 2018. Abstract PL02.03.
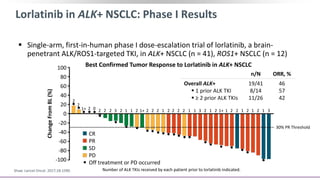
Lorlatinib in ALK+ NSCLC: Phase I Results
 Single-arm, first-in-human phase I dose-escalation trial of lorlatinib, a brain-
penetrant ALK/ROS1-targeted TKI, in ALK+ NSCLC (n = 41), ROS1+ NSCLC (n = 12)
Shaw. Lancet Oncol. 2017;18:1590.
n/N ORR, %
Overall ALK+
 1 prior ALK TKI
 ≥ 2 prior ALK TKIs
19/41
8/14
11/26
46
57
42
Best Confirmed Tumor Response to Lorlatinib in ALK+ NSCLC
CR
PR
SD
PD
Off treatment or PD occurred
ChangeFromBL(%)
100
80
60
40
20
0
-20
-40
-60
-80
-100
2
2
2
1+ 2 0 2 2 2 3 2 1 1 2 1+ 2 2 2 1 2 2 2 1 1 3 2 1 2 1+ 1 2 2 1 2 1 2 1 3
Number of ALK TKIs received by each patient prior to lorlatinib indicated.
30% PR Threshold
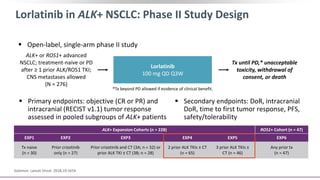
 Primary endpoints: objective (CR or PR) and
intracranial (RECIST v1.1) tumor response
assessed in pooled subgroups of ALK+ patients
 Secondary endpoints: DoR, intracranial
DoR, time to first tumor response, PFS,
safety/tolerability
Lorlatinib in ALK+ NSCLC: Phase II Study Design
 Open-label, single-arm phase II study
ALK+ or ROS1+ advanced
NSCLC; treatment-naive or PD
after ≥ 1 prior ALK/ROS1 TKI;
CNS metastases allowed
(N = 276)
Lorlatinib
100 mg QD Q3W
Tx until PD,* unacceptable
toxicity, withdrawal of
consent, or death
Solomon. Lancet Oncol. 2018;19:1654.
ALK+ Expansion Cohorts (n = 228) ROS1+ Cohort (n = 47)
EXP1 EXP2 EXP3 EXP4 EXP5 EXP6
Tx naive
(n = 30)
Prior crizotinib
only (n = 27)
Prior crizotinib and CT (3A; n = 32) or
prior ALK TKI ± CT (3B; n = 28)
2 prior ALK TKIs ± CT
(n = 65)
3 prior ALK TKIs ±
CT (n = 46)
Any prior tx
(n = 47)
*Tx beyond PD allowed if evidence of clinical benefit.
**
**
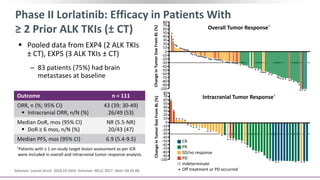
Phase II Lorlatinib: Efficacy in Patients With
≥ 2 Prior ALK TKIs (± CT)
 Pooled data from EXP4 (2 ALK TKIs
± CT), EXP5 (3 ALK TKIs ± CT)
‒ 83 patients (75%) had brain
metastases at baseline
CI, confidence interval; CT, chemotherapy; DOR, duration of response; mo, months; NR, not reache
Solomon. Lancet Oncol. 2018;19:1654. Solomon. WCLC 2017. Abstr OA 05.06.
Intracranial Tumor Response†
Overall Tumor Response†
Outcome n = 111
ORR, n (%; 95% CI)
 Intracranial ORR, n/N (%)
43 (39; 30-49)
26/49 (53)
Median DoR, mos (95% CI)
 DoR ≥ 6 mos, n/N (%)
NR (5.5-NR)
20/43 (47)
Median PFS, mos (95% CI) 6.9 (5.4-9.5)
†Patients with ≥ 1 on-study target lesion assessment as per ICR
were included in overall and intracranial tumor response analysis.
70
60
10
0
30
20
50
40
-10
-20
-30
-40
-50
-60
-70
-80
-90
-100
ChangeinTumorSizeFromBL(%)
80
CR
PR
SD/no response
PD
Indeterminate
Off treatment or PD occurred
*
*
*
*
*** **
*
**
****
*
* ***
*
*** ******
*** ******
*
***********
*
*
*
*** ******
70
60
10
0
30
20
50
40
-10
-20
-30
-40
-50
-60
-70
-80
-90
-100
ChangeinTumorSizeFromBL(%)
80
*
*
* * **
*
*
* * *
*
* * * * *
*
*
*
* *
*
** * * *
**
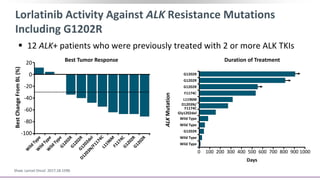
Lorlatinib Activity Against ALK Resistance Mutations
Including G1202R
 12 ALK+ patients who were previously treated with 2 or more ALK TKIs
Shaw. Lancet Oncol. 2017;18:1590.
Best Tumor Response Duration of Treatment20
0
-20
-40
-60
-80
-100
BestChangeFromBL(%)
G1202R
ALKMutation
G1202R
G1202R
F1174C
L1196M
D1203N/
F1174C
Gly1202del
Wild Type
Wild Type
G1202R
Wild Type
Days
10000 100 200 300 400 500 600 700 800 900
Wild Type
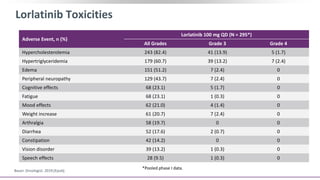
Lorlatinib Toxicities
Bauer. Oncologist. 2019;[Epub].
Adverse Event, n (%)
Lorlatinib 100 mg QD (N = 295*)
All Grades Grade 3 Grade 4
Hypercholesterolemia 243 (82.4) 41 (13.9) 5 (1.7)
Hypertriglyceridemia 179 (60.7) 39 (13.2) 7 (2.4)
Edema 151 (51.2) 7 (2.4) 0
Peripheral neuropathy 129 (43.7) 7 (2.4) 0
Cognitive effects 68 (23.1) 5 (1.7) 0
Fatigue 68 (23.1) 1 (0.3) 0
Mood effects 62 (21.0) 4 (1.4) 0
Weight increase 61 (20.7) 7 (2.4) 0
Arthralgia 58 (19.7) 0 0
Diarrhea 52 (17.6) 2 (0.7) 0
Constipation 42 (14.2) 0 0
Vision disorder 39 (13.2) 1 (0.3) 0
Speech effects 28 (9.5) 1 (0.3) 0
*Pooled phase I data.
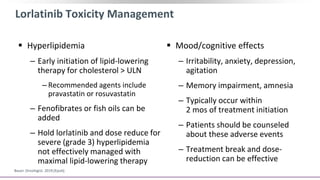
Lorlatinib Toxicity Management
 Hyperlipidemia
‒ Early initiation of lipid-lowering
therapy for cholesterol > ULN
‒ Recommended agents include
pravastatin or rosuvastatin
‒ Fenofibrates or fish oils can be
added
‒ Hold lorlatinib and dose reduce for
severe (grade 3) hyperlipidemia
not effectively managed with
maximal lipid-lowering therapy
 Mood/cognitive effects
‒ Irritability, anxiety, depression,
agitation
‒ Memory impairment, amnesia
‒ Typically occur within
2 mos of treatment initiation
‒ Patients should be counseled
about these adverse events
‒ Treatment break and dose-
reduction can be effective
Bauer. Oncologist. 2019;[Epub].
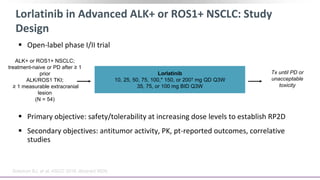
Lorlatinib in Advanced ALK+ or ROS1+ NSCLC: Study
Design
 Open-label phase I/II trial
 Primary objective: safety/tolerability at increasing dose levels to establish RP2D
 Secondary objectives: antitumor activity, PK, pt-reported outcomes, correlative
studies
ALK+ or ROS1+ NSCLC;
treatment-naive or PD after ≥ 1
prior
ALK/ROS1 TKI;
≥ 1 measurable extracranial
lesion
(N = 54)
Lorlatinib
10, 25, 50, 75, 100,* 150, or 200† mg QD Q3W
35, 75, or 100 mg BID Q3W
Solomon BJ, et al. ASCO 2016. Abstract 9009.
*Chosen as RP2D, n = 17.
†1 DLT observed.
Dose Escalation
Tx until PD or
unacceptable
toxicity
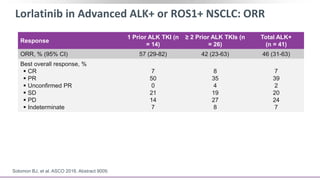
Lorlatinib in Advanced ALK+ or ROS1+ NSCLC: ORR
Solomon BJ, et al. ASCO 2016. Abstract 9009.
Response
1 Prior ALK TKI (n
= 14)
≥ 2 Prior ALK TKIs (n
= 26)
Total ALK+
(n = 41)
ORR, % (95% CI) 57 (29-82) 42 (23-63) 46 (31-63)
Best overall response, %
 CR
 PR
 Unconfirmed PR
 SD
 PD
 Indeterminate
7
50
0
21
14
7
8
35
4
19
27
8
7
39
2
20
24
7
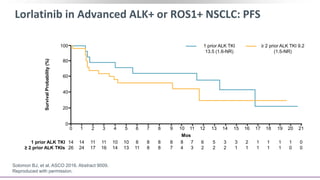
Lorlatinib in Advanced ALK+ or ROS1+ NSCLC: PFS
Solomon BJ, et al. ASCO 2016. Abstract 9009.
Reproduced with permission.
2120191817161514131211109876543210
Mos
0
0
1
0
1
1
1
1
1
1
2
1
3
1
3
2
5
2
6
2
7
3
8
4
8
7
8
8
8
8
8
11
10
13
10
14
11
16
11
17
14
24
14
26
1 prior ALK TKI
≥ 2 prior ALK TKIs
100
80
60
40
20
0
SurvivalProbability(%) 1 prior ALK TKI
13.5 (1.6-NR)
≥ 2 prior ALK TKI 9.2
(1.5-NR)Median PFS, mos (95% CI)
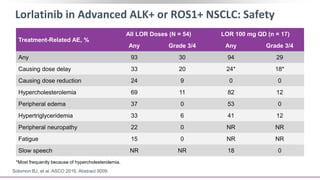
Lorlatinib in Advanced ALK+ or ROS1+ NSCLC: Safety
Solomon BJ, et al. ASCO 2016. Abstract 9009.
*Most frequently because of hypercholesterolemia.
Treatment-Related AE, %
All LOR Doses (N = 54) LOR 100 mg QD (n = 17)
Any Grade 3/4 Any Grade 3/4
Any 93 30 94 29
Causing dose delay 33 20 24* 18*
Causing dose reduction 24 9 0 0
Hypercholesterolemia 69 11 82 12
Peripheral edema 37 0 53 0
Hypertriglyceridemia 33 6 41 12
Peripheral neuropathy 22 0 NR NR
Fatigue 15 0 NR NR
Slow speech NR NR 18 0
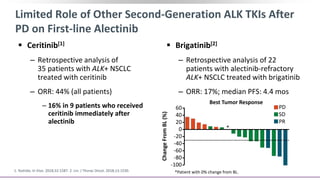
Limited Role of Other Second-Generation ALK TKIs After
PD on First-line Alectinib
 Ceritinib[1]
‒ Retrospective analysis of
35 patients with ALK+ NSCLC
treated with ceritinib
‒ ORR: 44% (all patients)
‒ 16% in 9 patients who received
ceritinib immediately after
alectinib
 Brigatinib[2]
‒ Retrospective analysis of 22
patients with alectinib-refractory
ALK+ NSCLC treated with brigatinib
‒ ORR: 17%; median PFS: 4.4 mos
1. Yoshida. In Vivo. 2018;32:1587. 2. Lin. J Thorac Oncol. 2018;13:1530.
Best Tumor Response
PD
SD
PR
60
40
20
0
-20
-40
-60
-80
-100ChangeFromBL(%)
*
*Patient with 0% change from BL.
Conclusions
 Lorlatinib is the preferred treatment for an ALK+ patient who
progresses on first-line alectinib
‒ ORR 43%, median PFS 6.9 mos among patients with > 2 prior ALK TKIs
‒ Excellent CNS activity: intracranial ORR 53% in a pre-treated population
‒ Broad-spectrum activity to most known ALK resistance mutations
 Common lorlatinib side effects include hypercholesterolemia,
hypertriglyceridemia, cognitive side effects, peripheral neuropathy,
and edema
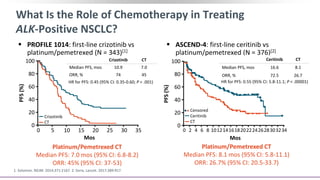
What Is the Role of Chemotherapy in Treating
ALK-Positive NSCLC?
 PROFILE 1014: first-line crizotinib vs
platinum/pemetrexed (N = 343)[1]
 ASCEND-4: first-line ceritinib vs
platinum/pemetrexed (N = 376)[2]
1. Solomon. NEJM. 2014;371:2167. 2. Soria. Lancet. 2017;389:917.
Ceritinib CT
Median PFS, mos 16.6 8.1
ORR, % 72.5 26.7
HR for PFS: 0.55 (95% CI: 5.8-11.1; P < .00001)
Crizotinib CT
Median PFS, mos 10.9 7.0
ORR, % 74 45
HR for PFS: 0.45 (95% CI: 0.35-0.60; P < .001)
Mos
Platinum/Pemetrexed CT
Median PFS: 7.0 mos (95% CI: 6.8-8.2)
ORR: 45% (95% CI: 37-53)
Platinum/Pemetrexed CT
Median PFS: 8.1 mos (95% CI: 5.8-11.1)
ORR: 26.7% (95% CI: 20.5-33.7)
100
80
60
40
20
0
PFS(%)
0 355 10 15 20 25 30
Mos
Censored
Ceritinib
CT
100
80
60
40
20
0
0 342
PFS(%)
4 6 8 101214161820222426283032
Crizotinib
CT
Treatment of ROS1 Rearrangement,
BRAF V600E and other Mutation–Positive NSCLC
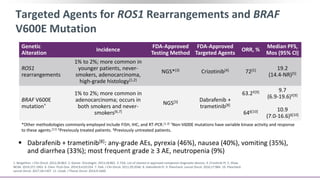
Targeted Agents for ROS1 Rearrangements and BRAF
V600E Mutation
*Other methodologies commonly employed include FISH, IHC, and RT-PCR.[1,3] †Non-V600E mutations have variable kinase activity and response
to these agents.[11] ‡Previously treated patients. §Previously untreated patients.
1. Bergethon. J Clin Oncol. 2012;30:863. 2. Gainor. Oncologist. 2013;18:865. 3. FDA. List of cleared or approved companion diagnostic devices. 4. Crizotinib PI. 5. Shaw.
NEJM. 2014;371:1963. 6. Chen. PLoS One. 2014;9:e101354. 7. Paik. J Clin Oncol. 2011;29:2046. 8. Dabrafenib PI. 9. Planchard. Lancet Oncol. 2016;17:984. 10. Planchard.
Lancet Oncol. 2017;18:1307. 11. Litvak. J Thorac Oncol. 2014;9:1669.
Genetic
Alteration
Incidence
FDA-Approved
Testing Method
FDA-Approved
Targeted Agents
ORR, %
Median PFS,
Mos (95% CI)
ROS1
rearrangements
1% to 2%; more common in
younger patients, never-
smokers, adenocarcinoma,
high-grade histology[1,2]
NGS*[3] Crizotinib[4] 72[5] 19.2
(14.4-NR)[5]
BRAF V600E
mutation†
1% to 2%; more common in
adenocarcinoma; occurs in
both smokers and never-
smokers[6,7]
NGS[3] Dabrafenib +
trametinib[8]
63.2‡[9]
64§[10]
9.7
(6.9-19.6)‡[9]
10.9
(7.0-16.6)§[10]
 Dabrafenib + trametinib[8]: any-grade AEs, pyrexia (46%), nausea (40%), vomiting (35%),
and diarrhea (33%); most frequent grade ≥ 3 AE, neutropenia (9%)
 Larotrectinib was recently approved by the FDA for adult and pediatric patients with solid tumors
that have a neurotrophic receptor tyrosine kinase (NTRK) gene fusion without a known acquired
resistance mutation, that are either metastatic or where surgical resection is likely to result in
severe morbidity, and who have no satisfactory alternative treatments or whose cancer has
progressed following treatment[6]
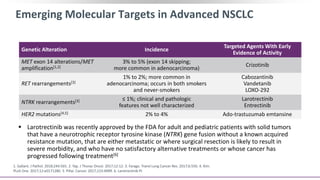
Emerging Molecular Targets in Advanced NSCLC
1. Gallant. J Pathol. 2018;244:565. 2. Yap. J Thorac Oncol. 2017;12:12. 3. Farago. Transl Lung Cancer Res. 2017;6:550. 4. Kim.
PLoS One. 2017;12:e0171280. 5. Pillai. Cancer. 2017;123:4099. 6. Larotrectinib PI.
Genetic Alteration Incidence
Targeted Agents With Early
Evidence of Activity
MET exon 14 alterations/MET
amplification[1,2]
3% to 5% (exon 14 skipping;
more common in adenocarcinoma)
Crizotinib
RET rearrangements[3]
1% to 2%; more common in
adenocarcinoma; occurs in both smokers
and never-smokers
Cabozantinib
Vandetanib
LOXO-292
NTRK rearrangements[3] ≤ 1%; clinical and pathologic
features not well characterized
Larotrectinib
Entrectinib
HER2 mutations[4,5] 2% to 4% Ado-trastuzumab emtansine
TRK Inhibitors
 Larotrectinib: FDA approved for adult and pediatric patients with solid tumors with a NTRK
gene fusion without a known acquired resistance mutation, who are either metastatic or not
candidates for surgical resection due to likely severe morbidity, and who have no satisfactory
alternative treatments or whose cancer has progressed following standard treatment[1]
 Entrectinib: granted FDA priority review for select adult and pediatric patients with locally
advanced or metastatic NTRK fusion–positive solid tumors and for patients with metastatic
ROS1+ NSCLC[2]
 LOXO-195: second-generation TKI with activity against multiple TRK kinase domain mutations
in patients with solid tumors with a TRK gene fusion[3]
1. Larotrectinib PI. 2018. 2. Demetri. ESMO 2018. Abstr LBA17. 3. Hyman. AACR 2019. Abstr CT127.
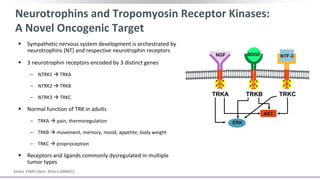
Neurotrophins and Tropomyosin Receptor Kinases:
A Novel Oncogenic Target
 Sympathetic nervous system development is orchestrated by
neurotrophins (NT) and respective neurotrophin receptors
 3 neurotrophin receptors encoded by 3 distinct genes
– NTRK1  TRKA
– NTRK2  TRKB
– NTRK3  TRKC
 Normal function of TRK in adults
– TRKA  pain, thermoregulation
– TRKB  movement, memory, mood, appetite, body weight
– TRKC  proprioception
 Receptors and ligands commonly dysregulated in multiple
tumor types
Amatu. ESMO Open. 2016;1:e000023.
NGF NTF-3
TRKA TRKB TRKC
P
P
P
P
P
P
P
P
P
P
P
P
ERK
AKT
BDGF
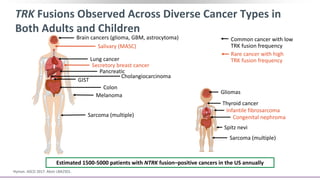
TRK Fusions Observed Across Diverse Cancer Types in
Both Adults and Children
Hyman. ASCO 2017. Abstr LBA2501.
Brain cancers (glioma, GBM, astrocytoma)
Thyroid cancer
Salivary (MASC)
Lung cancer
Secretory breast cancer
Pancreatic
Cholangiocarcinoma
GIST
Colon
Melanoma
Sarcoma (multiple)
Gliomas
Infantile fibrosarcoma
Thyroid cancer
Congenital nephroma
Spitz nevi
Sarcoma (multiple)
Common cancer with low
TRK fusion frequency
Rare cancer with high
TRK fusion frequency
Estimated 1500-5000 patients with NTRK fusion–positive cancers in the US annually
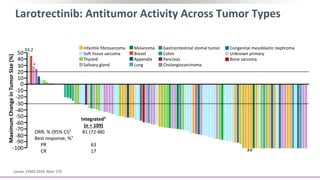
Larotrectinib: Antitumor Activity Across Tumor Types
Lassen. ESMO 2018. Abstr 279.
MaximumChangeinTumorSize(%)
40
20
0
-20
-40
-60
-80
-100
50
30
10
-10
-30
-50
-70
-90
Infantile fibrosarcoma
Soft tissue sarcoma
Thyroid
Salivary gland
Melanoma
Breast
Appendix
Lung
Gastrointestinal stomal tumor
Colon
Pancreas
Cholangiocarcinoma
Congenital mesoblastic nephroma
Unknown primary
Bone sarcoma
ORR, % (95% CI)†
Best response, %†
PR
CR
Integrated‡
(n = 109)
81 (72-88)
63
17
93.2
*
##
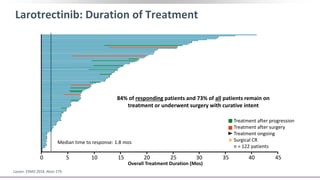
Larotrectinib: Duration of Treatment
Lassen. ESMO 2018. Abstr 279.
0 10 2015 25 30 4035 455
84% of responding patients and 73% of all patients remain on
treatment or underwent surgery with curative intent
Overall Treatment Duration (Mos)
Treatment after progression
Treatment after surgery
Treatment ongoing
Surgical CR
n = 122 patients
Median time to response: 1.8 mos
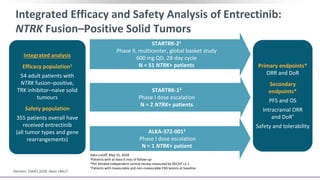
Integrated Efficacy and Safety Analysis of Entrectinib:
NTRK Fusion–Positive Solid Tumors
Integrated analysis
Efficacy population§
54 adult patients with
NTRK fusion–positive,
TRK inhibitor–naive solid
tumours
Safety population
355 patients overall have
received entrectinib
(all tumor types and gene
rearrangements)
Primary endpoints*
ORR and DoR
Secondary
endpoints*
PFS and OS
Intracranial ORR
and DoR†
Safety and tolerability
STARTRK-12
Phase I dose escalation
N = 2 NTRK+ patients
ALKA-372-0012
Phase I dose escalation
N = 1 NTRK+ patient
STARTRK-21
Phase II, multicenter, global basket study
600 mg QD, 28-day cycle
N = 51 NTRK+ patients
Data cutoff: May 31, 2018
§Patients with at least 6 mos of follow-up
*Per blinded independent central review measured by RECIST v1.1
†Patients with measurable and non-measurable CNS lesions at baseline
Demetri. ESMO 2018. Abstr LBA17.
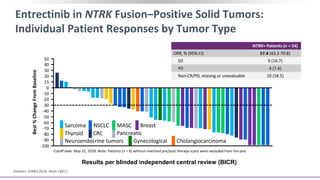
Entrectinib in NTRK Fusion–Positive Solid Tumors:
Individual Patient Responses by Tumor Type
Demetri. ESMO 2018. Abstr LBA17.
0
-30
-50
-90
Best%ChangeFromBaseline
15
-80
-70
-60
-40
-20
-10
20
30
40
-100
50
CRC
NSCLCSarcoma
Neuroendocrine tumors
PancreaticThyroid
MASC Breast
CholangiocarcinomaGynecological
NTRK+ Patients (n = 54)
ORR, % (95% CI) 57.4 (43.2-70.8)
SD 9 (16.7)
PD 4 (7.4)
Non-CR/PD, missing or unevaluable 10 (18.5)
Results per blinded independent central review (BICR)
Cutoff date: May 31, 2018. Note: Patients (n = 6) without matched pre/post therapy scans were excluded from the plot
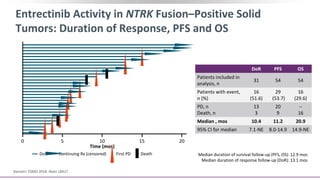
Entrectinib Activity in NTRK Fusion–Positive Solid
Tumors: Duration of Response, PFS and OS
Median duration of survival follow-up (PFS, OS): 12.9 mos
Median duration of response follow-up (DoR): 13.1 mos
DoR PFS OS
Patients included in
analysis, n
31 54 54
Patients with event,
n (%)
16
(51.6)
29
(53.7)
16
(29.6)
PD, n
Death, n
13
3
20
9
--
16
Median , mos 10.4 11.2 20.9
95% CI for median 7.1-NE 8.0-14.9 14.9-NE
0 5 10 15 20
Time (mos)
DoR Continuing Rx (censored) First PD Death
Demetri. ESMO 2018. Abstr LBA17.
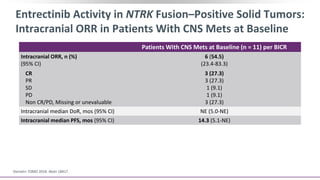
Entrectinib Activity in NTRK Fusion–Positive Solid Tumors:
Intracranial ORR in Patients With CNS Mets at Baseline
Patients With CNS Mets at Baseline (n = 11) per BICR
Intracranial ORR, n (%)
(95% CI)
CR
PR
SD
PD
Non CR/PD, Missing or unevaluable
6 (54.5)
(23.4-83.3)
3 (27.3)
3 (27.3)
1 (9.1)
1 (9.1)
3 (27.3)
Intracranial median DoR, mos (95% CI) NE (5.0-NE)
Intracranial median PFS, mos (95% CI) 14.3 (5.1-NE)
Demetri. ESMO 2018. Abstr LBA17.
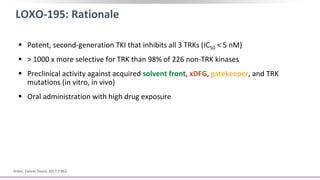
LOXO-195: Rationale
Drilon. Cancer Discov. 2017;7:963.
 Potent, second-generation TKI that inhibits all 3 TRKs (IC50 < 5 nM)
 > 1000 x more selective for TRK than 98% of 226 non-TRK kinases
 Preclinical activity against acquired solvent front, xDFG, gatekeeper, and TRK
mutations (in vitro, in vivo)
 Oral administration with high drug exposure
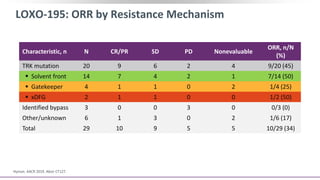
LOXO-195: ORR by Resistance Mechanism
Hyman. AACR 2019. Abstr CT127.
Characteristic, n N CR/PR SD PD Nonevaluable
ORR, n/N
(%)
TRK mutation 20 9 6 2 4 9/20 (45)
 Solvent front 14 7 4 2 1 7/14 (50)
 Gatekeeper 4 1 1 0 2 1/4 (25)
 xDFG 2 1 1 0 0 1/2 (50)
Identified bypass 3 0 0 3 0 0/3 (0)
Other/unknown 6 1 3 0 2 1/6 (17)
Total 29 10 9 5 5 10/29 (34)
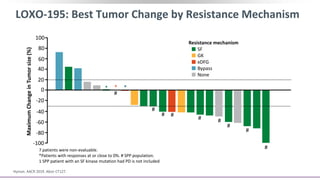
LOXO-195: Best Tumor Change by Resistance Mechanism
Hyman. AACR 2019. Abstr CT127.
MaximumChangeinTumorsize(%)
40
20
0
-20
-40
-60
-80
-100
80
60
100
7 patients were non-evaluable.
*Patients with responses at or close to 0%. # SPP population.
1 SPP patient with an SF kinase mutation had PD is not included
Resistance mechanism
SF
GK
xDFG
Bypass
None
* * *
#
#
#
#
#
#
# #
#
ROS1 Inhibitors
 Entrectinib: granted FDA priority review for select adult and pediatric
patients with locally advanced or metastatic NTRK fusion–positive
solid tumors and for patients with metastatic ROS1+ NSCLC[1]
 Crizotinib: Approved for patients with metastatic ROS1
rearrangement–positive or ALK fusion–positive NSCLC[2]
 Lorlatinib: granted FDA accelerated approval for patients with
metastatic ALK fusion–positive NSCLC who have progressed on
crizotinib and at least one other ALK inhibitor, alectinib, or ceritinib[3]
‒ MOA: highly potent, selective, and brain-penetrant TKI that inhibits ALK
and ROS1 proto-oncogene
1. Demetri. ESMO 2018. Abstr LBA17. 2. Crizotinib PI. 2018. 3. Lorlatinib PI. 2018.
ROS1 Rearrangements in NSCLC
 ROS1 rearrangements are identified in approximately 1% to 2% of NSCLC
cases[1-3]
 ROS1 rearrangements lead to fusion of a portion of ROS1, including its
tyrosine kinase domain, to a variety of different partner proteins[3,4]
 ROS1 fusion kinases are constitutively activated and function as potent
oncogenic drivers[3,4]
1. Bergethon. JCO. 2012;30:863. 2. Dugay. Oncotarget. 2017;8:53336. 3. Davies. Clin Cancer Res. 2013;19:4040.
4. Lin. J Thorac Oncol. 2017;12:1611. 5. Lin. J Thorac Oncol. 2017;12:1611.
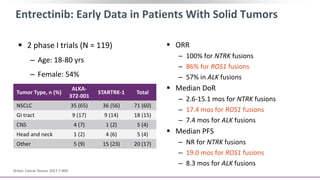
Entrectinib: Early Data in Patients With Solid Tumors
 2 phase I trials (N = 119)
‒ Age: 18-80 yrs
‒ Female: 54%
 ORR
‒ 100% for NTRK fusions
‒ 86% for ROS1 fusions
‒ 57% in ALK fusions
 Median DoR
‒ 2.6-15.1 mos for NTRK fusions
‒ 17.4 mos for ROS1 fusions
‒ 7.4 mos for ALK fusions
 Median PFS
‒ NR for NTRK fusions
‒ 19.0 mos for ROS1 fusions
‒ 8.3 mos for ALK fusions
Drilon. Cancer Discov. 2017;7:400.
Tumor Type, n (%)
ALKA-
372-001
STARTRK-1 Total
NSCLC 35 (65) 36 (56) 71 (60)
GI tract 9 (17) 9 (14) 18 (15)
CNS 4 (7) 1 (2) 5 (4)
Head and neck 1 (2) 4 (6) 5 (4)
Other 5 (9) 15 (23) 20 (17)
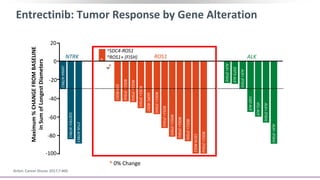
Entrectinib: Tumor Response by Gene Alteration
Drilon. Cancer Discov. 2017;7:400.
Maximum%CHANGEFROMBASELINE
inSumofLongestDiameters 20
0
-20
-40
-60
-80
-100
NTRK ROS1 ALK
* 0% Change
LMNA-NTRK1
SQSTM1-NTRK1
ETV6-NTRK3
a
EZR-ROS1
ROS1+(FISH)
ROS1+(FISH)
ROS1+(FISH)
GOPC-ROS1
ROS1+(FISH)
ROS1+(FISH)
ROS1+(FISH)
ROS1+(FISH)
ROS1+(FISH)
ROS1+(FISH)
CD74-ROS1
ALK+(FISH)
D5F3-ALK
ALK+(FISH)
CAD-ALK
VCL-ALK
ALK+(FISH)
ALK+(FISH)
*b
aSDC4-ROS1
bROS1+ (FISH)
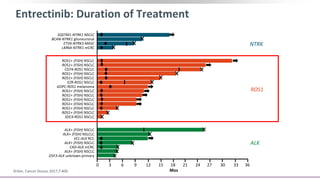
Entrectinib: Duration of Treatment
Drilon. Cancer Discov. 2017;7:400.
SQSTM1-NTRK1 NSCLC
BCAN-NTRK1 glioneuronal
ETV6-NTRK3 MASC
LMNA-NTRK1 mCRC
ROS1+ (FISH) NSCLC
ROS1+ (FISH) NSCLC
CD74-ROS1 NSCLC
ROS1+ (FISH) NSCLC
ROS1+ (FISH) NSCLC
EZR-ROS1 NSCLC
GOPC-ROS1 melanoma
ROS1+ (FISH) NSCLC
ROS1+ (FISH) NSCLC
ROS1+ (FISH) NSCLC
ROS1+ (FISH) NSCLC
ROS1+ (FISH) NSCLC
ROS1+ (FISH) NSCLC
SDC4-ROS1 NSCLC
ALK+ (FISH) NSCLC
ALK+ (FISH) NSLCLC
VCL-ALK RCC
ALK+ (FISH) NSCLC
CAD-ALK mCRC
ALK+ (FISH) NSCLC
D5F3-ALK unknown primary
NTRK
ROS1
ALK
0 3 6 9 12 15 18 21 24 27 30 33 36
Mos
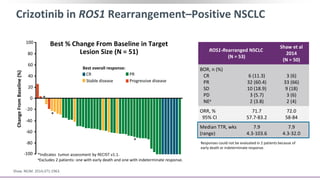
Crizotinib in ROS1 Rearrangement–Positive NSCLC
Best % Change From Baseline in Target
Lesion Size (N = 51)
Best overall response:
CR PR
Stable disease Progressive disease
20
ChangeFromBaseline(%)
40
60
80
100
0
-20
-40
-60
-80
-100
*
*
*
*Indicates tumor assessment by RECIST v1.1.
aExcludes 2 patients: one with early death and one with indeterminate response.
ROS1-Rearranged NSCLC
(N = 53)
Shaw et al
2014
(N = 50)
BOR, n (%)
CR
PR
SD
PD
NEa
6 (11.3)
32 (60.4)
10 (18.9)
3 (5.7)
2 (3.8)
3 (6)
33 (66)
9 (18)
3 (6)
2 (4)
ORR, %
95% CI
71.7
57.7-83.2
72.0
58-84
Median TTR, wks
(range)
7.9
4.3-103.6
7.9
4.3-32.0
Responses could not be evaluated in 2 patients because of
early death or indeterminate response.
Shaw. NEJM. 2014;371:1963.
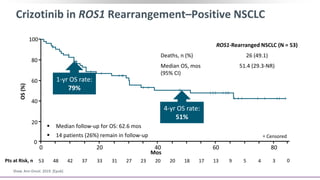
Crizotinib in ROS1 Rearrangement–Positive NSCLC
 Median follow-up for OS: 62.6 mos
 14 patients (26%) remain in follow-up
ROS1-Rearranged NSCLC (N = 53)
Deaths, n (%) 26 (49.1)
Median OS, mos
(95% CI)
51.4 (29.3-NR)
40
OS(%)
Mos
60
80
100
20
0
0 4020 60 80
53Pts at Risk, n 48 42 37 31 27 23 20 18 17 9 5 4 02033 13 3
1-yr OS rate:
79%
4-yr OS rate:
51%
Censored
Shaw. Ann Oncol. 2019. [Epub]
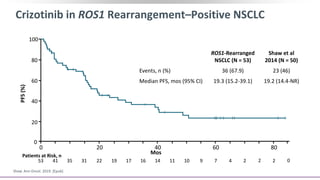
Crizotinib in ROS1 Rearrangement–Positive NSCLC
ROS1-Rearranged
NSCLC (N = 53)
Shaw et al
2014 (N = 50)
Events, n (%) 36 (67.9) 23 (46)
Median PFS, mos (95% CI) 19.3 (15.2-39.1) 19.2 (14.4-NR)
PFS(%)
53 41 35 31 19 17 16 11 10 9 4 2 2 01422 7 2
Patients at Risk, n
40
60
80
100
20
0
0 4020 60 80
Mos
Shaw. Ann Oncol. 2019. [Epub]
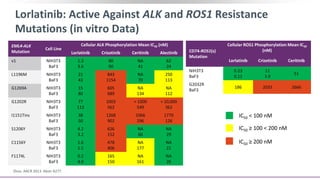
Lorlatinib: Active Against ALK and ROS1 Resistance
Mutations (in vitro Data)
Zhou. AACR 2013. Abstr A277.
EML4-ALK
Mutation
Cell Line
Cellular ALK Phosphorylation Mean IC50 (nM)
Lorlatinib Crizotinib Ceritinib Alectinib
v1 NIH3T3
BaF3
1.3
3.6
80
90
NA
41
62
24
L1196M NIH3T3
BaF3
21
43
843
1154
NA
70
250
113
G1269A NIH3T3
BaF3
15
80
605
689
NA
134
NA
112
G1202R NIH3T3
BaF3
77
113
1003
562
> 1000
549
> 10,000
362
I1151Tins NIH3T3
BaF3
38
50
1268
902
1066
296
1770
126
S1206Y NIH3T3
BaF3
4.2
3.2
626
152
NA
60
NA
29
C1156Y NIH3T3
BaF3
1.6
1.5
478
406
NA
177
NA
21
F1174L NIH3T3
BaF3
0.2
4.0
165
150
NA
161
NA
26
CD74-ROS1(s)
Mutation
Cellular ROS1 Phosphorylation Mean IC50
(nM)
Lorlatinib Crizotinib Ceritinib
NIH3T3
BaF3
0.23
0.11
11
3.9
51
G2032R
BaF3
186 2033 2666
IC50 < 100 nM
IC50 ≥ 100 < 200 nM
IC50 ≥ 200 nM
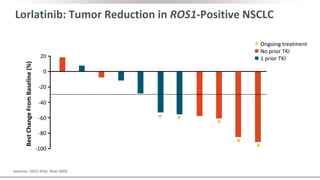
Lorlatinib: Tumor Reduction in ROS1-Positive NSCLC
Solomon. ASCO 2016. Abstr 9009.
BestChangeFromBaseline(%)
20
0
-20
-40
-60
-80
-100
Ongoing treatment
No prior TKI
1 prior TKI
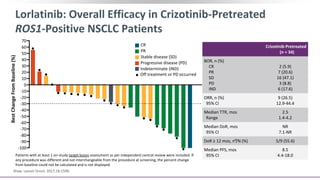
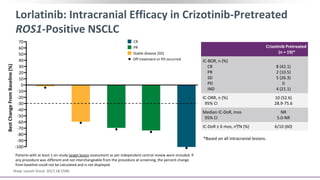
Lorlatinib: Overall Efficacy in Crizotinib-Pretreated
ROS1-Positive NSCLC Patients
Shaw. Lancet Oncol. 2017;18:1590.
Crizotinib Pretreated
(n = 34)
BOR, n (%)
CR
PR
SD
PD
IND
2 (5.9)
7 (20.6)
16 (47.1)
3 (8.8)
6 (17.6)
ORR, n (%)
95% CI
9 (26.5)
12.9-44.4
Median TTR, mos
Range
2.5
1.4-4.2
Median DoR, mos
95% CI
NR
7.1-NR
DoR ≥ 12 mos, n⁰/N (%) 5/9 (55.6)
Median PFS, mos
95% CI
8.5
4.4-18.0Patients with at least 1 on-study target lesion assessment as per independent central review were included. If
any procedure was different and not interchangeable from the procedure at screening, the percent change
from baseline could not be calculated and is not displayed.
70
60
10
0
30
20
50
40
-10
-20
-30
-40
-50
-60
-70
-80
-90
-100
BestChangeFromBaseline(%)
Indeterminate (IND)
CR
PR
Stable disease (SD)
Progressive disease (PD)
Off treatment or PD occurred
Lorlatinib: Intracranial Efficacy in Crizotinib-Pretreated
ROS1-Positive NSCLC
Crizotinib Pretreated
(n = 19)*
IC-BOR, n (%)
CR
PR
SD
PD
IND
8 (42.1)
2 (10.5)
5 (26.3)
0
4 (21.1)
IC-ORR, n (%)
95% CI
10 (52.6)
28.9-75.6
Median IC-DoR, mos
95% CI
NR
5.0-NR
IC-DoR ≥ 6 mos, n⁰/N (%) 6/10 (60)
*Based on all intracranial lesions.
70
60
10
0
30
20
50
40
-10
-20
-30
-40
-50
-60
-70
-80
-90
-100
BestChangeFromBaseline(%)
Off treatment or PD occurred
CR
PR
Stable disease (SD)
Shaw. Lancet Oncol. 2017;18:1590.
Patients with at least 1 on-study target lesion assessment as per independent central review were included. If
any procedure was different and not interchangeable from the procedure at screening, the percent change
from baseline could not be calculated and is not displayed.
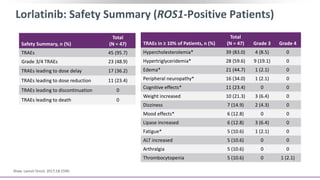
Lorlatinib: Safety Summary (ROS1-Positive Patients)
TRAEs in ≥ 10% of Patients, n (%)
Total
(N = 47) Grade 3 Grade 4
Hypercholesterolemia* 39 (83.0) 4 (8.5) 0
Hypertriglyceridemia* 28 (59.6) 9 (19.1) 0
Edema* 21 (44.7) 1 (2.1) 0
Peripheral neuropathy* 16 (34.0) 1 (2.1) 0
Cognitive effects* 11 (23.4) 0 0
Weight increased 10 (21.3) 3 (6.4) 0
Dizziness 7 (14.9) 2 (4.3) 0
Mood effects* 6 (12.8) 0 0
Lipase increased 6 (12.8) 3 (6.4) 0
Fatigue* 5 (10.6) 1 (2.1) 0
ALT increased 5 (10.6) 0 0
Arthralgia 5 (10.6) 0 0
Thrombocytopenia 5 (10.6) 0 1 (2.1)
Safety Summary, n (%)
Total
(N = 47)
TRAEs 45 (95.7)
Grade 3/4 TRAEs 23 (48.9)
TRAEs leading to dose delay 17 (36.2)
TRAEs leading to dose reduction 11 (23.4)
TRAEs leading to discontinuation 0
TRAEs leading to death 0
Shaw. Lancet Oncol. 2017;18:1590.
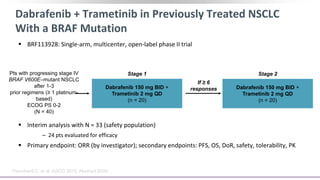
Dabrafenib + Trametinib in Previously Treated NSCLC
With a BRAF Mutation
 BRF113928: Single-arm, multicenter, open-label phase II trial
 Interim analysis with N = 33 (safety population)
‒ 24 pts evaluated for efficacy
 Primary endpoint: ORR (by investigator); secondary endpoints: PFS, OS, DoR, safety, tolerability, PK
Dabrafenib 150 mg BID +
Trametinib 2 mg QD
(n = 20)
Pts with progressing stage IV
BRAF V600E–mutant NSCLC
after 1-3
prior regimens (≥ 1 platinum-
based)
ECOG PS 0-2
(N = 40)
Planchard D, et al. ASCO 2015. Abstract 8006.
Dabrafenib 150 mg BID +
Trametinib 2 mg QD
(n = 20)
If ≥ 6
responses
Stage 1 Stage 2