INTRODUCTION
Nutrition isrequired to
sustain life, the most
individuals require nutrients
from eating balanced food.
The HYPOTHALAMUS
contains the appetite
regulation center with in the
brain. This complex neural
system regulates the body’s
ability to recognize when it is
hungry and when it has been
stated.
When it is disturbed, lead to
eating disorder.
4.
WHAT IS ANEATING DISORDER?
Eating disorders are
mental illnesses that
cause serious disturbances
in a person’s everyday
diet.
It can manifest as eating
extremely small amounts
of food or severely
overeating.
leading to severe changes.
5.
EATING DISORDER
Eatingdisorders are characterized by severe
form of disturbances in eating pattern / behavior
leading to life threatening conditions.
6.
CLASSIFICATION: ICD-10
TheICD10 codes for eating disorders fall under the category
F50. Here are some key codes:
• F50.0: Anorexia nervosa
• F50.1: Bulimia nervosa
• F50.2: Binge eating disorder
• F50.9: Eating disorder, unspecified.
EPIDEMIOLOGICAL FACTOR
Theincidence of Anorexia Nervosa has increased in the
past 30 years both in the united states and in western
Europe. Studies indicate a prevalence rate among young
women in the united state of approximately 1 percent .
Anorexia nervosa occurs predominantly in females 12-30
years.
More prevalent in higher socio-economical groups.
Bulimia nervosa is more prevalent than anorexia nervosa,
with estimates up to 4 percent of young women.
Onset occurs in early childhood and late adolescent .
11.
Obesity hasbeen defined as a body mass index
(BMI= weight/height(2) of 30 or greater. In the
united state, statistics indicate that, among
adults 20 years of age or older, 68 % are
overweight.
ANOREXIA NERVOSA
Anorexia:Prolonged loss of appetite.
Nervosa : Indicates that the loss is due to
emotional reason.
Body image: a subjective concept of one’s
physical appearance based on the personal
perceptions of self and the reactions of others.
14.
ANOREXIA NERVOSA:
Anorexianervosa
happens when one is
obsessed with
becoming thin that
they reach extreme
measures and this
leads to extreme
weight loss.
15.
DEFINITION
Anorexia nervosais characterized by excessive
food restriction, irrational fear of gaining weight
and a distorted body self-perception which leads
to excessive weight loss.
16.
ICD-11 CLASSIFICATION
Eatingdisorder-Block L1-6B8
6B80- Anorexia nervosa
6B80.0- Anorexia nervosa with significantly low body
weight
6B80.1- Anorexia nervosa with dangerously low body
weight
6B80.2- Anorexia nervosa in recovery with normal
body weight
6B80.Y- Other specified anorexia nervosa
6B80.Z- Anorexia nervosa, unspecified
17.
Prevalence and Incidence
A.N is found all around the world but prevalence
is significantly higher in developed countries.
At any given point in time between 0.3-0.4 % of
young women and 0.1% of young men will suffer
from anorexia nervosa.
Overall prevalence is 0.3-1% in women and 0.1-
0.3 % in men.
18.
TYPES OF ANOREXIANERVOSA
Restricting type: individual has not engaged in
recurrent episodes of binge –eating or purging
behavior (self –induced vomiting or the misuse of
la, laxatives, diuretics or enemas). In this weight
loss by excess starvation or rigid exercise.
Binge-eating / purging type: individual has
engaged in recurrent episodes of binge-eating or
purging behavior (self –induced vomiting or the
misuse of laxatives, diuretics or enemas).
19.
CHARACTERISTIC FEATURES
Anorexianervosa is characterized by a morbid
fear of being obese. This fear does not decrease
even if body becomes very thin and underweight.
The term anorexia was actually a misnomer.
It was initially believed that anorexics didn't
experience sensation of hunger .
However, research indicates that they do indeed
suffer from pangs of hunger, and it is only with
food intake of less than 200 calories per day that
hunger sensation actually ceases.
20.
Significant lossof weight occurs, usually more
than 25% of the original weight. The final weight
is usually 15% less than the minimum limit of
normal weight or the Quetelet’s body-mass
index (BMI) of 17.5 or less.
No known medical illness, which can account for
the weight loss , is present.
Absence of any other psychiatric disorder.
21.
Symptoms includes:
Extremefear of gaining weight or becoming fat , even when
underweight
o Gross distortion of body image
Preoccupation with food, and refusal to eat food.
Weight loss due to less intake of food and extensive exercising
Poor sexual adjustment.( often conflict about being a female and
fear of pregnancy)
Up to 50% of anorexics have bulimic episodes. Characterized by
rapid consumption of large amount of food in a short period,
when alone , called binge eating. Due to intense guilt attempt to
remove eaten food by:
purging behavior such as Self induced vomiting and abuse of laxative
or diuretics also may occur.
22.
Others symptoms:
hypothermia, edema, lanugo, and variety
of metabolic changes.
Yellow dry skin
Obsessed with food . E.g.: hoard or
conceal food, talk about food and
recipes or prepare food for others.
Feeling of depression, anxiety .
Confusion, poor memory, judgment
Loss of bone strength, osteoporosis
Extreme sensitivity to cold
Death may occur due to hypokalemia
( by self induced vomiting), dehydration,
malnutrition, CCF.
23.
ANOREXIA NERVOSA:
WARNING SIGNS
Dramatic weight loss
Refusal to eat certain foods or food categories.
Consistent excuses to avoid situations involving food
Excessive and rigid exercise routine
Withdrawal from usual friends/relatives
24.
HEALTH RISKS WITHANOREXIA
NERVOSA
Heart failure
Kidney failure
Low protein stores
Digestive problems
25.
SEVERITY OF ANOREXIA
NERVOSA
Levelof severity of the disorder can be
determined by calculating BMI.
Level-1: Mild (BMI >17)
Level-2: Moderate (BMI 16-16.99)
Level-3: severe (BMI 15-15.99)
Level-4: Extreme (BMI <15)
26.
COMPLICATIONS OF ANOREXIA
NERVOSA
Bone weakening
Decrease in white blood cells, which lead to
increased risk of infection
Low potassium levels in the blood, which may
cause dangerous heart rhythms
Severe dehydration and malnutrition
Seizures due to fluid or sodium loss from
repeated diarrhea or vomiting
Thyroid gland problems and tooth decay
27.
DIAGNOSTIC CRITERIA
Acc. ToDSM-5:
Restriction of energy intake as per the body
requirements that leads to significantly low body
weight.
Extreme fear of gaining weight or persistent
behavior that interferes with weight gain, even
though at a significantly low weight.
Disturbance in the way in which one’s body
weight or shape is experienced, undue influence
of body weight or shape on self evaluation.
28.
DIAGNOSTIC CRITERIA
Acc. ToICD-11:
Significantly low body weight for the individual’s height,
age, developmental stage that is not due to another health
condition or to the unavailability of food .
BMI <18.5 kg/m2 in adults.
Rapid weight loss (>20 % of total body weight within 6
months) .
Failure to weight gain as expected
Low body weight is accompanied by a persistent pattern of
behaviors to prevent restoration of normal weight , involved
in restricted eating, purging behavior (self induced vomiting
, misuse of laxatives) , associated with fear of weight gain.
Low body weight or shape is central to the person’s self
evaluation.
BULIMIA NERVOSA
Bulimia: excessive, insatiable appetite (Hunger)
Nervosa: Indicates that due to emotional reason.
31.
BULIMIA NERVOSA
BulimiaNervosa is an episodic,
uncontrolled , compulsive, rapid
ingestion of large amount of
food over a short period of
time (bingeing), followed by
inappropriate compensatory
behavior to rid the body of the
excess calorie(purging)
32.
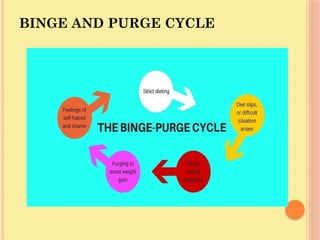
BINGE AND PURGECYCLE
Strict dieting
Craving
Binge –eating
Purging
Shame and disgust –
leads to strict dieting
and restart the cycle.
Prevalence and Incidence
Lifetime prevalence of bulimia nervosa is 1 % .
Prevalence among women is 1.5 % and 0.5% of
young men will suffer from bulimia nervosa.
The onset is often during adolescence, between
13 and 20 years of age.
Adolescents have self-imposed perfectionism and
compulsivity issues in eating compared to their
peers.
35.
CHARACTERISTIC FEATURES
Earlyteens or adolescents
Intense fear of being obese. There may be history of anorexia
nervosa.
Body image disturbance
Persistent preoccupation with eating, and an irresistible
craving for food.
Episode of binge eating
No known medical illness
Absence of psychiatric disorder.
36.
Recurrent episodesof
binge eating. An
episode of binge eating
is characterized by
both of the following:
A) eating in a discrete
period of time
B) a sense of lack of
control over eating
during the episode.
37.
Attempt to‘counteract’ the effects by inappropriate
compensatory behavior in order to prevent weight
gain, self induced vomiting ;misuse of laxatives,
diuretics, enemas, fasting, or excessive exercise.
The binge eating and inappropriate compensatory
behavior occurs, at least twice a week for 3 months.
Specific types:
Purging type: during the current episode of bulimia
nervosa, the person has regularly engaged in self-
induced vomiting or the misuse of laxative, diuretics,
or enemas.
Nonpurging type: during the current episode of
bulimia nervosa, the person has used other
inappropriate compensatory behaviors, such as
fasting, or excessive exercise.
38.
PHYSICAL SIGNS ANDSYMPTOMS
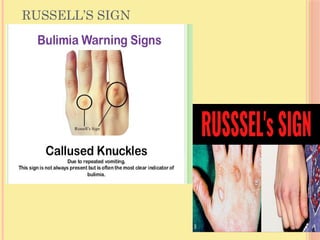
Calluses or scars on the knuckles or back of the hands
from sticking fingers down the throat to induce vomiting
over long period of time (Russell’s sign).
Bulimics who are capable of “hand free purging” induce
the vomiting by the use of pen, tooth brushes).
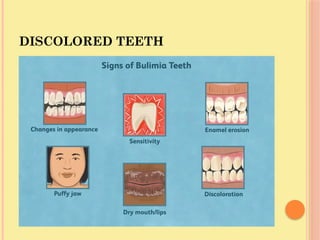
Puffy ‘chipmunk’ cheeks / faces (sialadinosis-swollen
salivary glands due to repeated exposure to stomach acid)
caused by repeated vomiting.
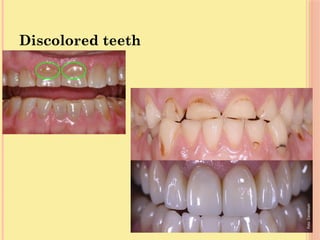
Discolored teeth from exposure to stomach acid when
throwing -up.
They may have normal weight or slightly overweight.
Frequent fluctuations in weight due to alternating
episodes of binge –eating and purging.
SEVERITY OF BULIMIA
NERVOSA(DSM-5)
Mild : an average of 1-3 episodes of
inappropriate compensatory behaviors per week.
Moderate : an average of 4-7 episodes of
inappropriate compensatory behaviors per week.
Severe : an average of 8-13 episodes of
inappropriate compensatory behaviors per week.
Extreme : an average of 14 or more episodes of
inappropriate compensatory behaviors per week.
44.
BULIMIA NERVOSA: WARNINGSIGNS
Wrappers/containers indicating consumption of large
amounts of food
Frequent trips to bathroom after meals
Signs of vomiting e.g. staining of teeth, calluses on hands
Excessive and rigid exercise routinely.
Withdrawal from usual friends/relatives
45.
HEALTH RISKS WITHBULIMIA
Dehydration and
electrolyte
imbalance
Dental problems
Stomach rupture
Menstruation
irregularities
Mood disorder,
anxiety disorder,
substance abuse etc.
46.
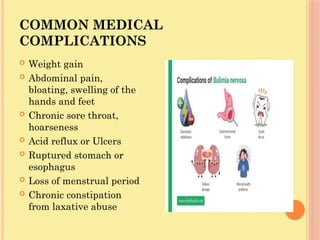
COMMON MEDICAL
COMPLICATIONS
Weightgain
Abdominal pain,
bloating, swelling of the
hands and feet
Chronic sore throat,
hoarseness
Acid reflux or Ulcers
Ruptured stomach or
esophagus
Loss of menstrual period
Chronic constipation
from laxative abuse
47.
DIAGNOSTIC CRITERIA
Acc. ToDSM-5:
Recurrent episodes of binge –eating that is
characterized by-eating large amount of food in a
discrete period of time (within 2 hours period) and a
sense of lack of control over eating during the episodes .
Recurrent inappropriate compensatory behaviors to
prevent weight gain, such as self induced vomiting,
misuse of laxatives, diuretics, fasting or excessive
exercise.
The binge-eating and inappropriate compensatory
behaviors both occur, at least once a week for 3 months.
Self-evaluation is improperly influenced by body shape
and weight.
48.
DIAGNOSTIC CRITERIA
Acc. ToICD-11:
Frequent, recurrent episodes of binge eating (once a week
or more over a period of at least one month).
Binge –eating episode.
Binge-eating is accompanied by repeated inappropriate
compensatory behaviors aimed at preventing weight gain .
Preoccupied with body shape or weight, strongly
influenced by self-evaluation.
Marked distress about pattern of binge –eating and
inappropriate compensatory behavior or significant
impairment in important areas of functioning.
Low body weight or shape is central to the person’s self
evaluation.
BINGE EATING DISORDER
Binge eating is
disorder in which
someone eats a
lot amount of
food at a time but
they don't vomit.
51.
DEFINITION
It ischaracterized by loses control over her
eating. Unlike bulimia nervosa, periods of binge
eating are not followed by purging and excessive
exercise or fasting.
As a result people with binge eating disorder are
often overweight or obese. They have risk of
developing cardiovascular disease and high blood
pressure. They also experience guilt, shame and
distress about their binge eating, which can lead
to more binge eating.
52.
BINGE EATING DISORDER:
WARNINGSIGNS
Wrappers/containers indicating consumption of
large amounts of food
MAY be overweight
MAY eat throughout the day with no planned
mealtimes
53.
HEALTH RISKS WITH
BINGEEATING DISORDER
High blood pressure
High cholesterol
Gall bladder disease
Diabetes
Heart disease
Certain types of cancer
54.
PREDISPOSING FACTOR
Biologicalinfluences:
Genetics- on the basis of family history
Chromosome abnormality: 1,2,13
• Neuroendocrine abnormalities :
- primary hypothalamic dysfunction in anorexia nervosa
- Elevated cerebrospinal fluid, cortical levels (proteolysis)
(released in response to stress or low blood-glucose
concentration).
- Impairment of dopaminergic regulation(brain dopamine
receptors –known for controlling movement, also for
weight and feeding behavior)
• Neurochemical influences:
- Neurotransmitter serotonin and nor epinephrine
- High level of endogenous opioids in the spinal fluids.
55.
Psychological influences:
-Personality traits- Perfectionist, overachievers, neuroticism,
negative emotionality, obsessive compulsiveness.
Low self-esteem
Feelings of inadequacy or failure
Feeling out of control
Response to change (puberty)
Response to stress
Personal illness
breakup.
56.
Psychodynamic influences:
Earlyand profound disturbances in mother –infant
interactions may results in retarded ego
development in child.
Troubled family and personal relationships
Difficulty in expressing emotions and feelings
History of being teased or ridiculed based on size
or weight
History of physical or sexual abuse
Social acceptance of thinness
Mass media- TV, magazines, advertising influences.
57.
• Family andsocial pressure:
- Participation in any activity: Gymnastic , modeling
Cultural pressures that glorify thinness and
place value on obtaining the perfect body
Narrow definitions of beauty that include only
women and men of specific body weights and
shapes.
Cultural norms that value people on the basis of
physical appearance and not inner qualities and
strengths.
58.
PSYCHODYNAMICS
Predisposing factorssuch as genetics, hypothalamic
dysfunction, unresolved childhood conflict in mother-child
relationship.
Underdeveloped ego
Precipitating factors, stressful situations, failure to fulfill
social expectations
Distorted cognitive self-assessment
Use of maladaptive coping mechanisms (distortion, denial,
regression, rationalization)
Abnormal eating behavior
59.
OBESITY
Obesity hasbeen defined as a body mass index
(BMI= weight/height2) of 30 or greater.
The following formula is used to determine extent of obesity
in individual:
BMI=Weight (kg)
Height (m)2
BMI range for normal weight is 18.5-24.9
Overweight= BMI of 25.0-29.9
Obesity= BMI of 30.0 or greater
American average women has BMI= 26
Fashion models=18
Anorexia nervosa=17.5
PREDISPOSING FACTORS TO
OBESITY
Biological influences:
-Genetics:
- Physiological factors: lesions in the appetite and
satiety centers in the hypothalamus may
contribute to overeating and obesity.
-hypothyroidism( thyroid helps in metabolism of
calories).
- Lifestyle factors: sedentary life style, ingestion
of greater no. of caloric food.
- Psychosocial influences: obese individual have
unresolved dependency needs and are fixed in
the oral stage of psychosexual development.
62.
TREATMENT MODALITIES:
Behaviormodifications along with cognitive therapies helps
the patient to confront irrational thinking and strands to
modify distorted and maladaptive cognitions about body
image and eating behaviors. Providing positive
reinforcement.
Individual therapy
Family therapy
Psychopharmacology: fluoxetine, clomipramine,
chlorpromazine, olanzapine ( antipsychotic), other
antidepressants: imipramine, desipramine, amitriptyline
etc.
Hospitalization: with adequate nursing care for food intake
and weight gain.
63.
GENERAL MANAGEMENT
Identificationof psychosocial stressors.
Environmental manipulation to deal with stress.
Teaching coping skills.
Psychotherapy
64.
PURGING DISORDER
Purgingdisorder is characterized by recurrent
purging (self-induced vomiting, misuse of
laxative, diuretics or enemas) to control weight or
shape in the absence of binge eating episodes
that occurs in people with normal or near-
normal weight.
65.
RUMINATION SYNDROME
Ruminationsyndrome or merycism is an
underdiagnosed chronic condition characterized
by effortless regurgitation of most meals
following consumption. There is no vomiting,
nausea, heartburn, odours or abdominal pains
associated with the regurgitation.
66.
Rumination syndromeis a condition in which
recently swallowed food comes back up into
the mouth without nausea, retching, or
vomiting. The food is then either re-chewed, re-
swallowed, or spit out. It is a functional
gastrointestinal disorder, meaning it occurs
because of abnormal function rather than a
structural disease.
67.
Symptoms
• Effortless regurgitationof undigested food within
10–30 minutes after eating
• Food tastes relatively normal because it has not
yet been digested
• Re-chewing and swallowing or spitting out the
regurgitated food
• Feeling of pressure or fullness in the upper
abdomen before regurgitation
• Bad breath
• Weight loss or poor weight gain (especially in
children or severe cases)
• Nutritional deficiencies in prolonged cases
68.
Causes
The exactcause is not always known, but it may
be associated with:
• A learned, involuntary habit of contracting the
abdominal muscles after meals
• Stress or anxiety
• Previous gastrointestinal illness
• It can occur in infants, children, adolescents, and
adults.
69.
Diagnosis
Diagnosis ismainly based on the clinical
history and symptom pattern. Doctors may
perform tests to rule out other conditions, such
as:
Repeated regurgitation of food for at least 1
month
• Upper gastrointestinal endoscopy
• Esophageal manometry
• pH monitoring
• Gastric emptying studies (if indicated)
70.
Treatment
The maintreatment is behavioral therapy,
especially:
• Diaphragmatic breathing (abdominal
breathing) during and after meals, which helps
prevent regurgitation.
• Habit-reversal training with a psychologist or
therapist.
• Stress management if anxiety is a contributing
factor.
• Nutritional counseling if there has been weight loss.
Medications are generally not very effective,
although they may be used if another
gastrointestinal condition is also present.
PICA DISORDER
Picais an eating disorder characterized by the
persistent craving and consumption of non-food
items (such as clay or chalk) that have no
nutritional value, often linked to nutritional
deficiencies or mental health conditions.
For these actions to be considered pica,
symptoms must persist for > 1 month at an age.
73.
WHAT IS PICA?
Pica is a psychologically compulsive eating
disorder where individuals consume substances
not intended as food, such as dirt, paint, hair,
chalk, or ice, over a period of at least one month.
The behavior is considered developmentally
inappropriate and not part of culturally
sanctioned practices. While occasional mouthing
of objects is normal in children under two, pica is
diagnosed when the behavior persists beyond this
age or causes health risks
74.
WHO IS AFFECTED?
Pica can occur at any age but is most commonly seen
in:
Young children, especially those over two years old
Pregnant women, often linked to nutritional deficiencies
Individuals with developmental or mental health
conditions, such as autism spectrum disorder, intellectual
disabilities, or schizophrenia. Certain environmental and
psychological factors, including stress, trauma, maternal
deprivation, or family instability, may increase the risk
75.
CAUSES AND RISKFACTORS
The exact cause of pica is not fully understood,
but several factors are associated with the
disorder:
Nutritional deficiencies, particularly iron or
zinc deficiency
Pregnancy, which may trigger cravings for non-
food items
Mental health conditions or developmental
disorders
Environmental stressors, such as poverty or
neglect
76.
COMMONLY INGESTED
SUBSTANCES
Peoplewith pica may consume a wide range of non-food items, often focusing on
one preferred substance, though multiple items can be involved. Common
examples include:
• Amylophasia- Consumption of starch
• Coprophagy-Consumption of feces-animal feces
• Geophasy- Consumption of soil, clay, chalk.
• Hyalophagia-Consumption of glass
• Consumption of dust or sand has been reported among iron-deficient patients.
• Mucophagia-Consumption of mucus
• Odowa- Soft stones eaten by pregnant women in Kenya
• Consumption of paint.
• Pagophagia- Pathological consumption of ice
• Self-cannibalism-Rare condition where body parts may be consumed
• Tricophagia- Consumption of hair or wool
• Urophagia- Consumption of urine
• Xylophagia- Consumption of wood or paper
77.
HEALTH RISKS
Picacan lead to serious complications depending
on the substances ingested:
Toxicity, such as lead poisoning from paint or
contaminated soil
Gastrointestinal issues, including obstruction,
perforation, or infection
Nutritional deficiencies, particularly iron
deficiency anaemia
Parasitic infections from contaminated soil or
feces
78.
DIAGNOSIS
There areno laboratory tests for pica.
Diagnosis is based on:
• Clinical history of persistent non-food ingestion
for at least one month
• Exclusion of culturally accepted practices
• Assessment for nutritional deficiencies, intestinal
blockages, or toxic exposure
79.
Treatment
Treatment focuseson addressing underlying causes and preventing
harm:
• Nutritional supplementation for deficiencies (iron, zinc)
• Behavioral therapy, including cognitive-behavioral approaches to
reduce cravings
• Aversive therapy, oral taste (lemon) smell sensation ( ammonia) and physical
sensation ( water mist in face)
• Environmental modifications, such as keeping non-food items out of
reach
• Positive reinforcement
• Discrimination training between edible and inedible items, with
negative consequences.
• Physical restraints and behavior modification: Self- protection devices
that prohibit placement of objects in mouth.
• Time-out contingent on pica being attempted
• Overcorrection, with attempted pica resulting in required washing of
self, disposal of nonedible objects and chore-based punishment.
• Negative practice- Non-edible object held against patient’s mouth
without allowing ingestion.
80.
• Monitoring andmedical care for complications
like poisoning or gastrointestinal issues
In children, pica often improves with age, but
persistent cases, especially in those with
developmental disorders, may require ongoing
support
NURSING INTERVENTION
Foranorexia nervosa:
Imbalanced nutrition/deficient fluid volume less
than body requirements related to refusal to
eat/ drink, severe fear of obesity self-induced
vomiting , abuse of laxatives as evidenced by loss
of weight, poor muscle tone, dry mucous
membrane.
Interventions:
1. Dietitian will determine number of calories
required to provide adequate nutrition.
2. Weight patient daily. Keep strict record of
intake and output.
86.
Stay withpatient during established time for
meal(usually 30 min) and for at least 1 hours
following meals.
If excessive weight loss occurs due to deterioration
in nutritional status, tube feedings will be initiated.
Encourage the patient to explore and identify the
true feelings and fears that contribute to
maladaptive eating behavior.
FOR BULIMIA NERVOSA:
2. Imbalanced nutrition more than body requirements :
1. Encourage the patient to keep a diary of food
intake.
2. Discuss feelings and emotions associated with
eating. Formulate an eating plan that includes food
from the required food groups with low-fat intake.
87.
Plan aprogressive exercise program tailored to
individual goals and choice. Exercise may enhance
weight loss by burning calories, reducing
appetite, increasing energies etc.
88.
With inputfrom the client, formulate an eating
plan with emphasis on low intake food.
Provide instruction about medications to assist
with weight loss. Appetite suppressant drugs:
phentermine and other that have weight loss as a
side effect e.g. : fluoxetine, topiramate.
89.
NURSING INTERVENTIONS: FOR
THEPATIENT WITH OBESITY
Assess the patient’s feeling and attitude about being obese.
Obesity and compulsive eating behavior may have deep rooted
psychological implications such as compensation for lack of love or
nurturing.
Determine the patient’s motivation for weight loss and set goals.
The individual may harbor repressed feelings of hostility, which
may be expressed inwardly on the self.
Help the patient identify positive self-attributes. Focus on
strengths and past accomplishment unrelated to physical
appearance.
Group therapy : support groups – increase motivation
Editor's Notes
#12 Individuals have a distorted body image that causes them to perceive themselves as overweight even when they are dangerously emaciated. They often lose large amount of weight stemming from refusal to eat, exercising compulsively or refusing to eat in front of others. Females experience loss of menstrual cycles & males may become impotent.
#29 Family & friends may have difficultly detecting bulimic behavior because many individuals keep these rituals very secretive and often maintain normal or above normal body weight.
#49 May be excessively overweight, but can maintain normal weight. Is different from bulimia because individuals do not purge their bodies after excessive intake of food. Individuals may consume large amounts of food throughout the day rather than just consuming large amounts of food only during binges.