info@medicoseacademics.com
0310-7990649
info@medicoseacademics.com
Respiratory Pathology
Dr. Sidra Arshad
Assistant Professor
Physiology
0310-7990649
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 2
A quick revision of:
1. Obstructive lung diseases – COPD, Asthma
2. Pulmonary infections – Pneumonia and Tuberculosis
3. Sarcoidosis
4. Pneumoconioses
5. Pulmonary neoplasms
6. Pleural effusion
7. ARDS
8. Pulmonary embolism and hypertension
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 3
• Obstructive lung diseases – airflow limitation due to narrowed or
obstructed airways
• Restrictive lung diseases - a decrease in lung volume or capacity due
to conditions that affect the lung parenchyma (lung tissue) or the
chest wall
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 4
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 5
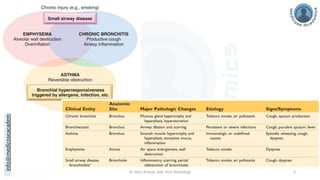
Emphysema
• Permanent enlargement of the air spaces distal to the terminal
bronchioles, accompanied by destruction of their walls without
significant fibrosis
• Four major types of emphysema:
(1) centriacinar
(2) panacinar
(3) distal acinar
(4) irregular
Significant
Airway obstruction
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 6
Types
of
Emphysema
Type Characteristics
Centrilobular • the damage is in the proximal portion of the acinus and the
cause is cigarette smoking
• more common and severe in the upper lobes
Panacinar • entire acinus and the common cause is alpha-1 antitrypsin
deficiency
• commonly in the lower lung zones
Distal acinar extension to the pleura  pneumothorax
Irregular
emphysema
• post-inflammatory scarring involves the acinus in an irregular
distribution
• although clinically asymptomatic, this may be the most
common form of emphysema
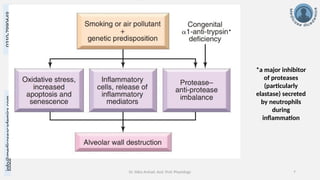
Destruction of alveolar septa  enlarged air spaces + loss of elastic recoil
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 7
*a major inhibitor
of proteases
(particularly
elastase) secreted
by neutrophils
during
inflammation
*
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 8
Chronic Bronchitis
• a productive cough that occurs during at least 3 consecutive months
over at least 2 consecutive years
• asthmatic bronchitis or as COPD (in cigarette smokers)
• Hypersecretion of mucus, hyperplasia of bronchial submucosal glands
• increased Reid index (>0.4), ratio of the thickness of the gland layer to
that of the bronchial wall
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 9
Pink puffers
• individuals with COPD
• related to severe airflow limitation
(emphysema)
• significant dyspnea (shortness of breath) and
increased work of breathing
• appear to be pink or flushed due to increased
respiratory effort and hyperventilation
• pursed-lip breathing and accessory respiratory
muscles to maintain adequate airflow
• relatively normal blood oxygenation at rest
• may have a more preserved body weight
compared to blue bloaters
Blue bloaters
• individuals with COPD
• symptoms related to chronic bronchitis and impaired
gas exchange
• chronic cough, excessive sputum production, and
recurrent respiratory infections
• Dyspnea less prominent  decreased respiratory drive
 retain carbon dioxide  bluish tint to their skin due
to cyanosis
• more severe airflow obstruction and impaired lung
function
• right-sided heart failure (cor pulmonale)
• retain fluid, leading to a bloated appearance
Dr. Sidra Arshad, Medicose Academics
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 10
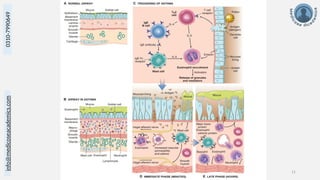
Asthma
Extrinsic/Immune asthma:
• mediated by a type I hypersensitivity response involving IgE bound to mast cells
• childhood
• a family history of allergy
Intrinsic/Non-immune asthma:
• chronic bronchitis
• exercise- or cold-induced asthma
• begins in adult life
• not associated with a history of allergy
Other types: drug induced, industrial
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 11
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 12
Morphologic Manifestations
• bronchial smooth muscle hypertrophy
• hyperplasia of goblet cells, increase in the size of submucosal glands
• thickening and hyalinization of basement membranes
• proliferation of eosinophils
• sub-basement membrane fibrosis
• intrabronchial mucous plugs containing:
1. whorl-like accumulations of epithelial cells (Curschmann spirals)
2. crystalloids of eosinophil-derived proteins galectin-10 (Charcot -Leyden crystals)
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 13
Bronchiectasis
• Permanent abnormal bronchial dilation caused by chronic infection, with
inflammation and necrosis of the bronchial wall
• Bronchial obstruction (tumor), chronic sinusitis with postnasal drip,
Kartagener syndrome
• Most often involves the lower lobes of both lungs
• Production of copious purulent sputum, hemoptysis, and recurrent
pulmonary infection that may lead to lung abscess
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 14
Cystic Fibrosis
• Autosomal recessive
• Nucleotide deletion on chromosome 7 – defective CFTR (Cl-
transporter)
• Lack of CFTR  a lack of fluid production + enhanced Na+ absorption through ENaC
causes increased fluid absorption thick mucus  obstructs the airways  airflow
limitation and reduced ability to exhale effectively
• Thick mucus mucus clearance impaired  growth of bacteria  chronic
inflammation, recurrent infections, and progressive lung damage
• Sweat chloride test – Cl-
> 60mEq/L
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 15
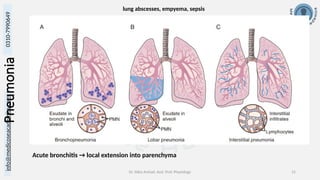
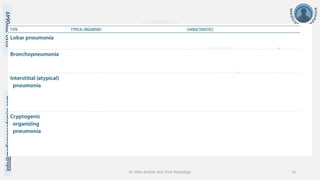
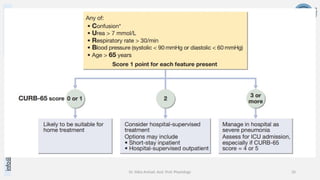
Pneumonia
Acute bronchitis → local extension into parenchyma
lung abscesses, empyema, sepsis
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 16
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 17
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 18
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 19
• Viral pneumonias are characterized by respiratory distress out of
proportion to the clinical and radiologic signs, and by inflammation
that is predominantly confined to alveolar septa, with generally clear
alveoli
• Common causes of viral pneumonia include influenza A and B,
respiratory syncytial virus, human metapneumovirus, parainfluenza
virus, and adenovirus.
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 20
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 21
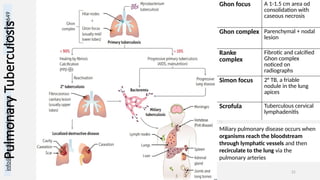
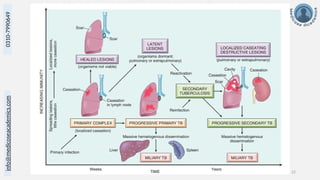
Pulmonary
Tuberculosis
Ghon focus A 1-1.5 cm area od
consolidation with
caseous necrosis
Ghon complex Parenchymal + nodal
lesion
Ranke
complex
Fibrotic and calcified
Ghon complex
noticed on
radiographs
Simon focus 2° TB, a friable
nodule in the lung
apices
Scrofula Tuberculous cervical
lymphadenitis
Miliary pulmonary disease occurs when
organisms reach the bloodstream
through lymphatic vessels and then
recirculate to the lung via the
pulmonary arteries
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 22
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 23
Interpretation of Mantoux test/PPD/TST
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 24
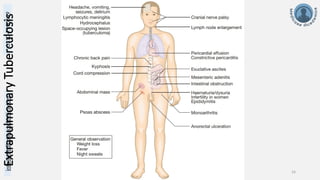
Extrapulmonary
Tuberculosis
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 25
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 26
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 27
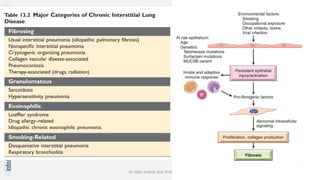
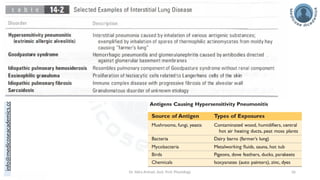
Sarcoidosis
• Unknown etiology, elevated serum ACE levels, and elevated CD4+/CD8+ ratio in bronchoalveolar lavage fluid
• Immunologic abnormalities include high levels of CD4+ TH1 cells in the lung that secrete cytokines such as
IFN-γ
• On biopsy:
• Non-necrotizing epithelioid granuloma
• noncaseating granulomas/Schumann bodies [laminated dystrophic calcification]
• asteroid bodies [stellate giant cell cytoplasmic inclusions])
• no pathognomonic microscopic features
• X-ray studies frequently show bilateral hilar lymphadenopathy
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 28
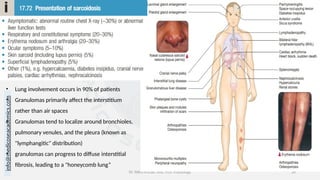
• Lung involvement occurs in 90% of patients
• Granulomas primarily affect the interstitium
rather than air spaces
• Granulomas tend to localize around bronchioles,
pulmonary venules, and the pleura (known as
"lymphangitic" distribution)
• granulomas can progress to diffuse interstitial
fibrosis, leading to a "honeycomb lung”
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 29
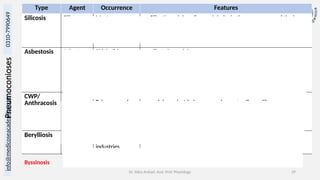
Pneumoconioses Type Agent Occurrence Features
Silicosis Silica Most common,
foundries,
sandblasting
mines
• Silicotic nodules - fine nodularity in the upper zones of the lung
• Eggshell calcification of hilar lymph nodes on CXR
• Associated with an increased susceptibility to tuberculosis
Asbestosis Asbestos Shipbuilders,
plumbers
• affects lower lobes
• diffuse interstitial fibrosis
• asbestos bodies/ferruginous bodies, hyalinized fibrocalcific
plaques of the parietal pleura
• pleural effusion
• bronchogenic carcinoma
• malignant mesothelioma (pleural/peritoneal)
CWP/
Anthracosis
Coal dust Coal miners
Tobacco smokers
• characterized by the presence of coal macules and larger coal
nodules – dust-laden macrophages + collagen fibers
• the upper lobes and upper zones of the lower lobes are more
heavily involved
• Coal workers' pneumoconiosis, prolonged exposure upper
lobes, dark black scars, emphysema
Berylliosis Beryllium Aerospace and
manufacturing
industries.
• Granulomatous (noncaseating)
• Increased risk of cancer and cor pulmonale
Byssinosis
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 30
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 31
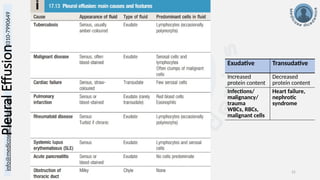
Exudative Transudative
Increased
protein content
Decreased
protein content
Infections/
malignancy/
trauma
WBCs, RBCs,
malignant cells
Heart failure,
nephrotic
syndrome
Pleural
Effusion
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 32
ARDS • Diffuse damage of alveolar epithelium and capillaries  progressive respiratory failure 
unresponsive to oxygen treatment
• Diffuse alveolar damage (DAD) to describe the pathologic changes
• May be caused by shock, sepsis, trauma, gastric aspiration, radiation, oxygen toxicity,
drugs, or pulmonary infection
• Activated neutrophils  cell damage
• Dyspnea, tachypnea, hypoxemia, cyanosis, and use of accessory respiratory muscles
• X-rays: bilateral lung opacity WHITE OUT
• Gross: heavy, stiff, and noncompliant
• Microscopically: intra-alveolar edema + hyaline membranes line the alveolar spaces
• Overall mortality 40%
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 33
Pneumothorax
Primary spontaneous
pneumothorax
Rupture of apical subpleural bleb or cysts; in tall, thin,
young males
Secondary
spontaneous
pneumothorax
Diseased lung, barotrauma
Traumatic
pneumothorax
Blunt or penetrating trauma
Tension
pneumothorax
Any of the above causes
Air enters pleural space but cannot exit
Trachea deviates away from the affected lung
Immediate needle decompression and chest tube
placement
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 34
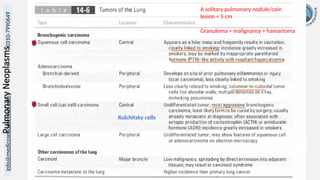
Pulmonary
Neoplasms
Kulchitsky cells
A solitary pulmonary nodule/coin
lesion < 5 cm
Granuloma > malignancy > hamartoma
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 35
Pancoast tumor
• Occurs in the apex of the lung
• Pancoast syndrome – invasion of cervical sympathetic chain
• Compression of locoregional structures causes:
i. Recurrent laryngeal nerve  hoarseness
ii. Superior cervical ganglion  Horner syndrome
iii. Superior vena cava  SVC syndrome
iv. Sensorimotor deficit
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 36
Pulmonary Emboli
• More than 95% of all pulmonary emboli arise from
thrombi within the large deep veins of the legs,
most often those that have propagated to involve
the popliteal vein and larger veins above it
• Risk factors:
1. prolonged bed rest (particularly with
immobilization of the legs)
2. surgery, especially orthopedic surgery on the
knee or hip
3. severe trauma (including burns or multiple
fractures)
4. congestive heart failure
5. in women, the period around parturition or the
use of OCPs with high estrogen content
• emboli can result in hemorrhagic, or red,
infarcts, usually in patients with
compromised circulation, but embolism can
occur without infarction because of the
dual blood supply to the lungs
• most emboli (60% to 80%) are clinically
silent
• a minority (5%, typically large “saddle
emboli”) cause acute right-sided heart
failure, shock, or sudden death
• the remainder cause pulmonary infarction
• Lines of Zahn are interdigitating areas of
pink (platelets, fibrin) and red (RBCs) found
only in thrombi formed before death; help
distinguish pre- and postmortem thrombi
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 37
Embolism Type Characteristics Causes Features Occurrence Timeline
Pulmonary
Embolism
Blockage of
pulmonary artery by
blood clot
Deep vein
thrombosis (DVT),
clot from leg or
pelvis
Shortness of breath,
chest pain, coughing up
blood
Can occur suddenly
or gradually
Arterial Embolism
Obstruction of an
artery by an
embolus, arise from
a mural thrombus
Blood clot, fat, air,
or foreign material
travels to artery
Sudden pain, pale or
blue skin, decreased
pulse
Rapid onset, sudden
Fat Embolism
Fat globules in
bloodstream, often
after trauma
Fractures,
orthopedic surgery,
severe burns
Respiratory distress,
petechiae, altered
mental status
Within 24-72 hours
after trauma/surgery
Air Embolism
Air bubbles enter
blood vessels
Medical
procedures, diving
accidents
Chest pain, difficulty
breathing, neurological
symptoms
Immediate after air
entry
Amniotic Fluid
Embolism
Entry of amniotic
fluid into maternal
circulation
Labor, delivery
complications
Sudden respiratory
distress, cardiac arrest,
seizures
During labor or
shortly after birth
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 38
Pulmonary Hypertension
• Defined as pressures of 25 mm Hg or more at rest may be caused by a decrease in the cross-
sectional area of the pulmonary vascular bed or, less commonly, by increased pulmonary
vascular blood flow
• WHO classification:
1. Pulmonary arterial hypertension
2. Pulmonary hypertension due to left-sided heart disease
3. Pulmonary hypertension due to lung diseases and/or hypoxia
4. Chronic thromboembolic pulmonary hypertension
5. Pulmonary hypertension with unclear or multifactorial mechanisms
• all forms of pulmonary hypertension are associated with medial hypertrophy of the
pulmonary muscular and elastic arteries, pulmonary arterial atherosclerosis, and right
ventricular hypertrophy
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 39
1. Pulmonary embolism
mostly occurs by:
a. Left mural thrombi
b. Atherosclerosis
c. DVT
d. Infective endocarditis
2. Which of the following
enzyme’s activity is
increased in emphysema?
a. Elastase
b. Collagenase
c. Protease
d. Lipase
3. Most common cause of
cor pulmonale is?
a. Bronchogenic tumor
b. COPD
c. Pneumonia
d. Pulmonary
hypertension
4. Sarcoidosis is diagnosed
microscopically by:
a. Granuloma with
asteroid
b. Non-caseating
granuloma
c. Caseating granuloma
d. Macrophages and giant
cells
5. Carbon-laden
macrophages are present
in:
a. Anthracosis
b. Asbestosis
c. Silicosis
d. Byssinosis
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 40
Thank you.
Please contact us for your questions and queries.
info@medicoseacademics.com
0310-7990649
https://www.facebook.com/medicoseacademics/
https://www.instagram.com/medicoseacademics/
https://twitter.com/MedicoseAcad
https://www.youtube.com/@MedicoseAcademics