info@medicoseacademics.com
0310-7990649
Reproductive Pathology- I
Dr. Sidra Arshad
Assistant Professor
Physiology
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 2
A quick revision of:
1. Disorders of sex development
2. Abnormalities of male reproductive system
3. Complications of pregnancy
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 3
Differences between males and females exist at three sex levels:
1. Genetic/chromosomal – presence or absence of Y chromosome
2. Gonadal – presence of either testes or ovaries
3. Phenotypic – external genitalia
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 4
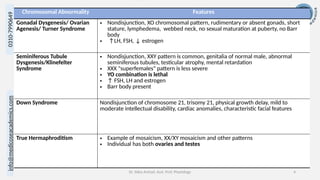
Chromosomal Abnormality Features
Gonadal Dysgenesis/ Ovarian
Agenesis/ Turner Syndrome
• Nondisjunction, XO chromosomal pattern, rudimentary or absent gonads, short
stature, lymphedema, webbed neck, no sexual maturation at puberty, no Barr
body
• ↑LH, FSH, ↓ estrogen
Seminiferous Tubule
Dysgenesis/Klinefelter
Syndrome
• Nondisjunction, XXY pattern is common, genitalia of normal male, abnormal
seminiferous tubules, testicular atrophy, mental retardation
• XXX "superfemales" pattern is less severe
• YO combination is lethal
• ↑ FSH, LH and estrogen
• Barr body present
Down Syndrome Nondisjunction of chromosome 21, trisomy 21, physical growth delay, mild to
moderate intellectual disability, cardiac anomalies, characteristic facial features
True Hermaphroditism • Example of mosaicism, XX/XY mosaicism and other patterns
• Individual has both ovaries and testes
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 5
Hormonal Disorders
• Chromosomal sex is normal and so is the gonadal sex, however,
phenotypic sex is abnormal
• Manifests as pseudohermaphrodotism
• A pseudohermaphrodite is an individual with the genetic constitution
and gonads of one sex and the genitalia of the other
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 6
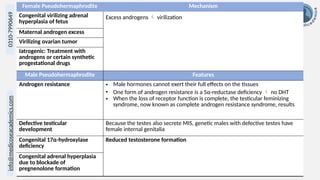
Female Pseudohermaphrodite Mechanism
Congenital virilizing adrenal
hyperplasia of fetus
Excess androgens  virilization
Maternal androgen excess
Virilizing ovarian tumor
Iatrogenic: Treatment with
androgens or certain synthetic
progestational drugs
Male Pseudohermaphrodite Features
Androgen resistance • Male hormones cannot exert their full effects on the tissues
• One form of androgen resistance is a 5α-reductase deficiency  no DHT
• When the loss of receptor function is complete, the testicular feminizing
syndrome, now known as complete androgen resistance syndrome, results
Defective testicular
development
Because the testes also secrete MIS, genetic males with defective testes have
female internal genitalia
Congenital 17α-hydroxylase
deficiency
Reduced testosterone formation
Congenital adrenal hyperplasia
due to blockade of
pregnenolone formation
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 7
5α-reductase Deficiency
• Autosomal recessive condition
• Limited to genetic males with 46,XY
• Inability to convert testosterone to DHT
• Ambiguous genitalia present until puberty
• Increased testosterone during puberty leads to
masculinization and increased growth of
external genitalia
• Testosterone and estrogen levels are normal
• LH is normal or increased
• Internal genitalia are normal
Kallmann Syndrome
• A form of hypogonadotropic hypogonadism
• Failure to complete puberty
• Caused by defective migration of GnRH-releasing
neurons, leading to the failure of GnRH-releasing
olfactory bulbs to develop
• Results in decreased synthesis of GnRH in the
hypothalamus
• Common symptoms include hyposmia/anosmia
(reduced or absent sense of smell)
• Decreased levels of GnRH, FSH, LH, and testosterone
• Infertility is common, with low sperm count in males
and amenorrhea (absence of menstruation) in females
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 8
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 9
Penile Carcinoma
• SCC
• Association with HPV, lack of circumcision
• Precursor in situ lesion:
• Bowen disease – penile shaft, leukoplakia
• Erythroplasia of Queyrat – glans penis, erythroplakia
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 10
Cryptorchidism:
• Failure of testes to descend from the abdomen into the scrotum at or
near the time of the birth of the fetus
• Descent occurs in the last 2-3 months of gestation under the influence
of fetal testosterone
• Descent is incomplete on one or, less commonly, both sides in 10% of
newborn males, with the testes remaining in the abdominal cavity or
inguinal canal
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 11
• Even the few degrees’ higher temperature in the abdomen than in the
scrotum is sufficient to cause degeneration of the tubular epithelium
and, consequently, to cause sterility
• If testes are normally developed, surgical placement of testicles into
the scrotum can be carried out – orchiopexy
• Gonadotropic hormone treatment speeds descent in some cases
• High incidence of malignant tumors in undescended testes compared
to scrotal testes
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 12
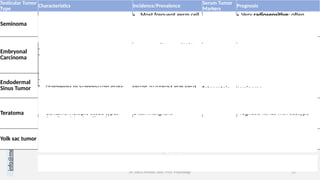
Testicular Tumor
Type
Characteristics Incidence/Prevalence
Serum Tumor
Markers
Prognosis
Seminoma
• Malignant germ cell tumor
• Analogous to dysgerminoma
(ovary tumor)
• Most frequent germ cell
tumor (40%)
• Peak incidence in mid-
30s age group
Sometimes
increased
hCG
• Very radiosensitive; often
curable
• Even with abdominal lymph
node metastasis
Embryonal
Carcinoma
• Malignant germ cell tumor
• Analogous to a similar tumor in the
ovary
• Second most common
germ cell tumor (20%-
30%)
• Presenting conditions
may include pain or
metastasis
Often
increased
hCG
Worse prognosis compared to
seminoma
Endodermal
Sinus Tumor
• Malignant germ cell tumor
• Analogous to endodermal sinus
tumor of the ovary
Most common testicular
tumor in infancy and early
childhood
Increase in
serum α-
fetoprotein
(AFP)
Associated with hepatocellular
carcinoma
Teratoma
• Germ cell tumor derived from two
or more embryonic layers
• Contains multiple tissue types
(cartilage islands, ciliated
epithelium, liver cells, etc.)
Often malignant - Prognosis varies with subtype
Yolk sac tumor • Yellow, mucinous
• Schiller – Duval bodies (glomeruli)
Most common tumor in
boys < 3 years
AFP
Aggressive, analogous to ovarian
yolk sac tumor
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 13
Testicular Tumor Type Characteristics Incidence/Prevalence
Serum Tumor
Markers
Prognosis
Choriocarcinoma
• Malignant germ cell tumor
• Analogous to choriocarcinoma
of the ovary
• Incidence peaks in
second to third decades
• Histologic
characteristics include
syncytiotrophoblasts
and cytotrophoblasts
Increase in
serum hCG
Can occur as part of other
germ cell tumors
Mixed Germ Cell
Tumors
• Consist of varying
combinations of germ cell
tumor types
• Tumors can be
teratocarcinoma, combining
teratoma and embryonal
carcinoma (poor prognosis)
• Other combinations include
teratoma, embryonal
carcinoma, and seminoma
Prognosis determined by
the least mature element
AFP, hCG, LDH Good
Leydig Cell Tumor
Non-germ cell tumor derived
from testicular stroma
Most often benign None
Associated with precocious
puberty (children) and
gynecomastia (adults)
Lymphoma is the
most common
testicular tumor
in older adults
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 14
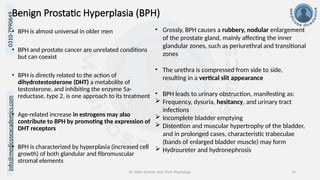
Benign Prostatic Hyperplasia (BPH)
• BPH is almost universal in older men
• BPH and prostate cancer are unrelated conditions
but can coexist
• BPH is directly related to the action of
dihydrotestosterone (DHT) a metabolite of
testosterone, and inhibiting the enzyme 5a-
reductase, type 2, is one approach to its treatment
• Age-related increase in estrogens may also
contribute to BPH by promoting the expression of
DHT receptors
• BPH is characterized by hyperplasia (increased cell
growth) of both glandular and fibromuscular
stromal elements
• Grossly, BPH causes a rubbery, nodular enlargement
of the prostate gland, mainly affecting the inner
glandular zones, such as periurethral and transitional
zones
• The urethra is compressed from side to side,
resulting in a vertical slit appearance
• BPH leads to urinary obstruction, manifesting as:
 Frequency, dysuria, hesitancy, and urinary tract
infections
 Incomplete bladder emptying
 Distention and muscular hypertrophy of the bladder,
and in prolonged cases, characteristic trabeculae
(bands of enlarged bladder muscle) may form
 Hydroureter and hydronephrosis
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 15
Prostatic Adenocarcinoma
• Prostate cancer is predominantly found in older individuals
• From posterior lobe mostly
• The tumor's behavior can vary from slow-growing (indolent) to aggressive, with
the Gleason grading system used to predict aggressiveness based on
differentiation
• Diagnosis is commonly made through rectal examination
• Early-stage prostate cancer is associated with an increase in serum prostate-
specific antigen (PSA)
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 16
• Increased serum prostatic acid
phosphatase may indicate the
tumor has penetrated the capsule
and invaded adjacent tissues
• Prostate adenocarcinoma often
progresses to bony osteoblastic
metastasis, which can be the
presenting sign, increased ALP
• In cases of disseminated prostate
cancer, endocrine therapy may be
effective, as tumor growth is
partially influenced by androgens
• PSA > 10 ng/ml – highly
predictive of carcinoma
• Between 4-10 ng/ml – overlap
b/w early carcinoma and BPS
• ↑ bound-PSA – carcinoma
• PSA doubling time ∝
1/aggressiveness of the tumor
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 17
Hydatidiform mole
• Hydatidiform mole (molar pregnancy) is a tumor
of placental trophoblastic tissue
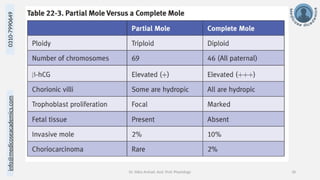
• Complete mole results from a fertilized ovum
with no chromosomal material, with all genetic
material coming from sperm  no embryo
• Partial mole results from fertilization of an ovum
by two sperms, resulting in a triploid cell (69,
XXY)  embryo develops for a few weeks
• Invasive mole is a mole that invades the uterine
wall
• Symptoms include excessive uterine
enlargement, vaginal bleeding, passage
of grape-like soft tissue, and elevated
beta-human chorionic gonadotropin (β-
hCG) levels
• Microscopic features include
edematous chorionic villi, trophoblast
proliferation, and possible fetal tissue
in partial mole
• Diagnosis is made using ultrasound
(U/S)
• Treatment involves endometrial
curettage and monitoring β-hCG levels
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 18
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 19
Pregnancy
Complications Abruptio
placentae
• Premature separation of placenta from uterine wall before delivery
• Risk factors: trauma, smoking, hypertension, preeclampsia, cocaine
abuse
• Presentation: abrupt, painful bleeding in third trimester; may lead to
DIC, maternal shock, and fetal distress
• Life-threatening for both mother and fetus
Morbidly
adherent
placenta
• Defective decidual layer leads to abnormal attachment and separation
after delivery
• Risk factors: prior C-section or uterine surgery, inflammation, placenta
previa, advanced maternal age, multiparity
• Three types based on depth of penetration:
• Placenta accreta: attaches to myometrium without penetrating it;
most common type
• Placenta increta: penetrates into myometrium
• Placenta percreta: penetrates through myometrium and into uterine
serosa; may attach to rectum or bladder
• Presentation: often detected on ultrasound before delivery
• No separation of placenta after delivery leads to postpartum bleeding
and can cause Sheehan syndrome
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 20
Placenta
previa
• Placenta attaches to the lower uterine segment over or very close to the
internal cervical os
• Risk factors: multiparity, prior C-section
• Associated with painless third-trimester bleeding
• A "preview" of the placenta is visible through the cervix
Vasa previa • Fetal blood vessels run over or very close to the cervical os
• May lead to vessel rupture, severe bleeding, and fetal death
• Presents with the triad of membrane rupture + painless vaginal bleeding
+ fetal bradycardia (heart rate < 110 beats/min)
• Emergency C-section is usually necessary
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 21
Ectopic Pregnancy
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 22
Hypertension
in
Pregnancy Condition Definition and Features Incidence and Risk Factors Complications
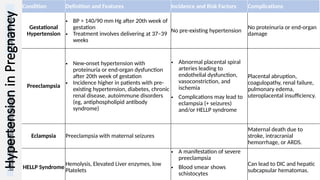
Gestational
Hypertension
• BP > 140/90 mm Hg after 20th week of
gestation
• Treatment involves delivering at 37–39
weeks
No pre-existing hypertension
No proteinuria or end-organ
damage
Preeclampsia
• New-onset hypertension with
proteinuria or end-organ dysfunction
after 20th week of gestation
• Incidence higher in patients with pre-
existing hypertension, diabetes, chronic
renal disease, autoimmune disorders
(eg, antiphospholipid antibody
syndrome)
• Abnormal placental spiral
arteries leading to
endothelial dysfunction,
vasoconstriction, and
ischemia
• Complications may lead to
eclampsia (+ seizures)
and/or HELLP syndrome
Placental abruption,
coagulopathy, renal failure,
pulmonary edema,
uteroplacental insufficiency.
Eclampsia Preeclampsia with maternal seizures
Maternal death due to
stroke, intracranial
hemorrhage, or ARDS.
HELLP Syndrome
Hemolysis, Elevated Liver enzymes, low
Platelets
• A manifestation of severe
preeclampsia
• Blood smear shows
schistocytes
Can lead to DIC and hepatic
subcapsular hematomas.
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 23
Thank you.
Any questions?