REVIEW OF LITERATURE
Abey P Rajan
2nd Year MPT
Department of Orthopedic physiotherapy
KLEU Institute Of Physiotherapy1
CONTENTS
• Introduction
• History
• Levels Of Lower Extremity Amputation
• Prosthesis in Partial Foot Amputation
• -Ankle Disarticulation
• -Transtibial Amputation
• -Knee Disarticulation
• -Trans femoral Amputation
• -Hip Disarticulation And Trans pelvic Amputation
• References
2
INTRODUCTION
AMPUTATION:
• Amputation is the intentional surgical removal of a limb or
body part. It is performed to remove diseased tissue or
to relieve pain.
• Major lower limb amputation is a commonly performed
procedure that is indicated in patients with failed attempts at
revascularization, comorbidity or anatomic factors
precluding revascularization efforts, and extensive tissue
loss or infection. (3)
3
Causes:
1. Peripheral vascular disease
2. Trauma
3. Malignancy
4. Infections
5. Congenital deficiency
• In India, trauma is the most common cause of lower
limb amputation, but amputations for complications of
diabetes is on the rise and may be the leading aetiology
in future. (2) 4
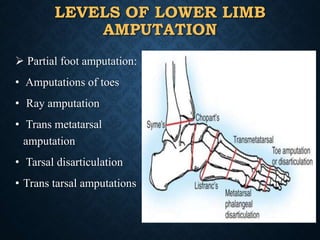
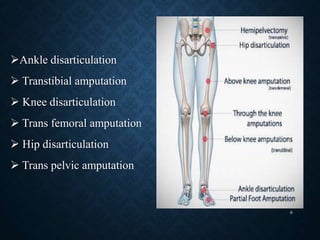
LEVELS OF LOWER LIMB
AMPUTATION
 Partial foot amputation:
• Amputations of toes
• Ray amputation
• Trans metatarsal
amputation
• Tarsal disarticulation
• Trans tarsal amputations
5
Ankle disarticulation
 Transtibial amputation
 Knee disarticulation
 Trans femoral amputation
 Hip disarticulation
 Trans pelvic amputation
6
• Prosthesis: Is an artificial device that replaces a
missing body part.
• Prosthetist: Health care professional who designs,
fabricates and fits limb prosthesis.
7
HISTORY OF PROSTHESIS
• The earliest example of a prosthesis
ever discovered is the great toe ,
found in Egypt dated to between
950-710 B.C
• In early 16th century Ambroise Pare
developed the first hinged prosthetic
hand, and a leg with a locking knee
joint.
• Prosthetic development took
technological leaps during the
American civil war in the 20th
century where the ‘Hanger limb’ and
suction sock for lower limb
amputees were invented.
8
• From then till date
advancements in prosthetic
technology brought about
many functional and aesthetic
improvements making it easier
to use and more acceptable in
the community.
9
PARTIAL FOOT PROSTHESIS
• Prescribed for toe amputation, trans-metatarsal amputation and
tarsal disarticulation.
PURPOSE:
• To restore foot function, particularly in walking, as much as
possible
• To replicate the shape of the missing foot segment.
10
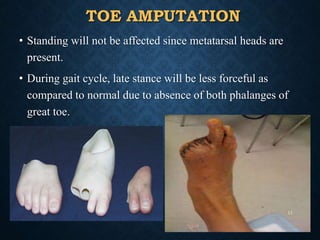
TOE AMPUTATION
• Standing will not be affected since metatarsal heads are
present.
• During gait cycle, late stance will be less forceful as
compared to normal due to absence of both phalanges of
great toe.
11
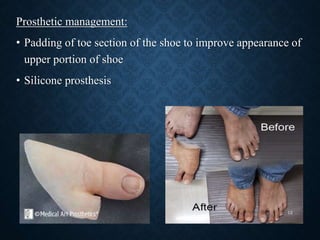
Prosthetic management:
• Padding of toe section of the shoe to improve appearance of
upper portion of shoe
• Silicone prosthesis
12
Limitations:
• Current prosthetic technology cannot effectively restore
active push-off during late stance of the gait cycle.(9)
Dillon, MP. Biomechanical models for the analysis of partial foot amputee gait.
Doctoral thesis, Queensland University of Technology, 2015
[http://adt.library.qut.edu.au/adt-qut/public- QUT20011008.094224/].
13
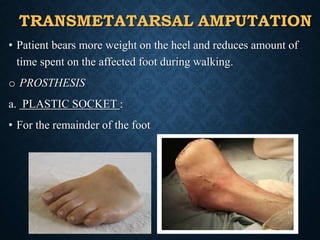
TRANSMETATARSAL AMPUTATION
• Patient bears more weight on the heel and reduces amount of
time spent on the affected foot during walking.
o PROSTHESIS
a. PLASTIC SOCKET :
• For the remainder of the foot
14
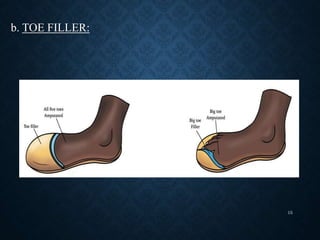
b. TOE FILLER:
15
• Instrumented gait studies have concluded that trans
metatarsal amputees are unable to generate normal plantar
flexion power during late stance, despite having a mobile
ankle and a much larger foot remnant remaining.
Gerald Stark. Clinical Biomechanics of the Partial Foot Amputation; ACPOC News
2012 Vol 18, (1). 5-19.
http://www.acpoc.org/newsletters-and-journals/2012_01_005.asp
16
TARSAL DISARTICULATON
• Lisfranc & Choprat disarticulations
• The foot length decreasing further due to equinus deformity
of the amputated limb resulting from unbalanced contraction
of triceps surae.
17
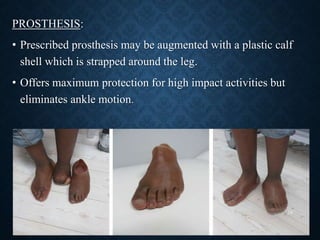
PROSTHESIS:
• Prescribed prosthesis may be augmented with a plastic calf
shell which is strapped around the leg.
• Offers maximum protection for high impact activities but
eliminates ankle motion.
18
SYME’S AMPUTATION
PROSTHESIS :-
Syme’s prosthesis-
• Syme’s prosthesis is suspended by the contour of its brims and
socket walls, ordinarily without any other suspension
mechanism.
• Syme’s amputation is an
amputation done through the
ankle joint, removal of the entire
foot but the calcaneal fat pad will
be preserved.
19
FLEX SYMES :
• Made of carbon fiber.
• The heel stores energy after
initial contact, thus slowly
releasing it at midstance. The
forward momentum generated
by this action results in the toe
being loaded for optimum
energy release at terminal
stance.
20
LO RIDER FOOT :
• Made of carbon fiber
• Flexible during heel off
• Appropriate for amputees with
low activity level as well as for
older individuals.
21
FUNCTIONS:-
• Restores normal contour of patient’s foot
• Absorbs shock at heel contact
• Plantar flexes in early stance
*Made of carbon fiber which is lighter and stronger than wood.
22
PROSTHESTIC FOOT ANKLE
ASSEMBLIES
• Artificial foot designed to replace many of the functions of
the anatomic human foot.
Categories:-
• Non-articulating feet
• Articulating – (a)Single-axis (b)Multi-axis
• Dynamic response/ Energy storing designs
• Microprocessor controlled feet
23
Single-axis:-
• Permit motion about the one plane of the joint axis
• Modern single-axis foot is composed of a keel with a moulded
rubber foot shell.
• Most single-axis allow up to 15 degree plantar flexion and 5-7
degree of dorsiflexion.
24
Multi-axis:-
• Allows foot inversion and eversion while increasing stability
and comfort on non-level surfaces.
• Offers coronal and transverse plane motion in addition to
motion in sagittal plane.
• Maintain maximum contact with the walking surface,
irrespective of even or uneven terrains
25
PROPRIO FOOT
• Includes electronic sensors to detect when the wearer needs
movements.
• It also provides greater ankle excursions than other foot ankle
assemblies and reduces pressure on the amputated limb
LIMITATIONS :
• Less durable
• Heavier
26
27
• A study was done by Agrawal V et.al in 2013 on Comparing
microprocessor-controlled ankle/foot and conventional prosthetic feet
during stair negotiation in people with unilateral transtibial
amputation. The purpose of the study was to compare Symmetry in
External Work (SEW) between a microprocessor-controlled foot and
conventional prosthetic feet with unilateral transtibial amputation
during stair ascent and descent, 10 subjects were evaluated while
wearing three conventional prosthetic feet—solid ankle cushion heel
(SACH), stationary attachment flexible endoskeleton (SAFE) and the
Proprio foot ,were given a 10- to 14-day period with each foot. The
study concluded that during stair ascent with unilateral TTA, the
microprocessor-controlled Proprio foot resulted in greater work
symmetry than conventional prosthetic feet.(5)
O'Toole C. Comparison between microprocessor-controlled ankle/foot and conventional
prosthetic feet during stair negotiation in people with unilateral transtibial amputation.
Journal of rehabilitation research and development. 2013 Aug 10;50(7):941.
28
C-WALK
• Consist of:
• The C-spring and base spring are dynamically linked by a
control ring. This systematic interaction allows the user to walk
comfortably and dynamically.
29
FLEX FOOT-CHEETAH XTREME
• Made of carbon fiber, designed specifically for the fast, short-
distance sprints. The dynamic shape allows the foot to flex more
offering a powerful energy kick. A longer, flatter toe enhances push
off, while the plantar-flexed pylon supports better forward
progression.
 Active Tibial Progression
• Vertical forces generated at blade during contact with the ground are
stored and translated into a linear motion described as Active Tibial
Progression. This action reduces the need to actively push the body
forward using the contralateral foot and also equalizes stride length.
Benefit: More natural gait and reduced running effort.
30
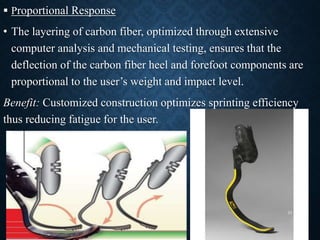
 Proportional Response
• The layering of carbon fiber, optimized through extensive
computer analysis and mechanical testing, ensures that the
deflection of the carbon fiber heel and forefoot components are
proportional to the user’s weight and impact level.
Benefit: Customized construction optimizes sprinting efficiency
thus reducing fatigue for the user.
31
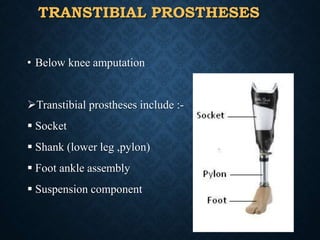
TRANSTIBIAL PROSTHESES
• Below knee amputation
Transtibial prostheses include :-
 Socket
 Shank (lower leg ,pylon)
 Foot ankle assembly
 Suspension component
32
SOCKET
• The amputation limb fits into a plastic receptacle called the
socket.
• Provide a comfortable interface
for the transmission of body
weight.
• Provide stability during stance
phase.
• Allow sufficient control for
mobility.
• Protect the residual limb soft
tissue.
• Contribute to suspension of the
prosthesis
33
SUSPENSION :-
• The method of connecting a prosthesis to residual limb
• Suspension designed according to activity level, comfort and
safety
Types of suspension :-
i. Vacuum
ii. Shuttle lock
iii. Suction
iv. Magnetic Prosthetic Suspension system
v. Osseous integration
34
►Vacuum Suspension
• A sleeve creates a seal around the top edge of the socket, then
a pump and exhaust valve remove virtually all air between the
socket and the liner. The system regulates the vacuum level
within a defined range. Vacuum enhances how well the socket
adheres to the limb, which reduces shear, regulates residual-
limb volume changes and improves circulation of the affected
limb. 35
• Samitier et. al conducted a study in 2016 on the benefits of
using a vacuum-assisted socket system to improve balance
and gait in elderly transtibial amputees. Study included 16
transtibial amputees aged 50 years and more. The subjects
were initially assessed using their prosthesis with the regular
socket and re-evaluated 4 weeks after fitting including the
vacuum-assisted socket system. The study concluded that
vacuum-assisted socket systems are useful for improving
balance, gait, and transfers in over-50- year-old transtibial
amputees.(8)
Samitier CB, Guirao L, Costea M, Camós JM, Pleguezuelos E. The benefits of using a
vacuum-assisted socket system to improve balance and gait in elderly transtibial amputees.
Prosthetics and orthotics international. 2016 Feb;40(1):83-8. 36
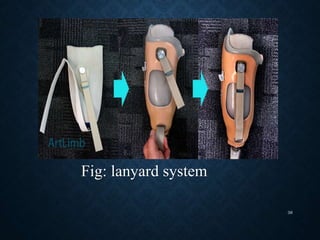
► Shuttle lock Suspension:-
• In this case, use a padded liner with a pin at the end. The pin is
inserted into a shuttle lock built into the bottom of the socket,
the only connection point. One variation for above-knee
prostheses, called a lanyard system, uses a strap to pull the
liner into the socket. The lanyard also connects the socket to
the liner near the top, which slightly reduces rotation and
shear.
37
Fig: lanyard system
38
► Suction Suspension :-
• A suction system consists of a soft liner, a one-way valve and a
sealing sleeve. Inserting the liner-covered limb into the socket
and applying body weight as the wearer stand expels excess air
through the valve. Suction provides even adhesion to the entire
interior surface of the socket for security, stability and reduced
friction and shear.
39
► Magnetic Prosthetic Suspension system :-
• Magnetic coupling device, which holds the residual part of the
limb inside the prosthesis. It consist of 3 parts:
a. A metal plate inside the socket
b. A magnetic assembly
c. A switch
• After donning the prosthetic soft liner the user puts the stump
inside the prosthesis. The switch is in the on mode. The
magnetic field will hold and retain the stump within the
prosthesis.
• While removing the prosthesis the user need to switch to off
mode. 40
• A study done by Michael P et. al in 2015 on Comparison of a New
Prosthetic Suspension System with Two Existing Suspension
Systems for Lower Limb Amputees. The objective of the study
were to compare magnetic suspension system with that of 2
existing suspension methods on pistoning inside the socket and
perceived problems among transtibial amputees. Study included 10
transtibial amputees. The participants used each of the three
prosthesis for 1 months in random order. The study concluded that
the new system showed compatible prosthetic suspension with the
other two systems (suction & pin lock). The satisfaction with
donning and doffing was high with the magnetic system and the
subjects reported fewer problems with the new system.(7)
Dillon MP, Richardson AJ, Hafner BJ. Re:“ Comparison of a New Prosthetic Suspension
System with Two Existing Suspension Systems for Lower Limb Amputees”. American
journal of physical medicine & rehabilitation. 2015 Jul 1;94(7):e59-60.

41
Osseous Integration :-
• Osseous integration refers to a direct structural and functional
connection between living bone and a prosthetic
device. Osseous integration eliminates the need for a
traditional socket-type prosthesis by surgically implanting a
rod in the bone that can connect to any prosthesis through an
external connection.
42
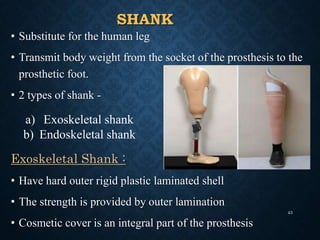
SHANK
• Substitute for the human leg
• Transmit body weight from the socket of the prosthesis to the
prosthetic foot.
• 2 types of shank -
Exoskeletal Shank :
• Have hard outer rigid plastic laminated shell
• The strength is provided by outer lamination
• Cosmetic cover is an integral part of the prosthesis
a) Exoskeletal shank
b) Endoskeletal shank
43
• Weight of the prosthesis is heavier than Endoskeletal design
• Appropriate for person who will be using the same prosthesis
for many years.
Endoskeletal Shank :
• The Endoskeletal shank consist of a central aluminium or
rigid plastic tube (pylon) usually covered with foam rubber
and a sturdy stocking.
• More natural in appearance than exoskeletal shank
• More comfortable and easy walking.
44
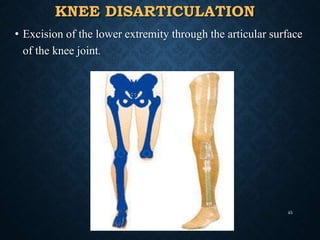
KNEE DISARTICULATION
• Excision of the lower extremity through the articular surface
of the knee joint.
45
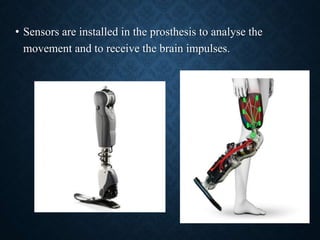
SYMBIONIC LEG
• Combination of microprocessor controlled knee and
microprocessor controlled ankle.
• Increased the symmetry during gait cycle
• Powered toe off
• Increased stumble recovery
• Good ground clearance
• Stability while walking on variable terrains
• Extension lock mechanism for knee
46
• Sensors are installed in the prosthesis to analyse the
movement and to receive the brain impulses.
47
TRANSFEMORAL PROSTHESES
• Individuals with amputation between the femoral condyles
and greater trochanter are fitted with transfemoral prostheses
(above knee).
• The transfemoral prosthesis consist of :-
1. Socket
2. Knee Unit
3. Shank/Pylon
4. Foot-ankle assembly
5. Suspension device
48
Foot Ankle Assembly
1. Single axis foot:-
• More commonly used as it reaches foot flat position with
minimal application of weight bearing load.
• Wearers of transfemoral prosthesis do not load the prosthesis
vigorously hence, less energy would be stored in a dynamic
response foot; hence energy storing is not preferred.
49
Shank
• Endoskeletal is preferred over exoskeletal
a) More pleasing appearance
b) Adjustable in alignment
c) Light weight
• Rotator with or without shock absorber incorporated in the
shank to diminish shear stress on the amputation limb.
50
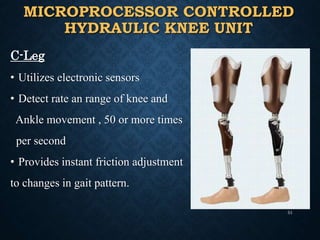
MICROPROCESSOR CONTROLLED
HYDRAULIC KNEE UNIT
C-Leg
• Utilizes electronic sensors
• Detect rate an range of knee and
Ankle movement , 50 or more times
per second
• Provides instant friction adjustment
to changes in gait pattern.
51
• Units programmed with
computer provides
a. Stumble recovery
b. Locking option
c. Accommodation to
walking on various
terrains
d. Bicycle riding
52
• A study was done by Seymour. R in 2007 to compare the
energy expenditure, obstacle course performance and quality of
life in C-Leg microprocessor-controlled prosthetic knee users
and non-microprocessor controlled prosthetic knee users. The
study included 13 subjects with unilateral limb loss (12 with
trans-femoral and one with a knee disarticulation amputation)
and concluded that C-leg users have less energy expenditure,
comparatively higher obstacle course performance and better
quality of life.
Seymour R, Engbretson B, Kott K, Ordway N, Brooks G, Crannell J, Hickernell E, Wheeler
K. Comparison between the C-leg® microprocessor-controlled prosthetic knee and non-
microprocessor control prosthetic knees: A preliminary study of energy expenditure, obstacle
course performance, and quality of life survey. Prosthetics and orthotics international. 2007
Mar;31(1):51-61.
53
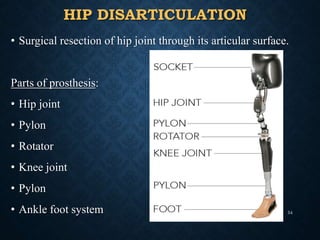
HIP DISARTICULATION
• Surgical resection of hip joint through its articular surface.
Parts of prosthesis:
• Hip joint
• Pylon
• Rotator
• Knee joint
• Pylon
• Ankle foot system 54
HELIX 3-D
• All currently known joints only
execute movements in a single plane.
This means that the natural
simultaneous movement of hip
flexion / extension and pelvic
rotation is not reproduced. The Helix
3-D joint has manual locking
mechanisms or spring-driven
extension mechanisms as well as
extension stops. Swing-through
phase initialisation is not supported
by currently known designs.
55
Biomechanical improvements for the prosthesis wearer
compared to conventional joints:
– More stable hip movements during weight transfer
– Support for swing-through phase initialisation
– Control of hip movements during the swing-through phase
– Three-dimensional movements in terms of the relationship
between hip joint extension / flexion and transversal pelvic
rotation.
56
• Specialised hydraulics control the level of stance and swing-
through phase resistance in this hip joint. The hydraulics offer a
total of three adjustable parameters:
• – Stance phase damping
• – Free swing-through phase
• – Swing-through phase damping
• The Helix3D Hip Joint System is suitable for hip disarticulation
and hemi-pelvectomy amputees.
• For amputees with mobility Grades 2 and 3
• Maximum body weight: 100 kg/220 lbs 57
• Ludwigs. E et.al done a study in 2010 on Biomechanical
differences between two prosthetic hip joint systems during
level walking. The objective of the study was to compare two
different prosthetic hip joints: The Helix3D and The 7E7. The
study analyzed the gait pattern of 6 hip disarticulation amputee
subjects, Kinematics and kinetics of the gait were recorded by
an optoelectronic camera system and force plates. The result of
the study show that the Helix3D Hip Joint can reduce gait
abnormalities compared to the 7E7 hip joint.
Ludwigs E, Bellmann M, Schmalz T, Blumentritt S. Biomechanical differences between two
prosthetic hip joint systems during level walking. Prosthetics and orthotics international.
2010 Dec;34(4):449-60.
58
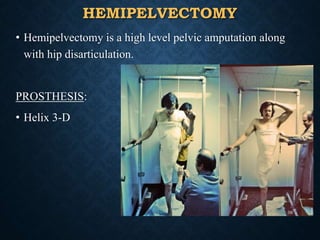
HEMIPELVECTOMY
• Hemipelvectomy is a high level pelvic amputation along
with hip disarticulation.
PROSTHESIS:
• Helix 3-D
59
REFERENCES
1. Young AJ, Simon AM, Fey NP, Hargrove LJ. Intent recognition in a powered
lower limb prosthesis using time history information. Annals of biomedical
engineering. 2014 Mar 1;42(3):631-41.
2. Maqsood M, Ali N, Bhat A, Bangroo FA, Dhanda MS, Singh R. Current trends
of major lower limb amputations at a tertiary care centre of Jammu, India.
International Journal of Medical Science Research and Practice. 2015 Jun
30;2(2):77-80.
3. Aulivola B, Hile CN, Hamdan AD, Sheahan MG, Veraldi JR, Skillman JJ,
Campbell DR, Scovell SD, LoGerfo FW, Pomposelli Jr FB. Major lower
extremity amputation: outcome of a modern series. Archives of Surgery. 2004
Apr 1;139(4):395-9.
4. Susan B. O’Sullivan, Thomas J.Schmitz, George D.Fulk.Physical
Rehabilitation,Chapter 31, Prosthetics; Jaypee Brothers Medical Publishers (p)
Limited,New Delhi, 5th Edition,2014.
60
5. Parent A, Pouliot-Laforte A, Laberge M, Hamdy R, Rochelle R, Ballaz L.
Articulated vs. fixed carbon-fibre prosthesis after transmetatarsial amputation:
a case study. Computer methods in biomechanics and biomedical engineering.
2014 Aug 6;17:106-7
6. O'Toole C. Comparison between microprocessor-controlled ankle/foot and
conventional prosthetic feet during stair negotiation in people with unilateral
transtibial amputation. Journal of rehabilitation research and development.
2013 Aug 10;50(7):941.
7. Dillon MP, Richardson AJ, Hafner BJ. Re:“ Comparison of a New Prosthetic
Suspension System with Two Existing Suspension Systems for Lower Limb
Amputees”. American journal of physical medicine & rehabilitation. 2015 Jul

1;94(7):e59-60
8. Samitier CB, Guirao L, Costea M, Camós JM, Pleguezuelos E. The benefits of
using a vacuum-assisted socket system to improve balance and gait in elderly
transtibial amputees. Prosthetics and orthotics international. 2016
Feb;40(1):83-8
61
9. Dillon MP, Richardson AJ, Hafner BJ. Re:Comparison of a New Prosthetic
Suspension System with Two Existing Suspension Systems for Lower Limb
Amputees”. American journal of physical medicine & rehabilitation. 2015 Jul

1;94(7):59-60.
10. Mihelle M.Lusardi, Caroline C. Nielsen. Orthotics and Prosthetics in
rehabilitation, Chapter 24-26.Butterworth-Heinmann publications,USA,1st
Edition, 2000.

11. Seymour R, Engbretson B, Kott K, Ordway N, Brooks G, Crannell J, Hickernell
E, Wheeler K. Comparison between the C-leg® microprocessor-controlled
prosthetic knee and non-microprocessor control prosthetic knees: A preliminary
study of energy expenditure, obstacle course performance, and quality of life
survey. Prosthetics and orthotics international. 2007 Mar;31(1):51-61.
12. Gerald Stark. Clinical Biomechanics of the Partial Foot Amputation; ACPOC
News 2012 Vol 18, (1). 5-19.
62
63