1
PRIMARY HEALTH CARE
Dr. Priyanka
(PG 2nd Year)
Public health dentistry
SGT university
2
CONTENTS
Introduction
Levels of health care
Changing concepts
Historical evolution
Definition
Elements
Principles
Primary Health care in India
Current scenario
Conclusion
References 3
INTRODUCTION
• Health has been declared as a fundamental human right.
• Health care is multitude of services provided to
individuals or communities by agents of health services
or professions, for the purpose of promoting,
maintaining, monitoring or restoring health.
4
5
• The best way to provide health care
to the vast majority of underserved
rural people and urban poor is to
develop effective "primary health
care" services supported by an
appropriate referral system.
LEVELS OF HEALTH CARE
Primary Secondary Tertiary
6
Primary care level
First level of contact of individuals, the family and
community with the national health system.
7
Secondary care level
Patients from primary health care are referred to
specialists in higher hospitals for treatment. In India, the
health centres for secondary health care include District
hospitals and Community Health Centre at block level.
8
Tertiary care level
Refers to a third level of health system, in which
specialized consultative care is provided.
This care is provided by the regional or centre level
institutions.
9
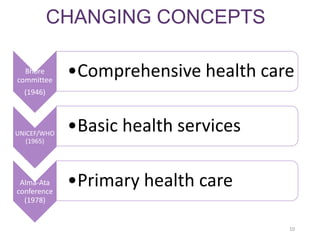
CHANGING CONCEPTS
Bhore
committee
(1946)
•Comprehensive health care
UNICEF/WHO
(1965)
•Basic health services
Alma-Ata
conference
(1978)
•Primary health care
10
Comprehensive Health Care
The term “Comprehensive Health Care” was first used by
Bhore committee in 1946.
• It meant provision of integrated preventive, curative and
promotional health services from “womb to tomb” to
every individual residing in a defined geographic area.
11
• Bhore committee suggested that comprehensive
health care should replace the policy of providing
more medical care.
• This concept formed the basis of national health
planning in India and led to the establishment of a
network of primary health centers and sub-centers.

12
Basic health services
UNICEF/WHO in their joint health policy used this term “Basic
health services”
• It is defined as “ A basic health service is understood to be a
network of coordinated, peripheral and intermediate health
units capable of performing effectively a selected group of
functions essential to health of an area and assuring the
availability of competent professional and auxiliary personnel
to perform these functions” 13
• Shortcomings of both these approaches
1) Lack of community participation
2) Lack of inter-sectoral co-ordination
3) Dissociation from the socio-economic aspects of health.
14
Primary health care approach
• A new approach to health care came into existence in
1978 following an international conference at Alma-Ata
(USSR) this is called as “primary health care approach”
• It has all the hallmarks of a primary health care delivery as
first proposed by Bhore committee in 1946 and now
espoused by world wide by international agencies and
national governments.
15
HISTORICAL EVOLUTION OF HEALTH CARE
IN INDIA
16
1967, Jungalwalla Committee
1962, Mudaliar Committee
1952, Community Development Programme
1946, Bhore committee
Pandve HT, Pandve TK. Primary healthcare system in India: Evolution and challenges.
International Journal of Health System and Disaster Management. 2013 Jul 1;1(3):125.
17
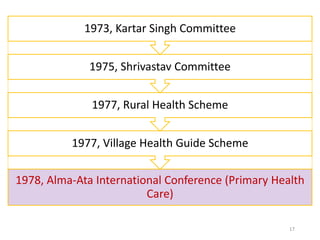
1978, Alma-Ata International Conference (Primary Health
Care)
1977, Village Health Guide Scheme
1977, Rural Health Scheme
1975, Shrivastav Committee
1973, Kartar Singh Committee
18
The International conference co-sponsored by WHO &
UNICEF, held in Alma Ata, from 6th-12th Sep 1978, finalized
on 12th Sep 1978.
19
1983, India’s National Health Policy
2005, National Rural Health Mission
https://mohfw.gov.in/documents/policy
2018, Astana Global conference on Primary health care
2013, National Health Mission
2nd conference on Primary Health Care
20
Selective Primary Health Care
21
Cueto M. The origins of primary health care and selective primary health care.
American journal of public health. 2004 Nov;94(11):1864-74.
22
PRIMARY HEALTH CARE
23
ELEMENTS OF PRIMARY HEALTH CARE(Alma-Ata Declaration)
E– Education concerning prevailing health problems and the methods of
identifying, preventing and controlling them.
L– Locally endemic disease prevention and control.
E– Expanded programme of immunization against major infectious diseases.
M– Maternal and child health care including family planning.
E– Essential drugs arrangement.
N– Nutritional food supplement, an adequate supply of safe and basic
nutrition.
T– Treatment of communicable and non-communicable disease and
promotion of mental health.
S– Safe water and sanitation. 24
• The Declaration of Astana, adopted at the conference,
makes pledges in four key areas:
(1) Make bold political choices for health across all
sectors;
(2) Build sustainable primary health care;
(3) Empower individuals and communities; and
(4) Align stakeholder support to national policies,
strategies and plans.
25
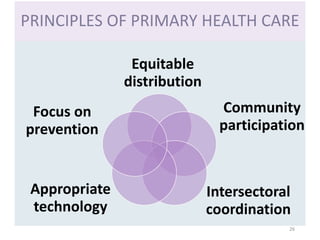
PRINCIPLES OF PRIMARY HEALTH CARE
26
Equitable
distribution
Community
participation
Intersectoral
coordination
Appropriate
technology
Focus on
prevention
Equitable distribution
The first key principle is
• EQUITY: Health care must be shared equally by all
the people irrespective of their ability to pay and all
(urban/rural, rich/poor) must have access to them.
28
• Social injustice: Health services are mainly
concentrated in the major towns and cities resulting in
inequality of care to the people in rural areas. The
worst hit are the needy and vulnerable groups of the
population in rural areas and urban slums.
29
• PHC aims to redress this imbalance by shifting the
centre of gravity of the health care system from cities
(where three-quarters of the health budget is spent) to
the rural areas (where three-quarters of the people
live), and bring these services as near people's homes
as possible.
Community participation
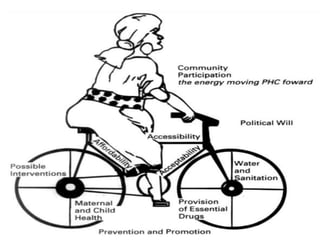
• Universal coverage by primary health care cannot be
achieved without the involvement of the local
community.
• There must be a continuing effort to secure meaningful
involvement of the community in the planning,
implementation and maintenance of health services,
besides maximum reliance on local resources such as
manpower, money and materials.
31
• One such approach in India is use of village health guides
and trained Dais, who are selected by the community and
trained locally in delivery of services to the community they
belong, free of cost.
• By overcoming cultural and communication barriers, they
provide primary health care in ways that are acceptable to
the community.
32
Intersectoral coordination
• Declaration of Alma-Ata states that “Primary health
care involves in addition to the health sector, all
related sectors and aspects of national and
community development, in particular agriculture,
animal husbandry, food, industry, education,
housing, public works, communication and other
works. This requires strong political will.”
34
To achieve such cooperation:
• Countries may have to review their administrative
system,
• reallocate their resources; and
• introduce suitable legislation to ensure that
coordination can take place
VALUES ACTION
POLITICAL WILL
Appropriate technology
• “Technology that is scientifically sound, adaptable
to local needs, and acceptable to those for whom it
is used, and that can be maintained by the people
themselves in keeping with the principle of self
reliance with resources the community and the
country can afford.”
36
• "appropriate" is emphasized because in some
countries, large luxurious hospitals that are totally
inappropriate to the local needs, are built, which
absorb a major part of the national health budget,
effectively blocking any improvement in general
health services.
Focus on prevention
37
• Health services should not only be curative but
should also promote health and healthy lifestyles
with emphasis on prevention.
PRIMARY HEALTH CARE IN INDIA
38
HEALTH CARE SYSTEMS
1. Public Health sector
• Primary health care – Primary health centre and Sub
centre
• Hospitals/health centers – CHCs, Rural hospitals,
District hospitals/Health centers , Specialist hospitals,
Teaching hospitals
• Health insurance schemes – Employees State
Insurance, Central Government Health Scheme
• Other agencies - Defense services, Railways.
39
2. Private sector
• Private hospitals, polyclinics, nursing homes and dispensaries
• General practitioners and clinics.
3. Indigenous systems of medicine
• Ayurveda and Siddha
• Unani and Tibbi
• Homeopathy
• Unregistered practitioners
4. Voluntary Health Agencies
5. National Health Programmes
40
PRIMARY HEALTH CARE SYSTEMS
•Village level
•Sub centre level
•Primary health centre level
41
VILLAGE LEVEL
42
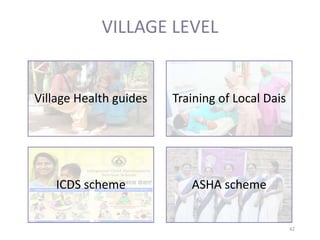
Training of Local DaisVillage Health guides
ICDS scheme ASHA scheme
43
Village health guides
Scheme introduced on 2nd Oct. 1977.
• Village health guide is a person with an aptitude for social
service and is not a full time Govt. functionary.
• The scheme was launched in all states except Kerala,
Karnataka, Tamilnadu, Arunachal Pradesh and J & K which
had alternative systems (e.g. mini-health centers in
Tamilnadu) of providing health services at village level.
44
Their assigned duties include simple activities in
• first aid,
• mother & child health and family planning,
• health education and sanitation and
• medical care of common illnesses according to the
manual and
• patient referral to nearest health centre if needed.
45
Local Dais
An extensive program has been undertaken, under the
rural health scheme(2005), to train all categories of
local dais (traditional birth attendants) in the country to
improve their knowledge in elementary concept of
MCH care, sterilization and obstetric skills.
46
• Training period- 30 working days.
• Training location - PHC, subcentre or MCH centre for 2
days in a week
• During her training each dai is required to conduct at
least 2 deliveries under the guidance and supervision
of the HW (F), ANM or HA (F).
Integrated Child Development Scheme
• ICDS services are offered through a network
of anganwadi centers.

• Number of operating anganwadi centres in September,2017:-
All india: 13,56,569
 In Haryana: 25962
47
https://icds-wcd.nic.in/icdsdatatables.aspx
48
The beneficiaries are especially
• nursing mothers.

• pregnant women,
• other women (15-45 years),
• children below the age of 6 years and adolescent
girls
Along with Village Health Guides, anganwadi workers
are the community's primary link with the health
services and all other services for young children.

Duties:
• Health check up
• Immunization
• Supplementary
nutrition
• Health education
• Non formal pre school
education
49
50
• Accredited social health activist
• community health worker
• Instituted by the government of India's Ministry of
Health and Family Welfare (MoHFW)
• As a part of the National Rural Health Mission (NRHM).
• The mission began in 2005.
ASHA
51
Requirements:
• She must be the resident of the village - a woman (married /
widow / divorced)
• preferably in the age group of 25-45 years
• with formal education up to eighth class, having
communication skills and leadership qualities.
Duties:
• Counsel women.
• Facilitating access to health services.
• Comprehensive village health plan.
• Primary medical care
• Depot holder for essential provisions.
• Inform about births, deaths, unusual health
problems.
• Promote construction of household toilets.
52
Sub centre level
53
• Sub-Centers (SC) is the most peripheral outpost of
the existing health delivery system in rural areas.
• A Sub-centre provides interface with the
community at the grass-root level, providing all the
primary health care services.
Functions:
• Immunization
• Antenatal, natal and postnatal care
• Prevention of childhood diseases.
• Family planning services.
• Elementary drugs.
• National and family welfare programmes.
54
Categorization
55
• They have been categorized into two types - Type A
and Type B.
• Categorization has taken into consideration various
factors namely catchment area, health seeking
behavior, case load, location of other facilities like
PHC/CHC/Hospitals in the vicinity of the Sub-centre.
Type A
56
i. Sub-centres not having adequate space and physical infrastructure
for conducting deliveries
ii. Sub-centres situated in the vicinity of other higher health facilities
like PHC/CHC/FRU/Hospital, where delivery facilities are available.
ii. Sub-centres in headquarter area
iii. Sub-centres where at present no delivery or occasional delivery
may be taking place i.e. very low case load of deliveries.
If the case load increases, these Sub-centres should be considered for
up gradation to Type B.
57
• This would include following types of Sub-centres:
i. Centrally or better located Sub-centres with good
connectivity to catchment areas.
ii. They have good physical infrastructure preferably with
own buildings, adequate space, residential
accommodation and labour room facilities.
iii. They already have good case load of deliveries from the
catchment areas.
iv. There are no nearby higher level delivery facilities.
Type B (MCH Sub-Centre)
58
• Minimum requirements at sub-centre for meeting the
IPHS
1. Maternal health care
2. Child health care
3. Family Planning and contraception
4. Counselling and appropriate referral for safe abortion
service
5. Adolescent health care: Education, counselling and
referral.
6. Assistance to school health services.
7. Water quality monitoring.
59
8. Promotion of sanitation including use of toilet and appropriate
garbage disposal.
9. Field visits by appropriate health workers for disease surveillance,
family welfare services including STI, RTI awareness.
10. Community need assessment.
11. Curative services for minor ailments including fever, diarrhoea,
worm infestation and first-aid. appropriate and prompt referral if
needed.
60
12. To organize Village Health and Nutrition Day at least
once in a month.
13. Training of Traditional Birth Attendants and ASHA
community health volunteers.
14. Co-ordinate services of anganwadi workers, ASHA,
village
health and sanitation committee
15. National health programmes.
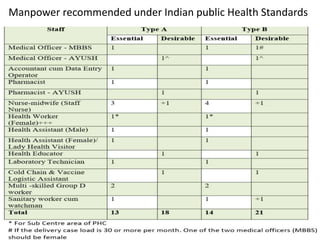
Manpower recommended under Indian Public Health
Standards (IPHS)
61
62nhm.gov.in
63
• Primary Health Centre is the cornerstone of rural health
services- a first port of call to a qualified doctor of the
public sector in rural areas for the sick and those who
directly report or referred from Sub-Centres for curative,
preventive and promotive health care.
PRIMARY HEALTH CENTRE LEVEL
CATEGORIZATION
64
From Service delivery angle, PHCs may be of two types, depending upon
the delivery case load – Type A and Type B.
• Type A PHC: PHC with delivery load of less than 20 deliveries in a
month,
• Type B PHC: PHC with delivery load of 20 or more deliveries in a month
The services have been classified as Essential (Minimum Assured Services)
or Desirable (which all States/UTs should aspire to achieve at this level of
facility).
65
• Minimum requirements at PHC for meeting the IPHS:
1. Medical care
2. Maternal and Child Health Care Including Family
Planning
3. Medical Termination of Pregnancies
4. Management of Reproductive Tract
Infections/Sexually Transmitted Infections
5. Nutrition Services (coordinated with ICDS)
6. School Health
66
7. Adolescent Health Care
8. Promotion of Safe Drinking Water and Basic
Sanitation
9. Prevention and control of locally endemic diseases
like malaria, Kala Azar, Japanese Encephalitis etc.
9. Collection and reporting of vital events.
10.Health Education and Behaviour Change
Communication
11.Other National Health Programmes
67
12.Training to undergraduate, ASHAs, Doctors and
paramedics Basic Laboratory and Diagnostic Services
13.Functional Linkages with Sub-Centres
14. Mainstreaming of AYUSH
15.Selected Surgical Procedures
16.Maternal Death Review (MDR).
17. Record of Vital Events and Reporting
68
Manpower recommended under Indian public Health Standards
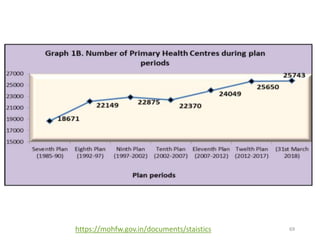
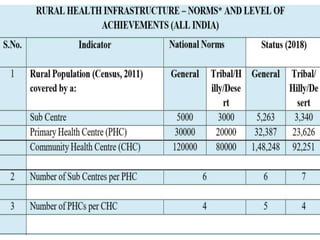
69https://mohfw.gov.in/documents/staistics
70
71
• In Gurgaon district , as on 5 April, 2016 there are :
• 3 CHC; Farukhnagar, Pataudi, Ghangola
• 13 PHC; Ghangola, Borakalan, Badshahpur, Bhangrola,
Mandpura, Kasan, Gurgaon village, Garhi-harsaru, Bhondsi,
Wazirabad, Pataudi, Farukhnagar, Daultabad
• 76 Sub-centres.
DISTRICTWISE COMMUNITY HEALTH CENTRES / PRIMARY HEALTH CENTRES / SUB
CENTRES IN HARYANA. Health department of Haryana.
http://haryanahealth.nic.in
• National Urban Health Mission (NUHM) as a sub-mission
under the National Health Mission (NHM) (1st may, 2013)
Under the Scheme the following proposals have been
approved :
1. 1 Urban Primary Health Centre (U-PHC) for every 50,000
population.
2. 1 Urban Community Health Centre (U-CHC) for5 to 6 U-
PHCs in big cities.
3. 1 Auxiliary Nursing Midwives (ANM) for 10,000
population.
4. 1 Accredited Social Health Activist ASHA (community link
worker) for 200 to 500 households.
72
India. Department of Health and Family Welfare. National Urban Health Mission‐ Framework for
implementation. New Delhi: Ministry of Health and Family Welfare Government of India; May
2013.
• Urban Primary Health Centre (UPHC), Krishna Nagar
Gamri, District Kurukshetra Of Haryana Has Become
The First UPHC In The Country Which Has Got “Quality
Certification” Under National Quality Assurance
Standards (NQAS).
73
https://prharyana.gov.in
India’s rank in the Human Development Index Report
2018 (130 out of 189 countries) issued by the UNDP
depicts the level of ignorance of the health sector in a
country like India.
74
https://www.indiaspend.com/budget-2018-indias-healthcare-crisis-is-
holding-back-national-potential-29517/
http://hdr.undp.org/en/2018-update
India spends 1.4% of GDP on health, less than Nepal,
Sri Lanka
Where does India stand?
75
Primary healthcare failing, tertiary care centres
overburdened
• In 2016, sub-centres were 20% short of human resources, while
primary and community health centres were 22% and 30% short,
respectively, according to the 2016 Rural Health Statistics(RHS).
• Most functioning rural health facilities in India lack basic
infrastructure–29% of sub-centres did not have regular water
supply, 26% lacked electricity supply and 11% did not have all-
weather roads connecting them, according to the 2016 RHS data.
76
• Primary health centres (PHCs) are supposed to be the first point
of contact between the village and a medical officer. Each PHC is
manned by a medical officer and 14 paramedical staff, and is
supposed to be equipped with an operation theatre, six beds,
essential laboratory facilities and a pharmacy.
• While 63% of primary health centres did not have an operation
theatre and 29% lacked a labour room, community health centres
were short of 81.5% specialists–surgeon, gynecologists and
pediatricians.
77
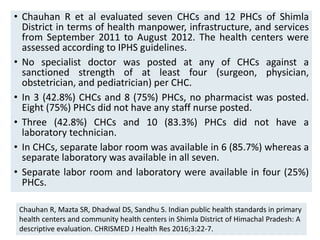
• Chauhan R et al evaluated seven CHCs and 12 PHCs of Shimla
District in terms of health manpower, infrastructure, and services
from September 2011 to August 2012. The health centers were
assessed according to IPHS guidelines.
• No specialist doctor was posted at any of CHCs against a
sanctioned strength of at least four (surgeon, physician,
obstetrician, and pediatrician) per CHC.
• In 3 (42.8%) CHCs and 8 (75%) PHCs, no pharmacist was posted.
Eight (75%) PHCs did not have any staff nurse posted.
• Three (42.8%) CHCs and 10 (83.3%) PHCs did not have a
laboratory technician.
• In CHCs, separate labor room was available in 6 (85.7%) whereas a
separate laboratory was available in all seven.
• Separate labor room and laboratory were available in four (25%)
PHCs.
78
Chauhan R, Mazta SR, Dhadwal DS, Sandhu S. Indian public health standards in primary
health centers and community health centers in Shimla District of Himachal Pradesh: A
descriptive evaluation. CHRISMED J Health Res 2016;3:22-7.
• Sodani PR, Sharma K identified the existing gap with respect to
Indian Public Health Standards (IPHS) for availability of
infrastructure, human resources, investigative services and
essential newborn care services at 24 × 7 primary health centers
(PHCs) of Bharatpur district of Rajasthan state.
The study depicted that the availability of human resources,
infrastructure and facilities for newborn care services at the 24 ×
7 PHCs were not satisfactory as per the prescribed IPHS.
79
Sodani PR, Sharma K. Assessing Indian Public Health Standards for 24 × 7 primary
health centers: A case study with special reference to newborn care services. J Nat
Accred Board Hosp Healthcare Providers 2014;1:12-6
• Indian Public Health Standards (IPHS) Guidelines for
Primary Health Centres Revised 2012
80
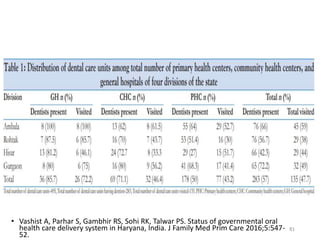
• Vashist A, Parhar S, Gambhir RS, Sohi RK, Talwar PS. Status of governmental oral
health care delivery system in Haryana, India. J Family Med Prim Care 2016;5:547-
52.
81
• Iyer K, Krishnamurthy A, Pathak M, Krishnan L, Kshetrimayum N, Moothedath M. Oral health
taking a back seat at primary health centers of Bangalore urban district, India – A situation
analysis. J Family Med Prim Care 2019;8:251-5.
82
• India is one of the fastest growing economies of the world. The very
essential components of primary health care– promotion of food supply,
proper nutrition, safe water and basic sanitation and provision for quality
health information concerning the prevailing health problems – is largely
ignored.
• Access to healthcare services, provision of essential medicines and
scarcity of doctors are other bottlenecks in the primary health care
scenario.
• In India certain constraints at the level of planning, implementation and
evaluation has to be removed for the success of primary health care
concepts.
83
Conclusion
• At the governmental level, services by doctors in villages do not
get rewarded, and, disillusionment can set in rapidly as
encouragement does not come from most rural communities at
times.
• Also, India’s progress towards achieving the Millennium
Development Goal is slow and it is well known that primary health
care is important for achieving the goals. The only thing which can
be done is that government should take effective step in order to
resolve the health related issues and problem.
84
References
Park K. Park's textbook of preventive and social medicine. Banarasidas Bhanot.
2017;24th edition.
Peter S. Essentials of Public Health Dentistry;5th Edition.
Pandve HT, Pandve TK. Primary healthcare system in India: Evolution and
challenges. International Journal of Health System and Disaster Management.
2013 Jul 1;1(3):125.
Declaration of Alma-Ata. World Health Organization.1978.
Global Conference on Primary Health Care - World Health Organization.2018.
https://www.who.int/primary-health/conference-phc
85
 https://mohfw.gov.in/documents/policy
https://mohfw.gov.in/sites/default/files/rural%20health%20care%20system%20in
%20india.pdf
Rural health care system in India. Ministry of health and family welfare. 2018
 Kulkarni P. National Urban Health Mission: An Effort to Achieve Equity in Health.
Annals of Community Health. 2014 Mar 1;2(1):3-6.
 India. Department of Health and Family Welfare. National Urban Health
Mission‐ Framework for implementation. New Delhi: Ministry of Health and
Family Welfare Government of India; May 2013.
 https://icds-wcd.nic.in/icdsdatatables.aspx
86
 nhm.gov.in
 Vashist A, Parhar S, Gambhir RS, Sohi RK, Talwar PS. Status of governmental
oral health care delivery system in Haryana, India. J Family Med Prim Care
2016;5:547-52.
 Iyer K, Krishnamurthy A, Pathak M, Krishnan L, Kshetrimayum N, Moothedath
M. Oral health taking a back seat at primary health centers of Bangalore urban
district, India – A situation analysis. J Family Med Prim Care 2019;8:251-5.
DISTRICTWISE COMMUNITY HEALTH CENTRES / PRIMARY HEALTH CENTRES /
SUB CENTRES IN HARYANA. Health department of Haryana.
http://haryanahealth.nic.in
 India. Department of Health and Family Welfare. National Urban Health
Mission‐ Framework for implementation. New Delhi: Ministry of Health and
Family Welfare Government of India; May 2013.
87
 https://prharyana.gov.in
 Rural Health Statistics. Ministry of health and Family Welfare. GOI
• Chauhan R, Mazta SR, Dhadwal DS, Sandhu S. Indian public health standards
in primary health centers and community health centers in Shimla District of
Himachal Pradesh: A descriptive evaluation. CHRISMED J Health Res
2016;3:22-7.
88
89