Non-insulin pharmacologic (antidiabetic)agents
in T2DM
.
When glucose levels are above target in type 2 diabetes despite
appropriate lifestyle advice, drug therapy will usually be initiated and
subsequently increased (‘intensified’) with the aim of establishing or
re-establishing ;
adequate glucose control.
abolishing osmotic symptoms.
preventing microvascular complications.
Some individuals require pharmacological therapy from the time of
(or very soon after) diagnosis.
Over the following years and decades, the majority will require to
take combinations of glucose-lowering drugs, oral or injectable, and
some will also require insulin.
3.
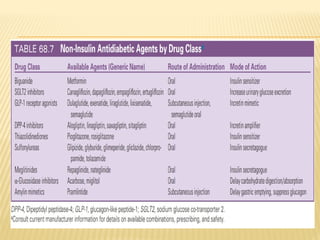
Nine main classesof glucose-lowering drugs are generally used to
manage type 2 diabetes.
seven are oral agents:
Metformin (the only available biguanide),
Sulphonylureas,
Pioglitazone (the only available thiazolidinedione),
DPP-4 inhibitors and
Sodium-glucose transporter-2 (SGLT2) inhibitors.
GLP-1 receptor agonists are usually given by subcutaneous
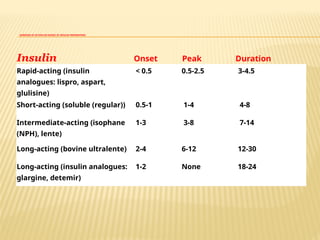
injection, but an oral preparation is available.
Acarbose (an intestinal disaccharidase inhibitor that prevents
dietary glucose absorption) and
Meglitinides (oral agents that stimulate endogenous insulin) are
also available, but little used due to relatively low efficacy and, in
the case of acarbose, frequent (gastrointestinal) side effects.
Amylin memitics
5.
Factors that determinewhich of these drugs should be prescribed first – and
then which should subsequently be added in – include:
1- Individual profile (severity of initial symptoms, degree of obesity) .
2- Glucose-lowering efficacy.
3- Protective properties in relation to cardiovascular and renal complications.
4- Adverse effect profile (hypoglycemia, weight gain).
5- Renal function.
6- Drug factors (mechanism of clearance/metabolism).
7- Ability to self-inject.
8- Occupation (e.g. driving, working at heights).
9- Cost.
6.
Metformin isoften positioned as first-line, with second-line treatment
personalized for each patient according to the above factors.
A third or even fourth oral agent may be added in over time, but injectable
therapy (GLP-1 receptor agonists or insulin) should not be delayed while levels
of glycemia above target are sustained for months or years.
Unlike microvascular complications, it cannot be assumed that all agents that
lower glucose also reduce rates of macrovascular complications, i.e. myocardial
infarction and stroke. Some newer agents clearly protect against cardiovascular
disease (GLP-1 receptor agonists and SGLT2 inhibitors),
SGLT2 inhibitors have additional protective properties in heart failure and
diabetic kidney disease, while TZDs (thiazolidinediones) increase rates of heart
failure.
7.
Metformin.
Metformin is anoral agent in the biguanide class that produces its most prominent
effects by decreasing gluconeogenesis and thus reducing hepatic glucose production.
This insulin-sensitizing effect is associated with a low risk of hypoglycemia.
The usual starting dose is 500 mg once or twice daily with incremental advancement
at several-week intervals to a usual maximum of 2000 mg daily in two or three divided
doses.
Metformin benefits typically include
A. Decreases HbA1c by up to 1.5%.
B. Modest weight loss (approximately 3 kg on average) and a
C. Small improvement in plasma lipid profile (decrease in low-density lipoprotein [LDL]-
cholesterol and triglycerides and increase in HDL).
Adverse reactions include gastrointestinal effects and, rarely, lactic acidosis.
The drug should be avoided in patients with an estimated glomerular filtration rate
(eGFR) of 30 to 45 mL/min/1.73m2.
8.
Sulfonylureas
.
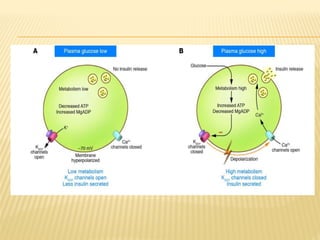
Sulfonylureas stimulateendogenous insulin secretion by binding and activating
potassium channels in beta cells.
In patients with adequate residual beta-cell function, they can lower HbA1c levels by
1% to 2%.
Drugs in this class have been in clinical use for more than 40 years, and many
inexpensive, generic sulfonylureas are available that differ in duration of action,
metabolism, and mode of clearance.
Because they can increase insulin secretion even in the absence of hyperglycemia,
they have significant potential to cause hypoglycemia.
10.
Patients needto be instructed how to recognize and treat hypoglycemia before
starting a sulfonylurea.
Factors that increase the risk for hypoglycemia with sulfonylureas include advanced
age, poor nutrition, alcohol ingestion, and hepatic and renal insufficiency.
Other disadvantages of this drug class are a tendency to cause weight gain and a
yet unresolved concern about increased risk for cardiovascular events.
12.
Classification
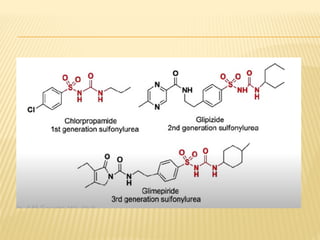
first-generation compounds:chlorpropamide, tolbutamide,
icetohexamide.
second-generation compounds: glibenclamide, gliclazide and glipizide;
they are up to 200 times more pogg tent than first-generation agents.
third-generation compounds: e.g. glimepiride; these compounds may
interact with different cellular proteins than other sulfonylureas.
13.
Meglitinides
.
Repaglinide and nateglinideactivate beta cell potassium channels and thus
stimulate endogenous insulin secretion through a mechanism similar to that
of sulfonylureas, although they generally result in less reduction in blood
glucose than sulfonylureas
.
They have rapid action and have less tendency to cause hypoglycemia than
sulfonylureas
.
Their use has been limited by high cost and lack of advantage over the
sulfonylureas
.
14.
Pioglitazone.
The thiazolidinedione,pioglitazone, activates the nuclear peroxisome proliferator-
activated receptor-γ, which leads to changes in transcription rates of multiple
genes.
The net effect is reduced insulin resistance, resulting in increased glucose uptake
in peripheral tissues and reduced hepatic glucose production.
Pioglitazone typically lowers HbA1c by 0.5% to 1.4% and is available as a low-cost
drug. It carries a low risk of hypoglycemia, but potential side effects include weight
gain, fluid retention and heart failure, hepatoxicity, concerns about increased
fracture risk in the setting of low bone density, and a potential link to bladder
cancer.
Another member of this drug class, rosiglitazone, is little used because of its
potential link to increased cardiovascular events.
15.
Dipeptidyl peptidase-4 inhibitors
.
DPP-4 inhibitors (alogliptin, linagliptin, saxagliptin, and sitagliptin) block the
deactivation of GLP-1 and glucose-dependent insulinotropic peptide (GIP),
peptide hormones that are important in the regulation of glucose homeostasis.
DPP-4 inhibitors are taken orally and result in decreased HbA1c in the range of
0.5% to 1.0%.
They have a low risk of causing hypoglycemia, have neutral effects on
cardiovascular disease outcomes and body weight, and can be used in the
context of CKD with agent-specific dose reductions.
They have generally favorable side effect profiles, although there is concern that
some members of the class may increase heart failure risk.
They should not be used in combination with GLP-1 receptor agonists.
16.
Sodium-glucose co-transporter 2(SGLT2) inhibitors.
Canagliflozin, dapagliflozin, empagliflozin, and ertugliflozin function by inhibiting
SGLT2.
SGLT2 mediates more than 90% of glucose reabsorption in the proximal renal
tubule, and the drug lowers blood glucose levels by promoting excretion of glucose
in the urine.
This typically results in a decrease in HbA1c in the range of 0.5% to 1.0%, plus
modest weight loss (2-3 kg on average) and decrease in blood pressure.
The mechanism of action is independent of insulin, and this class of drugs does not
cause hypoglycemia.
17.
SGLT2 inhibitors
1)decreased major cardiovascular events in T2DM patients with established
cardiovascular disease with canagliflozin and empagliflozin.
2) decreases in hospitalization for heart failure.
3) decreases in progression of diabetic nephropathy.
The mechanism by which they lower blood glucose exploits the handling of glucose in the
kidneys.
Glucose is filtered freely in the glomerulus and then completely reabsorbed in the
proximal tubules with sodium (mainly via SGLT2)
SGLT2 inhibitors act by lowering the renal threshold for glucose excretion, such that
typically 25% of filtered glucose is not reabsorbed.
18.
As well aslowering blood glucose, a negative energy balance is created with 200–300
kcal being lost each day (as glucose in the urine), resulting in significant weight loss.
As sodium is also lost in the urine (also known as natriuesis), blood pressure is also
reduced.
SGLT2 inhibitors reduce rates of major adverse cardiovascular outcomes, particularly
heart failure, and also have a reno-protective effect, i.e. reducing rates of death, dialysis
and transplantation.
Compensatory glucagon release from pancreatic α cells (in response to urinary loss of
glucose) decreases the circulating ratio of insulin to glucagon, promoting lipolysis and
even mild ketosis; however, because of weight loss, this is not sufficient to exacerbate
insulin resistance.
19.
The work ofthe myocardium is more efficient when it utilizes free fatty acids (and
ketones) for fuel than it is when metabolizing glucose (as it does in heart failure).
Renal benefits of SGLT2 inhibitors are due to constriction of the afferent arteriole (as a
reflex response to increased renal tubular loss of sodium, termed ‘tubuloglomerular
feedback’).
This decreases intraglomerular pressure in a complementary manner to ACE
inhibitors ,which cause relaxation of the efferent arteriole by opposing the action of
angiotensin II.
20.
Clinical use
SGLT2inhibitors are effective oral glucose-lowering agents that are usually
added in with other agents second-line after metformin.
They help with body weight reduction and are associated with improvements in
cardiovascular and renal outcomes that have substantially advanced the
treatment of type 2 diabetes.
They should now be prescribed for all individuals with type 2 diabetes and prior
myocardial infarction, coronary artery disease, stroke, unstable angina, occlusive
peripheral arterial disease or cardiac failure.
Dapagliflozin is also licensed for use in type 1 diabetes, but must be used with
caution due to the increased risk of ketoacidosis .
21.
The main adverseeffect (in 5%–10% of those who take these agents) is genital mycotic
(fungal) infections usually with Candida albicans, i.e. vaginal ‘thrush’ and balanitis. Urine
infection is also more common and, very rarely, severe genital infection (Fournier’s
gangrene,) can occur.
Euglycaemic diabetic ketoacidosis (i.e. DKA not associated with marked hyperglycaemia)
is a rare complication of this class of drugs, presumably driven by reduced insulin :
glucagon ratio and consequent increased levels of circulating ketones.
It can be minimised by education about ‘sick day rules’, i.e. interrupting therapy during
acute illness (e.g. gastrointestinal or respiratory), avoiding dehydration and seeking
medical attention.
22.
Glucagon-like peptide-1 receptoragonists
.
GLP-1 is one of several hormones produced in the small intestine (designated
incretins) that modify gastrointestinal motility and insulin secretion.
The GLP-1 receptor agonists, dulaglutide, exenatide, liraglutide, lixisenatide, and
semaglutide, bind to GLP-1 receptors and improve blood glucose control by enhancing
glucose-dependent insulin secretion, slowing gastric emptying, suppressing
postprandial glucagon production, and decreasing food intake through enhanced
satiety.
This results in decreases in HbA1c by 0.5% to 1.5% and modest weight loss (in the
range of 3 kg).
There is evidence for improved cardiovascular outcomes for several of these agents in
patients with established cardiovascular disease and possibly an improvement in CKD
outcomes.
23.
They maybe a favorable choice as a second-line drug for glycemia management if
weight loss is a goal and in patients with established cardiovascular disease.
Because of their relatively high efficacy, GLP-1 receptor agonists are a reasonable
option to consider before starting insulin in patients not adequately controlled on
other agents.
Most members of this drug class are administered via injection with prefilled pens,
twice daily, once daily, or once weekly
The most common side effects are nausea and sometimes diarrhea, likely related
to effects on gastrointestinal motility, and these agents should not be used in
patients with a history of pancreatitis or in combination with DPP-4 inhibitors.
24.
α-Glucosidase inhibitors
.
Theα-glucosidase inhibitors, acarbose and miglitol, are oral agents that improve
glycemia by inhibiting the enzymatic breakdown of complex carbohydrates within
the lumen of the small intestine.
They have modest glucose-lowering effects, decreasing HbA1c in the range of
0.5% to 0.8%.
Their use is limited by the frequent occurrence of flatulence and diarrhea as a
consequence of undigested carbohydrates reaching lower intestinal regions.
25.
INSULIN THERAPY
Insulin wasdiscovered in 1921 and transformed the
management of type 1 diabetes.
Until the 1980s insulin was obtained by extraction and
purification from pancreata of cows and pigs (bovine and
porcine insulins), and some patients still prefer to use
animal insulins.
Recombinant DNA technology enabled large-scale
production of human insulin.
More recently, the amino acid sequence of insulin has
been altered to produce analogues of insulin, which differ in
their rate of absorption from the site of injection.
26.
The duration ofaction of short-acting, unmodified insulin ('soluble' or
'regular' insulin), which is a clear solution, can be extended by the addition
of protamine and zinc at neutral pH to create Neutral Protamine Hagedorn
insulin (known as ‘isophane’ or NPH insulin) – this has a cloudy
appearance (and requires to be resuspended by shaking before use).
It is now referred to as ‘intermediate-acting’ with onset of action at 60–
90 minutes, peaking at 6 hours and wearing off by 12–16 hours.
Pre-mixed formulations containing short-acting and isophane insulins in
various proportions are available.
In most patients,insulin is injected subcutaneously several
times a day into the anterior abdominal wall, upper arms, outer
thighs and buttocks.
Accidental intramuscular injection often occurs in children
and thin adults.
The rate of absorption of insulin may be influenced by many
factors other than the insulin formulation, including the site,
depth and volume of injection, skin temperature (warming),
local massage and exercise.
Absorption is delayed from areas of lipohypertrophy at
injection sites , which results from the local trophic action of
insulin, so repeated injection at the same site should be
avoided.
29.
Short-acting insulin hasto be injected at least 30 minutes
before a meal to allow adequate time for absorption.
Many patients find this inconvenient and ignore this
requirement.
However, the rapidly absorbed fast-acting insulin analogues can
be administered immediately before, during or even after
meals, and their peak action coincides more closely with the
post-prandial rise in blood glucose .
30.
Once absorbed intothe blood, insulin has a half-life of a few
minutes.
It is removed mainly by the liver and also the kidneys;
plasma insulin concentrations are elevated in patients with liver
disease or renal failure.
The rate of clearance is also affected by binding to insulin
antibodies (associated with the use of animal insulins).
31.
The dose ofbolus insulin administered at any one meal is primarily determined by the
carbohydrate content of the meal, the prevailing glucose level and the target glucose for
the individual
.
Each patient is advised by health-care professionals of their ‘insulin to carbohydrate ratio’,
i.e. the amount of insulin to take for each carbohydrate portion
.
In most people, this ratio is around 1:10 (i.e. 1 unit of insulin is taken for each 10 g
carbohydrate portion in the meal to be consumed), but may be higher or lower depending
on the individual’s insulin sensitivity
.
It may also vary between meals (e.g. breakfast vs evening meal)
.
32.
Intravenous insulin therapy
Circulating insulin has a half-life of approximately 2.5 minutes (the longer duration
of action of subcutaneous insulin is because of the time taken for insulin to be
absorbed from subcutaneous sites to the blood).
Therefore, direct infusion of insulin via the intravenous route gives maximum
flexibility in regulating blood glucose concentrations: an increase in the infusion
rate will rapidly correct hyperglycaemia, while cessation of intravenous insulin will
arrest a rapidly declining blood glucose.
33.
This inherentflexibility makes intravenous insulin a powerful tool in the management
of hyperglycaemic emergencies and in stabilising blood glucose in a perioperative
situation or in individuals who are unwell, e.g. with poor oral intake or delayed gastric
emptying.
Subcutaneous insulin does not lower blood glucose quickly enough for hyperglycaemic
emergencies, particularly if skin perfusion is reduced during sepsis, while its duration
of action may also be too long (i.e. result in hypoglycaemia) if given to an unwell
patient who subsequently cannot eat or vomits. Intravenous insulin is, however, a
dangerous therapy if not properly supervised and monitored.
34.
A common problemthat associated with the use of
insulins is fasting hyperglycaemia ('the dawn
phenomenon') associated with the normal circadian
rhythm and causing release of counter-regulatory
hormones during the later part of the night, which
antagonise insulin action before wakening.
35.
Dawn Phenomenon andthe Somogyi Effect
The dawn phenomenon and the Somogyi effect cause high blood sugar levels,
especially in the morning before breakfast, in people who have diabetes
.
The dawn phenomenon happens naturally, but the Somogyi effect usually happens
because of problems with your diabetes management routine
.
Dawn phenomenon
The dawn phenomenon is a normal rise in blood sugar as a person's body
prepares to wake up
.
•
In the early morning hours, hormones (growth hormone, cortisol, and
catecholamines) cause the liver to release large amounts of sugar into the
bloodstream. For most people, the body produces insulin to control the rise in
blood sugar
.
•
If the body doesn't produce enough insulin, blood sugar levels can rise. This may
cause high blood sugar in the morning (before eating)
.
.
36.
Somogyi effect
If theblood sugar level drops too low in the early morning hours, hormones
(such as growth hormone, cortisol, and catecholamines) are released.
These help reverse the low blood sugar level but may lead to blood
sugar levels that are higher than normal in the morning.
An example of the Somogyi effect is:
•A person who takes insulin doesn't eat a regular bedtime snack, and
the person's blood sugar level drops during the night.
•The person's body responds to the low blood sugar by releasing
hormones that raise the blood sugar level. This may cause a high
blood sugar level in the early morning.
37.
How can youtell the difference
?
The Somogyi effect can occur any time you has extra
insulin in the body
.
To sort out whether an early morning high blood sugar
level is caused by the dawn phenomenon or Somogyi
effect, check blood sugar levels at bedtime, around 2 a.m.
to 3 a.m., and at your normal wake-up time for several
nights
.
•
If the blood sugar level is low at 2 a.m. to 3 a.m., suspect
the Somogyi effect
.
•
If the blood sugar level is normal or high at 2 a.m. to 3
a.m., it's likely the dawn phenomenon
.
38.
SIDE-EFFECTS OF INSULINTHERAPY
1. Hypoglycaemia
2. Weight gain
3. Peripheral oedema (insulin treatment
causes salt and water retention in the short
term)
4. Insulin antibodies (animal insulins)
5. Local allergy (rare)
6. Lipodystrophy at injection sites
39.
INSULIN DOSING REGIMENS
Thechoice of regimen depends on the desired
degree of glycaemic control, the severity of underlying
insulin deficiency, the patient's lifestyle, and his or her
ability to adjust the insulin dose.
Most people require two or more injections of
insulin daily.
Once-daily injections rarely achieve satisfactory
glycaemic control and are reserved either for some
elderly patients or for those who retain substantial
endogenous insulin secretion and have a low insulin
requirement.
40.
Twice-daily administration ofa short-acting and intermediate-
acting insulin (usually soluble and isophane insulins), given in
combination before breakfast and the evening meal, is the
simplest regimen and is still used commonly.
Individual doses vary considerably but usually two-thirds of the
total daily requirement of insulin is given in the morning in a ratio
of 1:2, short-:intermediate-acting insulins.
The remaining third is given in the evening, and doses are
adjusted according to blood glucose measurements.
41.
Several pre-mixed formulationsare available containing
different proportions of soluble and isophane insulins (e.g.
30:70 and 50:50).
These are useful for patients who have difficulty mixing
insulins, but are inflexible as the individual components
cannot be adjusted independently, and require to be
resuspended by shaking the vial several times before
administration.
42.
Multiple injection regimensare popular, with short-acting
insulin being taken before each meal (usually by en injector),
and intermediate- or long-acting insulin being injected once or
twice daily (basal-bolus regimen).
This type of regimen allows greater freedom of timing of
meals and more variable day-to-day physical activity, but
snacks may have to be taken between meals to prevent
hypoglycaemia
43.
Honeymoon period
• Afterinstitution of insulin and other therapy, stress-induced
insulin resistance resolves, and there may be an improvement
in beta-cell function.
• Some patients then revert to a state in which no insulin is
required.
• This phenomenon, designated the honeymoon period, can last
for several weeks to as long as 1 year.
• Patients generally should continue insulin administration at
doses low enough to be tolerated during this interval, because
progressive beta-cell function can be expected eventually to
result in recurrent hyperglycemia and, potentially, DKA.