ANTIHYPERLIPIDEMICS
By: Saima
Assistant professor
Magadh institute of pharmacy
Hyperlipidemia
• Hyperlipidemia refers to abnormally high levels of lipids (fats), such as cholesterol and
triglycerides, in the blood.
• It is a significant risk factor for cardiovascular diseases, including atherosclerosis, coronary artery
disease, and stroke.
Types of Hyperlipidemia:
• Primary Hyperlipidemia: Caused by genetic factors, such as familial hypercholesterolemia.
• Secondary Hyperlipidemia: Due to underlying conditions or lifestyle factors, such as:
• Obesity
• Diabetes
• Hypothyroidism
• Excessive alcohol consumption
• High-fat diet
• Sedentary lifestyle
Lipid Types Involved:
Low-Density Lipoprotein (LDL-C):
• "Bad cholesterol" that contributes to plaque formation in arteries.
High-Density Lipoprotein (HDL-C):
• "Good cholesterol" that helps remove LDL cholesterol from the bloodstream.
Triglycerides (TG):
• A type of fat stored in the body; elevated levels are harmful.
Total Cholesterol (TC):
• Combined measure of LDL, HDL, and other lipid components.
VLDL :
• VLDL is a type of lipoprotein produced by the liver. It primarily carries triglycerides to tissues for energy
storage or use. After delivering triglycerides, VLDL particles are converted into LDL (low-density lipoprotein).
CLASSIFICATION OF ANTIHYPERLIPIDEMICS
HMG-CoA reductase inhibitors ( Statins)
• Statins are the most commonly prescribed drugs for lowering cholesterol
and preventing cardiovascular diseases.
Examples:
High Potency: Atorvastatin, Rosuvastatin.
Moderate Potency: Simvastatin, Pravastatin, Fluvastatin
Therapeutic Uses:
oHyperlipidemia (high LDL levels).
oPrevention of cardiovascular events (e.g., heart attack, stroke).
oTreatment of atherosclerosis and related disorders.
MECHANISM OF ACTION OF STATINS
1. Inhibition of Cholesterol Synthesis:
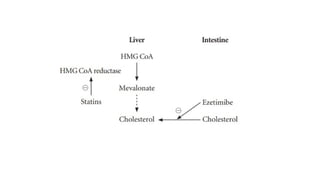
• Statins competitively inhibit HMG-CoA reductase,
the key enzyme in cholesterol biosynthesis.
• This blocks the conversion of HMG-CoA to
mevalonate, a precursor of cholesterol.
2. Upregulation of LDL Receptors:
• Reduced hepatic cholesterol levels trigger upregulation of LDL
receptors on hepatocytes.
• Increased LDL receptor expression enhances the clearance of
LDL from the bloodstream.
3. Reduction in Plasma LDL Levels:
• Enhanced LDL uptake lowers circulating LDL cholesterol levels,
reducing the risk of atherosclerosis.
4. Increased HDL levels
Adverse effects ( HMG )
• Hepatotoxicity , headache
• Myopathy – muscle pain, weakness
• Gastrointestinal disturbances – Anorexia, nausea, vomiting, diarrhoea.
• Contraindicated in pregnancy.
Uses :
• Used in both primary and secondary hyperlipidemias.
Bile Acid Sequestrants (Resins)
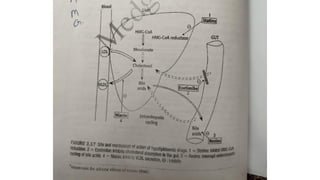
• They are basic ion exchange resins.
• They are neither digested nor absorbed in the gut.
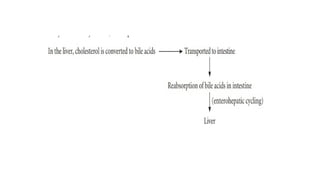
• They bind bile acids in the intestine interrupting their enteroheptic
cycling. They promote conversion of cholesterol to bile acids in the liver.’
• They stimulate the formation of hepatic LDL-receptors which take up
more LDL-cholesterol from the circulation.
• The net effect is reduction of LDL levels with little effect on HDL levels.
Adverse effects:
Unpalatibility, bloating, nausea, constipation.
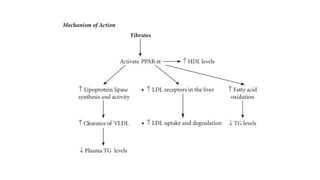
FIBRATES(Clofibrate, gemfibrozil, fenofibrate)
• They activate peroxisome proliferator-activated receptor α (PPAR-
α) present in the liver adipose tissue and skeletal muscle.
Gemfibrozil –
First line drug for patients with markedly raised TG levels.
Most effective in type III hyperlipoproteinaemia.
Epigastric distress, loose motion are common side effects.
Use of combination of gemfibrozil with statins increases the risk
of myopathy. (Fenofibrate, benzafibrate can be combined with statins)
NICOTINIC ACID
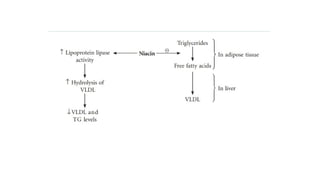
• Niacin is a B-complex vitamin. In large doses, it has hypolipidaemic
effect.
• It reduces plasma TG, VLDL, LDL, and increases HDL levels.
• It is highly efficacious in hypertriglyceridaemia ( type III, IV, V).
• It is mostly used to lower VLDL and raise HDL levels.
Adverse effect –
Flushing, dyspepsia, hyperglycemia.
Contraindicated in pregnancy.
Sterol absorbtion inhibitor ( Ezetimibe )
• It inhibits the absorption of dietary and biliary cholesterol in the
intestine.
• It is mainly used with a statin.
• The combination of ezetimibe and statins has a beneficial effect.
Statins inhibit cholesterol synthesis but increases intestinal
cholesterol absorption. Ezetimibe inhibits intestinal cholesterol
absorption but increses cholesterol synthesis.
• Combination use of these drugs prevents the increase in cholesterol
absorption caused by statins and increased cholesterol synthesis by
ezetimibe.
"Pharmacology of Antihyperlipidemic Drugs"