info@medicoseacademics.com
0310-7990649
Pharmacology III
Dr. Sidra Arshad
Assistant Professor
Physiology
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 2
A quick revision of:
1. Drugs acting in the CNS
• Glaucoma
• Anti-epileptic drugs
• Sedative-hypnotics
• Anesthetics
• Opioids
• Management of Parkinson’s disease
• Antipsychotics and antidepressants
2. Diabetes Mellitus drugs
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 3
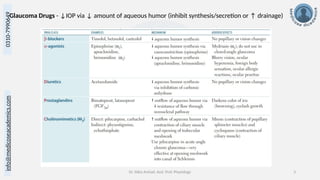
Glaucoma Drugs - ↓IOP via ↓ amount of aqueous humor (inhibit synthesis/secretion or ↑ drainage)
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 4
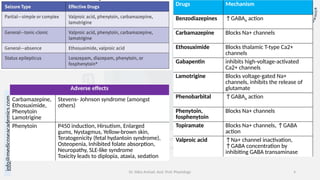
Drugs Mechanism
Benzodiazepines ↑GABAA action
Carbamazepine Blocks Na+ channels
Ethosuximide Blocks thalamic T-type Ca2+
channels
Gabapentin inhibits high-voltage-activated
Ca2+ channels
Lamotrigine Blocks voltage-gated Na+
channels, inhibits the release of
glutamate
Phenobarbital ↑GABAA action
Phenytoin,
fosphenytoin
Blocks Na+ channels
Topiramate Blocks Na+ channels, ↑GABA
action
Valproic acid ↑Na+ channel inactivation,
↑GABA concentration by
inhibiting GABA transaminase
Adverse effects
Carbamazepine,
Ethosuximide,
Phenytoin
Lamotrigine
Stevens- Johnson syndrome (amongst
others)
Phenytoin P450 induction, Hirsutism, Enlarged
gums, Nystagmus, Yellow-brown skin,
Teratogenicity (fetal hydantoin syndrome),
Osteopenia, Inhibited folate absorption,
Neuropathy, SLE-like syndrome
Toxicity leads to diplopia, ataxia, sedation
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 5
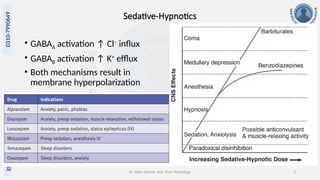
Sedative-Hypnotics
• GABAA activation ↑ Cl−
influx
• GABAB activation ↑ K+
efflux
• Both mechanisms result in
membrane hyperpolarization
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 6
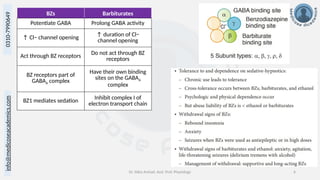
BZs Barbiturates
Potentiate GABA Prolong GABA activity
↑ Cl− channel opening ↑ duration of Cl−
channel opening
Act through BZ receptors Do not act through BZ
receptors
BZ receptors part of
GABAA complex
Have their own binding
sites on the GABAA
complex
BZ1 mediates sedation
Inhibit complex I of
electron transport chain
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 7
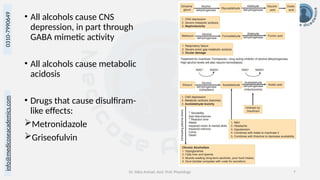
• All alcohols cause CNS
depression, in part through
GABA mimetic activity
• All alcohols cause metabolic
acidosis
• Drugs that cause disulfiram-
like effects:
Metronidazole
Griseofulvin
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 8
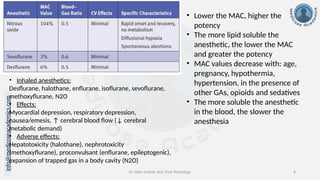
• Lower the MAC, higher the
potency
• The more lipid soluble the
anesthetic, the lower the MAC
and greater the potency
• MAC values decrease with: age,
pregnancy, hypothermia,
hypertension, in the presence of
other GAs, opioids and sedatives
• The more soluble the anesthetic
in the blood, the slower the
anesthesia
• Inhaled anesthetics:
Desflurane, halothane, enflurane, isoflurane, sevoflurane,
methoxyflurane, N2O
• Effects:
Myocardial depression, respiratory depression,
nausea/emesis, ↑ cerebral blood flow (↓ cerebral
metabolic demand)
• Adverse effects:
Hepatotoxicity (halothane), nephrotoxicity
(methoxyflurane), proconvulsant (enflurane, epileptogenic),
expansion of trapped gas in a body cavity (N2O)
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 9
Intravenous anesthetics
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 10
Mechanisms:
• the ionized form blocks the inactivated Na+ channel
• slows recovery and prevents propagation of action potentials
• Nerve fiber sensitivity: most sensitive to blockade are of smaller diameter and have high firing rates
• Order of sensitivity is:
• type B and C > type Aδ > type Aβ and Aγ > type Aα
• Recovery is in reverse order
Absorption:
Coadministration of α1 agonists:
• ↓ local anesthetic absorption into the systemic circulation
• Prolong effects and ↓ toxicity
Side effects:
• Neurotoxicity • Cardiovascular toxicity • Allergies
Local Anesthetics:
• Esters—procaine, tetracaine, benzocaine, chloroprocaine
• Amides—lidocaine, mepivacaine, bupivacaine, ropivacaine
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 11
• Skeletal Muscle Relaxants:
Malignant Hyperthermia: Life-threatening syndrome and
treatment
• Characterized by muscle rigidity, hyperthermia,
hypertension, acidosis, and hyperkalemia
• Often triggered by the use of skeletal muscle relaxants,
particularly succinylcholine, in anesthesia regimens
• Genotypic susceptibility linked to mutations in genes
encoding ryanodine receptors and/or a protein component
of L-type calcium channels in skeletal muscle
• Dantrolene is a key treatment -acts directly on skeletal
muscle by blocking Ca2+ release from the sarcoplasmic
reticulum
Nondepolarizing
(competitive)
Depolarizing (noncompetitive)
– Nicotinic antagonists
– Rocuronium is the
prototype
– Reversible with AChE
inhibitors
– Progressive paralysis
(face, limbs, respiratory
muscle)
– No effects on cardiac and
smooth muscle
– No CNS effects
– Specific drugs: atracurium
(rapid recovery, safe in
hepatic or renal
impairment, spontaneous
inactivation to laudanosine
(laudanosine can cause
seizures)
– Nicotinic agonist
– Specific drug: succinylcholine
– Two phases: phase I is
depolarization, fasciculation,
prolong depolarization, flaccid
paralysis; phase II
is desensitization
– AChE inhibitors ↑ phase I; may
reverse phase II
– Rapidly hydrolyzed by
pseudocholinesterase: short
duration
– Complications: hypercalcemia,
hyperkalemia; malignant
hyperthermia
Centrally Acting Skeletal Muscle Relaxants:
• BZD through GABAA receptors
• Baclofen through GABAB receptors
• Use: spasticity
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 12
Opioid Analgesics
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 13
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 14
Parkinson Disease Drugs
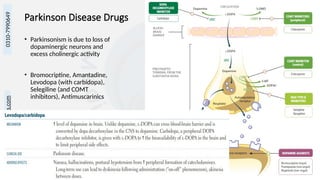
• Parkinsonism is due to loss of
dopaminergic neurons and
excess cholinergic activity
• Bromocriptine, Amantadine,
Levodopa (with carbidopa),
Selegiline (and COMT
inhibitors), Antimuscarinics
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 15
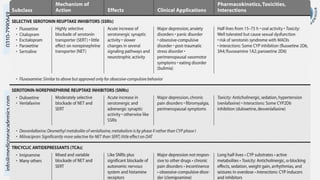
Antipsychotics and Antidepressants
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 16
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 17
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 18
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 19
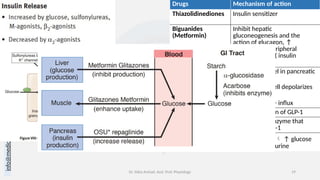
Drugs Mechanism of action
Thiazolidinediones Insulin sensitizer
Biguanides
(Metformin)
Inhibit hepatic
gluconeogenesis and the
action of glucagon, ↑
glycolysis, ↑ peripheral
glucose uptake ( insulin
sensitivity)
Sulfonylureas Close K+ channel in pancreatic
β cell
membrane cell depolarizes
 insulin
release via Ca2+ influx
Incretin drugs Mimic the action of GLP-1
DPP 4 inhibitors Inhibit DPP-4 enzyme that
deactivates GLP-1
Gliflozins SGLT2 inhibitor  ↑ glucose
excreted in the urine
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 20
Thank you.
Any questions?