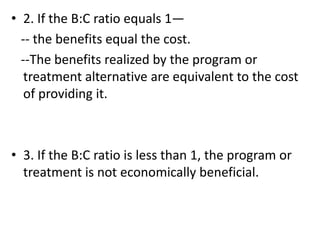Pharmacoeconomics
(For MD Pharmacology)
Dr. Advaitha M. V
TERMINOLOGIES
Health economics :
• Health Economics is an applied field of study that
allows for the systematic and rigorous
examination of the problems faced in promoting
health for all –
• This is achieved By applying economic theories of
consumer, producer and social choice.
• The aim of Health economics :
is to identify what is most efficient, so that the
greatest amount of benefit (Pharmaceutical
products/ Health services) can be bought for a
given amount of money or resources.
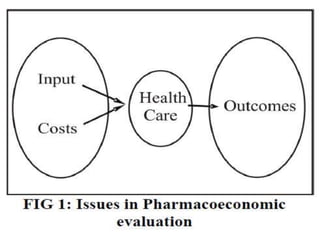
Pharmacoeconomics (PE)
• It is a branch of Health economics.
• Definition : “Research that identifies,
measures and compares the costs (resources
consumed) and the Economic, Clinical and
Humanistic Outcomes of diseases, drug
therapies and programmes directed to these
diseases.”
• Term first coined in 1986 by Townsend

Who takes Key Interest in PE
Health care funders
Pharmaceutical Companies.
Governments.
Social security funds.
insurance companies.
REMARKS :
• They struggle to meet their rising costs.
• They make many efforts to contain drug costs, by
price negotiation, patient co-payments or dedicated
drug budgets.
COSTS AND BENEFITS
Cost classification
• 1.Direct Cost–
• Cost from the perspective of the healthcare
funder.
Includes staff costs, capital costs, drug
acquisition costs.
Contd.. Direct cost
• Cost from the perspective of the Patient
Medications, Supplies, Laboratory tests,
Healthcare professionals' time, Hospitalization.
• Direct costs are relatively easy to measure.
2.Indirect Cost –
• It is Cost from the perspective of society as a
whole:
• for example :
loss of earnings, loss of productivity, loss of
leisure time, due to the illness, and cost of
travel to hospital etc.
• This would include not just the patient
themselves but also their family and society as
a whole.
• Many of these are difficult to measure, and
there is some controversy over how to value
these.
3.Intangible Cost –
• It is the pain, worry or other distress which a
patient or their family might suffer.
• These may be impossible to measure in
monetary terms, but are sometimes captured
in measures of quality of life.
Scenario :
1.Laparoscopic Appendectomy with Sevoflurane
Versus
2. Open Appendectomy with Ether
1. –
• Direct Cost is High.(For equipment, Specialized
Surgeon, cost of anaesthetic)
• Indirect cost is less (Less No. of days at Hospital in
Post Operative Period)
• Intangible cost is less.(Less Pain and suffering,
Minimal Scar )
• 2.—
• Direct Cost is less.(No special equipments,
Medications are relatively cheap.)
• Indirect cost is High. (Has to stay more no. of
days Post OP)
• Intangible cost is High.(More Pain and
suffering, Conspicuous Scar)
Benefits
• The benefits we expect from an intervention
might be measured in:
• 1. “Natural” units –
• e.g. years of life saved, strokes prevented,
peptic ulcers healed etc.
• 2.“Utility” units –
• Utility is an economist’s word for satisfaction, or
sense of well being.
• It is an attempt to evaluate the quality of a state
of health, and not just its quantity.
• E.g,
• The Quality Adjusted Life Year (QALY) is one
widely used measure, which attempts to
integrate both quality and the quantity of life.
[QALYs represent the number of full years at
full health that are valued equivalently to the
number of years as experienced]
• QALYs are calculated as the average number of
additional years of life gained from an
intervention.
• Then it is multiplied by a utility judgment of
the quality of life in each of those years.
• For example,
A person might be placed on hypertension therapy
for 30 years, which prolongs his life by 10 years at a
slightly reduced quality level of 0.9.
• In addition, the need for continued drug therapy
reduces his quality of life by 0.03.
• Hence, the QALYs gained would be 10 x 0.9 - 30 x
0.03 = 8.1 years.
• The valuations of quality may be collected from
surveys; a subjective weight is given to indicate the
quality or utility of a year of life with that disability.
Method of Economic evaluation
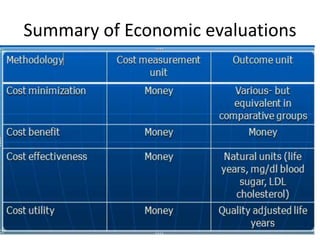
• Cost minimization analysis.
• Cost effectiveness analysis.
• Cost utility analysis.
• Cost benefit analysis.
Cost minimization analysis (CMA)
• This involves measuring only costs.
• It is applicable only where the outcomes are
identical .
• An e.g.
• Prescribing a generic preparation Vs brand Drugs
( Generic has lower cost but same health
outcomes ).
An Exercise ,
Drug ‘X’ (Rs 20 for 10 tab) and ‘X1’ (Rs 45 for 10tab)
are Antihypertentensives which Prolongs Life
Expectancy by 15yrs and 20 yrs respectively in
Patients with essential Hypertension.
Please suggest can Cost Minimization analysis be
used to include one this Drugs in our Hospital
Pharmacy ??
• Ans : No
• Why – The outcome or the Health benefit of
the 2 drugs are not equivalent. so we cannot
use CMA.
Methods of Economic Assessment
Answer :
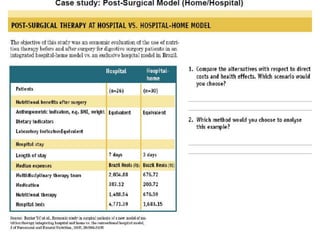
• Case study : Hospital vs Home Model
• 1st –Since the clinical efficacy of the 2
programs is equivalent, we should look at the
difference in length of stay and costs.
The hospital-home model has less
expenditures and is thus more cost-effective
• 2nd –cost-minimization analysis.
Cost-Effectiveness Analysis
• A Scenario :
• The Government Organization has to decide
Whether to launch Oral Polio Vaccine (OPV) or
Inactivated Polio Vaccine (IPV) Programme. ??
• Cost : OPV is cheaper To IPV.
• Effects :
OPV :
• 1. Provides ‘herd immunity’ ( it provides
immunity even to non-immunized) which is
essential in countries like India.
• Does not requires highly trained personnel.
• Useful in controlling epidemics.
Effects of IPV :
• It is safe to administer as it contains
inactivated virus.
• Especially in People over 50 yrs, With
corticosteroid/Radiation therapy.
• So, Basically we are comparing two
treatments with different efficacy and costs to
achieve a similar outcome.
• Another E.g,
• Whether to Implement Pentavalent Vaccine
Or Go for DPT with optional influenza and
HBV vaccine In our Govt Health set-up ?
?!?! Still Debate is On..
• Cost-effectiveness analysis (CEA) is a way of
summarizing the health benefits and
resources used by competing healthcare
programs—
So that policy makers can choose among them.
• CEA involves comparing programs or
treatment alternatives with different safety
and efficacy profiles.
• Cost is measured in Money.
• Outcomes are measured in terms of obtaining
a specific therapeutic outcome.
Outcomes are expressed in physical units,
natural units—
e.g., lives saved, cases cured, life expectancy,
or drop in blood pressure.
• The results of CEA are expressed as a ratio—
either as an
Average cost-effectiveness ratio (ACER)
or
 Incremental cost-effectiveness ratio (ICER).
Average Cost Effective Ratio(ACER)
• An ACER : represents the dollar cost per
specific clinical outcome gained, independent
of comparators.
• It is given by Formula.
• This allows the costs and outcomes to be
reduced to a single value to allow for
comparison.
• Using this ratio, the clinician would choose the
alternative with the least cost per outcome
gained.
• The most cost-effective alternative is not
always the least costly alternative for
obtaining a specific therapeutic objective.
• In this regard, cost-effectiveness need not be
cost reduction but rather cost optimization
Incremental Cost Effective Ratio
(ICER)
• Often clinical effectiveness is gained at an
increased cost.
• Is the increased benefit worth the increased cost?
• Incremental CEA can be used to determine the
additional cost and effectiveness gained when
one treatment alternative is compared with the
next best treatment alternative.
• Thus, instead of comparing the ACERs of each
treatment alternative –
The additional cost that a treatment
alternative imposes over another treatment is
compared with the additional effect, benefit,
or outcome it provides.
• An E.g,
• Already there is an existing ART Regimens in Govt
health set up……..
• Lately, research shows A few new drugs are to be
added and some drugs are to be removed from the
regimen to increase the effectiveness of treatment.
• However this modified treatment comes with an
additional cost.
• Question – Is this modified treatment (additional
benefit) worth the additional cost ?
• The ICER is given by Formula :
• This formula yields the additional cost required
to obtain the additional effect gained by
switching from drug A to drug B.
• CEA is useful in balancing cost with patient
outcome, determining which treatment
alternatives represent the best health
outcome per dollar spent.
• CEA can provide valuable data to support drug
policy, formulary management, and individual
patient treatment decisions.
• Globally, CEA is being used to set public
policies regarding the use of pharmaceutical
products (national formularies) in countries
such as Australia, New Zealand, Canada etc.
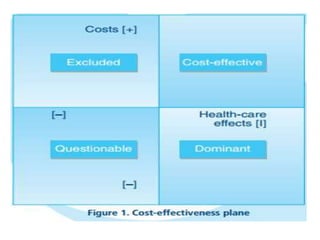
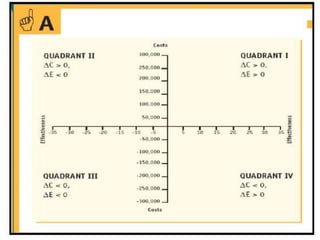
HANDLING THE RESULTS OF CEA- Cost effectiveness
Plane
• Quadrant II : is highly recommended.
• Quadrant I : it is most common scenario. It is
recommended But………..
A judgement must be made regarding
whether the additional benefits are worth the
extra costs of the new drug.
This might be defined by a previously agreed
ICER threshold value.
• Quadrant IV : Not recommended or Excluded.
• Quadrant III : Challenge and justify to retain or
to replace the standard drug when compared
with this new drug.
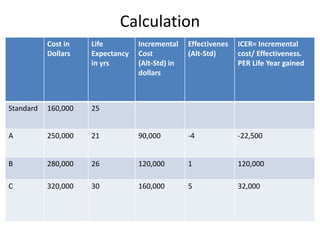
Calculation
Cost in
Dollars
Life
Expectancy
in yrs
Incremental
Cost
(Alt-Std) in
dollars
Effectivenes
(Alt-Std)
ICER= Incremental
cost/ Effectiveness.
PER Life Year gained
Standard 160,000 25
A 250,000 21 90,000 -4 -22,500
B 280,000 26 120,000 1 120,000
C 320,000 30 160,000 5 32,000
ANS :
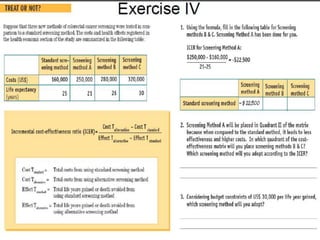
Q1)
• ICER for Screening method B is $120,000 per
additional life year gained
• ICER for Screening method C is $32,000 per
additional life year gained
Q2)
• Quadrant – B = I and C = I
• Choose -C
Q3)
• None. So, In Such cases usually Standard
method is retained.
Cost-Utility Analysis
• E.g, Osteoarthritis Knee –
QALY of :- Arthodesis Vs Knee Replacement
Surgery
• Primary Concerns in Disease : Severe Pain and
decreased Mobility. Also Cost of Surgery.
• Arthodesis : Cost : Cheap.
outcome- Pain reduced but requires walking
aids.(QALY- Reduces)
• Knee Replacement Surgery : Cost : High (for
Prosthesis and surgical equipments).
Pain reduced and can do Routine activities
without walking aids. (QALY- Increases)
• Pharmacoeconomists sometimes want to
include a measure of patient preference or
quality of life when comparing competing
treatment alternatives.
• Cost-utility analysis (CUA) is a method for
comparing treatment alternatives that integrates
patient preferences and Health-related quality
of life (HRQoL).
• CUA compares cost, quality, and the quantity of
patient-years.
• Cost is measured in dollars, and therapeutic
outcome is measured in patient-weighted
utilities rather than in physical units.
• Often the utility measurement used is a quality-
adjusted life year (QALY) gained.
• QALY is a common measure of health status used
in CUA, combining morbidity and mortality data.
• Results of CUA are also expressed in a ratio.
• Cost-utility ratio (C:U ratio).
• Most often this ratio is translated as the cost
per QALY gained.
• The preferred treatment alternative is that with
the lowest cost per QALY (or other health-status
utility)
• CUA is employed less frequently than other
economic evaluation methods.
• Because of –
lack of agreement on measuring utilities
Difficulty comparing QALYs across patients and
populations
Difficulty quantifying patient preferences.
• CUA is complex, So it is limited in scope of
application from a hospital perspective.
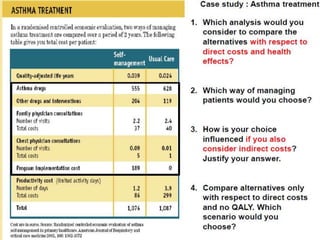
1Q)
• ANS :- Cost-utility analysis . Because Here we are
giving the patient a choice between the program.
2Q)
• Cost utility = Direct cost/QALY
• So, Cost Utility Of Self Management= 1076-
86/0.039= 25384.61 Euros per QALY gained
• Cost Utility of Usual care= 1087-299/0.024=32833.33
Euros per QALY gained
• Ans :– Self management (25384.61 vs. 32833.33 UC)
Q3)
• Calculate Cost utility= (Direct+ Indirect)/QALY
• It comes as Self management 27589 Vs 45291
Usual care
• So Ans –Self management program ( Also due
to the smaller number of limited activity days
In Self management).
Q4)
• Direct cost for self mgmt is $990 and for usual
care $788.
• ANS : So If we consider only direct costs, the
Usual care scenario is less expensive and that is
chosen.
Cost-Benefit Analysis
Let us Think !!!!
• Why there is High No. research going on For
Diabetes, Hypertension ??
• Why there is relatively less research on
Antimicrobials ??
• Why Pharma companies requests to CDSCO to
Waiver Phase III trials of NDA for Multiple
Myeloma and some rare type of cancers ??
• Cost-benefit analysis (CBA) is a method that
allows for the identification, measurement,
and comparison of the benefits (In Monetary
terms) and costs of a program or treatment
alternative.
• Both the costs and the benefits are measured
and converted into equivalent dollars in the
year in which they will occur.
• Future costs and benefits are discounted or
reduced to their current value.
• These costs and benefits are expressed as a
ratio (a benefit-to-cost ratio), a net benefit, or
a net cost.
• A clinical decision maker would choose the
program or treatment alternative with the highest
net benefit or the greatest benefit-to-cost (B:C)
ratio.
• Guidelines for the interpretation of this ratio are –
• 1. If the B:C ratio is greater than 1, the program or
treatment is of value.—
The benefits realized by the program or treatment
alternative outweigh the cost of providing it.
• 2. If the B:C ratio equals 1—
-- the benefits equal the cost.
--The benefits realized by the program or
treatment alternative are equivalent to the cost
of providing it.
• 3. If the B:C ratio is less than 1, the program or
treatment is not economically beneficial.
• CBA can be an appropriate method to use in
justifying and documenting the value of an
existing healthcare service or the potential
worth of a new one.
• For e.g, Conventional ultrasound (present in
Hospital for last 20 yrs) Vs To purchase a New
color Doppler sonography.
• However, the relative magnitude of the costs and
benefits for the service must be considered when
making this resource-allocation decision.
• If a service costs $100 to implement and results in
a benefit to the hospital of $1,000, and a service
that costs $100,000 to implement results in a
benefit of $1 million, both have a B:C ratio of 10.
• Thus caution should be exercised when using
B:C ratios and CBA as a comparison tool.
• Of all Pharmacoeconomic evaluation methods,
CBA is probably used the least. Because—
Although, method has the advantage of valuing
indirect costs and Intangible costs (monetarily) ,
Valuation of outcomes such as productivity and
quality of life is difficult to perform reliably and
meaningfully.
Summary of Economic evaluations
LIMITATIONS OF PHARMACOECONOMIC
EVALUATION
• The whole process may be open to bias,
in the choice of comparator drug,
the assumptions made, or
in the selective reporting of results.
• This suspicion arises because most studies are
conducted or funded by pharmaceutical
companies.
• Health economics is therefore sometimes
misused as a marketing ploy .
References
• LISA SANCHEZ TRASK, Access Pharmacy Chapter 1. Pharmacoeconomics: Principles,
Methods, and Applications.
http://accesspharmacy.mhmedical.com/content.aspx?bookid=462&sectionid=411007
67.
• Tom Walley, M.D. Chapter 9. Pharmacoeconomics and Economic Evaluation of Drug
Therapies
• SURENDRA G. GATTANI. PHARMACOECONOMICS: A REVIEW. Asian Journal of
Pharmaceutical and Clinical Research Vol.2 Issue 3, July-September 2009.
THANK YOU
Pharmacoeconomics (Basics for MD Pharmacology)