PERIOPERATIVE
BRADYARRYTHMIAS
Moderator- Dr. Surajit Moral
Assistant Professor
Department of Anaesthesiology and Critical Care, GMCH
Presenter- Dr. Anwesha Bayan
PGT- 3
INTRODUCTION
• Arrhythmias are the most common perioperative cardiac abnormalities in
patients undergoing both cardiac and non-cardiac surgery.
• Bradycardia is the most common arrhythmias that occur during anesthesia.
They result in significant causes of morbidity and mortality particularly in elderly
patients
• Bradycardia is defined as a heart rate less than 60 beats/min.
• Relative Bradycardia – is used in explaining a HR which is not actually below
60bpm, is still considered too slow for individual’s current medical condition.
• E.g – a HR of 70bpm is too slow for a patient with cardiogenic or septic shock
• Symptomatic bradycardia, or high grade heart block (third degree heart block)
warrants postponement of elective procedures to facilitate
evaluation ,stabilisation and possible cardiology evaluation.
PATHOPHYSIOLOGY
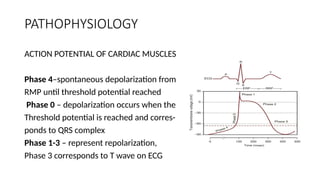
ACTION POTENTIAL OF CARDIAC MUSCLES
Phase 4–spontaneous depolarization from
RMP until threshold potential reached
Phase 0 – depolarization occurs when the
Threshold potential is reached and corres-
ponds to QRS complex
Phase 1-3 – represent repolarization,
Phase 3 corresponds to T wave on ECG
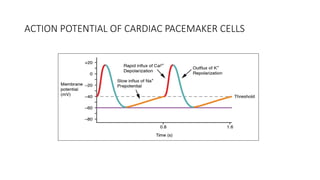
ACTION POTENTIAL OF CARDIAC PACEMAKER CELLS
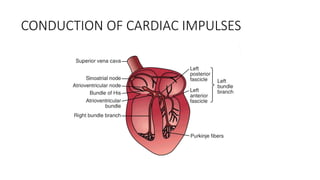
CONDUCTION OF CARDIAC IMPULSES
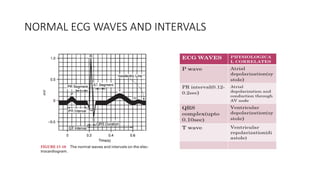
NORMAL ECG WAVES AND INTERVALS
CAUSES OF BRADYARRYTHMIAS
INTRINSIC CAUSE
• Systemic causes
- hypoxia
- hypercarbia
- hypothermia < 34degree celsius
- raised ICT (Cushings reflex)
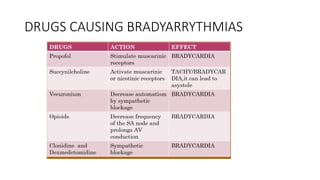
- drugs: opioids, volatile anesthetics, Succinyl choline, vecuronium, beta-blockers, CCBs,
anticholinesterase inhibitors (neostigmine)
• Cardiac causes
- Sick sinus syndrome, sinus bradycardia
- junctional rhythm
- AV nodal block
- Myocardial infarction
VAGAL RESPONSE
- traction on
extraocular muscles (oculocardiac reflex)
oropharynx ( laryngoscopy , intubation and extubation)
bronchus , peritoneum , bowel , rectum
- right atrial distension
- bladder distension
DIRECT EFFECT
- narcotics
- volatile anesthetics
- regional anesthesia
- high spinal / spinal shock
DRUGS CAUSING BRADYARRYTHMIAS
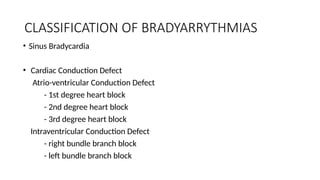
CLASSIFICATION OF BRADYARRYTHMIAS
• Sinus Bradycardia
• Cardiac Conduction Defect
Atrio-ventricular Conduction Defect
- 1st degree heart block
- 2nd degree heart block
- 3rd degree heart block
Intraventricular Conduction Defect
- right bundle branch block
- left bundle branch block
SINUS BRADYCARDIA
• ECG demonstrates a regular rhythm with normal appearing P wave before each QRS
complex and HR < 60bpm
• common in athletes and many individuals during sleep.
• It is due to decreased sympathetic stimulation or increased parasympathetic stimulation.
• sinus bradycardia may be asymptomatic or symptomatic. Asymptomatic patients, no
treatment is required
• in symptomatic patients, experiencing chest pain or syncope immediate transcutaneous
or transvenous pacing is indicated.
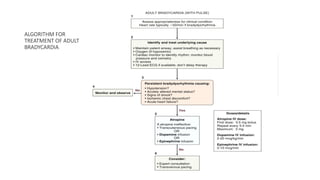
• Atropine 0.5 mg i.v every 3- 5 minutes (to a maximum of 3 mg) may be given to increase
heart rate but should not delay initiation of pacing.
• If cardiac pacing is delayed or pacing capabilities are limited, an epinephrine or
dopamine infusion maybe titrated to response while cardiac pacing is awaited.
• If bradycardia is due to beta-blockers or CCB overdose, or if unresponsive to
atropine-
Glucagon 50-70mcg/kg every 3- 5 minutes until clinical response is achieved or a
total dose of 10 mg is reached.
To maintain clinical effect, a continuous infusion at 2- 10 mg/ hour should be
maintained.
• Bradycardia during neuraxial blockade : incidence is approx. 1.5 per 10,000cases
- can occur any time but most often occurs approx. 1hr after anesthetic
administration
- risk of bradycardia and asystole may extend into the postoperative period even
after the sensory or motor blockade has diminished.
- should be treated aggressively
- in case of severe bradycardia , preparation should be made for management of
asystole , which is treated with CPR (ACLS protocol)
• Recalcitrant bradycardia necessitates transcutaneous / transvenous pacing.
JUNCTIONAL RHYTHM
• occurs when the tissues around the AV node becomes the dominant
pacemaker of the heart
( depressed SA node function, SA node block, delayed AV node conduction)
• generates a rhythm with HR 40-60bpm
• variable relation with P wave
- absent P wave ( buried within QRS complex)
- P wave may preceed the QRS complex ( short PR interval)
- may follow the QRS complex
• causes – myocarditis , myocardial ischaemia, digitalis toxicity
• Atropine ( dose of 0.5mg iv) repeated every 5min , max dose 3mg – used to
treat a slow junctional rhythm if it becomes hemodynamically significant
HEART BLOCKS
• AVHB are broadly classified into 3 categories
- first degree heart block
- second degree heart block
- third degree heart block
• May be transient or permanent
• Transient AVHB can be produced by acute MI and general anesthetics
such as enflurane or halothane in patients using calcium channel
blockers or amiodarone
• Permanent AVHB – usually idiopathic , other causes – Levs or Lenegre
disease , where fibrosis of the conducting system occurs
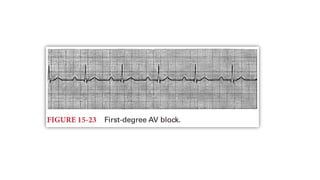
FIRST DEGREE AV BLOCK
• Defined as a delay in the passage of the cardiac impulse through the
AV node resulting in a PR interval of longer than 200 ms.
• Each P wave has a corresponding QRS Complex of normal duration
• considered generally benign, asymptomatic, accompanying normal
ageing
• other causes – myocardial ischemia, inferior wall MI, drugs affecting
AV node conduction ( digoxin, amiodarone)
SECOND DEGREE AV BLOCK
• Second-degree AV block can be suspected when a P wave is present without a corresponding
QRS complex.
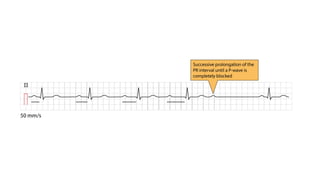
• 1. Mobitz type 1 block (Wenckebach block)
- characterized by progressive prolongation of the PR interval until a beat is dropped.
- it is thought to occur because each successive depolarization produces a prolongation
of the refractory period of the AV node. This process continues until an atrial impulse reaches
the AV node during its absolute refractory period and conduction of that impulse is blocked
completely.
- more benign block, related to AV nodal delay
- easily responsive to atropine and unlikely to progress to complete heart block
- can be the result of myocardial ischemia/infarction, myocardial fibrosis or calcification,
infiltrative or inflammatory disease of the myocardium, also seen after cardiothoracic surgery
- can be associated with certain drugs – CCBs, beta-blockers, digoxin and sympatholytic
drugs
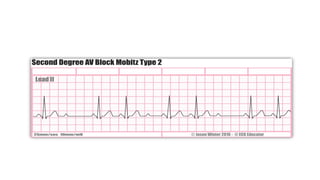
2. Mobitz type 2 block
- characterized by sudden and complete interruption of
conduction (dropped QRS) without PR prolongation.
- related to infranodal block, capable of progressing to complete
heart block
- usually symptomatic with palpitations and near syncope
(common complaints)
- placement of a cardiac pacemaker maybe necessary.
- temporary treatment includes transcutaneous or transvenous
cardiac pacing until a permanent pacemaker in place
- atropine is unlikely to improve bradycardia, isoproterenol
infusion ( chemical pacemaker) helpful as temporary measures
THIRD DEGREE AV BLOCK
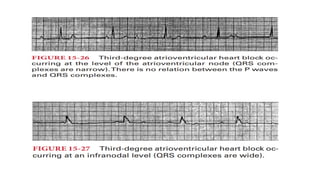
• complete dissociation between the atria and the ventricular beats (complete interruption of
AV conduction)
• can manifest as a slow escape rhythm insufficient to sustain an acceptable cardiac output
• if conduction block near AV node:HR 45-55 and QRS Complex narrow
if the conduction block is below AV node (infranodal) : HR 30-40, QRS Complex wide
• Causes :
- in anesthetized patients: cardiac ischaemia, metabolic or electrolyte abnormalities,
infection or inflammation near the conduction system, reperfusion injury, stunned myocardium
after cardiac surgery
- in adults : fibrotic degeneration of the distal conducting system associated with ageing
(Lenegre disease )
degenerative and calcific changes in more proximal conduction tissue adjacent to
the mitral valve annulus can also interrupt cardiac conduction ( Lev disease)
• treatment : transcutaneous / transvenous cardiac pacing (during
anaesthesia)
IV isoproterenol infusion (acts as chemical pacemaker)
• requires a pacemaker placement unless a reversible cause is identified
TRANSCUTANEOUS CARDIAC PACING
-non–invasive pacing used on a temporary basis until a patient is
stabilised and either an adequate intrinsic rhythm has returned or a
transvenous pacemaker is inserted, whether temporary or permanent.
1. Place the pacing electrodes on the chest
2. Set the demand rate to 60-80/min . The rate can be adjusted
3. Set the current output 2mA above the dose at which consistent
capture is observed.
Transcutaneous pacing may be uncomfortable for the patient .
Sedation should be considered
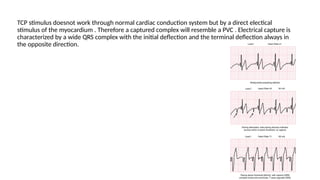
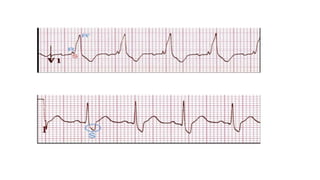
TCP stimulus doesnot work through normal cardiac conduction system but by a direct electical
stimulus of the myocardium . Therefore a captured complex will resemble a PVC . Electrical capture is
characterized by a wide QRS complex with the initial deflection and the terminal deflection always in
the opposite direction.
QRS COMPLEX ABNORMALITIES
• BUNDLE BRANCH BLOCK
- RIGHT BUNDLE BRANCH BLOCK
- LEFT BUNDLE BRANCH BLOCK
• FASCICULAR BLOCK
RIGHT BUNDLE BRANCH BLOCK
• Present in approximately 1% of hospitalized adult patients.
• The conduction delay resulting from RBBB is seldom symptomatic and rarely progresses to advanced AV
block.
• It does not always imply cardiac disease and is often of no clinical significance in patients without
structural heart disease.
• RBBB is due to a disruption of the cardiac impulse as it travels over the RBB.
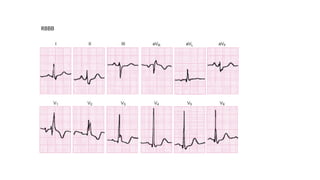
• It is recognized by-
- widened QRS complex >120ms
- rSR configuration in lead V1 and V2 (M shaped QRS complex)
- deep/ slurred S wave > 40ms in lead 1 and V6
* If the QRS is between 110 and 120 ms, with the other criteria for RBBB fulfilled, it is considered an
incomplete RBBB.
• Treatment: Observation and elimination of drugs or clinical factors known to contribute to conduction
disturbance. Pacing capability should be available in the event of progression to complete heart block.
RBBB
LEFT BUNDLE BRANCH BLOCK
• the LBB of the bundle of His composed of two components- LAF and LPF
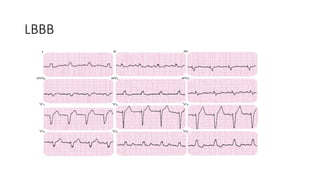
• A complete LBBB is recognized as
- QRS complex > 120ms
- absence of Q wave in lead 1 , V5 and V6
- broad notched or slurred R wave in lead 1, aVL ,V5 and V6
- S and T waves are usually opposite in direction to QRS
• LAHB is the most common hemiblock. LPHB is uncommon because of larger
and better perfused posterior fascicle.
• left axis deviation associated with LAHB
right axis deviation associated with LPHB
• the appearance of LBBB on ECG is often an indication of serious heart
disease (e.g hypertension, coronary artery disease , aortic valve
disease , cardiomyopathy)
• The appearance of LBBB has been observed during anesthesia ,
particularly during hypertensive or tachycardic episodes and may be
signs of myocardial ischaemia
• The presence of LBBB has special implications if insertion of a
pulmonary artery catheter is planned. Third degree heart block can
occur if the catheter induces RBBB in a patient with preexisting LBBB.
• RBBB (usually transient) occurs during insertion of a pulmonary artery
catheter in approximately 2%- 5% of patients.
LBBB
FASCICULAR BLOCK
• Bi fascicular heart block – when RBBB exist in combination with block
of either the left anterior or left posterior fascicle of the LBB.
RBBB+ LAHB is more common than than RBBB+ LPHB
• concern in patients with bifascicular heart block is that ,
perioperative changes in BP , arterial oxygenation and serum
electrolyte concentration might compromise impulse conduction in
the remaining fascicles and lead to third degree heart block
• Treatment : observation and elimination of drugs or clinical factors
known to contribute to conduction disturbances
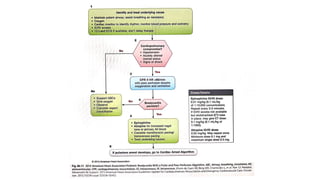
ALGORITHM FOR
TREATMENT OF ADULT
BRADYCARDIA
REFERENCES
• Stoelting’s Anaesthesia and coexisting disease, 3rd
SEA Edition.
• Miller’s Anaesthesia, 9th
edition