Bone and Skin Pathology
Dr. Sidra Arshad
Assistant Professor
Physiology
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 2
0310-7990649
info@medicoseacademics.com
A quick revision of:
1. Diseases of Bone
2. Diseases of Joints
3. Inflammatory and vesicular lesions of skin
4. Disorders of pigmentation
5. Skin malignancies
Dr. Sidra Arshad, Asst. Prof. Physiology 3
0310-7990649
info@medicoseacademics.com
Normal Bone
Organic matrix:
• Cells
• Type I collagen (90% of bone protein)
• Osteocalcin
• Glycoproteins
• Proteoglycans
Inorganic matrix:
• Calcium hydroxyapatite Ca10(PO4)6(OH)2
• Magnesium
• Potassium
• Chloride
• Sodium
• Fluoride
There are 3 cell types:
• Osteoblasts
• Osteocytes
• Osteoclasts
Dr. Sidra Arshad, Asst. Prof. Physiology 4
0310-7990649
info@medicoseacademics.com
Genetic Skeletal Disorders
Achondroplasia Failure of longitudinal bone growth, short limbs, head bigger relative to
limbs, most common cause of dwarfism, associated with increasing
parental age
Osteogenesis
Imperfecta
Generalized osteopenia, brittle bone disease, abnormal synthesis of type
I collagen, abnormally thin sclera with blue hue, hypermobile joints, skin
susceptible to easy bruising
Fibrous
Dysplasia
Painful swelling, deformity, or pathologic fracture of involved bone
(typically ribs, femur, or cranial bones), usually in children and young
adults
Osteopetrosis A hereditary defect leading to decreased osteoclast function, decreased
resorption and thick sclerotic bones
0310-7990649
info@medicoseacademics.com
Osteoporosis
Dr. Sidra Arshad, Asst. Prof. Physiology 5
0310-7990649
info@medicoseacademics.com
Osteopetrosis
Dr. Sidra Arshad, Asst. Prof. Physiology 6
0310-7990649
info@medicoseacademics.com
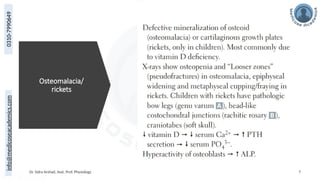
Osteomalacia/
rickets
Dr. Sidra Arshad, Asst. Prof. Physiology 7
0310-7990649
info@medicoseacademics.com
Paget
disease of
bone
(osteitis
deformans)
Dr. Sidra Arshad, Asst. Prof. Physiology 8
Dr. Sidra Arshad, Asst. Prof. Physiology 9
0310-7990649
info@medicoseacademics.com
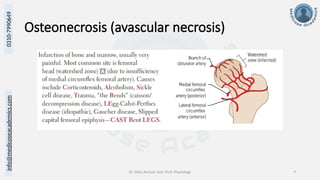
Osteonecrosis (avascular necrosis)
Dr. Sidra Arshad, Asst. Prof. Physiology 10
0310-7990649
info@medicoseacademics.com
Dr. Sidra Arshad, Asst. Prof. Physiology 11
0310-7990649
info@medicoseacademics.com
Dr. Sidra Arshad, Asst. Prof. Physiology 12
0310-7990649
info@medicoseacademics.com
Dr. Sidra Arshad, Asst. Prof. Physiology 13
0310-7990649
info@medicoseacademics.com
Dr. Sidra Arshad, Asst. Prof. Physiology 14
0310-7990649
info@medicoseacademics.com
Dr. Sidra Arshad, Asst. Prof. Physiology 15
0310-7990649
info@medicoseacademics.com
Skin Disorders
Dr. Sidra Arshad, Asst. Prof. Physiology 16
0310-7990649
info@medicoseacademics.com
Pemphigus
vulgaris
• Formation of severe intraepidermal bullae is characteristic
• First lesions occur in the oral mucosa, and extensive skin involvement follows
• lesions often rupture, leaving large denuded surfaces subject to secondary
infection
• characterized by IgG autoantibodies directed against the epidermal intercellular
cement substance
Bullous
pemphigoid
• Clinically much less severe
• Subepidermal bullae, with a characteristic inflammatory infiltrate of eosinophils
in the surrounding dermis
• An autoimmune disorder characterized by IgG autoantibodies directed against
epidermal basement membrane
Dermatitis
herpetiformis
• Recurrent pruritic blistering disorder usually involves the extensor surfaces of
the knees and elbows, scalp, upper back, and sacral area
• Associated with celiac disease - deposits of IgA at the tips of dermal papillae
Erythema
multiforme
• multiple types of lesions
• usually hypersensitivity to coexistent infectious agents, various drugs, a
concomitant connective tissue disorder, or an associated malignancy
Dr. Sidra Arshad, Asst. Prof. Physiology 17
0310-7990649
info@medicoseacademics.com
Disorders of Pigmentation
Albinism:
A failure of pigment production by otherwise intact melanocytes
It occurs in two variants
1. Ocular albinism: is a melanin dysfunction that is limited to the eyes; X-linked disorder
2. Oculocutaneous albinism: is a melanin synthetic defect that involves the eyes, skin, and hair; it
predisposes to basal and squamous cell carcinoma, and malignant melanoma because of sensitivity of
skin to sunlight, inheritance is most often autosomal recessive
Vitiligo:
• Acquired loss of melanocytes in discrete areas of skin appears as depigmented white patches
• No relationship to albinism
• May be of autoimmune etiology;
• Associated with other autoimmune disorders, such as Graves disease and Addison disease
Dr. Sidra Arshad, Asst. Prof. Physiology 18
0310-7990649
info@medicoseacademics.com
Pigmented nevi:
1. Nevocellular nevus (common mole)
Classified as a benign tumor or hamartoma; nevus cells are derived from melanocytes and ordinarily
occur in clusters or nests
2. Blue nevus
• present at birth
• nodular foci of dendritic, highly pigmented melanocytes in the dermis; the blue external
appearance results from the dermal location
3. Spitz nevus (juvenile melanoma)
• always benign
• often characterized by spindle-shaped cells and can be confused with malignant melanoma
4. Dysplastic nevus
• often familial, AD inheritance
• atypical, irregularly pigmented lesion with disorderly proliferation of
• melanocytes, dermal fibrosis, and often subjacent dermal lymphocytic infiltration; may transform
into mal malignant melanoma.
5. Lentigo maligna (Hutchinson freckle)
• a nonfamilial precursor to lentigo maligna melanoma
Dr. Sidra Arshad, Asst. Prof. Physiology 19
0310-7990649
info@medicoseacademics.com
Skin Malignancies
• Squamous cell carcinoma
• Basal cell carcinoma
• Malignant melanoma
Dr. Sidra Arshad, Asst. Prof. Physiology 20
0310-7990649
info@medicoseacademics.com
Squamous Cell Carcinoma
• A common malignant skin tumor
• Usually locally invasive, with less than 5% metastasizing; excision is typically
curative
• Associated with excessive sunlight exposure, affecting sun-exposed areas like the
face (lower part) and hands
• Other associations: arsenic, radiation, radiological exposure
• Frequently arises from preexisting actinic keratosis
• Presentation often includes scaling, indurated, ulcerated nodules with invasion of
dermis by neoplastic epidermal cells
Dr. Sidra Arshad, Asst. Prof. Physiology 21
0310-7990649
info@medicoseacademics.com
Basal Cell Carcinoma
• Typically affects sun-exposed areas, especially the head and neck, upper part of the
face
• Gross presentation often includes pearly papules with overlying telangiectatic
vessels
• Characterized by clusters of darkly staining basaloid cells with a typical palisade
arrangement of nuclei
• While locally aggressive and prone to ulceration and bleeding, it rarely metastasizes
• Surgical resection is almost always curative
Dr. Sidra Arshad, Asst. Prof. Physiology 22
0310-7990649
info@medicoseacademics.com
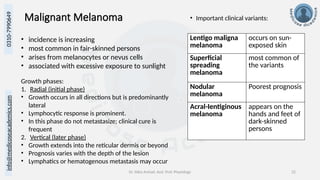
Malignant Melanoma • Important clinical variants:
• incidence is increasing
• most common in fair-skinned persons
• arises from melanocytes or nevus cells
• associated with excessive exposure to sunlight
Growth phases:
1. Radial (initial phase)
• Growth occurs in all directions but is predominantly
lateral
• Lymphocytic response is prominent.
• In this phase do not metastasize; clinical cure is
frequent
2. Vertical (later phase)
• Growth extends into the reticular dermis or beyond
• Prognosis varies with the depth of the lesion
• Lymphatics or hematogenous metastasis may occur
Lentigo maligna
melanoma
occurs on sun-
exposed skin
Superficial
spreading
melanoma
most common of
the variants
Nodular
melanoma
Poorest prognosis
Acral-Ientiginous
melanoma
appears on the
hands and feet of
dark-skinned
persons
Dr. Sidra Arshad, Asst. Prof. Physiology 23
0310-7990649
info@medicoseacademics.com
Thank you.
Please contact us for your questions and queries.
0310-7990649
info@medicoseacademics.com