Presentation by
Dr Abhidha Tripathi
Introduction
Assessment
Rationale for Orthodontic
Treatment
Use of Orthodontics as an adjunct
to Overall therapy
Indications and Contra Indications
Conclusion
Iatrogenic Factors Associated with
Ortho treatment
References
01
o6
02 07
03 08
05
04
• Primary Objective of periodontal therapy is to restore and maintain the health and
integrity of the attachment apparatus of teeth.
• Loss of teeth or periodontal support can result in pathologic tooth migration involving
either a single tooth or a group of teeth.
• This results in the development of a median diastema or general spacing of the teeth,
rotation or tipping of premolars and molars with the collapse of the posterior occlusion
and decreasing vertical dimension.
Malaligned teeth, such as a mesially tipped molar, necessitate additional removal of
tissue on the mesial aspect of the molar abutment to achieve compat?ible paths of
placement for a planned fixed dental prosthesis.
If the molar abutment is orthodontically uprighted before tooth preparation, crown
preparation can be more conservative
• Minor orthodontic tooth movement can significantly enhance the prognosis of
subsequent restorative treatment.
• Uprighting mal positioned abutment teeth can improve axial alignment, create more
favorable pontic spaces, and improve embrasure form in the fixed prosthesis.
• It can also direct occlusal forces along the long axes of the teeth and often leads to a
substantial conservation of tooth structure
• The clinical examination should focus on tooth malpositioning both buccolingually
and mesiodistally.
• The need for orthodontic treatment is determined through a careful analysis of
articulated diagnostic casts, whose usefulness can be enhanced with a dental
surveyor.
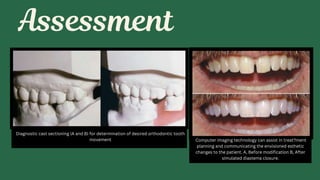
• One helpful procedure is to section a duplicate cast and reassemble it according to
the proposed orthodontic modifications. This facilitates assessing the validity of any
minor tooth movement (e.g., closing diastemas, uprightingmolars, aligning tilted
teeth) and is especially valuable when explaining the treatment proposal to the
patient.
• Diagnostic preparations and waxing procedures
made on these altered casts often clearly illustrate
the benefits of minor tooth movement.
• Many dentists are now using computer imaging
technology to optimize esthetic treatment planning
and improve patient communication. Use of diagnostic preparations (A) and a dental
surveyor (B) in assessing the need for orthodontic
treatment before
Diagnostic cast sectioning (A and B) for determination of desired orthodontic tooth
movement Computer imaging technology can assist in treat?ment
planning and communicating the envisioned esthetic
changes to the patient. A, Before modification B, After
simulated diastema closure.
1. REDUCING PLAQUE RETENTION
• Example: Crowded teeth (arch length deficiency), mesially tipped teeth, usually
into an edentulous area creates plaque accumulation sites that are difficult to
clean.
• They open the distal contact creating an area of fooda impaction.
• Crowding also creates enlarged contact surfaces and altered embrasure
spaces that are displaced apically, thereby becoming less accessible to use
floss and other plaque removing devices.
• In these situations orthodontic treatment can improve the health of the tissues
2. IMPROVING GINGIVAL AND OSSEOUS FORM
• There is an interrelation between the position of the tooth, the shape of the
gingiva and bone that surrounds it.
• For example, lower first or second molar tilted into an edentulous mesial
space.
• In these cases there is a narrow space between its crown and the bone that
easily becomes inflamed and in which case a pocket may develop.
• Orthodontic treatment may improve the shape of the periodontium and
reduces the indications for bone surgery
3. FACILITATING PROSTHETIC REPLACEMENTS
• The uprighting of tilted abutment teeth may be important for a better contoured
crown and this will benefit the periodontal condition.
4. IMPROVING ESTHETICS
• Correction of pathologic tooth migration and diastema between anterior teeth.
• Correction of tongue-thrusting and other habits
1. Uprighting or repositioning of teeth to improve parallelism of abutment teeth
(e.g. tipped abutment teeth)
2. Improving future pontic spaces (e.g. inadequate spaces)
3. Correcting cross bites
4. Extruding teeth/Intruding teeth
5. Correcting crowding of teeth
6. Achieving adequate embrasure space and proper root positioning
7. Repositioning teeth for implant placement
8. Restoring lost vertical dimension
9. Increasing/decreasing overjet /overbite
10. Closure of diastema.
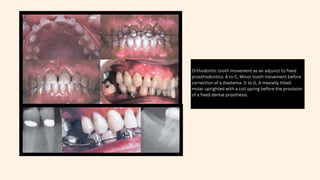
Orthodontic tooth movement as an adjunct to fixed
prosthodontics. A to C, Minor tooth movement before
correction of a diastema. D to G, A mesially tilted
molar uprighted with a coil spring before the provision
of a fixed dental prosthesis.
1. Crowded teeth
2. Closure of anterior diastema,
3. Mesial tilting of molars
4. Open contacts.
1. Persistence of active disease in spite of phase-I therapy procedures.
2. The superimposition of tooth movement on inflamed gingiva may
exacerbate the periodontal problem. This can occur by shifting the position of
plaque subgingivally, increasing the rate of periodontal attachment loss and
altering the morphology of the bone
1. Orthodontic treatment may cause injuries to the teeth and periodontium but in
most of the cases the changes are reversible and regeneration and repair of the
tooth structures and periodontal tissues can occur.
2. Radiography should be performed at regular intervals in order to disclose any
iatrogenic effects during the orthodontic treatment
• CONTEMPORARY FIXED PROSTHODONTICS, ROSENSTEIL – 5 TH EDITION
• FUNDAMENTALS OF FIXED PROSTHODONTICS, SHILLINBURG- 4 TH EDITION
• TEXTBOOK OF PROSTHODONTICS – DEEPAK NALLASWAMY, 2ND EDITION
ThankYou!