oral hypoglycemic agents.Agents which are used for treatment of diabetes mellitus
2.
Overview
◉ The pancreasis both an endocrine gland
that produces the peptide hormones
insulin, glucagon, and somatostatin and
an exocrine gland that produces
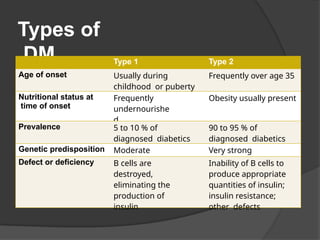
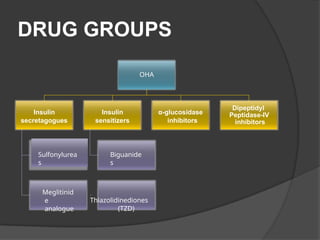
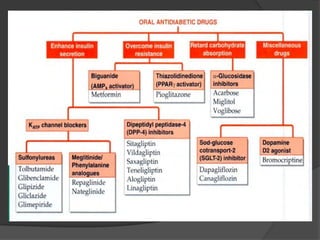
digestive enzymes. The peptide
hormones are secreted from cells
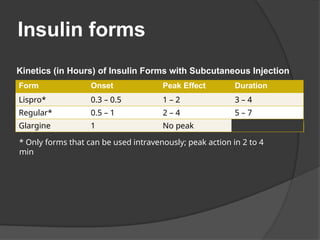
located in the islets of Langerhans (
β
cells produce insulin, α cells produce
glucagon, and δ cells produce
somatostatin). These hormones play an
important role in regulating the
metabolic activities of the body,
particularly the homeostasis of blood
glucose.
3.
Overview
◉ Hyperinsulinemia (due,for example, to
an insulinoma) can cause severe
hypoglycemia. More commonly, a
relative or absolute lack of insulin, such
as in diabetes mellitus, can cause
serious hyperglycemia, which, if left
untreated, can
resul
t
i
n
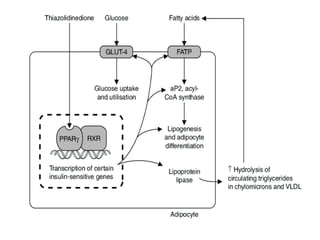
retinopath
y,
nephropathy,
neuropathy,
caanrddiovascul
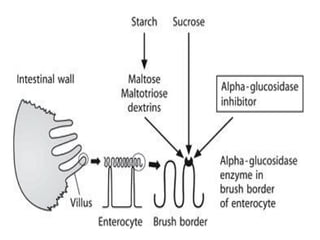
ar
complication
s.
Administration of insulin preparations or
oral hypoglycemic agents can prevent
morbidity and reduce mortality
associated with diabetes.
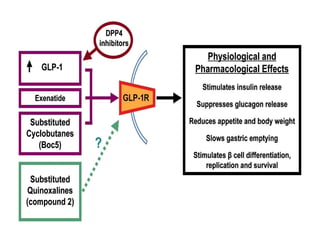
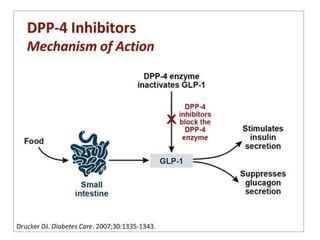
4.
Overview
◉ Anti-diabetic medicationstreat
diabetes mellitus by lowering glucose
levels in the blood. With the
exceptions of
insulin, exenatide, and pramlintide, all
are administered orally and are thus
also called oral hypoglycemic agents or
oral antihyperglycemic agents. There
are different classes of anti-diabetic
drugs, and their selection depends on:
◉ Nature of the diabetes
◉ Age and situation of the person
◉ Other factors.
5.
Diabetes Mellitus Type
I
⦿
Type1 diabetes most commonly afflicts individuals in
puberty or early adulthood, but some latent forms can
occur later in life. The disease is characterized by an
absolute deficiency of insulin caused by massive β-cell
necrosis. Loss of β-cell function is usually ascribed to
autoimmune-mediated processes directed against the
β
- cell, and it may be triggered by an invasion of
viruses or the action of chemical toxins. As a result of
the
destruction of these cells, the pancreas fails to
respond to glucose, and the Type 1 diabetic shows
classic symptoms of insulin deficiency (polydipsia,
polyphagia,
polyuria,
and
weight loss). Type 1 diabetics
require
exogenous insulin to avoid the catabolic state that
results from and is characterized by hyperglycemia
and life-threatening ketoacidosis.
6.
Diabetes Mellitus Type
⦿IIMost diabetics are Type 2. The disease
is
influenced
by
geneti
c
factors, aging, obesity,
and
peripher
al
insulin resistance rather than
by
autoimmune processes or viruses. The
metabolic alterations observed are
milder than those described for Type 1
(for example, Type 2 patients typically
are not ketotic), but the long-term
clinical consequences can be just as
devastating (for example, vascular
complications and subsequent infection
can lead to amputation of the lower
limbs).
7.
Types of
⦿DMDiabetes mellitustype 1is
a disease
caused by the lack of insulin. Insulin
must be used in Type I, which must be
injected.
◉ Diabetes mellitus type 2 is a disease of
insulin resistance by cells. Treatments
include:
⚫ agents that increase the amount of insulin
secreted by the pancreas
⚫ agents that increase the sensitivity of target
organs to insulin
⚫ agents that decrease the rate at which
glucose is absorbed from the gastrointestinal
tract.
8.
Types of
DM Type1 Type 2
Age of onset Usually during
childhood or puberty
Frequently over age 35
Nutritional status at
time of onset
Frequently
undernourishe
d
Obesity usually present
Prevalence 5 to 10 % of
diagnosed diabetics
90 to 95 % of
diagnosed diabetics
Genetic predisposition Moderate Very strong
Defect or deficiency B cells are
destroyed,
eliminating the
production of
insulin
Inability of B cells to
produce appropriate
quantities of insulin;
insulin resistance;
other defects
9.
Insulin forms
Form OnsetPeak Effect Duration
Lispro* 0.3 – 0.5 1 – 2 3 – 4
Regular* 0.5 – 1 2 – 4 5 – 7
Glargine 1 No peak
* Only forms that can be used intravenously; peak action in 2 to 4
min
Kinetics (in Hours) of Insulin Forms with Subcutaneous Injection
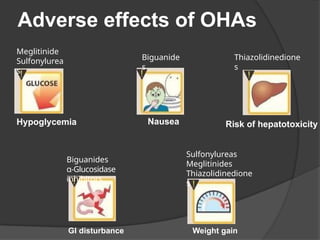
Adverse effects ofOHAs
Meglitinide
Sulfonylurea
s
Hypoglycemia
Biguanides
α-Glucosidase
inhibitors
GI disturbance
Biguanide
s
Nausea
Thiazolidinedione
s
Risk of hepatotoxicity
Sulfonylureas
Meglitinides
Thiazolidinedione
s
Weight gain
14.
1) Insulin secretagogues
◉Useful in the treatment of patients who
have Type 2 diabetes but who cannot be
managed by diet alone.
◉ Best response to OHA is seen in one who
develops diabetes after age 40 and has
had diabetes less than 5 years.
◉ Patients with long-standing disease may
require a combination of hypoglycemic
drugs with or without insulin to control
their hyperglycemia.
◉
Oral hypoglycemic agents should
NOT be given to patients with Type 1
diabetes.
15.
A. Sulfonylureas
glipizide,
and
◉ Theseagents are classified as
insulin secretagogues, because
they promote insulin release
from the β cells of the
pancreas. The primary drugs used
today are tolbutamide and the
second- generation
derivatives,
glyburide,
glimepiride.
16.
A. Sulfonylureas
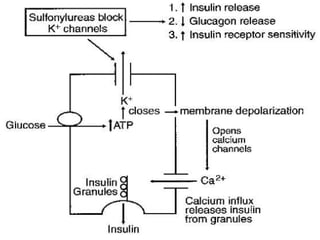
◉ Mechanismof action:
1) stimulation of insulin release from
the β cells of the pancreas by
blocking the ATP-dependent K+
channels, resulting in
depolarization and Ca2+
influx
2) reduction in hepatic glucose
production
3) increase in peripheral
insulin sensitivity.
17.
A. Sulfonylureas
◉ Pharmacokinetics:
◉Given orally, these drugs bind to
serum proteins
◉ Metabolized by the liver
◉ Excreted by the liver or kidney
◉ Tolbutamide has the shortest
duration of action (6-12 hours),
whereas the second-generation
agents last about 24 hours
19.
A. Sulfonylureas
◉ AdverseEffects:
◉ Weight gain
◉ Hyperinsulinemia
◉ Hypoglycemia
◉ These drugs should be used with caution in patients
with hepatic or renal insufficiency, because delayed
excretion of the drug-resulting in its accumulation-may
cause hypoglycemia.
◉ Renal impairment is a particular problem in the case of
those agents that are metabolized to active
compounds, such as glyburide.
◉ Glyburide has minimal transfer across the placenta and
may be a reasonably safe alternative to insulin
therapy for diabetes in pregnancy.
20.
B. Meglitinide analogs
◉This class of agents includes
repaglinide and nateglinide. Although
they are not sulfonylureas, they have
common actions.
21.
B. Meglitinide analogs
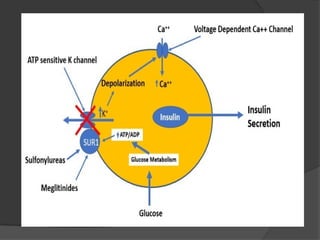
◉Mechanism of action:
◉ Their action is dependenton functioning
pancreatic βcells.
◉ They bind to a distinct site on the sulfonylurea
receptor of ATP-sensitive
potassium channels, thereby
initiating a series of reactions culminating in the
release of insulin.
◉ However, in contrast to the sulfonylureas, the
meglitinides have a rapid onset and a short duration
of action.
◉ They are are categorized as postprandial
glucose regulators.
◉ Meglitinides should not be used in
22.
B. Meglitinide analogs
◉Pharmacokinetics:
◉ These drugs are well absorbed orally
after being taken 1 to 30 minutes
before meals.
◉ Both meglitinides are metabolized
to in
the
inactive products by
CYP3A4
liver.
◉ Excreted through the bile.
24.
B. Meglitinide analogs
◉Adverse Effects:
◉ Incidence of hypoglycemia is lower than
that of the sulfonylureas.
◉ Repaglinide has been reported to
cause severe hypoglycemia in
patients who are also taking the
lipid-lowering drug gemfibrozil.
◉ Weight gain is less of a problem
with the meglitinides than with
the sulfonylureas.
◉ Must be used with caution in
25.
2) Insulin sensitizers
◉Two classes of oral agents-the
biguanides and thiazolidinediones
improve insulin action. These
agents lower blood sugar by
improving target- cell response to
insulin without increasing
pancreatic insulin secretion.
◉ They address the core problem in
Type II diabetes—insulin
resistance.
26.
A. Biguanides
◉ Metformin(glucophage), the
only currently available
biguanide
◉ it increases glucose uptake and
utilization by target tissues, thereby
decreasing insulin resistance.
◉ Requires insulin for its action, but it
does not promote insulin secretion.
◉ Hyperinsulinemia is not a problem.
Thus, the risk of hypoglycemia is far
less than that with sulfonylureas
27.
A. Biguanides
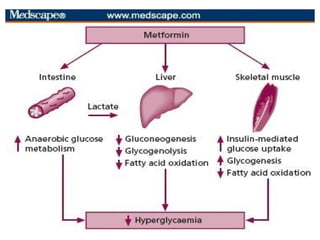
◉ Mechanismof action:
◉ reduction of hepatic glucose output,
largely by inhibiting hepatic
gluconeogenesis.
◉ Slowing intestinal absorption of sugars
◉ Improves peripheral glucose uptake
and utilization. or
in
agents
,
◉ Metformin may be used
alone combination with one of
the other as well as with insulin.
whe
n
◉ Hypoglycemia has
occurred metformin was taken in
combination.
29.
A. Biguanides
◉ Pharmacokinetics:
◉Metformin is well absorbed orally, is
not bound to serum proteins
◉ It is not metabolized
◉ Excretion is via the urine.
30.
A. Biguanides
◉ Adverseeffects:
◉ These are largely
gastrointestinal.
◉ Contraindicated in diabetics
with
ahnedp/aotri
c
disease,
infarction,
severe
acut
e
renal
myocardi
al
infection, or
diabetic
ketoacidosis
.
◉ It should be used with caution in patients
greater than 80 years of age or in those with
a history of congestive heart failure or
alcohol abuse.
◉ Long-term use may interfere with vitamin
B12
absorption.
31.
B. Thiazolidinediones
◉ Anothergroup of agents that are insulin
sensitizers are the thiazolidinediones
(TZDs) or, more familiarly the glitazones.
◉ Although insulin is required for their action,
these drugs do not promote its release
from the pancreatic β cells; thus,
hyperinsulinemia does not result.
◉ Troglitazone was the first of to be
tahpepsreoved for the treatment of Type 2
diabetic, but was withdrawn after a number
of deaths due to hepatotoxicity were
reported. Presently, two members of this
class are available, pioglitazone and
rosiglitazone.
33.
B. Thiazolidinediones
◉ Mechanismof action:
◉ Exact mechanism by which the TZDs
lower insulin resistance remains to be
elucidated
◉ They are known to target the peroxisome
proliferator-activated receptor-γ (PPARγ)-α
nuclear hormone receptor. Ligands for
PPARγ regulate adipocyte production and
secretion of fatty acids as well as glucose
metabolism, resulting in increased
insulin sensitivity in adipose tissue, liver,
and skeletal muscle.
34.
B. Thiazolidinediones
◉ Pharmacokinetics:
◉Both pioglitazone and rosiglitazone are absorbed
very well after oral administration and are
extensively bound to serum albumin.
by
different
◉ Both undergo extensive
metabolism cytochrome P450
isozymes.
◉ Pioglitazone:
⦿
Renal elimination is negligible, with the
majority of the active drug and metabolites
excreted in the bile and eliminated in the feces.
◉ Rosiglitazone:
◉ The metabolites are primarily excreted in the
urine.
35.
B. Thiazolidinediones
◉ AdverseEffects:
⦿ Very few cases of liver toxicity have been
reported with rosiglitazone or pioglitazone.
◉ Weight increase can occur, possibly through
the ability of TZDs to increase subcutaneous
fat or due to fluid retention.
◉ Glitazones have been associated
with osteopenia and increased fracture risk.
◉ Other adverse effects include headache
and anemia.
36.
3) α-glucosidase inhibitors
◉Alpha-glucosidase inhibitors are oral
anti- diabetic drugs used for diabetes
mellitus type 2 that work by preventing
the digestion of carbohydrates (such as
starch and table sugar). Carbohydrates
are
normallyconvertedinto simple
sugars (monosaccharides),
absorbed
through
whic
h
the
can
be
intestin
e.
Hence, alpha-glucosidase inhibitors
reduce the impact of carbohydrates on
blood sugar.
α-glucosidase inhibitors
◉ Mechanismof action:
◉ These drugs are taken at the beginning of meals.
They act by delaying the digestion of carbohydrates,
thereby resulting in lower postprandial glucose levels.
Both drugs exert their effects by reversibly inhibiting
membrane- bound α-glucosidase in the intestinal
brush border. This enzyme is responsible for the
hydrolysis of oligosaccharides to glucose and other
sugars. Consequently, the postprandial rise of blood
glucose is blunted. Unlike the other oral hypoglycemic
agents, these drugs do not stimulate insulin release,
nor do they increase insulin action in target tissues.
Thus, as monotherapy, they do not cause
hypoglycemia. However, when used in combination
with the sulfonylureas or with insulin, hypoglycemia
may develop.
40.
α-glucosidase inhibitors
◉ Pharmacokinetics:
◉Acarbose is poorly absorbed.
It is metabolized primarily by
intestinal bacteria, and some of
the metabolites are absorbed
and excreted into the urine. On
the other hand, miglitol is very well
absorbed but has no systemic
effects. It is excreted unchanged by
the kidney.
41.
α-glucosidase inhibitors
◉ Adverseeffects:
◉ The major side effects
are diarrhea,
and
abdominal
Patieinnftlsamwmitahtory
flatulenc
e,
cramping
. bowel
d
i
n
i
s
t
e
e
s
a
t
i
s
n
e
a
,
l
colonic ulceration,
or
obstruction should not
use
these
drugs.
43.
4) Dipeptidyl peptidase-4
inhibitor
◉DPP-4 inhibitors or gliptins, are a class of oral
hypoglycemics that block DPP-4. They can be used
to treat diabetes mellitus type 2.
◉ The first agent of the class - sitagliptin - was
approved by the FDA in 2006.
◉ Glucagon increases blood glucose levels, and
DPP-
4 inhibitors reduce glucagon and blood glucose
levels. The mechanism of DPP-4 inhibitors is to
increase incretin levels (GLP-1 and GIP), which
inhibit glucagon release, which in turn increases
insulin secretion, decreases gastric emptying, and
decreases blood glucose levels.
44.
Dipeptidyl peptidase-4
inhibitor
◉ Sitagliptinis an orally active
dipeptidyl peptidase-IV (DPP-IV)
inhibitor used for the treatment
of patients with Type
2 diabetes. Other agents in this
category are currently in
development.
46.
Sitagliptin
◉ Mechanism ofaction:
◉ Sitagliptin inhibits the enzyme DPP- IV,
which is responsible for the inactivation
of incretin hormones, such as glucagon-
like peptide-1 (GLP-1). Prolonging the
activity of incretin hormones results in
increased insulin release in response to
meals and a reduction in inappropriate
secretion of glucagon. Sitagliptin may be
used as monotherapy or in combination
with a sulfonylurea, metformin or a
glitazone.
47.
Sitagliptin
◉ Pharmacokinetics:
◉ Sitagliptinis well
absorbed
after
oral
administration. Food does not affect
the extent of absorption. The majority
of sitagliptin is excreted unchanged
in the ar
e
rena
l
urine. Dosage adjustments
recommended forpatients
with dysfunction.
48.
Sitagliptin
◉ Adverse Effects:
◉In general,
tolerate
d,
adverse
sitagliptin is
well the most
common
with
effects
being
and headache.
Rnaatesospohfarhyynpgoitgislycemia are
comparable to those with placebo
when sitagliptin is used as
monotherapy or in combination with
metformin or pioglitazone.






 Most read