
















































OHA
Dr P K Maharana
Introduction
• According to a report in 2017 by International Diabetes Federation
(IDF), 425 million persons suffer from diabetes mellitus out of
which more than 90 percent are adults and 352 million had
impaired glucose tolerance (IGT) .
• In individuals suffering from type II diabetes mellitus (T2DM),
hyperglycemia is not the only characteristic; it also involves multiple
complications such as kidney failure, blindness, heart attack, stroke,
and amputations of the lower limb.
• Ample proof suggests that normoglycemia accomplishment will
mitigate the risk of complications linked with DM.
• Diet and exercise are first line treatments along with oral
hypoglycaemic drugs to achieve the goal of improving glycaemic
control and preventing both microvascular and macrovascular
complications.
T2 DM
• T1DM is mostly found in the young where as
T2DM is an adult-related condition.
• The risk of T2DM increases with age which is due
to the deficiency of insulin secretion which
develops with age, and growing insulin resistance
caused by a change in body composition.
• Increase in body weight which leads to obesity is
closely associated with diabetes in a condition
termed diabesity.
• This is because increase in body weight leads to
increased insulin resistance
Classifications of OHA
• 1. Biguanides : Phenformin & Metformin
• 2. Sulphonylureas:
1st. Generation: Acetohexamide, Chlorpropamide, Tolazamide,
Tolbutamide.
2nd. Generations : (Glyburide , Glipizide , Glimepiride )
• 3. Meglitinides: (Repaglinide ,Nateglinide) .
• 4. Thiazolidinediones : (Pioglitazone,Rosiglitazone).
• 5. α-Glucosidase inhibitors: (Acarbose, Miglitol)
• 6. Incretin agonists
• 7. DPP-4 inhibitors ( Sitagliptin, Vildagliptin, Saxagliptin,)
Biguanides
• Phenformin :- Taken out of use in 1970s because of Lactic Acidosis.
• Metformin:- Effective & safe.
• It has been used in Europe for over thirty years, whereas in the United States it has
been available since 1995. Metformin should be prescribed to all people with type
2 diabetes, unless contraindicated.
• Current recommendations of the American Diabetes Association (ADA) and
European Association for the Study of Diabetes (EASD) include metformin, diet
and exercise as first-line therapy for the treatment of patients with type 2
diabetes, irrespective of the presence of overweight status.
• In contrast to sulfonylureas, metformin does not directly stimulate insulin
secretion;
 Its major effects are
 To increase insulin action and
 Insulin-mediated glucose utilization in peripheral tissues (such as muscle and
liver), particularly after meals, and to
 Decrease hepatic glucose output.
Dose
• Dose: To start with 500mg in evening with dinner, The
usual effective dose is 1,500 to 2,000 mg/day per day;
the maximum dose of 2,550 mg/day (850 mg TID).
• A new extended release formulation of metformin
was recently introduced to the market (Glucophage XR),
allowing a more convenient once-daily dosing regimen.
• Combination tablets of metformin and sulfonylureas,
thiazolidinediones, or dipeptidyl peptidase (DPP)-4 inhibitors
are also available to increase patients’ compliance.
Side effects of Metformin
• Gastrointestinal are most common side effects. 10% of the
patients reports GI disturbances with the onset of treatment.
(A metallic taste in the mouth, Mild anorexia, Nausea,
Abdominal discomfort and, Soft bowel movements or
diarrhea)., which disappears stating slowly with low dose.
• Lactic Acidosis: Lactic acidosis is predominantly due to a lack
of lactate's clearance than to an increased production.
• When used according to current prescribing
recommendations, however, the risk of metformin-induced
lactic acidosis is close to zero .
Contraindications
• Metformin should not be used in patients with elevated
serum creatinine levels, (1.4 mg per dL or more in women
and 1.5 mg per dL or more in men.
• In patients undergoing contrast studies, metformin
therapy should be withheld for approximately 48 hours
following the procedure or until it has been determined
that renal function has returned to baseline.
• Other situations in which metformin therapy should be
avoided include cardiogenic or septic shock, congestive
heart failure, severe liver disease, pulmonary insufficiency
with hypoxemia or severe tissue hypoperfusion.
Sulphonylureas
• Sulfonylureas were the mainstay of
antidiabetic therapy since the early 1950s.
• Following the release of the University Group Diabetes
Program (UGDP) study, which implicated tolbutamide in
increased mortality due to cardiovascular events, the use of
the first generation sulfonylureas (acetohexamide,
chlorpropamide, tolbutamide and tolazamide) quickly fell out
of favour.
1St Generation Sulfonylureas
• They are - Tolbutamide, Chlorpropamide,
Tolazamide, & Acetohexamide.
Because of Hypoglycaemia the 1st generation of
drugs fall out of favour.
2nd generation Sulphonylureas
 Drugs are : (Gliclazide, Glibenclamide, Glimepiride,
gliquidone).
• The second generation have a potency that allows them to
be given in much lower doses than the first generation.
• Sulfonylureas can be used as monotherapy, or in combination
with other oral hypoglycemic drugs or insulin.
• All sulfonylureas have been associated with weight gain,
unless the diabetic diet and exercise program are followed,
and thus are not suggested as first choice for obese patients.
• Glibenclamide is a long acting drug & gliquidone has a shorter
duration of action.
Mechanism of Action
• Stimulating insulin release from the insulin
secreting ß-cells of pancreas and may slightly
improve insulin resistance in peripheral target
tissues (muscle, fat).
Mechanism of Action
• Sulfonylureas are effective only in patients with functioning
pancreatic β cells.
• Sulfonylureas act at the pancreatic β-cell membrane by
closing ATP-sensitive potassium channels, which leads to an
enhanced insulin secretion independent of glucose.
• The effects of sulfonylureas are initiated by their binding to
and blocking an ATP-sensitive K+ channel.
• Glimepiride has been shown to have an additional effect: it
increases the sensitivity of peripheral tissues to insulin.
• Enhancing peripheral insulin receptor sensitivity and
reducing glycogenolysis.
Pharmacokinetics
• Sulfonylureas are well absorbed after oral
administration.
• Glipizide absorption is delayed by food.
• All sulfonylureas are highly bound to plasma
protein (90% to 99%).
• Plasma protein binding is least
for chlorpropamide and greatest for glyburide.
• Sulfonylureas are metabolized in the liver and
excreted in the urine.
Draw Backs ( Sulfonylureas)
• Hypoglycaemia ( frequent hypoglycaemia),
leads to cardiovascular events like
arrhythmias, cardiovascular mortality.
• Weight gain
• Patients using sulfonylureas and metformin in
combination are reportedly at greater risk
of cardiovascular mortality than patients using
metformin alone.
Dose of Sulfonylureas
• Drugs with longer half-lives ( Glibenclamide and
glimepiride) can be given once daily.
• They cause greater suppression of overnight
hepatic glucose output, thereby lowering fasting
blood glucose concentrations more; these
benefits, however, may be counterbalanced by an
increased risk of hypoglycemia.
• The usual dose of glyburide is 2.5 to 10 mg twice
daily.
Dose of Glimepiride
• Dose: 1-2 mg once a day in an adult. Not more than 8mg in
a single day.
• Swallow the tablets whole, with a drink of water. Do not
chew them.
• With food.
 Early warning signs of low blood sugar include:
• feeling hungry
• trembling or shaking
• sweating
• feeling confused
• having problems concentrating
Contraindications Sulfonylureas
• Hypersensitivity to Sulfa group of drugs.
• Ketosis
• Pregnancy
• Caution in reduced hepatic & renal function.
Meglitinides
• The meglitinides ( repaglinide and nateglinide), are short-acting glucose-lowering drugs. They
were designed to achieve more physiologic insulin release and less risk for hypoglycemia.
• Mechanism action : Same as that of Sulphonylureas, release of insulin from the pancreatic
beta cells, this action is mediated through a different binding site on the “sulfonylurea
receptor” of the beta cell, and the drug has somewhat different characteristics when
compared with the sulfonylureas. A shorter half life and quicker on set of action ( 15-30
minutes, patients should be instructed to administer a dose immediately before a meal.
• The meglitinides can be used as monotherapy, or in combination with other oral
hypoglycemic drugs like metformin, resulting in superior glycaemic control than with either
agent used as monotherapy, a greater decrease in postprandial glucose and a decreased risk
of hypoglycemia.
• Repaglinide had similar efficacy in reducing HbA1C values as metformin, whereas nateglinide
was similar or slightly less effective.
• DOSE: The recommended starting dose of repaglinide is 0.5 mg before each meal for patients
who have not previously taken oral hypoglycemic drugs.
• Repaglinide can be titrated to a dosage of 4 mg before each meal (maximum dosage of 16 mg
per day).
• Nateglinide can be titrated to a dosage of 120 mg taken immediately before each meal.
• Hypoglycemia is the most common adverse effect.
• Nateglinide is hepatically metabolized, with renal excretion of active metabolites.
• As repaglinide is principally metabolized by the liver, with less than 10 percent renally
excreted, it is the drug of choice in patient with impaired renal function .
Meglitinides
• There are no long-term studies of meglitinides
assessing cardiovascular outcomes or
mortality in patiens treated with his class of
drugs.
• Whether meglitinides are associated with
poorer outcomes after a myocardial infarction
is not known.
• However, since its mode of action is similar to
sulfonylureas, the same concern exists.
Thiazolidinediones
• During the last decade a new class of drugs have been
available for treatment of type 2 diabetes: the
thiazolidinediones (troglitazone, rosiglitazone and
pioglitazone).
• Actually only two thiazolidinediones (rosiglitazone and
pioglitazone) are currently marketed.
• Mechanism of Action: Thiazolinediones improve glycaemia
reducing insulin resistance and preserving pancreatic
beta-cell function with different mechanism of action;( as
example, the predominant effect of metformin is to inhibit
hepatic glucose production, whereas thiazolidinediones
act mainly by improving peripheral uptake and utilization
of glucose in muscle and fat, finally decreasing liver
glucose production )
Thiazolidinediones
• In human adipocytes, rosiglitazone treatment increases expression of genes involved in promoting
lipid storage and decreases expression of genes associated with inflammation, such IL-6 .
• These drugs activate one or more peroxisome proliferator-activated receptors (PPARs), which
regulate gene expression in response to ligand binding .
• PPAR-α is expressed mostly in liver, heart, skeletal muscle, and vascular walls. It is interesting to
note that various thiazolidinediones have differential effects on PPAR-γ and PPAR-α.
• Troglitazone and rosiglitazone are purely PPAR-γ agonists, while pioglitazone also exerts some PPAR-
α effects.
• PPAR-γ is found predominantly in adipose tissue, pancreatic beta-cells, vascular endothelium, and
macrophages; its concentration is also increased in skeletal muscle of obese and diabetic patients
[26]. PPAR-α is expressed mostly in liver, heart, skeletal muscle, and vascular walls. It is interesting
to note that various thiazolidinediones have differential effects on PPAR-γ and PPAR-α. Troglitazone
and rosiglitazone are purely PPAR-γ agonists, while pioglitazone also exerts some PPAR-α effects.
This may account for different effects within this class of drugs. In adipose tissue the insulin-
sensitizing effect may be related to the production of adipokines via PPAR-gamma activation
• Pioglitazone and rosiglitazone similarly improve blood glucose level; their efficacy is comparable to
metformin as monotherapy.
• However, thiazolidinediones are not generally indicated over metformin for initial therapy of type 2
diabetes as they are among the most expensive oral agents.
Thiazolidinediones
• Thiazolidinediones may have antiinflammatory, antithrombotic, and
antiatherogenic properties.
• Although they seem to improve a number of cardiovascular risk
factors and their surrogate cardiovascular endpoints (dyslipidemia,
endothelial function, vascular smooth muscle proliferation, markers
of inflammation [30], carotid intima media thickness [31], vascular
reactivity and progression of atherosclerosis on coronary
intravascular ultrasound [32,33]), both drugs enhance incidence of
heart failure.
• However, they might have different effects on ischemic outcomes
[34,35]. Some studies and meta-analyses have suggested that
rosiglitazone increase the risk of myocardial infarction (MI) [36,37],
not confirmed by other studies [38,39], whereas pioglitazone may
not have the same cardiovascular risk profile than rosiglitazone:
α-Glucosidase Inhibitors
• α-Glucosidase inhibitors include acarbose and miglitol.
• Mechanism of Action: They act on α-glucosidase, an
enzyme found in brush border cells of small intestine,
cleaving more complex carbohydrates into simple
sugars.
• α-Glucosidase inhibitors  inhibits the breakdown
and absorption of carbohydrates (dextrins, maltose,
sucrose and starch; no effect on glucose); impact is on
postprandial hyperglycemia and their effect on FPG
levels is modest.
• They have been associated with a reduction in HbA1c
& Post Prandial Glucose level.
α-Glucosidase Inhibitors
• Complications: Main side effects of α- glucosidase
inhibitors are flatulence, abdominal discomfort, bloating
and diarrhea, which reduce compliance in treated patients.
• Similar to metformin, patients should be instructed to take
this medication with food, starting with the lowest effective
dose and titrated slowly over intervals of two to four week.
• Although hypoglycemia is not typically associated with
monotherapy with α- glucosidase inhibitors, it can occur in
combination with other drugs.
• It is important, to inform patients that the traditional
treatment for hypoglycemia may be blocked during
treatment with α- glucosidase inhibitors and only glucose
should be consumed in this condition.
Contraindications (α-Glucosidase
Inhibitors)
• Therapy with acarbose has been linked to elevations
in serum transaminase levels and the use of this agent is
contraindicated in patients with liver cirrhosis.
• It has been shown to increase proportionally to the
degree of renal dysfunction and their use in patients with
a serum creatinine level more than 2.0 mg per dL (180
μmol per L) is not recommended.
• Other contraindications include patients with
inflammatory bowel disease or a history of bowel
obstruction.
Incretins
• Incretin hormones are : GLP-1 (glucagon-like peptide-1) and GIP (gastric inhibitory peptide).
• These incretins are released within minutes of food intake, has a shorter half life of two minutes ,
as degraded by the enzyme DPP-4 quickly after its release.
• Its level decreases in type2 diabetes.
• GLP-1 is a hormone secreted by enteroendocrine L cells of the small intestine.
i. It stimulates secretion of insulin by the Beta cells, glucose dependant so dose
not produce hypoglycaemia seen with Sulfonylurea.
Ii. decreases Glucagon concentration &
Iii. delays gastric emptying.
• GIP is a hormone secreted in the stomach and proximal small intestine by
neuroendocrine K-cells.
Its half-life is approximately 7 minutes in healthy individuals and 5 minutes in individuals with type 2
diabetes
Advantages
1. No Hypoglycaemia when used as mono
therapy.
• 2. GLP-1 exhibits a short half-life of one to two
minutes due to N-terminal degradation by the
enzyme DPP4 ( Di peptidyl peptidase IV).
• 3.GLP-1 might have beneficial effects on
myocardial function: improves myocardial contractility,
improves glucose uptake in normal and post-ischemic rat
hearts, induces an endothelial-dependent reduction in
vascular tone of rat lungs.
Side effects of Incretin mimetics
• Hypoglycemia: Hypoglycaemic events are mainly observed
when combinations are used: in 20–30% of patients treated
in combination with a sulfonylurea and in 13% of patients
treated in combination with a thiazolidinedione,
hypoglycaemia is not observed with metformin.
• There have been reports of acute pancreatitis (necrotizing
or hemorrhagic) in patients taking exenatide.
• (The overall reported rate for pancreatitis in exenatide
users is 1 in 3,000 and for the more severe necrotizing or
hemorrhagic forms, less than 1 in 10,000, which is similar to
the background rate in patients with diabetes mellitus).
Incretin Mimetics and Incretin
Enhancers Drugs
• Exenatide has a relatively short mean terminal half-life of 2.4 hours.
• Elimination :
• The predominant route of elimination is via glomerular filtration with subsequent
proteolytic degradation; consequently, Exenatide is not recommended for use in
patients with severe renal impairment (GFR<30 mL/minute) or end-stage renal
disease.
• Clinical guidelines suggests that it is indicated as an adjunctive therapy to
improve glycaemic control in patients with type 2 diabetes who are already
receiving metformin, a sulfonylurea, or both, but continue to have suboptimal
glycaemic control.
• Dose: Exenatide should be initiated at 5 mcg per dose, administered twice daily at
any time within the 60-minute period before the morning and evening meals.
• Exenatide lowers glycosylated hemoglobin (HbA1C) levels by 0.4% to 0.9%, with
weight reductions of 0.9 to 3.1 kg. Reductions of systolic blood pressure ( 3.4–3.7
mm Hg) and diastolic blood pressure (0.8–2.3mm Hg) have also been reported.
Mechanism of Action of GLP-1
Agonists.
• Increasing insulin production
• Decreasing glucagon release
• Slowing the rate at which food leaves the
stomach
• Feeling less hungry (having a sense of fullness)
so that you feel satisfied with less food
GLP-1 Agonists
• Dulaglutide (Trulicity)
• Exenatide (Byetta)
• Extended-release exenatide (Bydureon)
• Liraglutide (Victoza)
• Lixisenatide (Adlyxin)
• Semaglutide (Ozempic, Rybelsus)
• Tirzepatide (Mounjaro)
• All of these drugs are given as injections except
Semaglutide (Rybelsus), which is an oral formulation.
Mechanism of Action
• DPP-4 is a ubiquitous enzyme that acts on incretin hormones, and
degrades these hormones immediately.
• DPP-4 inhibitors : By inhibiting the enzyme DPP-4 increase the levels of incretin
hormones,GLP-1 and GIP, which in turn increase beta-cell insulin secretion in the
pancreas, thereby reducing postprandial and fasting hyperglycemia.
• Incretin hormones are : GLP-1 (glucagon-like peptide-1) and GIP (gastric
inhibitory peptide).
• These incretins are released within minutes of food intake.
• GLP-1 is a hormone secreted by enteroendocrine L cells of the small intestine.
• i. It stimulates secretion of insulin by the Beta cells, decreases Glucagon concentration
& delays gastric emptying.
ii. It has a half-life of fewer than 2 minutes.
• GIP is a hormone secreted in the stomach and proximal small intestine by
neuroendocrine K-cells.
i. Its half-life is approximately 7 minutes in healthy individuals and 5 minutes in
individuals with type 2 diabetes
DPP-4 inhibitors
• Sitagliptin, Vildagliptin and Saxagliptin are DPP-IV inhibitors.
• Are approved as initial pharmacologic therapy for the treatment of
type 2 diabetes;
• As a second agent in those who do not respond to a single agent,
such as a sulfonylurea, metformin or a thiazolidinedione;
• As a third agent when dual therapy with metformin and a
sulfonylurea does not provide adequate glycemic control.
• Dose: The usual dose of Sitagliptin is 100 mg once daily, with
reduction to 50 mg for moderate to severe renal insufficiency (GFR
<30 to 50 mL/min) and 25 mg for severe renal insufficiency (<30
mL/min).
• Dose of Saxagliptin is 2.5 or 5 mg once daily, with the 2.5 mg dose
recommended for patients with moderate to severe chronic kidney
disease (GFR ≤ 50 mL/min) and for patients taking strong
cytochrome P450 3A4/5 inhibitors (e.g., ketoconazole).
DPP4
• Mechanism of Action :
• DPP-4 inhibitors mimic the therapeutic effects of
incretin mimetics
•  Stimulation of insulin secretion,
•  Inhibition of glucagon secretion,
•  Preservation of β-cell mass and inhibition of
apoptosis.
• These drugs display quite similar efficacy in lowering
HbA1C (≤1% reduction) compared with other
antihyperglycemic agents, but they are weight neutral and
have a low potential for hypoglycaemia when used as
monotherapy.
DPP4 inhibitors side effects
• One safety concern involves the potential of DPP-4 inhibitors to interfere
with immune functions: indicates an increased risk for infection
(nasopharyngitis and urinary tract infection) and headache.
• Other adverse effects occurring with more frequency in sitagliptin—
treated include, back pain, osteoarthritis, and extremities pain .
• DPP-4 inhibitors have minimal to no interactions with other drugs because
of their pharmacokinetic properties, the exception being saxagliptin.
• Saxagliptin is metabolized to its active form by CYP3A4/5; hence the levels
of the drug and its active metabolite might be modified when
administered along with drugs affecting CYP3A4/5 isoforms such as
ketoconazole, diltiazem (inhibitors of CYP3A4/5), or rifampicin (inducer of
CYP3A4/5).
• Dose adjustments of saxagliptin may be necessary for such instance
Adverse effects
• Gliptins are associated with a low incidence of adverse events, including
hypoglycemia, and have weight-neutral effects.
• However, the risk of hypoglycemia increases when used in conjunction
with sulfonylureas.
• The most common side effects noticed with the DPP-4 inhibitors
sitagliptin and saxagliptin are upper respiratory tract infection,
nasopharyngitis, headache, urinary tract infection, arthralgia.
• Reports of acute pancreatitis, including fatal and non-fatal hemorrhagic or
necrotizing variants, have correlations with the use of sitagliptin,
vildagliptin, and saxagliptin in post marketing data.
• DPP-4 inhibitors (alogliptin, sitagliptin, saxagliptin, linagliptin) did not
show an increased risk of cardiovascular death, non-fatal myocardial
infarction, or non-fatal stroke when compared to placebo in patients
with type 2 diabetes, although saxagliptin had an association with an
increased rate of hospitalization for heart failure.
Contraindications
DPP4 inhibitors
 Contraindications to gliptins include:
• 1. Type 1 diabetes and diabetic ketoacidosis.
• 2. Sitagliptin is contraindicated in individuals who are
sensitive to the drug or its components.
• 3.Caution is necessary when using gliptins in patients with a
history of pancreatitis; it would be reasonable to discontinue
these drugs if pancreatitis is suspected.
Combination Therapy
• When mono therapy fails.
• A two drug combination: sulfonylurea plus metformin, a
sulfonylurea plus an alpha-glucosidase inhibitor, a sulfonylurea plus
a thiazolidinedione, metformin plus repaglinide, biguanide plus
alpha-glucosidase inhibitor, and metformin plus a thiazolidinedione.
• A three drugs combinations: (sulfonylurea, metformin,
thiazolidinedione or sulfonylurea, metformin, alpha-glucosidase inhibitor).
SGLT-2 Inhibitors
• There are four SGLT-2 inhibitors approved for use in people with type 2
diabetes in the United States:
• Canagliflozin (Invokana)
• Dapagliflozin (Farxiga)
• Empagliflozin (Jardiance)
• Ertugliflozin (Steglatro)
• This group of medications works by acting on the kidneys, so there is an
increased elimination of blood sugar into the urine.
• At the same time, the drugs help to reduce blood pressure and promote
weight loss.
• SGLT-2 inhibitors are sometimes recommended for people with type 2
diabetes who have high A1C levels.
• SLGT-2 inhibitors have been shown in studies to lessen the progression of
kidney disease by 45% and to reduce the risk of hospitalization due to
heart failure (by 31%).
• 1. Metformin should be started at the time type 2 diabetes
is diagnosed unless there are contraindications.
• 2. Metformin is effective and safe, is inexpensive, and may
reduce risk of cardiovascular events and death.
• 3. The principal side effects of metformin are
gastrointestinal intolerance due to bloating, abdominal
discomfort, and diarrhea; these can be mitigated by gradual
dose titration.
• 4.A recent randomized trial confirmed previous
observations that metformin use is associated with vitamin
B12 deficiency and worsening of symptoms of neuropathy
• The drug is cleared by renal filtration, and very
high circulating levels (e.g., as a result of
overdose or acute renal failure) have been
associated with lactic acidosis. However, the
occurrence of this complication is now known
to be very rare, and metformin may be safely
used in patients with reduced estimated
glomerular filtration rates (eGFR);
Insulin in Type-2 DM
• Insulin has the advantage of being effective
where other agents are not and should be
considered as part of any combination regimen
when hyperglycemia is severe, especially if
catabolic features (weight loss,
hypertriglyceridemia, ketosis) are present.
• It is common practice to initiate insulin therapy
for patients who present with blood glucose
levels ≥300 mg/dL (16.7 mmol/L) or A1C >10%
(86 mmol/mol).
Combination Therapy
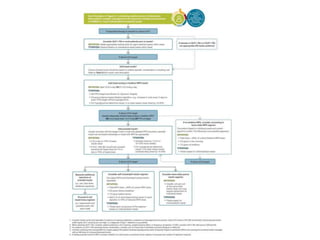
• If the A1C target is not achieved after
approximately 3 months, metformin can be
combined with any one of the preferred six
treatment options.
• 1. sulfonylurea, 2. thiazolidinedione, 3. DPP-
4 inhibitor, 4. SGLT2 inhibitor, 5. GLP-1 RA, or
• 6. Basal insulin;
• The choice of which agent to add is based on
drug-specific effects and patient factors
• For patients with established ASCVD or indicators of high
ASCVD risk (such as patients ≥55 years of age with
coronary, carotid, or lower-extremity artery stenosis >50%
or left ventricular hypertrophy), established kidney disease,
or heart failure, an SGLT-2 inhibitor or GLP-1 RA with
demonstrated CVD benefit is recommended as part of the
glucose-lowering regimen independent of A1C and in
consideration of patient-specific factors).
• For patients without established ASCVD, indicators of high
ASCVD risk, HF, or CKD, the choice of a second agent to add
to metformin is not yet guided by empiric evidence.
• Rather, drug choice is based on avoidance of side effects,
particularly hypoglycemia and weight gain, cost, and
patient preferences .
• Similar considerations are applied in patients who
require a third agent to achieve glycemic goals;
there is very little trial-based evidence to guide
this choice.
• In all cases, treatment regimens need to be
continuously reviewed for efficacy, side effects,
and patient burden.
• Common reasons for this include ineffectiveness,
intolerable side effects, expense, or a change in
glycemic goals.
• Although most patients prefer oral
medications to drugs that need to be injected,
the eventual need for the greater potency of
injectable medications is common, particularly
in people with a longer duration of diabetes.
• The addition of basal insulin, either human
NPH or one of the long-acting insulin analogs,
to oral agent regimens is a well-established
approach that is effective for many patients.
• Trial results support injectable GLP-1 RAs as
the preferred option for patients requiring the
potency of an injectable therapy for glucose
control.
• However, high costs and tolerability issues are
important barriers to the use of GLP-1 RAs.
Post Prandial
• Many individuals with type 2 diabetes require doses of insulin
before meals, in addition to basal insulin, to reach glycemic targets.
• A dose of 4 units or 10% of the amount of basal insulin at the
largest meal or the meal with the greatest postprandial excursion is
a safe estimate for initiating therapy.
• The prandial insulin regimen can then be intensified based on
patient needs.
• ( People with type 2 diabetes are generally more insulin resistant
than those with type 1 diabetes, require higher daily doses (∼1
unit/kg), and have lower rates of hypoglycemia).
• Titration can be based on home glucose monitoring or A1C.
• When initiating combination injectable therapy, metformin therapy
should be maintained while sulfonylureas and DPP-4 inhibitors are
typically discontinued.
use of a thiazolidinedione or an SGLT2
inhibitor
• In patients with suboptimal blood glucose
control, especially those requiring large insulin
doses, adjunctive use of a thiazolidinedione
or an SGLT2 inhibitor may help to improve
control and reduce the amount of insulin
needed.
• DPP-4i  (Dipeptidyl peptidase 4 inhibitor);
• GLP-1 RA, ( glucagon-like peptide 1 receptor
agonist);
• SGLT2i (sodium–glucose cotransporter 2
inhibitor);
• SLP
• TZD (Thiazolidinedione.)
• SU ( Sulfonylurea)
Conclusion
• The first line of treatment are lifestyle modifications and
metformin. If metformin alone cannot achieve a good
glycemic control or it is not tolerated or is contraindicated,
a second drug selected among the sulfonylureas,
thiazolinediones, incretin mimetics and incretin enhancer
drugs must be used. What is particularly relevant, anyway,
is to avoid therapeutic inertia, thus therapy should be
modified as soon as possible to keep glycemic control
HbA1c at about 7%.
• In this second step, various factors such risk of
hypoglycemia, comorbidities, age of patients, presence of
diabetic complications and cost of treatment must be
properly considered to individualize treatment.
Metformin
• Activation of Adenosine monophosphate
kinase.
• Inhibition of Gluconeogenesis.
• Improves Beta cell functions.
• Increase Insulin sensitivity
Thiazolidinedions
• Activation of PPPAR- Y
• Increase glucose transporter
• Expression ( GLUT 1 & GLUT 4)
• Decrease Gluconeogenesis
• Increase differentiation of Preadipocytes in
to adipocytes.
• DPP-4 inhibitors that have FDA
approval include sitagliptin, saxagliptin,
linagliptin, and alogliptin. Vildagliptin has
approval from the European Medicines
Agency (EMA), but not by the FDA.