CONGENITAL HEART
DISEASES
Mr. Pradeep Abothu, M.Sc (N), PhD Scholar
Associate Professor, Dept. of Child Health(N)
ASRAM College Of Nursing
CONTENT
• Review of blood circulation
• Fetal Circulation
• d/f between acyanotic & cyanotic heart
diseases
• Acyanotic diseases
1. Patent Ductus Arteriosus (PDA)
2. Atrial Septal Defect (ASD)
3. Ventricular Septal Defect (VSD)
4. Coarctation of the Aorta (CoA)
5. Aortic Stenosis
6. Pulmonary Stenosis
• Cyanotic diseases
1. Tetralogy of Fallot (TOF)
2. Transposition of the Great Arteries
(TGA)
3. Tricuspid Atresia
4. Total Anomalous Pulmonary Venous
Return (TAPVR)
5. Truncus Arteriosus
6. Hypoplastic Left Heart Syndrome
(HLHS).
• Nursing management
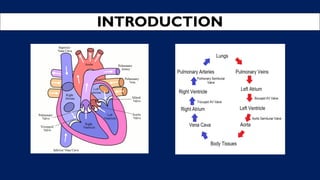
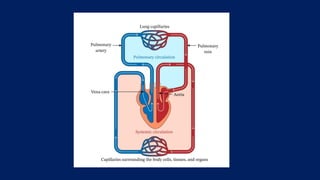
INTRODUCTION
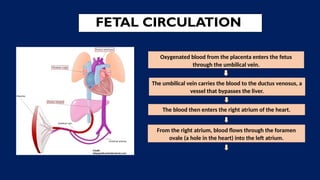
Oxygenated blood from the placenta enters the fetus
through the umbilical vein.
The umbilical vein carries the blood to the ductus venosus, a
vessel that bypasses the liver.
The blood then enters the right atrium of the heart.
From the right atrium, blood flows through the foramen
ovale (a hole in the heart) into the left atrium.
[
FETAL CIRCULATION
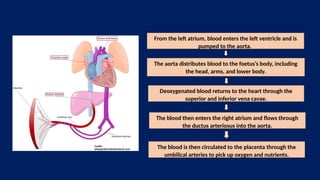
From the left atrium, blood enters the left ventricle and is
pumped to the aorta.
The aorta distributes blood to the foetus’s body, including
the head, arms, and lower body.
Deoxygenated blood returns to the heart through the
superior and inferior vena cavae.
The blood then enters the right atrium and flows through
the ductus arteriosus into the aorta.
The blood is then circulated to the placenta through the
umbilical arteries to pick up oxygen and nutrients.
DEFINITION
Congenital heart disease (CHD) refers to
structural abnormalities of the heart present at birth.
Some defects are simple and require no
treatment, while others may necessitate surgeries over
time.
INCIDENCE
• The global incidence of CHD is estimated to be about 8-10 per 1,000 live births.
• In India, about 2,00,000 children are born every year with CHD, resulting in a birth
prevalence of 8 per 1000 live births.
ETIOLOGY
• Chromosomal abnormalities (e.g., Down syndrome,Turner syndrome)
• Abnormal gene mutations.
• Maternal infections like rubella during pregnancy
• Maternal conditions such as diabetes, phenylketonuria
• Exposure to certain medications (e.g., lithium, isotretinoin)
• Alcohol consumption and smoking during pregnancy
• Higher risk if a sibling or parent has CHD.
• Deficiency in essential nutrients such as folic acid during pregnancy
TYPES OF CONGENITAL HEART DISEASE
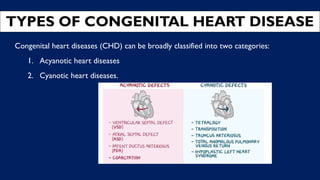
Congenital heart diseases (CHD) can be broadly classified into two categories:
1. Acyanotic heart diseases
2. Cyanotic heart diseases.
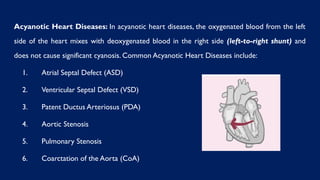
Acyanotic Heart Diseases: In acyanotic heart diseases, the oxygenated blood from the left
side of the heart mixes with deoxygenated blood in the right side (left-to-right shunt) and
does not cause significant cyanosis. Common Acyanotic Heart Diseases include:
1. Atrial Septal Defect (ASD)
2. Ventricular Septal Defect (VSD)
3. Patent Ductus Arteriosus (PDA)
4. Aortic Stenosis
5. Pulmonary Stenosis
6. Coarctation of the Aorta (CoA)
Cyanotic Heart Diseases: Cyanotic heart diseases are characterized by a right-to-left
shunt, which causes deoxygenated blood from the right side mixes with oxygenated blood
in the left side, leading to cyanosis. Common Cyanotic Heart Diseases include:
1. Tetralogy of Fallot (TOF)
2. Transposition of the Great Arteries (TGA)
3. Tricuspid Atresia
4. Total Anomalous PulmonaryVenous Return (TAPVR)
5. Truncus Arteriosus
6. Hypoplastic Left Heart Syndrome (HLHS).
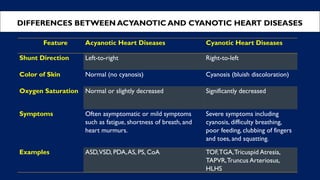
DIFFERENCES BETWEEN ACYANOTIC AND CYANOTIC HEART DISEASES
Feature Acyanotic Heart Diseases Cyanotic Heart Diseases
Shunt Direction Left-to-right Right-to-left
Color of Skin Normal (no cyanosis) Cyanosis (bluish discoloration)
Oxygen Saturation Normal or slightly decreased Significantly decreased
Symptoms Often asymptomatic or mild symptoms
such as fatigue, shortness of breath, and
heart murmurs.
Severe symptoms including
cyanosis, difficulty breathing,
poor feeding, clubbing of fingers
and toes, and squatting.
Examples ASD,VSD, PDA,AS, PS, CoA TOF,TGA,Tricuspid Atresia,
TAPVR,Truncus Arteriosus,
HLHS
ACYANOTIC
HEART
DISEASES
PATENT DUCTOUS
ARTERIOSUS
Mr. Pradeep Abothu, M.Sc (N), PhD Scholar
Associate Professor, Dept. of Child Health(N)
ASRAM College Of Nursing
DEFINITION
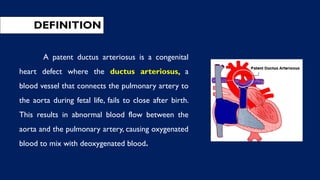
A patent ductus arteriosus is a congenital
heart defect where the ductus arteriosus, a
blood vessel that connects the pulmonary artery to
the aorta during fetal life, fails to close after birth.
This results in abnormal blood flow between the
aorta and the pulmonary artery, causing oxygenated
blood to mix with deoxygenated blood.
INCIDENCE
• PDA occurs in about 1 in 2,000 full-term live births.
• Significantly higher incidence in premature infants, especially before 28 weeks’
gestation (30-50%).
• More common in females, with a male-to-female ratio of 1:2.
PATHOPHYSIOLOGY
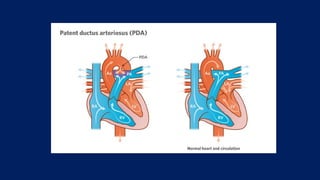
In patent ductus arteriosus (PDA), the ductus arteriosus
remains open after birth, allowing blood to flow abnormally
between the aorta and the pulmonary artery.
This creates a left-to-right shunt, increasing blood flow to the
lungs and placing extra workload on the left side of the heart.
Over time, this can lead to pulmonary congestion, heart
enlargement, and eventually heart failure.
CLINICAL FEATURES
• Small PDAs in term infants are asymptomatic. Large PDAs & pre term infants are
symptomatic. Symptoms include
• A continuous "machinery" murmur heard at the left upper sternal border.
• Respiratory Distress
• Poor Feeding
• Sweating
• Fatigue
• Tachycardia
• Bounding Pulses
• Cyanosis
DIAGNOSTICTOOLS
• Physical Examination: On auscultation a continuous, machinery-like
murmur over the left upper chest can be heard.
• Chest X-ray: Reveals an enlarged heart and evidence of increased
blood flow to the lungs.
• Electrocardiogram (ECG): Records the heart’s electrical activity,
detecting irregular rhythms and identifying an enlarged heart.
• Echocardiogram: Confirms the diagnosis by showing abnormal
blood flow and assessing the size of the heart.
MEDICAL MANAGEMENT
• Patent ductus arteriosus (PDA) can often be managed medically,
especially in premature infants. Nonsteroidal anti-inflammatory drugs
(NSAIDs) like indomethacin are commonly used to encourage the
closure of the ductus arteriosus.
• The typical dosage of indomethacin is 0.2 mg/kg initially, followed by two
additional doses of 0.1-0.25 mg/kg at 12 to 24-hour intervals, depending
on the infant's gestational age and response to the medication.
• Diuretics may be prescribed to manage symptoms of heart failure by
reducing fluid overload. Additionally, fluid restriction helps to prevent
fluid overload.
SURGICAL MANAGEMENT
• When medical management is insufficient, surgical options are considered.
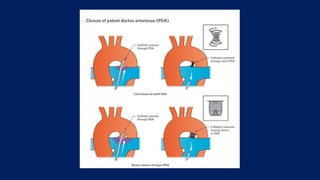
Percutaneous catheterization is a minimally invasive procedure where the ductus can
be closed using a spring coil introduced with a heart catheter.
• With some larger PDAs a ‘Device’ may be employed.
• If catheter-based methods are not feasible, surgical ligation through open surgery can
be performed. This procedure is often performed through a lateral thoracotomy,
where the ductus is either tied off with sutures or completely ligated and divided.
ATRIAL SEPTAL DEFECT
(ASD)
Mr. Pradeep Abothu, M.Sc (N), PhD Scholar
Associate Professor, Dept. of Child Health(N)
ASRAM College Of Nursing
DEFINITION
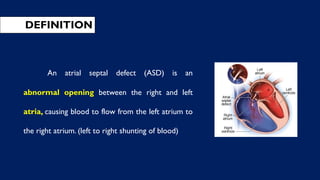
An atrial septal defect (ASD) is an
abnormal opening between the right and left
atria, causing blood to flow from the left atrium to
the right atrium. (left to right shunting of blood)
INCIDENCE
• Atrial septal defect (ASD) occurs in approximately 1 in 1,500 live births and
accounts for about 10% of all congenital heart diseases.
• It is more frequently diagnosed in females than in males, with a ratio of about 2:1.
TYPES OF ASD
Atrial septal defects can be classified into three types.
• Ostium Secundum ASD: The most common type,
accounting for about 70% of all ASD’s. It is located in the
middle of the atrial septum, within the region of the
fossa ovalis.
• Ostium Primum ASD: Accounts for about 15-20% of
ASD’s. It is located lower in the atrial septum, near the
atrioventricular valves.
• Sinus Venosus ASD: Represents about 5-10% of ASDs. It
is located near the entry of the superior vena cava or,
less commonly, the inferior vena cava.
PATHOPHYSIOLOGY
Presence of ASD
Blood flows from the left atrium to the right atrium
Increased Lung Blood Flow through pulmonary arteries
Right Heart Enlargement from extra blood flow.
Pulmonary Hypertension due to increased lung blood flow
Arrhythmias
[
Shortness of breath, fatigue, and heart failure.
CLINICAL FEATURES
• ASDs can range from small to large. Smaller defects may close on their own and are often
asymptomatic, with many children showing no symptoms and appearing healthy.
• Large or symptomatic ASDs may present the following symptoms:
Fatigue
Tachypnea
Shortness of breath
Poor growth
Arrhythmias
Frequent respiratory infections
DIAGNOSTICTOOLS
• Physical Examination to detect heart murmur suggesting ASD.
• Electrocardiogram (ECG) to reveal arrhythmias.
• Chest X-ray to show heart enlargement and increased lung blood
flow.
• Cardiac MRI/2D Echo to identify the location and size of ASD.
Management of atrial septal defects depends on the size of
the defect, the presence of symptoms, and the risk of
complications. Small ASDs are mostly asymptomatic and require no
intervention.
• Keep the heartbeat regular with medications like beta blockers
such as Lopressor and Inderal, and digoxin (Lanoxin).
• Anticoagulants, such as warfarin (Coumadin) and anti-platelet
agents like aspirin, are used to reduce the risk of blood clots
and strokes.
• Infection is controlled with antibiotics.
MEDICAL MANAGEMENT
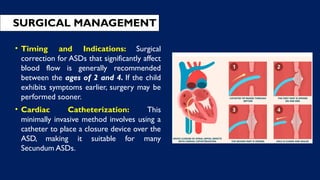
• Timing and Indications: Surgical
correction for ASDs that significantly affect
blood flow is generally recommended
between the ages of 2 and 4. If the child
exhibits symptoms earlier, surgery may be
performed sooner.
• Cardiac Catheterization: This
minimally invasive method involves using a
catheter to place a closure device over the
ASD, making it suitable for many
Secundum ASDs.
SURGICAL MANAGEMENT
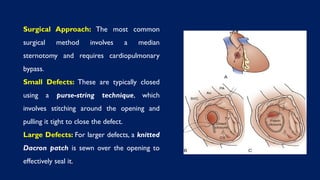
Surgical Approach: The most common
surgical method involves a median
sternotomy and requires cardiopulmonary
bypass.
Small Defects: These are typically closed
using a purse-string technique, which
involves stitching around the opening and
pulling it tight to close the defect.
Large Defects: For larger defects, a knitted
Dacron patch is sewn over the opening to
effectively seal it.
VENTRICULAR SEPTAL
DEFECT (ASD)
Mr. Pradeep Abothu, M.Sc (N), PhD Scholar
Associate Professor, Dept. of Child Health(N)
ASRAM College Of Nursing
DEFINITION
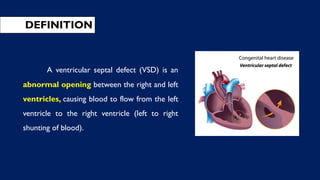
A ventricular septal defect (VSD) is an
abnormal opening between the right and left
ventricles, causing blood to flow from the left
ventricle to the right ventricle (left to right
shunting of blood).
INCIDENCE
• The incidence of ventricular septal defect (VSD) is approximately 1 in 500 live
births.
• VSD is one of the most common congenital heart defects, accounting for about 20-
30% of all congenital heart anomalies.
TYPES OFVSD
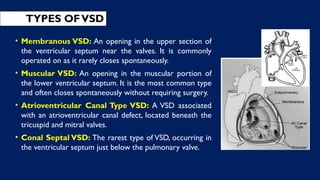
• Membranous VSD: An opening in the upper section of
the ventricular septum near the valves. It is commonly
operated on as it rarely closes spontaneously.
• Muscular VSD: An opening in the muscular portion of
the lower ventricular septum. It is the most common type
and often closes spontaneously without requiring surgery.
• Atrioventricular Canal Type VSD: A VSD associated
with an atrioventricular canal defect, located beneath the
tricuspid and mitral valves.
• Conal Septal VSD: The rarest type of VSD, occurring in
the ventricular septum just below the pulmonary valve.
PATHOPHYSIOLOGY
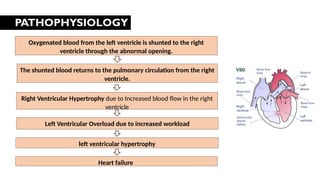
Oxygenated blood from the left ventricle is shunted to the right
ventricle through the abnormal opening.
The shunted blood returns to the pulmonary circulation from the right
ventricle.
Left Ventricular Overload due to increased workload
Right Ventricular Hypertrophy due to Increased blood flow in the right
ventricle
left ventricular hypertrophy
Heart failure
[
CLINICAL FEATURES
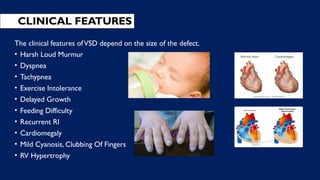
The clinical features ofVSD depend on the size of the defect.
• Harsh Loud Murmur
• Dyspnea
• Tachypnea
• Exercise Intolerance
• Delayed Growth
• Feeding Difficulty
• Recurrent RI
• Cardiomegaly
• Mild Cyanosis, Clubbing Of Fingers
• RV Hypertrophy
DIAGNOSTICTOOLS
• Physical Examination: Detects abnormal heart sounds (murmur),
at the lower left sternal border.
• Electrocardiogram (ECG): Normal in small VSDs; shows right
ventricular hypertrophy in moderate to largeVSDs.
• Echocardiogram: 2D Echo and color Doppler to determine the
size and location of theVSD and assess the degree of shunting.
• Chest X-ray: Shows enlarged heart and increased pulmonary
vascular markings in moderate to largeVSDs.
• Infants with Small VSDs do not require surgery and may close
before 1-2 years of age, but antibiotics are prescribed to
prevent endocarditis.
• Infants with moderate to Large VSDs who show symptoms of
congestive heart failure and poor growth are managed with a
combination of Digoxin and diuretics.
• Medical management also involves treating repeated respiratory
infections, anemia, and controlling congestive heart failure, along
with preventing infective endocarditis.
• If medical management fails and the infant continues to show
signs of congestive heart failure, early surgical repair is indicated.
MEDICAL MANAGEMENT
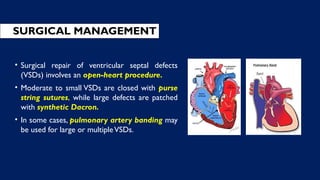
• Surgical repair of ventricular septal defects
(VSDs) involves an open-heart procedure.
• Moderate to small VSDs are closed with purse
string sutures, while large defects are patched
with synthetic Dacron.
• In some cases, pulmonary artery banding may
be used for large or multipleVSDs.
SURGICAL MANAGEMENT
COARCTATION OF
AORTA
Mr. Pradeep Abothu, M.Sc (N), PhD Scholar
Associate Professor, Dept. of Child Health(N)
ASRAM College Of Nursing
DEFINITION
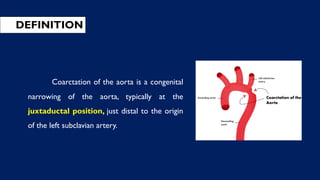
Coarctation of the aorta is a congenital
narrowing of the aorta, typically at the
juxtaductal position, just distal to the origin
of the left subclavian artery.
INCIDENCE
• The incidence of coarctation of the aorta is approximately 1 in 2,500 live births.
• It accounts for 5-8% of all congenital heart defects and is more common in males.
TYPES
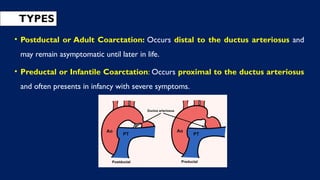
• Postductal or Adult Coarctation: Occurs distal to the ductus arteriosus and
may remain asymptomatic until later in life.
• Preductal or Infantile Coarctation: Occurs proximal to the ductus arteriosus
and often presents in infancy with severe symptoms.
PATHOPHYSIOLOGY
Coarctation of the aorta leads to a significant narrowing at the
juxtaductal position, causing increased resistance to blood flow.
This results in increased blood pressure in the upper body and
reduced pressure to the lower body.
Collateral circulation develops to bypass the constricted
area, but this can result in complications such as heart failure or
aortic rupture.
The heart compensates by increasing left ventricular workload,
leading to left ventricular hypertrophy.
[
CLINICAL FEATURES
The clinical presentation varies based on the severity of the coarctation and the
presence of other defects.
• Mild to Moderate Coarctation: Hypertension in the upper extremities, weak
or delayed pulses in the lower extremities, and a systolic murmur heard best over
the back.
• Severe Coarctation: Signs of congestive heart failure, including tachypnea, poor
feeding, and failure to thrive in infants; claudication, headache, and epistaxis in older
children.
DIAGNOSTICTOOLS
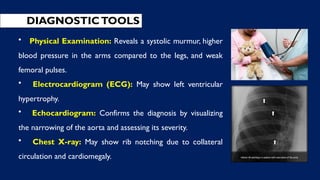
• Physical Examination: Reveals a systolic murmur, higher
blood pressure in the arms compared to the legs, and weak
femoral pulses.
• Electrocardiogram (ECG): May show left ventricular
hypertrophy.
• Echocardiogram: Confirms the diagnosis by visualizing
the narrowing of the aorta and assessing its severity.
• Chest X-ray: May show rib notching due to collateral
circulation and cardiomegaly.
• Infants with significant coarctation are initially managed with
prostaglandin E1 to keep the ductus arteriosus open,
improving blood flow.
• Antihypertensive medications such as beta-blockers or ACE
inhibitors may be used to manage hypertension in older children
and adults.
• Monitoring for complications such as heart failure or aortic
rupture is essential.
MEDICAL MANAGEMENT
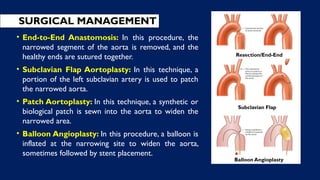
• End-to-End Anastomosis: In this procedure, the
narrowed segment of the aorta is removed, and the
healthy ends are sutured together.
• Subclavian Flap Aortoplasty: In this technique, a
portion of the left subclavian artery is used to patch
the narrowed aorta.
• Patch Aortoplasty: In this technique, a synthetic or
biological patch is sewn into the aorta to widen the
narrowed area.
• Balloon Angioplasty: In this procedure, a balloon is
inflated at the narrowing site to widen the aorta,
sometimes followed by stent placement.
SURGICAL MANAGEMENT
Resection/End-End
Subclavian Flap
Balloon Angioplasty
AORTIC STENOSIS
Mr. Pradeep Abothu, M.Sc (N), PhD Scholar
Associate Professor, Dept. of Child Health(N)
ASRAM College Of Nursing
DEFINITION
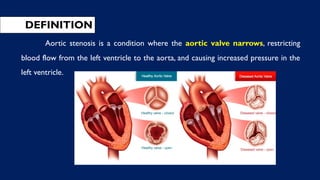
Aortic stenosis is a condition where the aortic valve narrows, restricting
blood flow from the left ventricle to the aorta, and causing increased pressure in the
left ventricle.
INCIDENCE
• Aortic stenosis in children is relatively rare, occurring in approximately 3-6 per
10,000 live births.
• It accounts for about 3-5% of all congenital heart defects, with a higher
prevalence in males compared to females.
TYPES OFVSD
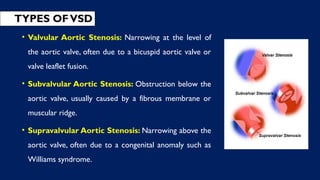
• Valvular Aortic Stenosis: Narrowing at the level of
the aortic valve, often due to a bicuspid aortic valve or
valve leaflet fusion.
• Subvalvular Aortic Stenosis: Obstruction below the
aortic valve, usually caused by a fibrous membrane or
muscular ridge.
• Supravalvular Aortic Stenosis: Narrowing above the
aortic valve, often due to a congenital anomaly such as
Williams syndrome.
PATHOPHYSIOLOGY
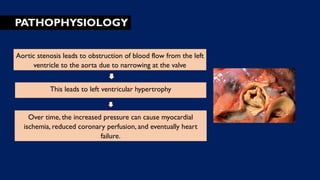
Aortic stenosis leads to obstruction of blood flow from the left
ventricle to the aorta due to narrowing at the valve
This leads to left ventricular hypertrophy
Over time, the increased pressure can cause myocardial
ischemia, reduced coronary perfusion, and eventually heart
failure.
CLINICAL FEATURES
• Decreased cardiac output
• Faint pulse
• Hypotension
• Tachycardia
• Chest pain
• Exercise intolerance
• Dizziness
• Ventricular dysfunction
DIAGNOSTICTOOLS
• Physical Examination: Presence of a systolic murmur,
often heard at the right upper sternal border.
• Electrocardiogram (ECG): May show left ventricular
hypertrophy.
• Echocardiogram: Essential for assessing valve area,
gradient, and left ventricular function.
• Chest X-ray: Shows left ventricular hypertrophy and post-
stenotic dilation of the ascending aorta.
• Symptomatic or Severe Aortic Stenosis:
Medical therapy includes beta-blockers, ACE
inhibitors, and diuretics to manage heart failure
symptoms, though these do not halt disease
progression.
MEDICAL MANAGEMENT
• Asymptomatic or Mild Aortic Stenosis: Regular monitoring, control of
hypertension, and prevention of endocarditis.
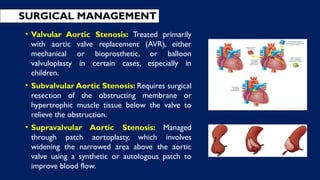
• Valvular Aortic Stenosis: Treated primarily
with aortic valve replacement (AVR), either
mechanical or bioprosthetic, or balloon
valvuloplasty in certain cases, especially in
children.
• Subvalvular Aortic Stenosis: Requires surgical
resection of the obstructing membrane or
hypertrophic muscle tissue below the valve to
relieve the obstruction.
• Supravalvular Aortic Stenosis: Managed
through patch aortoplasty, which involves
widening the narrowed area above the aortic
valve using a synthetic or autologous patch to
improve blood flow.
SURGICAL MANAGEMENT
PULMONARY
STENOSIS
Mr. Pradeep Abothu, M.Sc (N), PhD Scholar
Associate Professor, Dept. of Child Health(N)
ASRAM College Of Nursing
DEFINITION
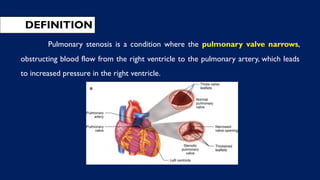
Pulmonary stenosis is a condition where the pulmonary valve narrows,
obstructing blood flow from the right ventricle to the pulmonary artery, which leads
to increased pressure in the right ventricle.
INCIDENCE
• Pulmonary stenosis in children is relatively common, occurring in approximately 8-
12 per 10,000 live births.
• It accounts for about 8-10% of all congenital heart defects, with a slightly higher
prevalence in males compared to females.
TYPES OFVSD
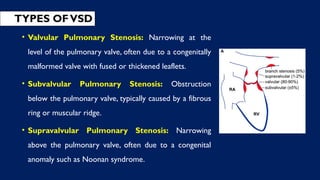
• Valvular Pulmonary Stenosis: Narrowing at the
level of the pulmonary valve, often due to a congenitally
malformed valve with fused or thickened leaflets.
• Subvalvular Pulmonary Stenosis: Obstruction
below the pulmonary valve, typically caused by a fibrous
ring or muscular ridge.
• Supravalvular Pulmonary Stenosis: Narrowing
above the pulmonary valve, often due to a congenital
anomaly such as Noonan syndrome.
PATHOPHYSIOLOGY
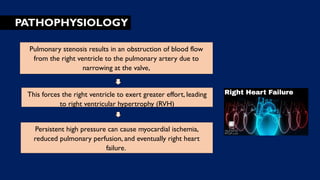
Pulmonary stenosis results in an obstruction of blood flow
from the right ventricle to the pulmonary artery due to
narrowing at the valve,
This forces the right ventricle to exert greater effort, leading
to right ventricular hypertrophy (RVH)
Persistent high pressure can cause myocardial ischemia,
reduced pulmonary perfusion, and eventually right heart
failure.
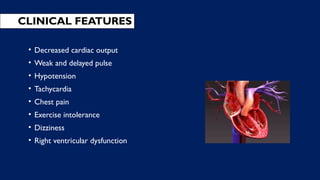
CLINICAL FEATURES
• Decreased cardiac output
• Weak and delayed pulse
• Hypotension
• Tachycardia
• Chest pain
• Exercise intolerance
• Dizziness
• Right ventricular dysfunction
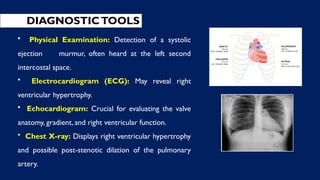
DIAGNOSTICTOOLS
• Physical Examination: Detection of a systolic
ejection murmur, often heard at the left second
intercostal space.
• Electrocardiogram (ECG): May reveal right
ventricular hypertrophy.
• Echocardiogram: Crucial for evaluating the valve
anatomy, gradient, and right ventricular function.
• Chest X-ray: Displays right ventricular hypertrophy
and possible post-stenotic dilation of the pulmonary
artery.
• Symptomatic or Severe Aortic Stenosis:
Medical therapy includes beta-blockers, diuretics
to manage symptoms, and Prostaglandin E1 to
maintain ductus arteriosus patency until the
obstruction is corrected.
MEDICAL MANAGEMENT
• Asymptomatic or Mild Aortic Stenosis: Regular monitoring, control of
hypertension, and prevention of endocarditis.
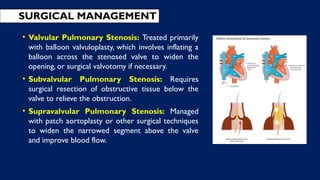
• Valvular Pulmonary Stenosis: Treated primarily
with balloon valvuloplasty, which involves inflating a
balloon across the stenosed valve to widen the
opening, or surgical valvotomy if necessary.
• Subvalvular Pulmonary Stenosis: Requires
surgical resection of obstructive tissue below the
valve to relieve the obstruction.
• Supravalvular Pulmonary Stenosis: Managed
with patch aortoplasty or other surgical techniques
to widen the narrowed segment above the valve
and improve blood flow.
SURGICAL MANAGEMENT
CYANOTIC
HEART
DISEASES
TETROLOGY OF
FALLOT
Mr. Pradeep Abothu, M.Sc (N), PhD Scholar
Associate Professor, Dept. of Child Health(N)
ASRAM College Of Nursing
DEFINITION
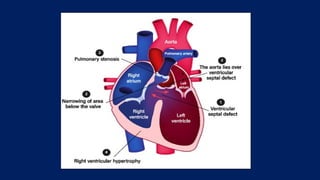
Tetralogy of Fallot is a congenital heart defect characterized by four
abnormalities that result in a right-to-left shunt and is considered a cyanotic heart disease.
The four defects are:
• Ventricular Septal Defect (VSD): Abnormal opening between the right and left
ventricles.
• Pulmonary Stenosis: Narrowing of the pulmonary valve, restricting blood flow from the
right ventricle to the lungs.
• Overriding Aorta: The aorta is positioned above the VSD, allowing deoxygenated blood
from both ventricles to enter the systemic circulation.
• Right Ventricular Hypertrophy: Thickening of the right ventricular muscle due to the
increased workload from pumping blood through the narrowed pulmonary valve.
INCIDENCE
• Tetralogy of Fallot is one of the common congenital heart defects, with an incidence
of approximately 1 in 2,000 to 3,000 live births.
• It accounts for about 7-10% of all congenital heart defects.
PATHOPHYSIOLOGY
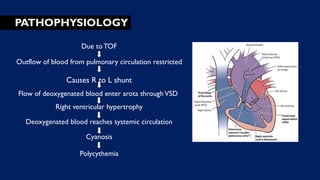
Due toTOF
Outflow of blood from pulmonary circulation restricted
Causes R to L shunt
Flow of deoxygenated blood enter arota throughVSD
Right ventricular hypertrophy
Deoxygenated blood reaches systemic circulation
Cyanosis
Polycythemia
CLINICAL FEATURES
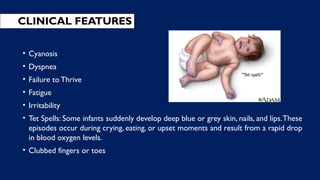
• Cyanosis
• Dyspnea
• Failure to Thrive
• Fatigue
• Irritability
• Tet Spells: Some infants suddenly develop deep blue or grey skin, nails, and lips.These
episodes occur during crying, eating, or upset moments and result from a rapid drop
in blood oxygen levels.
• Clubbed fingers or toes
DIAGNOSTICTOOLS
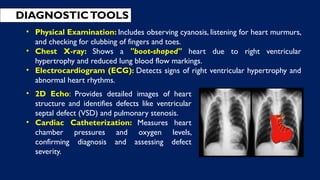
• 2D Echo: Provides detailed images of heart
structure and identifies defects like ventricular
septal defect (VSD) and pulmonary stenosis.
• Cardiac Catheterization: Measures heart
chamber pressures and oxygen levels,
confirming diagnosis and assessing defect
severity.
• Physical Examination: Includes observing cyanosis, listening for heart murmurs,
and checking for clubbing of fingers and toes.
• Chest X-ray: Shows a "boot-shaped" heart due to right ventricular
hypertrophy and reduced lung blood flow markings.
• Electrocardiogram (ECG): Detects signs of right ventricular hypertrophy and
abnormal heart rhythms.
MEDICAL MANAGEMENT
Medical management of Tetralogy of Fallot focuses on managing
symptoms and preparing the patient for surgical intervention:
• Prostaglandin E1 (PGE1) is administered to maintain ductal
patency in newborns with severe cyanosis until surgical repair.
• Beta-blockers and alpha-agonists are used to manage TET spells
by reducing the heart rate and systemic vascular resistance.
• Diuretics help in reducing fluid overload and managing congestive
heart failure symptoms.
Surgical intervention is the definitive treatment forTetralogy of Fallot and is usually
performed during infancy or early childhood, depending on the severity of symptoms and
the child's overall health:
a. Palliative Procedures:
• Palliative measures may be employed when the child is too young for complete repair.
• Palliative procedures, such as systemic-to-pulmonary artery shunt (e.g., Blalock-Taussig
shunt,Waterston shunt, Potts procedure, and Brock's procedure), may be performed to
temporarily improve oxygenation, especially in critically ill infants awaiting complete
repair.
SURGICAL MANAGEMENT
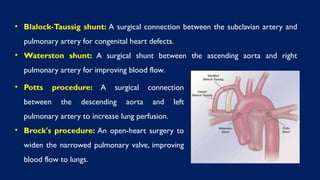
• Blalock-Taussig shunt: A surgical connection between the subclavian artery and
pulmonary artery for congenital heart defects.
• Waterston shunt: A surgical shunt between the ascending aorta and right
pulmonary artery for improving blood flow.
• Potts procedure: A surgical connection
between the descending aorta and left
pulmonary artery to increase lung perfusion.
• Brock's procedure: An open-heart surgery to
widen the narrowed pulmonary valve, improving
blood flow to lungs.
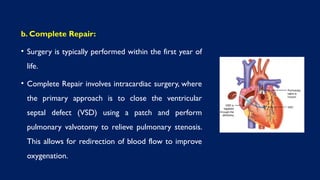
b. Complete Repair:
• Surgery is typically performed within the first year of
life.
• Complete Repair involves intracardiac surgery, where
the primary approach is to close the ventricular
septal defect (VSD) using a patch and perform
pulmonary valvotomy to relieve pulmonary stenosis.
This allows for redirection of blood flow to improve
oxygenation.
TRANSPOSITION OF
THE GREAT ARTERIES
(TGA)
Mr. Pradeep Abothu, M.Sc (N), PhD Scholar
Associate Professor, Dept. of Child Health(N)
ASRAM College Of Nursing
DEFINITION
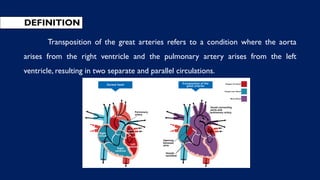
Transposition of the great arteries refers to a condition where the aorta
arises from the right ventricle and the pulmonary artery arises from the left
ventricle, resulting in two separate and parallel circulations.
INCIDENCE
• It affects approximately 1 in every 3,500 live births.
• Transposition of the great arteries accounts for approximately 5-7% of all congenital
heart defects.
PATHOPHYSIOLOGY
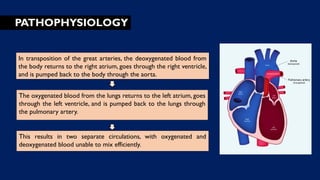
In transposition of the great arteries, the deoxygenated blood from
the body returns to the right atrium, goes through the right ventricle,
and is pumped back to the body through the aorta.
The oxygenated blood from the lungs returns to the left atrium, goes
through the left ventricle, and is pumped back to the lungs through
the pulmonary artery.
This results in two separate circulations, with oxygenated and
deoxygenated blood unable to mix efficiently.
CLINICAL FEATURES
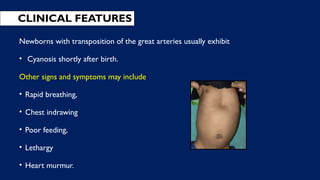
Newborns with transposition of the great arteries usually exhibit
• Cyanosis shortly after birth.
Other signs and symptoms may include
• Rapid breathing,
• Chest indrawing
• Poor feeding,
• Lethargy
• Heart murmur.
DIAGNOSTICTOOLS
Diagnostic evaluation of transposition of the great arteries includes:
Echocardiography: This is the primary tool for diagnosing TGA. It uses sound
waves to create images of the heart, allowing visualization of the abnormal
positioning of the great arteries.
Electrocardiogram (ECG): An ECG records the electrical activity of the heart
and can help identify any abnormalities in the heart’s rhythm and conduction.
Chest X-ray: A chest X-ray may show an enlarged heart and abnormal positioning
of the cardiac structures.
MEDICAL MANAGEMENT
Medical management of transposition of the great arteries
focuses on stabilizing the baby’s condition until surgical
intervention can be performed.This may include:
Prostaglandin infusion: Prostaglandin E1 is administered to keep
the ductus arteriosus open, which allows for mixing of oxygenated
and deoxygenated blood.
Oxygen therapy: Supplemental oxygen is provided to alleviate
cyanosis and improve oxygen saturation.
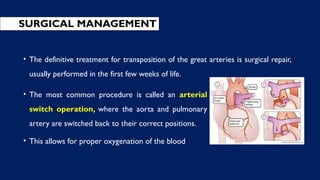
• The most common procedure is called an arterial
switch operation, where the aorta and pulmonary
artery are switched back to their correct positions.
• This allows for proper oxygenation of the blood
SURGICAL MANAGEMENT
• The definitive treatment for transposition of the great arteries is surgical repair,
usually performed in the first few weeks of life.
OTHER CONGENITAL HEART DISEASES
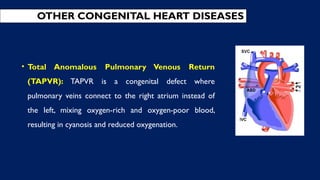
• Total Anomalous Pulmonary Venous Return
(TAPVR): TAPVR is a congenital defect where
pulmonary veins connect to the right atrium instead of
the left, mixing oxygen-rich and oxygen-poor blood,
resulting in cyanosis and reduced oxygenation.
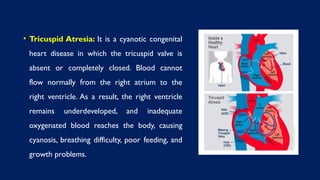
• Tricuspid Atresia: It is a cyanotic congenital
heart disease in which the tricuspid valve is
absent or completely closed. Blood cannot
flow normally from the right atrium to the
right ventricle. As a result, the right ventricle
remains underdeveloped, and inadequate
oxygenated blood reaches the body, causing
cyanosis, breathing difficulty, poor feeding, and
growth problems.
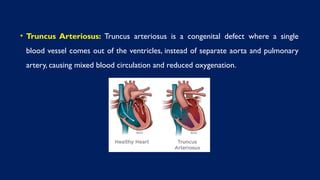
• Truncus Arteriosus: Truncus arteriosus is a congenital defect where a single
blood vessel comes out of the ventricles, instead of separate aorta and pulmonary
artery, causing mixed blood circulation and reduced oxygenation.
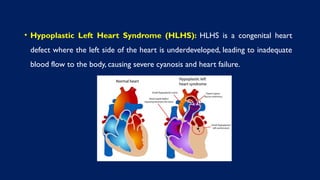
• Hypoplastic Left Heart Syndrome (HLHS): HLHS is a congenital heart
defect where the left side of the heart is underdeveloped, leading to inadequate
blood flow to the body, causing severe cyanosis and heart failure.
NURSING
MANAGEMENT OF
CONGENITAL HEART
DISEASES
PRE OPERATIVE NURSING MANAGEMENT
Nursing Assessment:
• Gather a comprehensive history from the parents.
• Conduct a thorough head-to-toe physical assessment, focusing on vital signs and
oxygen saturation levels.
• Assess the skin color for pink or cyanotic tones, and check peripheral pulses, the
presence of edema, and the color and temperature of extremities.
• Look for clubbing in the fingers or toes, and evaluate heart sounds for rate, rhythm,
and any murmurs.
• Observe for signs of respiratory distress and assess the
child's activity tolerance and energy levels.
• Additionally, consider the child's growth and developmental
milestones.
Respiratory Management:
• Position the child in a semi-upright position to ease breathing.
• Suction oral and nasal secretions if necessary.
• Continuously monitor oxygen saturation and provide supplemental oxygen as
needed.
• Perform arterial blood gas analysis when indicated.
Medication Administration:
• Administer prescribed medications, including diuretics and bronchodilators.
• Organize the medication schedule to allow for uninterrupted rest periods.
• Check blood pressure before administering medications such as Digoxin and
diuretics, do not administer if pressures are low.
Provide Rest & Comfort:
• Ensure the child has uninterrupted periods of rest and sleep.
• Advise parents to help with daily activities to conserve the child's energy.
• Provide bed rest and avoid strenuous activities.
Nutritional Support:
• Offer small, frequent feedings.
• Administer a high-calorie formula if needed.
• Monitor daily weight to ensure the child is receiving adequate nutrition.
• Keep an intake and output chart.
• Consider nasogastric feeding if the child struggles with oral feeds or shows signs
of cyanosis while feeding.