Neuromuscular Junction
Dr Faiza
MBBS (Best Graduate, AIMC Lahore)
FCPS Physiology,
MHPE (Riphah Int University, Islamabad)
ICMT, CHPE, DHPE (STMU)
MPH (GC University, Faisalabad)
MBA (Virtual University of Pakistan)
Neuromuscular Junction
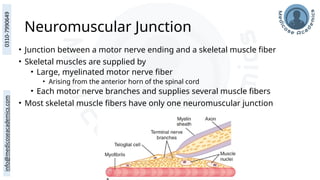
• Junction between a motor nerve ending and a skeletal muscle fiber
• Skeletal muscles are supplied by
• Large, myelinated motor nerve fiber
• Arising from the anterior horn of the spinal cord
• Each motor nerve branches and supplies several muscle fibers
• Most skeletal muscle fibers have only one neuromuscular junction
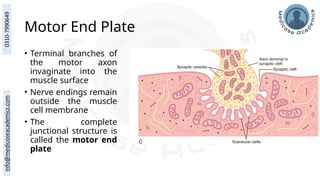
Motor End Plate
• Terminal branches of
the motor axon
invaginate into the
muscle surface
• Nerve endings remain
outside the muscle
cell membrane
• The complete
junctional structure is
called the motor end
plate
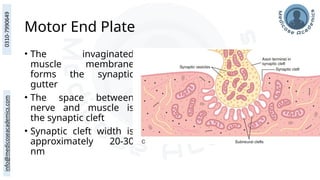
Motor End Plate
• The invaginated
muscle membrane
forms the synaptic
gutter
• The space between
nerve and muscle is
the synaptic cleft
• Synaptic cleft width is
approximately 20-30
nm
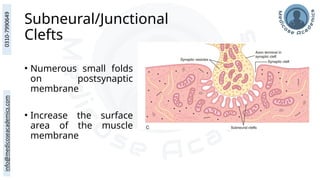
Subneural/Junctional
Clefts
• Numerous small folds
on postsynaptic
membrane
• Increase the surface
area of the muscle
membrane
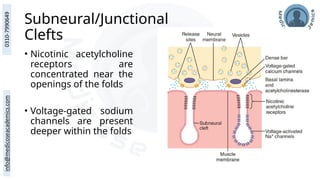
Subneural/Junctional
Clefts
• Nicotinic acetylcholine
receptors are
concentrated near the
openings of the folds
• Voltage-gated sodium
channels are present
deeper within the folds
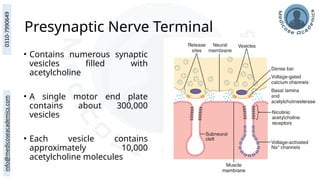
Presynaptic Nerve Terminal
• Contains numerous synaptic
vesicles filled with
acetylcholine
• A single motor end plate
contains about 300,000
vesicles
• Each vesicle contains
approximately 10,000
acetylcholine molecules
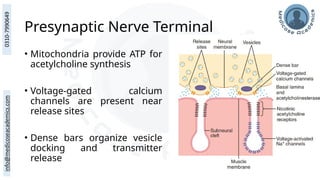
Presynaptic Nerve Terminal
• Mitochondria provide ATP for
acetylcholine synthesis
• Voltage-gated calcium
channels are present near
release sites
• Dense bars organize vesicle
docking and transmitter
release
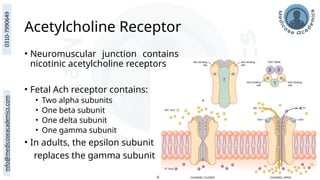
Acetylcholine Receptor
• Neuromuscular junction contains
nicotinic acetylcholine receptors
• Fetal Ach receptor contains:
• Two alpha subunits
• One beta subunit
• One delta subunit
• One gamma subunit
• In adults, the epsilon subunit
replaces the gamma subunit
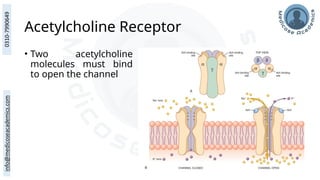
Acetylcholine Receptor
• Two acetylcholine
molecules must bind
to open the channel
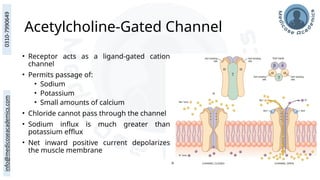
Acetylcholine-Gated Channel
• Receptor acts as a ligand-gated cation
channel
• Permits passage of:
• Sodium
• Potassium
• Small amounts of calcium
• Chloride cannot pass through the channel
• Sodium influx is much greater than
potassium efflux
• Net inward positive current depolarizes
the muscle membrane
End Plate Potential
• May increase membrane voltage by 50-75 mV
• It is a graded local potential
• It is not an all-or-none response
Acetylcholine
opens
nicotinic
receptor
channels
Sodium
enters the
muscle fiber
Local
depolarizatio
n develops at
the motor
end plate
Local
depolarizatio
n = end plate
potential
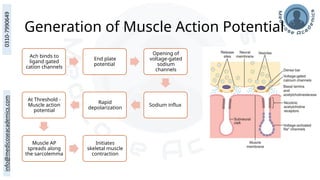
Generation of Muscle Action Potential
Ach binds to
ligand gated
cation channels
End plate
potential
Opening of
voltage-gated
sodium
channels
Sodium influx
Rapid
depolarization
At Threshold -
Muscle action
potential
Muscle AP
spreads along
the sarcolemma
Initiates
skeletal muscle
contraction
14
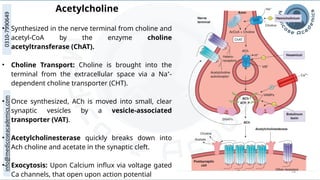
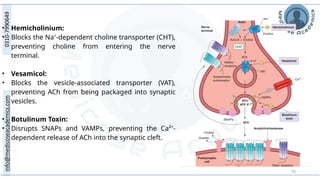
Acetylcholine
• Synthesized in the nerve terminal from choline and
acetyl-CoA by the enzyme choline
acetyltransferase (ChAT).
• Choline Transport: Choline is brought into the
terminal from the extracellular space via a Na⁺-
dependent choline transporter (CHT).
• Once synthesized, ACh is moved into small, clear
synaptic vesicles by a vesicle-associated
transporter (VAT).
• Acetylcholinesterase quickly breaks down into
Ach choline and acetate in the synaptic cleft.
• Exocytosis: Upon Calcium influx via voltage gated
Ca channels, that open upon action potential
15
• Hemicholinium:
• Blocks the Na⁺-dependent choline transporter (CHT),
preventing choline from entering the nerve
terminal.
• Vesamicol:
• Blocks the vesicle-associated transporter (VAT),
preventing ACh from being packaged into synaptic
vesicles.
• Botulinum Toxin:
• Disrupts SNAPs and VAMPs, preventing the Ca²⁺-
dependent release of ACh into the synaptic cleft.
16
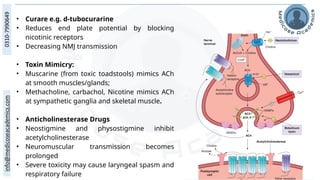
• Curare e.g. d-tubocurarine
• Reduces end plate potential by blocking
nicotinic receptors
• Decreasing NMJ transmission
• Toxin Mimicry:
• Muscarine (from toxic toadstools) mimics ACh
at smooth muscles/glands;
• Methacholine, carbachol, Nicotine mimics ACh
at sympathetic ganglia and skeletal muscle.
• Anticholinesterase Drugs
• Neostigmine and physostigmine inhibit
acetylcholinesterase
• Neuromuscular transmission becomes
prolonged
• Severe toxicity may cause laryngeal spasm and
respiratory failure
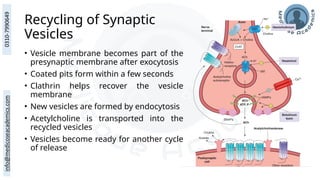
Recycling of Synaptic
Vesicles
• Vesicle membrane becomes part of the
presynaptic membrane after exocytosis
• Coated pits form within a few seconds
• Clathrin helps recover the vesicle
membrane
• New vesicles are formed by endocytosis
• Acetylcholine is transported into the
recycled vesicles
• Vesicles become ready for another cycle
of release
Safety Factor at the Neuromuscular
Junction
• A normal nerve impulse produces an end plate potential
much greater than threshold (3x stronger)
Fatigue of the Neuromuscular Junction
• Very rapid stimulation (100 impulses per second) can reduce
the number of available acetylcholine vesicles
• End plate potential may fall below threshold
• Some nerve impulses may fail to generate muscle action
potentials
• Junctional fatigue occurs mainly during extreme muscle
activity
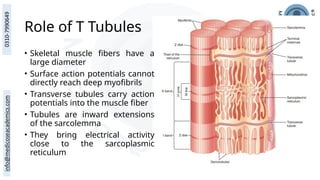
Role of T Tubules
• Skeletal muscle fibers have a
large diameter
• Surface action potentials cannot
directly reach deep myofibrils
• Transverse tubules carry action
potentials into the muscle fiber
• Tubules are inward extensions
of the sarcolemma
• They bring electrical activity
close to the sarcoplasmic
reticulum
Transmission Across Neuromuscular
Junction
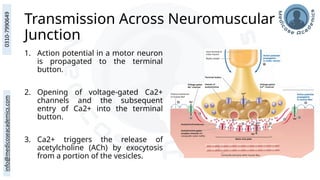
1. Action potential in a motor neuron
is propagated to the terminal
button.
2. Opening of voltage-gated Ca2+
channels and the subsequent
entry of Ca2+ into the terminal
button.
3. Ca2+ triggers the release of
acetylcholine (ACh) by exocytosis
from a portion of the vesicles.
Transmission Across Neuromuscular
Junction
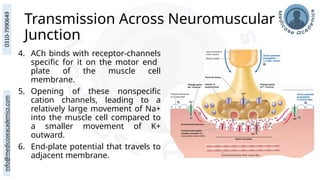
4. ACh binds with receptor-channels
specific for it on the motor end
plate of the muscle cell
membrane.
5. Opening of these nonspecific
cation channels, leading to a
relatively large movement of Na+
into the muscle cell compared to
a smaller movement of K+
outward.
6. End-plate potential that travels to
adjacent membrane.
Transmission Across Neuromuscular
Junction
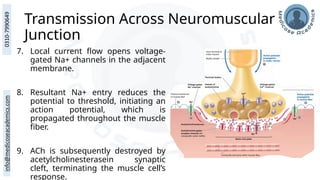
7. Local current flow opens voltage-
gated Na+ channels in the adjacent
membrane.
8. Resultant Na+ entry reduces the
potential to threshold, initiating an
action potential, which is
propagated throughout the muscle
fiber.
9. ACh is subsequently destroyed by
acetylcholinesterasein synaptic
cleft, terminating the muscle cell’s
response.
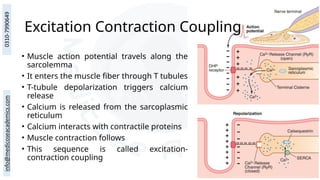
• Muscle action potential travels along the
sarcolemma
• It enters the muscle fiber through T tubules
• T-tubule depolarization triggers calcium
release
• Calcium is released from the sarcoplasmic
reticulum
• Calcium interacts with contractile proteins
• Muscle contraction follows
• This sequence is called excitation-
contraction coupling
Excitation Contraction Coupling
Clinical Case Scenario – Myasthenia
Gravis
• A 28-year-old woman presents with complaints of drooping
eyelids and double vision that worsen as the day progresses.
She also reports difficulty chewing and speaking, especially
after prolonged conversations. Her symptoms improve after
rest. On examination, she has bilateral ptosis, mild facial
muscle weakness, and normal deep tendon reflexes.
Muscle strength declines with repetitive movements.
• There is no sensory deficit. A Tensilon test produces a brief
improvement in muscle strength. Blood tests reveal anti-
acetylcholine receptor antibodies. A chest CT shows an
enlarged thymus.
Questions:
• What is the most likely diagnosis?
• What is the underlying pathophysiology?
• What pharmacological and surgical treatments are
appropriate?
• What other autoimmune diseases should be screened for in
this patient?
Myasthenia Gravis
• Chronic autoimmune disease causing skeletal muscle
weakness
• Affects 25–125 per million, bimodal peak:
• Women in 20s, men in 60s
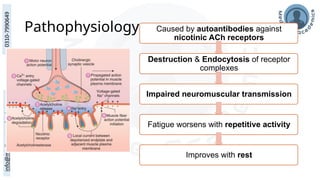
Pathophysiology Caused by autoantibodies against
nicotinic ACh receptors
Destruction & Endocytosis of receptor
complexes
Impaired neuromuscular transmission
Fatigue worsens with repetitive activity
Improves with rest
Myasthenia Gravis
Clinical Types
1.Ocular MG – extraocular
muscle weakness
2.Generalized MG –
widespread skeletal muscle
weakness
•In severe cases →
diaphragm weakness →
respiratory failure
Diagnosis
Eelectromyography:
•Shows decremental response with repetitive
stimulation
•Detection of anti-AChR antibodies
•Tensilon (edrophonium) test may show
temporary improvement
Histology
• Flattened, widened, or absent synaptic
clefts
• 70–90% loss of ACh receptors at endplate
Associated Conditions
•Increased risk of autoimmune diseases:
• SLE, RA, polymyositis
•~30% have a family history of autoimmune disorders
•Often associated with thymic hyperplasia or thymoma
(10–15%)
Treatment
• Acetylcholinesterase inhibitors
• e.g., neostigmine, pyridostigmine
• Immunosuppressants:
• Prednisone, azathioprine, cyclosporine
• Thymectomy:
• Indicated if thymoma present
• Also beneficial in non-thymoma cases (remission in ~35%)
• Plasmapheresis or IVIG in crisis situations
Lambert-Eaton Myasthenic Syndrome
(LEMS)
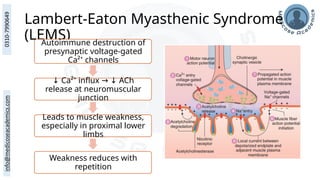
Autoimmune destruction of
presynaptic voltage-gated
Ca²⁺ channels
↓ Ca²⁺ influx ACh
→ ↓
release at neuromuscular
junction
Leads to muscle weakness,
especially in proximal lower
limbs
Weakness reduces with
repetition
Lambert-Eaton Myasthenic Syndrome
Adult-onset, equal in males and females
• Weakness improves with repetitive
stimulation
• Common symptoms:
• Waddling gait
• Difficulty rising or lifting arms
• No significant ocular involvement (unlike MG)
Associated Conditions
• 40% linked to small cell lung cancer (SCLC)
• Also associated with other malignancies
• Can mimic effects of aminoglycoside toxicity
Treatment
• Treat underlying cancer if present
• Immunotherapy:
• Prednisone, IVIG, Pplasmapheresis
• Aminopyridines:
• Enhance ACh release by blocking K⁺ channels
• AChE inhibitors:
• Less effective than in MG
Dr Faiza, FCPS Physiology
Thank You
References:
• Guyton, A. C., & Hall, J. E. (2021). Textbook of Medical Physiology (15th ed., Chapter 7:
Excitation of Skeletal Muscle: Neuromuscular Transmission and Excitation Contraction
Coupling ). Philadelphia, PA: Elsevier.
• Barrett, K. E., Barman, S. M., Brooks, H. L., & Yuan, J. X.-J. (2019). Ganong’s Review of Medical
Physiology (26th ed., Chapter 5: Excitable Tissue: Muscle). New York, NY: McGraw-Hill
Education.
• Sherwood, L. (2015). Human Physiology: From Cells to Systems (9th ed., Chapter 7: Excitable
Tissue:Muscle). Boston, MA: Cengage Learning.