Neo Innovation of Diabetic Foot Management, Vascular Surgery Experiments
Explores diabetic foot complications, vascular surgery treatment through revascularization approaches, and multidisciplinary management strategies including AI and wound therapy for improved patient outcomes.
Neo Innovation of Diabetic Foot Management, Vascular Surgery Experiments
1.
Neo Innovation
of DiabeticFoot
Management,
Vascular Surgery
Experiments
KHALID RAJHI MD FACS
Consultant of Vascular & Endovascular Surgery
Lead of Vascular Surgery, Jazan Health Cluster, Saudi
Arabia
Diabetes
• Noncommunicable diseasesthreaten population health in many countries
• Diabetes mellitus is of growing concern because of its prevalence and association with
adverse health outcomes
• Its complications pose a serious threat to human health and have become a global public
health issue
• Diabetic foot, affect 15% of all diabetic globally, 15– 20% may require amputation
• DFU account for up to 24% mortality in patients with DM
4.
• 17.7 %the prevalence of DM is
around 18% among beneficiaries in a
public health care system
‑ 1
• Over 90% of patients with diabetes
have type 2 DM (T2DM) 2
1- Alghnam, et al. Int J Environ Res Public Health; 2021
World Health Survey of Saudi Arabia; 2019
2- Jia, W. et al. Diabetes Metab. Res.(2019)
5.
WHO Definition •Diabetic foot Infection, ulceration or destruction tissues and
bones with associated neuropathy and occlusive arterial disease
in a patient with DM
6.
• Ogbera &Fasanmade et al (2015), reported
- 41.5% of DM patients have foot at risk
- Type II diabetes account for 98.1%
- Mean duration before development of DF is 10.8yrs
• Pathogenesis
- Peripheral Neuropathy 80 – 90% (Sensory - Motor - Autonomic)
- Peripheral vascular disease 30-40%
- Neuroischemic disease
7.
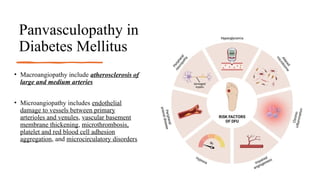
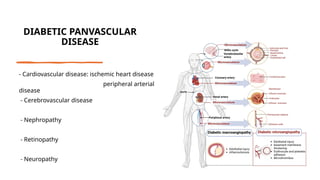
Panvasculopathy in
Diabetes Mellitus
•Macroangiopathy include atherosclerosis of
large and medium arteries
• Microangiopathy includes endothelial
damage to vessels between primary
arterioles and venules, vascular basement
membrane thickening, microthrombosis,
platelet and red blood cell adhesion
aggregation, and microcirculatory disorders
Diabetic Peripheral Vasculopathy
•One of the most important and common vascular complications in patients with T2DM.
• In such patients, DPVD increases the risk of major adverse limb events such as amputation.
• DPVD can manifest as diabetic foot syndrome and peripheral arterial disease (PAD), which
seriously affect the quality of life of patients with diabetes.
• Peripheral arterial disease is traditionally considered to be dominated by large artery
atherosclerosis.
• In fact, PAD is often accompanied by local and systemic microangiopathy.
• Multivessel endothelial dysfunction can manifest as microangiopathy (either exclusively or with
other diseases), such as capillary basement membrane thickening, endothelial hyperplasia, oxygen
tension reduction, and hypoxia, affecting peripheral nerve function.
• Pre-DM can affect blood vessels and accompanying nerves.
• The chronic course of DM might have further adverse effects under poor glycemic control.
• An increase in postprandial glucose plays an important role in the development of peripheral
vascular disease in DM.
Diabetes mellitus shouldhave an annual foot evaluation using the
Semmes-Weinstein monofilament test to assess for peripheral neuropathy
Diabetic foot ranges from foot at risk to frank gangrene
12.
” by Vuorlaaksoet al.
(2023)
Retrospective cohort
study of long-term
outcomes and prognostic
factors for survival after
lower extremity
amputation in patients
with diabetes.
a relationship between
frailty (especially
advanced age), CKD and
other multimorbidities
such as PAD
13.
• Following amputation,mortality ranges:
- from 13 to 40% in one year,
35 to 65% in three years,
39 to 80% in five years
14.
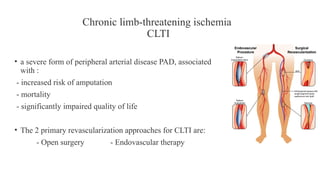
Chronic limb-threatening ischemia
CLTI
•a severe form of peripheral arterial disease PAD, associated
with :
- increased risk of amputation
- mortality
- significantly impaired quality of life
• The 2 primary revascularization approaches for CLTI are:
- Open surgery - Endovascular therapy
15.
Recent Trials ofRevascularization
• Best Endovascular versus best Surgical Therapy in patients with CLI (BEST-CLI)
• Bypass versus Angioplasty for Severe Ischemia of the Leg (BASIL-2)
• Regardless of the chosen strategy, early referral of patients with diabetes and
CLTI to a specialist team within a multidisciplinary environment is crucial.
16.
• Their findings,highlight the need for an individualized revascularization
strategy which accounts for underlying comorbidities, risk factors, disease
severity, availability of suitable bypass conduits, surgical risks, and timely
access to procedures
18.
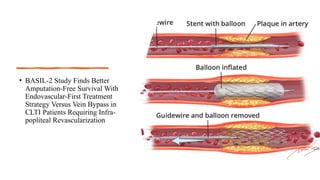
• BASIL-2 StudyFinds Better
Amputation-Free Survival With
Endovascular-First Treatment
Strategy Versus Vein Bypass in
CLTI Patients Requiring Infra-
popliteal Revascularization
Comprehensive care should
encompassessential elements
- smoking cessation
- glycemic control
- adequate debridement
- infection control
- offloading
- patient education