Neglected Causes of Infertility
A Comprehensive Evidence-Based
Review (2026) Infertility
Dr Muhammad M Al Hennawy
Senior Consultant of Obestetrics , gynecology, and Infertility
https://mmhennawy.github.io
https://www.youtube.com/c/mmhennawy
https://www.slideshare.net/muhammadelhennawy5
Neglected Causes of Infertility
• A Comprehensive Evidence-Based Review (2026) Infertility
is traditionally attributed to ovulatory disorders, tubal disease, male factor
infertility, endometriosis, and diminished ovarian reserve.
• However, 10–30% of couples have
overlooked or
under-recognized factors
that contribute to delayed conception.
• Identifying these neglected causes
• By a more comprehensive, individualized evaluation
improve pregnancy rates
while avoiding unnecessary assisted reproductive technologies.
While common fertility discussions focus
• on age, blocked fallopian tubes, and sperm counts,
• several neglected and overlooked medical conditions
significantly impair reproductive health.
• These hidden causes often fall outside routine screening
panels, delaying accurate diagnosis and treatment.
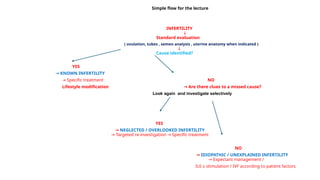
Simple flow for the lecture
INFERTILITY
↓
Standard evaluation
( ovulation, tubes , semen analysis , uterine anatomy when indicated )
↓
Cause identified?
YES
→ KNOWN INFERTILITY
→ Specific treatment NO
Lifestyle modification Are there clues to a missed cause?
→
Look again and investigate selectively
YES
→ NEGLECTED / OVERLOOKED INFERTILITY
Targeted re-investigation Specific treatment
→ →
NO
→ IDIOPATHIC / UNEXPLAINED INFERTILITY
Expectant management /
→
IUI ± stimulation / IVF according to patient factors
Classification of Infertility
Type Definition Examples Main approach
Known / Identified Infertility
A specific cause has been
identified after appropriate
evaluation
Ovulatory dysfunction, tubal
occlusion, hydrosalpinx,
severe male factor,
endometriosis, uterine cavity
lesions
Treat the identified cause
Neglected / Overlooked
Infertility
A potentially relevant cause
exists but was missed,
overlooked, or not
adequately investigated
Chronic endometritis,
adenomyosis, subtle
endometriosis, intrauterine
adhesions, small cavity
lesions, sexual dysfunction,
selected genital infections
Re-evaluate targeted
→
investigation specific
→
treatment
Idiopathic / Unexplained
Infertility
No cause is identified after an
appropriate standard
infertility evaluation
Normal ovulation, adequate
ovarian reserve for age, patent
tubes, normal uterine
assessment, and no significant
male factor
Expectant management / IUI
± stimulation / IVF according
to age, duration and
prognosis
The key difference
Known infertility
Cause found → Treat the cause
Neglected infertility
Cause may be present → It was missed → Look again and
investigate selectively
Idiopathic / Unexplained infertility
Appropriate evaluation completed → No cause found
Very important distinction
Neglected ≠ Idiopathic
A patient should not be labeled "unexplained infertility" simply
because
the basic work-up is normal if there are clinical clues suggesting
an overlooked condition.
Schistosomiasis (Bilharzia)
•This neglected tropical disease causes structural damage.
•Eggs deposited
•by the parasite induce chronic inflammation, granulomas, and fibrosis
•, leading to physical blockages
• in both male and female reproductive tracts.
• It also disrupts the hypothalamic-pituitary-gonadal (HPG) axis by releasing estrogen-like metabolites
Genital Tuberculosis (TB)
• Often asymptomatic in its early stages,
• pelvic and endometrial tuberculosis causes severe tubal
damage, pelvic adhesions, and
• endometrial scarring (Asherman’s syndrome), destroying
the lining where an embryo would implant.
Unrecognized Asherman Syndrome
• Occurs after: Curettage ,Postpartum infection ,
Postpartum hemorrhage
• Diagnosis: Hysteroscopy
• Treatment: Hysteroscopic adhesiolysis
Chronic Pelvic Inflammatory Disease Without Tubal
Occlusion
• Tubes may remain patent despite chronic inflammation
affecting fertility.
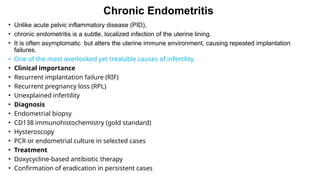
Chronic Endometritis
• Unlike acute pelvic inflammatory disease (PID),
• chronic endometritis is a subtle, localized infection of the uterine lining.
• It is often asymptomatic but alters the uterine immune environment, causing repeated implantation
failures.
• One of the most overlooked yet treatable causes of infertility.
• Clinical importance
• Recurrent implantation failure (RIF)
• Recurrent pregnancy loss (RPL)
• Unexplained infertility
• Diagnosis
• Endometrial biopsy
• CD138 immunohistochemistry (gold standard)
• Hysteroscopy
• PCR or endometrial culture in selected cases
• Treatment
• Doxycycline-based antibiotic therapy
• Confirmation of eradication in persistent cases
Celiac Disease:
• Sometimes presents solely as infertility.
• Screening:Tissue transglutaminase IgA
• Undiagnosed or untreated celiac disease can cause
• systemic inflammation
• and nutrient malabsorption
(such as zinc, iron, and folate deficiency),
• which directly impairs ovarian function and semen quality
Antisperm Antibodies (ASA)
• The body’s immune system can mistakenly identify sperm as
foreign invaders.
• In men,
a breach in the blood-testis barrier can cause them to
produce antibodies that immobilize their own sperm.
• In women,
cervical secretions may contain antibodies that destroy
sperm before they reach the egg
Antiphospholipid syndrome (APS)
Not recommended routinely:
•NK-cell testing
•Cytokine profiling
•Most immune-based infertility tests outside research setting
Thrombophilia
• Inherited or acquired blood-clotting disorders (like
Antiphospholipid Syndrome)
• can cause micro-clots in the developing placenta,
• preventing successful embryo implantation and
• leading to early, unnoticed pregnancy loss.
Endometrial Receptivity Disorders
• A morphologically normal endometrium may not be functionally
receptive.
• Potential mechanisms include:
• Altered progesterone signaling
• Defective decidualization
• Abnormal inflammatory cytokines
• Altered endometrial microbiome
• Routine endometrial receptivity testing (ERA) is not
recommended for all patients and should be reserved for
selected cases of repeated implantation failure.
Adenomyosis
• Increasingly recognized as an independent cause of infertility.
• Mechanisms:
• Chronic inflammation
• Abnormal uterine peristalsis
• Impaired implantation
• Increased miscarriage
• Diagnosis:
• Expert transvaginal ultrasound
• MRI
Minimal or Occult Endometriosis
• Even Stage I disease may significantly impair fertility despite
normal imaging.
• Mechanisms include:
• Oxidative stress
• Inflammatory cytokines
• Reduced oocyte competence
• Altered implantation
Endometriosis Without Pain
• Absence of dysmenorrhea or pelvic pain does not exclude
endometriosis.
• Infertility may be the only clinical presentati
Abnormal Uterine Peristalsis
• Excessive or disorganized uterine contractions may impair:
• Sperm transport
• Embryo migration
• Implantation
• Often
associated with adenomyosis and endometriosis.
Hidden Male Factor Infertility
Normal semen analysis does not guarantee normal fertility.
Important abnormalities include:
•Sperm DNA fragmentation
•Oxidative stress
•Aneuploidy
•Mitochondrial dysfunction
Advanced sperm testing should be considered
in selected couples with unexplained infertility, recurrent
miscarriage, or repeated ART failure.
7
Mild Varicocele
• Borderline semen parameters
• may hide significant DNA damage and
• impaired sperm function.
Sexual Dysfunction
• Frequently missed during infertility evaluation.
• Includes:
• Infrequent intercourse
• Erectile dysfunction
• Premature ejaculation
• Dyspareunia
• Vaginismus
Thyroid Dysfunction
• Both overt and subclinical hypothyroidism may impair
fertility.
• Recommended investigations:
• TSH
• Free T4
• TPO antibodies (selected patients)
Hyperprolactinemia
• May present without galactorrhea.
• Effects:
• Ovulatory dysfunction
• Luteal insufficiency
Luteal Phase Deficiency
• Although controversial,
• luteal dysfunction may occur in:
• PCOS
• Obesity
• Thyroid disorders
• Hyperprolactinemia
• No single diagnostic test has sufficient accuracy
Vitamin D Deficiency
• Associated with:
• PCOS
• Endometriosis
• Poor implantation
• Correction of deficiency is recommended
for general health,
• although fertility benefits remain uncertain.
Obesity-Associated Chronic
Inflammation
• Beyond BMI, metabolic inflammation contributes to:
• Insulin resistance
• Oxidative stress
• Poor oocyte quality
• Reduced IVF success
Lean PCOS
• Normal BMI does not exclude:
• Insulin resistance
• Hyperandrogenism
• Ovulatory dysfunction
Cesarean Scar Defect (Isthmocele)
• An increasingly recognized cause of secondary infertility.
• Mechanisms:
• In secondary infertility, a poorly healed C-section scar can
create a small pocket (isthmocele) that collects menstrual
blood. This fluid alters the vaginal pH and creates a chronically
inflamed uterine environment hostile to sperm and embryos
• Diagnosis:
• Saline infusion sonography
• 3D ultrasound
• Hysteroscopy
Small Hydrosalpinx
• Even minimal hydrosalpinges
• may reduce implantation through embryotoxic tubal fluid.
• Salpingectomy or proximal tubal occlusion improves IVF
outcomes.
Overlooked Anatomical and Structural Factors
•Silent Endometriosis / Adenomyosis:
•Many individuals experience "silent" endometriosis,
• which lacks the classic symptom of debilitating pelvic pain.
•Instead, localized inflammatory cytokines and
• altered pelvic anatomy quietly impair egg quality and fertilization
Endocrine Disrupting Chemicals (EDCs)
• Low-level, daily exposure to everyday toxins—such as
phthalates, bisphenols (BPA), and parabens found in plastics
and cosmetics—can alter hormone receptor sensitivity and
silently degrade egg and sperm quality over tim
Environmental Exposure
• Potential contributors include:
• BPA
• Phthalates
• Heavy metals
• Pesticides
• Air pollution
• Through endocrine disruption and oxidative stress.
Microbiome Disruptions
•Vaginal and Uterine Dysbiosis:
• A healthy reproductive tract relies heavily on Lactobacillus-dominated
microbiomes.
• A shift toward pathogenic bacteria (dysbiosis)
•triggers a localized immune response that prevents successful embryo
implantation,
• even without presenting as a full-blown infection.
Genetic Factors
• Female:
• Balanced translocations
• FMR1 premutation
• Mosaic Turner syndrome
• Male:
• Y chromosome microdeletions
• CFTR mutations
• Chromosomal abnormalitie
Sleep Disorders
• Circadian disruption may adversely affect:
• Ovulation
• Hormonal regulation
• Fecundity
• Especially among night-shift workers.
Suggested Diagnostic Approach
• A modern infertility evaluation should include:
• Comprehensive female assessment
• High-quality semen evaluation
• Consideration of advanced sperm function tests when indicated
• High-resolution transvaginal ultrasound
• Evaluation for chronic endometritis when suspected
• Thyroid and prolactin assessment
• Lifestyle and metabolic evaluation
• Genetic testing in selected couples
• Careful assessment before labeling infertility as "unexplained"
Key Clinical Messages (2026)
• Chronic endometritis
remains one of the most underdiagnosed yet highly treatable
causes of infertility.
• Mild adenomyosis, occult endometriosis, and cesarean scar defects
are increasingly recognized contributors to implantation failure.
• Normal semen analysis does not exclude clinically significant male
infertility.
• Immune testing, microbiome testing, and routine endometrial
receptivity assays
should not be performed routinely and
should be reserved for carefully selected patients according to
current ASRM, ESHRE, and NICE recommendations.
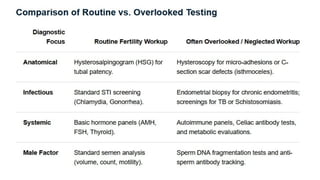
Difference Between Routine Infertility Investigation and Neglected Infertility Investigation
Aspect Routine Infertility Investigation Neglected / Overlooked Infertility Investigation
Main aim Identify common causes of infertility Detect less obvious or missed causes
Ovulation Menstrual history ± ovulation assessment Reassess subtle ovulatory/endocrine disorders when suspected
Ovarian reserve AMH + AFC ± FSH/E2 Interpretation in relation to age, previous surgery, endometriosis and treatment history
Male factor Semen analysis Repeat semen analysis + targeted hormonal/genetic evaluation when abnormal
Uterus TVUS Expert TVUS ± SIS ± hysteroscopy for subtle cavity lesions
Fallopian tubes HSG / HyCoSy Look specifically for hydrosalpinx, distal tubal disease and peritubal adhesions
Endometrial cavity TVUS ± HSG SIS / hysteroscopy for polyps, adhesions and subtle submucous fibroids
Chronic Endometritis Usually not routinely investigated Endometrial biopsy ± CD138 when clinically indicated
Endometriosis May be suspected from symptoms/US Detailed assessment ± expert TVUS/MRI; laparoscopy in selected cases
Adenomyosis May be detected on routine US Expert TVUS ± MRI when suspected
Pelvic adhesions Usually not directly assessed Consider laparoscopy when clinical suspicion is significant
Genital TB Not routine Targeted investigation in women with relevant epidemiological/clinical risk
Sexual dysfunction May be overlooked Detailed sexual history and examination
Recurrent implantation failure Not applicable initially
Review uterine cavity, endometrium, embryo-related and other relevant factors
systematically
Unexplained infertility Diagnosis after standard work-up is normal Re-review the diagnosis and look for previously missed causes
Advanced investigations Used selectively More likely to be considered, but only when clinically indicated
The practical difference
Routine infertility work-up:
Ovulation → Ovarian reserve → Semen analysis → Uterus → Tubal patency
⬇️
If normal but infertility persists:
Neglected/Overlooked causes →
Endometriosis → Adenomyosis → Chronic Endometritis → Polyps → Adhesions →
Hydrosalpinx
→ Subtle tubal disease → Sexual dysfunction → Selected endocrine/infectious
causes
Important message for your lecture
Neglected infertility does NOT mean ordering more tests for everyone.
It means revisiting the diagnosis and performing targeted investigations
when the clinical history or previous treatment suggests a missed cause.
This distinction is important because indiscriminate testing can
lead to false-positive results and unnecessary treatment.
Summary of the Main Issue
• Neglected causes of infertility—ranging from hidden
chronic infections and systemic autoimmune disorders to
silent anatomical defects—frequently mimic "unexplained
infertility" because they are omitted from standard
diagnostic protocols.
• Identifying these underlying issues requires looking beyond
standard hormone and fluid checks to evaluate systemic
immune, microbiome, and environmental health
Lifestyle Modification in Infertility
Lifestyle factor Recommendation
Weight Aim for a healthy BMI; both obesity and underweight can impair fertility
Smoking Stop completely; applies to both partners
Alcohol Avoid or minimize, particularly when trying to conceive
Caffeine Moderate intake; avoid excessive caffeine
Diet
Balanced diet rich in vegetables, fruits, whole grains, legumes, fish and
healthy fats
Physical activity
Regular moderate exercise; avoid excessive strenuous exercise if it causes
menstrual dysfunction
Sleep Adequate regular sleep
Stress
Stress reduction, counseling/CBT when needed; avoid blaming infertility on
stress
Environmental exposures
Reduce exposure to tobacco smoke, recreational drugs and relevant
occupational/environmental toxins
Heat exposure in men Avoid prolonged excessive scrotal heat when possible
Sexual timing
Intercourse every 1–2 days during the fertile window is generally
appropriate
Medications
Review medications that may affect fertility with a physician; do not stop
essential medications without advice
Lifestyle modification In neglected/overlooked infertility
•Lifestyle modification is particularly useful when there are modifiable risk factors,
•but it will not correct conditions such as:
•Hydrosalpinx
•Endometrial polyp
•Intrauterine adhesions
•Significant endometriosis
•Adenomyosis
•Severe male-factor infertility
•Tubal occlusion
Key message for the lecture:
Lifestyle modification should be offered to all couples trying to conceive,
but treatment must be directed at the underlying cause when one is
identified.
Empirical Treatment in Unexplained Infertility — 2026
Cause Evidence-based treatment when indicated Empirical treatment?
Chronic Endometritis Appropriate antibiotics, commonly doxycycline; reassessment in selected cases May be considered when strongly suspected, but not routinely
Adenomyosis
GnRH agonist in selected cases; conservative surgery in selected patients; IVF according to individual
factors
Not routinely
Endometriosis Surgery in selected cases; IVF according to age, duration of infertility and other factors No routine empirical treatment
Sperm DNA Fragmentation Treat underlying causes; lifestyle modification; varicocele treatment when indicated Antioxidants may be considered selectively; evidence remains limited
Varicocele Varicocele repair when clinical criteria are met No
Luteal Phase Dysfunction Progesterone in selected clinical/ART settings Not routinely recommended
Hypothyroidism Levothyroxine when hypothyroidism is diagnosed No — confirm diagnosis
Hyperprolactinemia Cabergoline or bromocriptine after confirming the diagnosis and cause No
Vitamin D Deficiency Vitamin D replacement when deficiency is documented No — not an empirical fertility treatment
PCOS with Anovulation Letrozole is first-line ovulation induction; IUI may be added in selected cases Yes, but only when the clinical diagnosis is established
Cesarean Scar Defect (Isthmocele) Hysteroscopic or laparoscopic repair in selected patients No
Hydrosalpinx Salpingectomy or proximal tubal occlusion before IVF when indicated No
Asherman Syndrome Hysteroscopic adhesiolysis No
Genital Tuberculosis Anti-tuberculous therapy after appropriate diagnostic confirmation No
Antiphospholipid Syndrome (APS) Low-dose aspirin + heparin according to established indications No — do not use routinely in unexplained infertility
Abnormal Uterine Hyperperistalsis Treat the underlying cause; selected interventions have been studied during embryo transfer No established empirical regimen
Isolated Uterine Spasm No established fertility-enhancing pharmacological treatment Not evidence-based
Empirical treatment ≠ treatment without thinking or without evaluation
• better approach is:
• Exclude major causes identify clinical clues select treatment
→ →
according to the most likely mechanism reassess outcome.
→
• I would classify treatments into three groups:
• 1. Evidence-based treatment
Treatment of an identified disease.
• 2. Selected empirical treatment
Used when there is a strong clinical suspicion but definitive testing is
unavailable, inappropriate, or unlikely to change management.
• 3. Investigational treatment
Promising mechanisms but insufficient evidence for routine clinical use.
• Doxycycline can therefore be discussed under Selected Empirical Treatment
when chronic endometritis is strongly suspected.
• Low-dose aspirin, Librax, Drotaverine, or other antispasmodics should
NOT be presented as standard empirical treatment for unexplained
infertility.