Clinical Trials
As per the revised Schedule Y of drugs and cosmetics act 2005:
122-DAA. Definition of Clinical trial
It is a systematic study of new drug(s) in human subjects to generate data for discovering and/or verifying
the clinical, pharmacological, and/or adverse effects with the objective of determining their safety and/or
efficacy of the new drugs.
Key elements:
PICO is used by health professionals to convey all elements of the clinical scenario in an orderly fashion:
P - Patient, Population of patients, Problem
I - Intervention (a therapy, test)
C - Comparison (another therapy, placebo)
O- Outcome (survival, response)
Bias:
Bias is a systematic error contained in the study design, conduct or interpretation of a study. Whereas extensive
lists of particular bias forms exist, there are two basic forms of bias:
1. Selection bias occurs if study populations are selected in an erroneous way that
comparison groups are not comparable.
2. Information bias occurs if measurements are different between
Techniques to avoid bias:
1. Randomisation of subjects.
2. Blinding of subjects as well as investigator.
3. Monitoring of clinical trial.
4. Checking original source documents.
5. Source data verification.
6. Clinical data management.
7. Quality control (QC) and Quality assurance (QA) procedures.
Randomization:
 It aims to obviate systematic differences between groups due to factors other than intervention.
 It gives each patient a known (or equal) chance of being assigned to any of the groups.
The most common methods of randomisation are:
1. Simple randomization
2. Blocked randomization
3. Stratified randomization
4. Cluster randomization
Blinding:
 Single- blind design
 Double- blind design
 Triple- blind design
Types of Clinical Trials:
 Superiority Trials: Compare a std treatment or intervention with a new or alternative
approach anticipated to be more effective.
 Inferiority Trials: An alternative therapy (perhaps one that is cheaper, less toxic or easier to administer)
is suggested to replace the standard provided its efficacy is no worse than the std.
 Equivalence: Test treatment is required to be neither less nor more efficacious than std.
Categorization of clinical trials:
 Based on Number of participating centers:
1. Single center vs Multicenter
2. National vs International
 Based on control grp:
1. Non-comparative
2. Historical controls
3. Concurrent controls
4. Self controls
 Based on randomization:
1. Non-randomized
2. Simple randomized
3. Balanced (stratified) randomized
4. Cluster randomized
 Based on blinding (masking):
1. Open label/non-blinded
2. Single
3. Double
4. Triple
5. Double dummy
 Based on purpose:
1. Treatment
2. Prevention
3. Screening
4. Quality of life
5. Compassionate use
6. Genetics
 Based on trial format:
1. Traditional designs for CT
• Parallel group
• Cross-over
• Factorial
• Add-on
• Randomized with-drawal
• Early escape
2. Special design issues for small CT:
• N-of-1 Design
• Sequential design
• Decision analysis based design
• Adaptive
• Risk based allocation design
3. Miscellaneous designs:
• Cluster randomized
• Enrichment design
• Placebo challenging
• Blind reader
• Zelen’s design
• Wennberg’s design
• Comprehensive cohort design
• Design using historical controls
• Rolling design
Factors considered in selecting CT design:
• Study population and indication
• Treatment duration
• Carry over effects
• Cost and logistics
• Patient convenience
• Statistical considerations
Role of placebo:
 No standard treatment exists.
 Standard treatment is ineffective.
 Standard treatment is inappropriate for the particular clinical trials.
 The placebo is reportedly effective in treating the disease.
 The disease is mild and lack of treatment is not considered to be medically important.
 The placebo is given as an add-on treatment to an already existing regimen that is
not sufficient to treat patients.
 The disease process is characterized by frequent spontaneous exacerbations and
remission(e.g., peptic ulcer).
 “Escape clauses” or points are
Run in period:
Before randomization of patients a run-in (or lead-in) period of placebo, no active treatment, dietary control, or
active maintenance therapy is usually employed.
Advantages:
1. It acts as a washout period to remove effects of previous therapy.
2. It can be used to obtain baseline data and to evaluate if patient fulfills study entry
criteria.
3. It can be used as a training period for patients, investigators, and their staff.
4. It helps in identifying placebo responders.
5. It provides useful information regarding patient compliance.
6. It can be used to estimate and compare the magnitude of possible placebo effects between two doses.
Parallel group design:
It is of two types:
1. Group comparison parallel design: In this method, efficacy of treatment is using two groups
(Treatment vs Control group).
2. Match pair parallel design: In this method pairs of subjects might be possessing same characteristics
and who might be expected to respond similarly to the treatment
Group comparison parallel design:
Most common clinical design.
Complete randomized design in which each patient receives one and only one treatment in a randomized
fashion
Advantages:
It’s simple and easy to implement.
It is universally acceptable.
It is applicable to acute conditions.
Analysis is less complicated and interpretation is straight forward.
Disadvantages:
It doesn’t take into account the individual inter-variability.
Matched pair parallel design:
 In this method, pairs of subjects are formed possessing the same characteristics and who might be
expected to respond similarly to the treatments.
 Matching of patients is done before randomization.
Advantages:
a. Requires small study population.
b. Can reduce variability from treatment comparison (compared with parallel froup designs).
Disadvantages:
a. The prognostic characteristics are not easily defined.
b. Patient recruitment is slow.
c. When the number of co-variants is large design is difficult to implement.
Cross over design:
 A crossover design is a modified randomized block design in which each block receives >1 treatment
at different dosing periods.
 A block can be a patient or a group of patients. Patients in each block receive different sequences of
treatments.
Crossover designs may be used in clinical trials in the following situations where:
1. Objective measures and interpretable data for both efficacy and safety are obtained.
2. Chronic (relatively stable) disease are under study.
3. Prophylactic drugs with relatively short half-life are being investigated.
4. Relatively short treatment periods are considered.
Advantages:
1. It allows a within-patient comparison between treatments, since each patient serves as his or
her own control.
2. It removes the interpatient variability from the comparison between treatments.
3. With a proper randomization of patients to the treatment sequences, it provides the best unbiased
estimates for the differences between treatments.
Disadvantages:
1. Carry- over effects: The residual influence of treatments on subsequent treatment periods.
Avoided by wash out period.
2. Order effects: Order in which the tt are administered affects the outcome.
3. Period effects: The diff. between the study periods.
4. Drop-outs can be higher.
Concept of wash-out effects:
AKA carry over / residual effects.
It is the rest period between 2 treatment periods.
 It permits the effect of previous treatment to wane off.
 It should be long enough for the treatment effect to wear off so that there is no carryover effect of
previous treatment to next.
 It depends upon the nature of the drug.
Split person design:
 Occasionally, it is possible to administer the two interventions at the same time.
 Very similar to that of the cross-over trial, except there is no equivalent to the periods or to the
wash-out although a carry-over (now termed carry-across) effect is likely to be present.
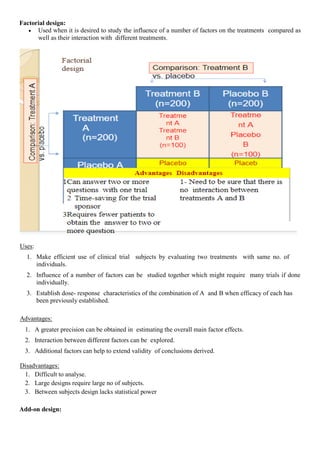
Factorial design:
 Used when it is desired to study the influence of a number of factors on the treatments compared as
well as their interaction with different treatments.
Uses:
1. Make efficient use of clinical trial subjects by evaluating two treatments with same no. of
individuals.
2. Influence of a number of factors can be studied together which might require many trials if done
individually.
3. Establish dose- response characteristics of the combination of A and B when efficacy of each has
been previously established.
Advantages:
1. A greater precision can be obtained in estimating the overall main factor effects.
2. Interaction between different factors can be explored.
3. Additional factors can help to extend validity of conclusions derived.
Disadvantages:
1. Difficult to analyse.
2. Large designs require large no of subjects.
3. Between subjects design lacks statistical power
Add-on design:
A placebo-controlled trial of an experimental intervention is tested with people already receiving
an established, effective treatment.
Uses:
1. Add on design is especially useful for testing of an experimental interventions that have mechanism
of action different from that of established effective treatment.
2. It can be used for long term studies of treatments of conditions like heart failure since
established treatment is life saving and is not being denied.
Trials minimizing time on inactive treatment or placebo:
Randomized withdrawal
Early escape
Randomized placebo
Stepped wedge design
Randomized withdrawal:
 Here, individuals who respond (+)ly to an experimental intervention are randomized to continue receiving
that intervention or to receive a placebo.
 Return of symptoms in placebo group causes withdrawal of subject from that group.
Advantage: This trial design minimizes the amount of time that individuals receive a placebo.
Disadvantages:
Carry over effects.
Difficulties in assessing whether the underlying disease process is still active.
Long lag times to adverse events if the disease is inremission.
Early escape design:
 Participants are removed from the study if symptoms reached a defined level or they fail to respond to a
defined extent.
 The patient could then be switched over to another therapy, including the test treatment if
appropriate
Advantages:
1. It minimizes an individual’s duration of exposure to a placebo.
2. Ethically justifiable.
Disadvantages:
1. Complex statistical analysis.
2. Difficulties in assessing whether underlying disease is active or not (like Randomised withdrawal
design).
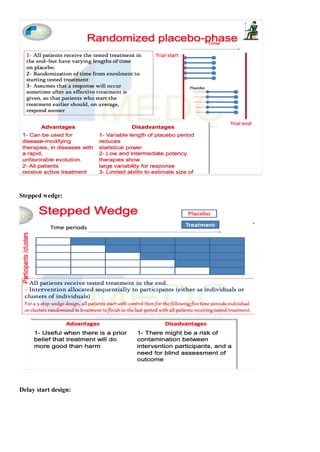
Randomized placebo trial:
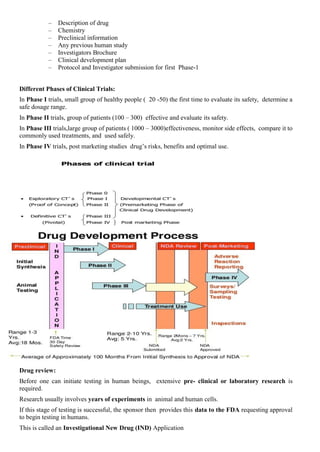
Stepped wedge:
Delay start design:
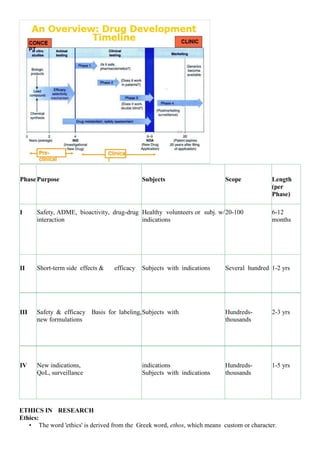
Drug Discovery and clinical trial phases:
Clinical Trial:
Clinical trial is a systematic investigation in human subjects for evaluating the safety & efficacy of any
new drug.
Clinical trials are a set of tests in medical research and drug development that generate safety and
efficacy data for health interventions in human beings.
Research studies involving people
Try to answer scientific questions and find better ways to prevent, diagnose, or treat disease
Translate results of basic scientific research into better ways to prevent, diagnose, or treat disease
Drug Development Process:
• Investigational New drug (IND)
• Pre clinical studies (animal studies)
• USFDA- ask for
– Description of drug
– Chemistry
– Preclinical information
– Any previous human study
– Investigators Brochure
– Clinical development plan
– Protocol and Investigator submission for first Phase-1
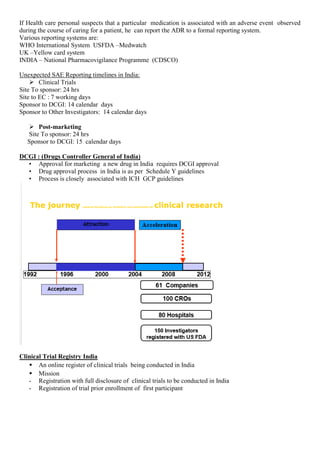
Different Phases of Clinical Trials:
In Phase I trials, small group of healthy people ( 20 -50) the first time to evaluate its safety, determine a
safe dosage range.
In Phase II trials, group of patients (100 – 300) effective and evaluate its safety.
In Phase III trials,large group of patients ( 1000 – 3000)effectiveness, monitor side effects, compare it to
commonly used treatments, and used safely.
In Phase IV trials, post marketing studies drug’s risks, benefits and optimal use.
Drug review:
Before one can initiate testing in human beings, extensive pre- clinical or laboratory research is
required.
Research usually involves years of experiments in animal and human cells.
If this stage of testing is successful, the sponsor then provides this data to the FDA requesting approval
to begin testing in humans.
This is called an Investigational New Drug (IND) Application
Preclinical evaluation phase (animal studies):
Pharmacodynamic studies in vivo in animals, in-vitro preparation
Absorption, distribution , elimination studies(Pharmacokinetics)
Acute ,sub acute, chronic toxicity studies (toxicity profile)
Therapeutic index (safety & efficacy evaluation)
Prephase I:
A-Preclinical Data Review : Drug Discovery Team- efficacy, safety, toxicology, ADME
B-Preparation of Investigator’s Brochure
Summaries of Preclinical data with clinical Extrapolation.
Prediction of Clinical Effects & Safety
C–Filing of Investigational New Drug Application with DCGI.
IND Application:
Clinical Evaluation needs Prior Regulatory and IRB Clearance.
Phase-wise clearances have to be obtained.
The End Result of Phase I-III studies is the filing of NDA (New Drug Application) for obtaining
Marketing Permission from DCGI.
Microdosing / Phase 0 study:
Early studies of the pharmacodynamic and pharmacokinetic properties of a potential drug in humans.
Microdosing approach could‘accelerate’ drug development without compromising clinical safety
Microdosing helps researchers select better drug candidates for clinical trials by providing early human PK
and bioavailability data.
Microdose (MD)
<100 μg dose of a drug that can be administered as a single dose or divided doses in any subject.
 Exploratory study
 early phase-1
 limited human exposure
 no therapeutic intent
 not intended to examine clinical tolerability
Principle:
Safely administering sub pharmacological doses of NCEs/NMEs to humans to obtain PK/PD, bioavailability
and metabolism at much earlier stage
Basic features
First in human trial (prior to traditional phase 1)
Small number of subjects (10-15)
Limited exposure to drug
- Low non-toxic dose
- short duration (</= 7 days)
No therapeutic intent (clinical benefit)
Goals:
Provide PK-PD data prior to definitive testing in phase 1
Evaluate BA to select most promising dose
Eliminate bad agents early (fails to reach target, rapid clearance, poor BA)
Procedure
Analytical method
Plasma /urine /biopsy sample serially collected
Samples analyzed for parent drug and metabolites
Micro-doses → micro plasma drug concentrations: extremely sensitive analytical methods required
- PET (Positron Emission Tomography)
- LC-MS (Liquid Chromatography – Mass Spectrometry)
- AMS (Accelerated Mass Spectromerty)
Application
Primary emphasis: early PK prediction
Estimating drug conc. at site of action Metabolic profiling of drug
Drug-drug interactions
Study in vulnerable population
Advantages:
Early selection of promising compounds
Avoid unnecessary exposure of participant to not-so-promising compounds
Early elimination of not-so-promising compounds– saves resources
Pose less risk of overall human toxicity (low dose/ less duration / limited subjects)
Lesser preclinical safety package required – reduce animal use
Drug can be ethically tested in sensitive population
Establishes likely pharmaceutical dose more accurately for subsequent Phase 1 study
Overall acceleration of drug development process
Limitations:
Not enough studies to prove
- false negatives (good compound rejected)
- false positives (unsuitable compounds)
Cautiously interpret while using drugs with non-linear / complex kinetics
Few drugs dissolve readily at low doses but
have limited solubility at high dose
Lack of therapeutic intent Requires expensive equipment
Advantages:
Less chances of adverse effects , Short duration, Less no. of volunteers, Reduced cost of development,
Reduced drug development time
Limitations:
Study mainly based on PK parameters - not efficacy and safety based
Agents having different kinetic characteristics between microdose and full dose are not evaluated by phase
0 trials
Of Limited use for agents having Non linear PKs
The laboratory parameters are very limited and expensive, researchers have to depend on BA/BE labs
Phase I:
First stage of testing in human subjects Designed to assess the safety, tolerability,
PK and PD of drug.
20-25 healthy volunteers
Patients: Anticancer drugs, AIDS therapy Duration: 6-12 months
No blinding / Open labelled
Basic pre-requisites:
Preclinical data IND application
Approval by the regulatory authority
Protocol approval by the Ethics Committee
Informed consent
Adherence to Declaration of Helsinki /ICH- GCP guidelines, at the start as well as from time to time,
during the study
The aim of a Phase I trial is to determine the maximum tolerated dose (MTD) of the new treatment.
The MTD is found by escalating the treatment dose until the dose-limiting toxicity (DLT) is reached.
Kinds of Phase I
SAD: single ascending dose studies
MAD: multiple ascending dose studies
Food Effect: investigates differences in absorption caused by food
Single ascending dose studies (SAD):
Small groups (3) of subjects are given a single dose of the drug while they are observed and tested for a
period of time.
If no adverse effects ….dose is escalated with 3 new healthy subjects
If toxicity is observed then ---- 3 more subjects are given the same dose and
If found toxic….. the dose is considered as max. tolerated dose (MTD).
Multiple ascending dose studies(MAD):
Conducted to understand the pharmacokinetics and pharmacodynamics of multiple doses of the drug.
A group of patients receives multiple low doses of the drug
Samples (of blood, and other fluids) are collected at various time points
Analyzed: How the drug is processed within the body.
Need:
To make reliable and rapid Prediction of human response, from Preclinical Data (PD, PK, Toxicity)
Involves Extrapolation from Animal data to first human exposure.
Phase I serves as an interface between Preclinical Research and Clinical Drug development.
Once Phase I is complete, Human beings become first-choice test species (Human Guinea- pigs).
Objectives:
1. Primary :
i. Tolerability and Safety
ii. Pharmacokinetics
2. Secondary
iii. Pharmacodynamics
Subjects:
Healthy human volunteers: Most commonly used. (Non-Therapeutic Research)
Subjects receive no therapeutic benefit by participation - Ethical issue.
Patient Volunteers: Cytotoxic drugs, AIDS therapy
Patients in advanced stage of disease
Reasons for Using Healthy Volunteers:
Large numbers available (vs. Patients) Rapid recruitment rate
Potential risks are considerably reduced Results not confounded by presence of disease variables
More homogenous group
Greater compliance with Protocol
In case of ADR’s Chances of Speedy and Complete recovery are better Advantages > Disadvantages
Patient Volunteers:
Whenever Preclinical Toxicity Data indicates potential risks for subjects & Ethical Concerns preclude use of
healthy human subjects e.g.Cancer/AIDs/Psychiatric patients
Dose range of interest is appropriate to determine in patients than in healthy volunteers
Special Population Healthy Volunteers
It is now a regulatory requirement to include:
-Women of child bearing age
-Children, if NCE is proposed to be used in them.
-Elderly (>65 years) of age.
Limitations
Trial restricted to homogenous subjects
Performance extrapolated to heterogeneous market place
Phase II
Therapeutic Exploratory Trial
20-300 Subjects
To confirm effectiveness, monitor side effects, & further evaluate safety
First in patients (who have the disease that the drug is expected to treat)
Duration: 6 months to several years.
Objectives
Efficacy in patients (primary objective) Safety issues (secondary objective) Optimum dose finding
Dose efficacy relationship:
 Therapeutic dose regimen
 Duration of therapy
 Frequency of administration
 Therapeutic window
Pre-requisites:
Review of Phase I data Innovator/ Experts
IRB DCGI
Prior approval by IRB and DCGI is Mandatory
For New Actions of a marketed drug, start with Phase II (Phase I exemption obtained)
Types:
Phase IIA: Designed to assess dosing requirements
Phases IIB: Designed to study efficacy
Phase III:
Therapeutic confirmatory trials.
Large scale, multicentre, Randomised, Controlled trials .
Target population: several 100’s to 3000 patients.
Takes a long time: up to 5 years
To establish efficacy of the drug against existing therapy in larger number of patients, method of usage, & to
collect safety data etc.
Objectives:
To assess overall and relative therapeutic value of the new drug Efficacy, Safety and Special Properties
To determine optimal dosage schedule for use in general
The dosage schedule in C.T.’s should be as close as possible to its anticipated clinical use
Prerequisites:
Efficacy and dose schedule defined in Phase II studies
No gross ADR’s
Long term preclinical safety studies completed
-Chronic Toxicity
- Reproductive toxicity
- -Carcinogenicity
- Marketing inputs favourable
- IRB and DCGI approval obtained
Subtypes
Phase IIIA: to get sufficient and significant data.
Phase IIIB: allows patients to continue the treatment, Label expansion, additional safety data. They are known
as "label expansion” to show the drug works for additional types of patients/diseases beyond the original use
for which the drug was approved for marketing.
End of Clinical Trial Activities
Sponsor: Expert Committee review of Efficacy, safety and potential sales (Profit).
Go-No Go decision to file new drug application with DCGI
Expert review by DCGI’s Committee
DCGI approval
NCE marketed ….. Phase IV begins
NDA: New Drug Application:
NDA Refers to New Drug Application
Formal proposal for the FDA/DCGI to approve a new drug for sale
Sufficient evidences provided to FDA/DCGI to establish:
-Drug is safe and effective.
-Benefits outweigh the risks.
-Proposed labeling is appropriate.
NDA contains all of the information gathered during preclinical to phase III
NDA can be thousands of pages long Can take 2-3 years for FDA to review
Phase IV:
Harmful effects discovered may result in a drug being no longer sold, or restricted to certain uses.
On September 30, 2004, Merck withdrew rofecoxib from the market because of concerns about increased
risk of heart attack and stroke associated with long-term, high-dosage use.
Objectives
Confirm the efficacy and safety profile in large populations during practice
Detect the unknown/rare adverse drug reaction/s
Evaluation of over-dosage
Identifications of new indications
Dose refinement: Evaluation of new formulations, dosages, durations of treatment
Evaluation in different age groups / types of patients
Comparative Benefit-Risk assessment
Benefit-Cost assessment (Pharmaco- economics)
Drug usage in the community
Quality Of Life assessment
REPORTING of ADR:
If Health care personal suspects that a particular medication is associated with an adverse event observed
during the course of caring for a patient, he can report the ADR to a formal reporting system.
Various reporting systems are:
WHO International System USFDA –Medwatch
UK –Yellow card system
INDIA – National Pharmacovigilance Programme (CDSCO)
Unexpected SAE Reporting timelines in India:
 Clinical Trials
Site To sponsor: 24 hrs
Site to EC : 7 working days
Sponsor to DCGI: 14 calendar days
Sponsor to Other Investigators: 14 calendar days
 Post-marketing
Site To sponsor: 24 hrs
Sponsor to DCGI: 15 calendar days
DCGI : (Drugs Controller General of India)
• Approval for marketing a new drug in India requires DCGI approval
• Drug approval process in India is as per Schedule Y guidelines
• Process is closely associated with ICH GCP guidelines
Clinical Trial Registry India
• An online register of clinical trials being conducted in India
• Mission
- Registration with full disclosure of clinical trials to be conducted in India
- Registration of trial prior enrollment of first participant
PhasePurpose Subjects Scope Length
(per
Phase)
I Safety, ADME, bioactivity, drug-drug
interaction
Healthy volunteers or subj. w/
indications
20-100 6-12
months
II Short-term side effects & efficacy Subjects with indications Several hundred 1-2 yrs
III Safety & efficacy Basis for labeling,
new formulations
Subjects with Hundreds-
thousands
2-3 yrs
IV New indications,
QoL, surveillance
indications
Subjects with indications
Hundreds-
thousands
1-5 yrs
ETHICS IN RESEARCH
Ethics:
• The word 'ethics' is derived from the Greek word, ethos, which means custom or character.
• Ethics is the systematic study of values, so as to decide what is right and what is wrong.
• Ethics is a subject that deals with values, principles, beliefs, and opinions
• Not a natural science but a creation of the human mind, open to the influence of time, place, and
situation
• A framework to determine what is right and wrong regarding human action, character, and behavior
• comes from within, unlike law which regulates the external behavior
Moral problem in clinical research
• The goal of clinical research is generation of useful knowledge about human health and illness
• Benefit to participants is not the purpose of research (although it does occur)
• People are the means to developing useful knowledge; and are thus at risk of exploitation
Ethics of Clinical Research:
• Ethical requirements in clinical research :
– minimize the possibility of exploitation;
– ensure that the rights and welfare of subjects are respected
History
1. The Nuremberg Code (1947)
2. The Declaration of Helsinki (1964)
3. U.S. Code of Federal Regulations (1974)
4. The National Research Act and The IRB System (1974)
5. The Belmont Report (1979)
6. ICMR Guidelines (2000,2006)
NAZI MEDICAL WAR CRIMES
• The Medical Case, U.S.A. vs. Karl Brandt, et al. (also known as the Doctors' Trial)
• 1946-47
• Twenty-three doctors and administrators
• Accused of organizing and participating in war crimes and crimes against humanity in the form of
medical experiments and medical procedures inflicted on prisoners and civilians
Nuremberg Trials: The Doctors Trial
• Ignorance
• Orders from superiors
• Medically justified
• Others
• 16 found guilty
• Verdict contained a section “Permissible Medical Experiments”
• Nuremberg Code
• The 23 defendants
Nuremberg code
Nazi Experiments- 1945-1947- The Nuremberg Trial
1. Children in concentration camps who had been used for medical experiments.
2. Thalidomide – phocomelia
3. Photograph of an injury caused by a phosporous experiment conducted at Ravensbruek in 1941
4. A Romani (Gypsy) victim to make seawater potable. Dachau concentration camp, Germany, 1944
5. Bodies and parts of bodies of people subjected to medical experiments
6. High Altitude Experiments
7. A victim immersed in icy water at the Dachau concentration camp. Germany, 1942
Nazi-era doctor Heinrich Gross, who was accused of killing children
Nazi Experiments
 experimental starvation
 induced gangrene
 low barometric pressure
 induced hypothermia
 induced burns and wounds
Characteristics
• conducted without consent of participants
• caused unnecessary pain, suffering and death
• absence of benefits for the participants
• lack of adequate scientific rationale
The Nuremberg Code is a set of research ethics principles for human experimentation set as a result of the
Subsequent Nuremberg Trials at the end of the Second World War.
The ten points of the Nuremberg Code "the voluntary consent of the human subject is absolutely essential"
THE TUSKEGEE SYPHILIS STUDY:
 Initiated in the 1930s by US Public Health Service (PHS)
 Examination of the natural history of untreated syphilis
 Continued until 1972
 About 400 black men with syphilis participated
 About 200 men without syphilis served as controls
 Nature of study not disclosed
 Treated for ‘bad blood’
 Last Chance for
 Special Free Treatment
• Penicillin was accepted as the treatment for syphilis in 1943. Deliberately withheld from study
subjects.
• Story broke in the Washington Star on July 25, 1972 (Article by Jean Heller of the Associated Press)
• By the end of the experiment, 28 of the men had died directly of syphilis, 100 were dead of related
complications, 40 of their wives had been infected, and 19 of their children had been born with
congenital syphilis.
• For the greater good of science
• Were just carrying out orders, mere cogs in the wheel of the PHS bureaucracy, exempt from personal
responsibility.
• The men had been ‘volunteers’ and ‘were always happy to see the doctors’
• An Alabama state health officer who had been involved claimed ‘somebody is trying to make a
mountain out of a molehill’
• Public outrage prompted Congress to pass the National Research Act in 1974
• The National Research Act also created the National Commission for the Protection of Human
Subjects of Biomedical and Behavioral Research
• This commission published the ‘Belmont Report’ in 1979
cited as "arguably the most infamous biomedical research study in U.S. history”
• "399 black men thought to have syphilis were recruited and followed to determine the course of the
disease (what would happen to them).
• Penicillin was known to be an effective treatment for syphilis by about 1947.
• The subjects were not informed of what was being studied or of the treatment alternatives available.
Belmont Report:
• National Research Act/Belmont Report 1979
• The report established three tenents of ethical research,
 respect for persons,
 beneficence and
 justice
PRUSSIAN DIRECTIVE (BERLIN CODE)
• 29 December, 1900
• First ever government issued directives on human experimentation
• Conditions for exclusion ‘under all circumstances’ of ‘all medical interventions for other than
diagnostic, healing and immunization purposes, regardless of other legal or moral authorization’
Conditions of exclusion:
• The human subject is a minor or not competent due to other reasons
• The human subject has not given his unambiguous consent
• The consent is not preceded by a proper explanation of the possible negative consequences of the
intervention
NUREMBERG CODE
(1946. Permissible Medical Experiments)
1. Voluntary consent essential
2. Experiment for fruitful results for the good of society and should be necessary
3. Animal experiments first and human study in anticipation of scientific benefits
4. Avoid physical and mental suffering and injury
5. No intentional death or disability
6. Risks not to exceed humanitarian importance of problem
7. Proper preparation and adequate facilities to protect against even remote possibilities of injury
8. Study only by qualified persons
9. Subject at liberty to discontinue
10. Investigator to stop if harm occurs or is anticipated
BELMONT REPORT
(National Commission for the Protection of Human Subjects of Biomedical and Behavioral Research, 1979)
A. Boundaries between research and practice
B. Ethical principles underlying the conduct of research:
• Respect for persons
Individuals should be treated as autonomous agents (capable of self-determination)
Persons with diminished autonomy deserve protection
Application: Informed consent
• Beneficence
Do no harm
Maximize possible benefits and minimize possible harms
Application: Risk/Benefit assessment
• Justice
Fairness in the distribution of the benefits and burdens of research (distributive justice)
Application:
– Fair procedures and outcomes in the selection of subjects
– Protection of vulnerable subjects
DECLARATION OF HELSINKI
• Developed by the World Medical Association
• As a statement of ethical principles to provide guidance to physicians and other participants in medical
research involving human subjects
• First adopted in 1964 (Helsinki, Finland). Has undergone 5 revisions; the most recent in October 2000
• Research must be based on sound scientific background
• Considerations related to the well-being of the human subject should take precedence over the
interests of science and society
• 1964 - Adopted by the 18th World Medical Assembly (latest version 2008)
• A notable change from the Nuremberg Code was a relaxation of the conditions of consent
• obtain consent 'if at all possible‘
• introduced the concept of oversight by an 'independent committee” Or ethics committees
• "all protocols must be submitted to an ethics committee for review, which must be independent of the
investigator, the sponsor or any other kind of undue influence".
ETHICAL REQUIREMENTS FOR A RESEARCH TRIAL
1. Social or scientific value
2. Scientific validity
3. Fair subject selection
4. Favourable risk-benefit ratio
5. Independent review
6. Informed consent
7. Respect for potential and enrolled subjects
ICF from ppt
CFR 21 PART 312: IND Application
 Subpart A- general provisions
 Subpart B - Investigational New Drug Application (IND)
 Subpart C - Administrative Actions
 Subpart D - Responsibilities of Sponsors and Investigators
 Subpart E - Drugs Intended to Treat Life-threatening and Severely-debilitating Illnesses
 Subpart F – Miscellaneous
 Subpart G - Drugs for Investigational Use in Laboratory Research Animals or In Vitro Tests
 Subpart H [Reserved]
 Subpart I - Expanded Access to Investigational Drugs for Treatment Use
Introduction
 An IND is a submission, to the Food and Drug Administration (FDA) requesting permission to initiate
a clinical trial, by the sponsor.
 An IND would be required to conduct a clinical trial if the drug is: (i) a new chemical entity, not
approved for the indication under investigation in a new dosage form, (ii) being administered at a new
dosage level, (iii) in combination with another drug and the combination is not approved.
 This application provides FDA necessarydata to decide whether the new drug and the proposed clinical
trial pose a reasonable risk to the human subjects.
 This application is not required for non-clinical studies, or approved indications.
 An IND is a submission, to the Food and Drug Administration (FDA) requesting permission to initiate
a clinical trial, by the sponsor.
 An IND would be required to conduct a clinical trial if the drug is: (i) a new chemical entity, not
approved for the indication under investigation in a new dosage form, (ii) being administered at a new
dosage level, (iii) in combination with another drug and the combination is not approved.
 This application provides FDA necessarydata to decide whether the new drug and the proposed clinical
trial pose a reasonable risk to the human subjects.
 This application is not required for non-clinical studies, or approved indications.
Sub-part a- general provisions:
 312.1 Scope
(a) Contains procedures and requirements governing the use of IND, including procedures and
requirements for the submission to, and review by, the FDA of INDA.
(b) An investigational new drug for which an INDA is in effect is exempt from the premarketing approval
requirements and may be shipped lawfully for the purpose of conducting clinical investigations of that
drug.
 312.2 Applicability.
(a) Applicability: This part applies to all clinical investigations of products
(b) Exemptions. The clinical investigation of a drug product is exempt from the requirements of this part if:
(i) Drug that is undergoing investigation is lawfully marketed as a prescription drug product,
(ii) Investigation does not involve a route of administration or dosage level or use in a patient that
significantly increases the risks
(iii) A clinical investigation involving an in vitro diagnostic biological product (a ) blood grouping serum;
(b ) reagent red blood cells; and (c ) anti-human globulin.
(iv) A clinical investigation involving use of a placebo
(v) Bioavailability studies. The applicability of this part to in vivo bioavailability studies in humans is
subject to the provisions of § 320.31.
Guidance. FDA may, on its own initiative, issue guidance on the applicability of this part to particular
investigational uses of drugs.
 312.3 Definitions and interpretations.
The definitions and interpretations of terms contained in this application:
a) Clinical investigation: any experiment in which a drug is administered or dispensed to human subjects.
b) Contract research organization: person that assumes, as an independent contractor with the sponsor,
one or more of the obligations of a sponsor, e.g., design of a protocol, selection or monitoring of
investigations, evaluation of reports, etc.
c) Independent ethics committee (IEC): a review panel that is responsible for ensuring the protection of
the rights, safety, and well-being of human subjects involved in a clinical investigation and is able to
provide assurance of that protection.
d) Sponsor: a person who takes responsibility for and initiates a clinical investigation.
e) Subject: a human who participates in an investigation, either as a recipient of the investigational new
drug or as a control.
 312.6 Labelling of an investigational new drug.
a) The immediate package of an IND intended for human use shall bear a label with the statement
"Caution: New Drug - Limited by Federal (or United States) law to investigational use."
b) The label or labelling of an IND shall not bear any statement that is false or misleading
 312.7 Promotion of investigational drugs.
a) A sponsor or investigator shall not represent in a promotional context that an IND is safe or effective
for the purposes for which it is under investigation
b) They shall not commercially distribute or test market an investigational new drug.
c) A sponsor shall not unduly prolong an investigation after finding that the results of the investigation
appear to establish sufficient data to support a marketing application.
 312.8 Charging for investigational drugs under an IND.
 A sponsor must justify the amount to be charged and obtain prior written authorization from FDA
 A sponsor who wishes to charge for its investigational drug, including investigational use of its
approved drug, must:
(i) Provide evidence that the drug has a potential clinical benefit
(ii) Demonstrate that the data to be obtained from the clinical trial would be essential to establishing that
the drug is effective or safe
(iii) Demonstrate that the clinical trial could not be conducted without charging because the cost of the drug
is extraordinary to the sponsor.
 312.10 Waivers.
 A sponsor may request FDA to waive applicable requirement under this part. A waiver request may be
submitted either in an IND or in an information amendment to an IND.
Subpart B - Investigational New Drug Application (IND)
 312.20 Requirement for an IND.
a) A sponsor shall submit an INDA to FDA if the sponsor intends to conduct a clinical investigation with
an investigational new drug that is subject to § 312.2(a).
b) A sponsor shall not begin a clinical investigation subject to § 312.2(a) until the investigation is subject
to an IND which is in effect in accordance with § 312.40.
c) A sponsor shall submit a separate IND for any clinical investigation involving an exception from
informed consent
 312.21 Phases of an investigation:
An IND may be submitted for one or more phases of an investigation.
(a) Phase 1:
i. includes the initial introduction of an IND into humans.
ii. closely monitored and may be conducted in patients or normal volunteer subjects.
iii. designed to determine the metabolism and pharmacologic actions of the drug in humans, the side
effects associated with increasing doses, and, to gain early evidence on effectiveness.
iv. During Phase 1, sufficient information about the drug's pharmacokinetics and pharmacological effects
should be obtained to permit Phase 2 studies.
v. The total number of subjects and patients included in Phase 1 studies varies with the drug, but is
generally in the range of 20 to 80.
(b)Phase 2:
i. Includes the controlled clinical studies conducted to evaluate the effectiveness of the drug for particular
indication(s) in patients with the disease or condition under study
ii. determine the common short-term side effects and risks associated with the drug.
iii. well controlled, closely monitored, and conducted in a relatively small number of patients (no more
than several hundred subjects.)
(c)Phase 3:
i. they are expanded controlled and uncontrolled trials and performed after preliminary evidence
suggesting effectiveness of the drug has been obtained
ii. intended to gather the additional information about effectiveness and safety that is needed to evaluate
the overall benefit-risk relationship of the
iii. provide an adequate basis for physician labelling.
iv. Phase 3 studies usually include from several hundred to several thousand subjects.
 312.22 General principles of the IND submission.
(a) FDA's primary objectives in reviewing an IND are to assure the safety and rights of subjects
(b) In Phase 2 and 3 they help assure that the quality of the scientific evaluation of drugs is adequate to
permit an evaluation of the drug's effectiveness and safety.
(c) The central focus of the initial IND submission should be on the general investigational plan and the
protocols for specific human studies.
(d) Amendments to the IND that contain new or revised protocols should build logically on previous
submissions and should be supported by additional information
(e) The IND format set forth in § 312.23 should be followed routinely by sponsors for an efficient review
of applications.
(f) Sponsors are expected to exercise considerable discretion, however, regarding the content of
information submitted in each section, depending upon the kind of drug being studied.
 312.23 IND content and format.
A sponsor shall submit an "Investigational New Drug Application" (IND) including, in the following order:
 Cover sheet:
i. The name, address, and telephone number of the sponsor, the date of the application, and the name of
the investigational new drug.
ii. The name and title of the person responsible for monitoring the conduct and progress of the clinical
investigations.
iii. The name(s) and title(s) of the person(s) responsible for review and evaluation of information about
safety of the drug.
iv. The signature of the sponsor or the sponsor's authorized representative.
 A table of contents.
 Introductory statement and general investigational plan.
i. A brief introductory statement giving the name of the drug and all active ingredients, the drug's
pharmacological class, the structural formula, the formulation of the dosage form(s), the route of
administration, and the broad objectives and planned duration of the proposed clinical investigation(s)
 Investigator's brochure
 Protocols.
(i) A protocol for each planned study.
(ii) Phase 1 protocols should provide an outline of the investigation: the number of patients, a description
of safety exclusions, and a description of the dosing plan, or method to be used in determining dose
(iii) In Phases 2 and 3, detailed protocols describing all aspects of the study should be submitted.
(iv) A protocol for a Phase 2 or 3 investigation should be designed to provide alternatives or contingencies
in case deviation from study is required.
(v) A protocol is required to contain the following,:
a) A statement of the objectives and purpose,
b) The name and address and a statement of the qualifications of each investigator,
c) Inclusion and exclusion criteria,
d) Study design,
e) observations and measurements to be made to fulfil the objectives of the study.
 Chemistry, manufacturing, and control information
A section describing the composition, manufacture, and control of the drug substance and the drug product.
The submission is required to contain the following:
a) Drug substance. A description of the drug substance, including its physical, chemical, or biological
characteristics
b) Drug product. A list of all components, which may include reasonable alternatives for inactive
compounds, used in the manufacture of the investigational drug product
c) A brief general description of the composition, manufacture, and control of any placebo
d) Labelling. A copy of all labels and labeling
e) Environmental analysis requirements.
 Pharmacology and toxicology information
i. Pharmacology and drug disposition: describes the pharmacological effects and mechanism(s) of action
of the drug in animals, and information on the absorption, distribution, metabolism, and excretion of
the drug, if known.
ii. Toxicology. An integrated summary of the toxicological effects of the drug in animals and in vitro.
iii. Previous human experience with the investigational drug: A summary of previous human experience
known to the applicant, if any, with the investigational drug.
 Additional information.
Such information shall be submitted in this section as follows:
i. Drug dependence and abuse potential. If the drug is a psychotropic substance or otherwise has abuse
potential, a section describing relevant clinical and pre-clinical studies and experience
ii. Radioactive drugs. If the drug is a radioactive drug, sufficient data from animal or human studies to
allow a reasonable calculation of radiation-absorbed dose to the whole body and critical organs upon
administration to a human subject.
iii. Paediatric studies: Plans for assessing paediatric safety and effectiveness.
 Relevant information.
If requested by FDA, any other relevant information needed for review of the application eg:
i. Information previously submitted,
ii. Material in a foreign language,
iii. Number of copies,
iv. Numbering of IND submissions,
v. Identification of exception from informed consent.
 312.30 Protocol amendments.
 This section sets forth the provisions under which new protocols may be submitted and changes in
previously submitted protocols may be made.
 New protocol:
 Whenever a sponsor intends to conduct a study that is not covered by a protocol already contained in
the IND, the sponsor shall submit to FDA a protocol amendment containing the protocol for the study.
 Changes in a protocol:
 A sponsor shall submit a protocol amendment describing any change in a Phase 1 protocol that
significantly affects the safety of subjects or any change in a Phase 2 or 3 protocol that significantly
affects the safety of subjects, the scope of the investigation, or the scientific quality of the study.
 New investigator.
 A sponsor shall submit a protocol amendment when a new investigator is added to carry out a
previously submitted protocol, except that a protocol amendment is not required when a licensed
practitioner is added in the case of a treatment protocol
 312.31 Information amendments
 Requirement for information amendment.
 A sponsor shall report in an information amendment essential information on the IND that is not within
the scope of a protocol amendment:
i. IND safety reports, or annual report
ii. New toxicology, chemistry, or other technical information; or
iii. A report regarding the discontinuance of a clinical investigation.
 312.32 IND safety reporting.
 Definitions:
Life-threatening adverse event or life-threatening suspected adverse reaction, Serious adverse event or serious
suspected adverse reaction, Suspected adverse reaction, Unexpected adverse event or unexpected suspected
adverse reaction.
 Review of safety information.
 The sponsor must review all information relevant to the safety of the drug obtained
 IND safety reports.
 The sponsor must notify FDA and all participating investigators an IND safety report of potential
serious risks, from clinical trials or any other source in no case later than 15 calendar days after the
sponsor determines that the information qualifies for reporting.
 312.33 Annual reports.
 A sponsor shall within 60 days of the anniversary date that the IND went into effect, submit a brief
report of the progress of the investigation that includes:
A. Individual study information; The title of the study, The total number of subjects initially planned,
brief description of any available study results.
B. Summary information;
i. tabular summary showing the most frequent and most serious adverse experiences,
ii. summary of all IND safety reports,
iii. list of subjects who died, list of subjects who dropped out
iv. information about dose response
v. information from controlled trials
vi. information about bioavailability
vii. list of the preclinical studies, manufacturing or microbiological changes made, etc
 312.38 Withdrawal of an IND.
 At any time a sponsor may withdraw an effective IND without prejudice.
 If an IND is withdrawn, FDA shall be so notified, all clinical investigations conducted under the IND
shall be ended, all current investigators notified, and all stocks of the drug returned to the sponsor or
otherwise disposed of.
 If an IND is withdrawn because of a safety reason, the sponsor shall promptly so inform FDA, all
participating investigators, and all reviewing Institutional Review Boards, together with the reasons
for such withdrawal.
Subpart C - Administrative Actions:
 312.40 General requirements for use of an investigational new drug in a clinical investigation.
 An investigational new drug may be used in a clinical investigation if the following conditions are met:
i. The sponsor of the investigation submits an INDA for the drug to FDA,
ii. Each participating investigator conducts his or her investigation in compliance with the requirements.
 An IND goes into effect Thirty days after FDA receives the IND,
 A sponsor may ship an investigational new drug to investigators named in the IND Thirty days after
FDA receives the INDA
 An investigator may not administer an investigational new drug to human subjects until the INDA goes
into effect
 312.41 Comment and advice on an IND.
 FDA may communicate with the sponsor orally or in writing about deficiencies in the INDA or about
FDA's need for more data or information.
 Advice may be on the adequacy of technical data to support an investigational plan, on the design of a
clinical trial, etc.
 Unless the communication is accompanied by a clinical hold order under § 312.42, FDA
communications with a sponsor under this section are solely advisory.
 312.42 Clinical holds and requests for modification.
 A clinical hold is an order issued by FDA to the sponsor to delay a proposed clinical investigation or
to suspend an on-going investigation.
 Grounds for imposition of clinical hold:
i. Human subjects are or would be exposed to an unreasonable and significant risk of illness or injury,
ii. The clinical investigators named in the IND are not qualified
iii. The investigator brochure is misleading,
iv. The plan or protocol for the investigation is clearly deficient in design,
v. Insufficient quantities of the investigational drug exist
vi. The drug has received marketing approval
 Resumption of clinical investigations:
 An investigation may only resume after FDA has notified the sponsor.
 Resumption of the affected investigation(s) will be authorized when the sponsor corrects the
deficiency(ies) previously cited or otherwise satisfies the agency that the investigation(s) can proceed.
 If a sponsor of an IND that has been placed on clinical hold requests in writing that the clinical hold
be removed and submits a complete response to the issue(s) identified in the clinical hold order, FDA
shall respond in writing to the sponsor within 30-calendar days of receipt of the request and the
complete response.
 Appeal.
 If the sponsor disagrees with the reasons cited for the clinical hold, the sponsor may request
reconsideration.
 312.44 Termination.
 This section describes the procedures under which FDA may terminate an IND. If an IND is
terminated, the sponsor shall end all clinical investigations conducted under the IND.
 Grounds for termination:
i. Human subjects are or would be exposed to an unreasonable and significant risk of illness or injury,
ii. The INDA does not contain sufficient information,
iii. The methods, facilities, and controls used for the manufacturing, processing, and packing of the
investigational drug are inadequate to establish and maintain appropriate standards of identity,
strength, quality, and purity as needed for subject safety,
iv. The clinical investigations are being conducted substantially different than that in the protocols,
v. The drug is being promoted or distributed for commercial purposes,
vi. The IND, or any amendment or report to the IND, contains an untrue statement
vii. The IND has remained on inactive status for 5 years or more.
 Opportunity for sponsor response: If FDA proposes to terminate an IND, FDA will notify the sponsor
in writing, and invite correction or explanation within a period of 30 days.
 312.45 Inactive status.
 If no subjects are entered into clinical studies for a period of 2 years or more under an IND, or if all
investigations under an IND remain on clinical hold for 1 year or more, the IND may be placed by
FDA on inactive status.
 If an IND is placed on inactive status, all investigators shall be so notified and all stocks of the drug
shall be returned or otherwise disposed of.
 A sponsor is not required to submit annual reports to an IND on inactive status.
 A sponsor who intends to resume clinical investigation under an IND placed on inactive status shall
submit a protocol amendment. An IND that remains on inactive status for 5 years or more may be
terminated.
 312.47 Meetings.
 Meetings between a sponsor and the agency are encouraged by FDA as they aid in the evaluation of
the drug
 "End-of-Phase 2" meetings and meetings held before submission of a marketing application:
 Meetings between FDA and a sponsor can be especially helpful in minimizing wasteful expenditures
of time and money and thus in speeding the drug development and evaluation process
 The purpose to determine the safety of proceeding to Phase 3, to evaluate the Phase 3 plan and
protocols.
 At least 1 month in advance of an end-of-Phase 2 meeting, the sponsor should submit background
information on the sponsor's plan for Phase 3. This includes:
i. summaries of the Phase 1 and 2 investigations
ii. the specific protocols for Phase 3 clinical studies
iii. plans for any additional nonclinical studies
iv. plans for paediatric studies
v. time line for protocol finalization, enrolment, completion, and data analysis
vi. information to support any planned request for waiver or deferral of paediatric studies
vii. tentative labelling for the drug.
 Arrangements for an end-of-Phase 2 meeting are to be made with the division in FDA's which is
responsible for review of the IND.
 "Pre-NDA" and "pre-BLA" meetings:
 The primary purpose of this kind of exchange is:
i. to uncover any major unresolved problems
ii. to identify those studies that the sponsor is relying on as adequate and well-controlled to establish the
drug's effectiveness
iii. to identify the status of on-going or needed studies adequate to assess paediatric safety and
effectiveness
iv. to acquaint FDA reviewers with the general information to be submitted in the marketing application
(including technical information)
v. to discuss appropriate methods for statistical analysis of the data
vi. to discuss the best approach to the presentation and formatting of data in the marketing application.
 312.48 Dispute resolution.
 The Food and Drug Administration is committed to resolving differences between sponsors and FDA
reviewing divisions with respect to requirements for IND.
 Administrative and procedural issues:
 When administrative or procedural disputes arise, the sponsor should first attempt to resolve the matter
with the division in FDA which is responsible for review of the IND.
 If the dispute is not resolved, the sponsor may raise the matter with the person designated as
ombudsman, whose function shall be to investigate what has happened and to facilitate a timely and
equitable resolution.
 Scientific and medical disputes:
 When scientific or medical disputes arise during the drug investigation process, sponsors should
discuss the matter directly with the responsible reviewing officials.
 The "end-of-Phase 2" and "pre-NDA" meetings will also provide a timely forum for discussing and
resolving scientific and medical issues.
Subpart D - Responsibilities of Sponsors and Investigators
 312.50 General responsibilities of sponsors.
 Sponsors are responsible for:
i. selecting qualified investigators, providing them with the information they need to conduct an
investigation properly,
ii. ensuring proper monitoring of the investigation(s) and that the investigation(s) is conducted in
accordance with the general investigational plan and protocols contained in the IND
iii. maintaining an effective IND with respect to the investigations
iv. ensuring that FDA and all participating investigators are promptly informed of significant new adverse
effects or risks with respect to the drug.
 312.52 Transfer of obligations to a contract research organization
 A sponsor may transfer responsibility for any or all of the obligations set forth in this part to a CRO.
 Any such transfer shall be described in writing.
 A contract research organization that assumes any obligation of a sponsor shall comply with the
specific regulations and shall be subject to the same regulatory action as a sponsor
 312.53 Selecting investigators and monitors.
 A sponsor shall select only investigators qualified by training and experience as appropriate experts to
investigate the drug.
 A sponsor shall ship investigational new drugs only to investigators.
 Before permitting an investigator to begin participation in an investigation, the sponsor shall obtain the
following:
(A) A signed investigator statement (Form FDA-1572) containing:
i. The name and address of the investigator,
ii. The name and code number, if any, of the protocol(s),
iii. The name and address of facility where the clinical investigation(s) will be conducted,
iv. The name and address of the IRB,
v. A commitment bythe investigator that they will comply with all requirements regarding the obligations
of clinical investigators
(B) A curriculum vitae or other statement of qualifications of the investigator
(C) Clinical protocol:
i. For Phase 1 investigations, a general outline of the planned investigation including the estimated
duration of the study and the maximum number of subjects
ii. For Phase 2 or 3 investigations, an outline of the study protocol
iii. copies or a description of case report forms to be used.
(D) Financial disclosure information
 312.54 Emergency research under 50.24 of this chapter.
 The sponsor shall monitor the progress of all investigations involving an exception from informed
consent under § 50.24 of this chapter.
 When the sponsor receives from the IRB information concerning the public disclosures required by §
50.24(a)(7)(ii) and (a)(7)(iii) of this chapter, the sponsor promptly shall submit to the IND file.
 The sponsor also shall monitor such investigations to identify when an IRB determines that it cannot
approve the research because it does not meet the criteria in the exception in § 50.24(a) of this chapter
or because of other relevant ethical concerns.
 312.55 Informing investigators.
 Before the investigation begins, a sponsor (other than a sponsor-investigator) shall give each
participating clinical investigator an investigator brochure.
 The sponsor shall keep investigator informed of new observations discovered by or reported to the
sponsor on the drug, particularly with respect to adverse effects and safe use.
 312.56 Review of ongoing investigations.
 The sponsor shall monitor the progress of all clinical investigations being conducted under its IND.
 A sponsor who discovers that an investigator is not complying with the signed agreement (Form FDA-
1572), the general investigational plan, or the requirements of this part or other applicable parts shall
promptly either secure compliance or discontinue shipments of the investigational new drug to the
investigator and end the investigator's participation.
 The sponsor shall review and evaluate the evidence relating to the safety and effectiveness of the drug.
 A sponsor who determines that its investigational drug presents an unreasonable and significant risk
to subjects shall discontinue those investigations
 312.57 Recordkeeping and record retention.
 A sponsor shall maintain adequate records showing the receipt, shipment, or other disposition of the
investigational drug.
 A sponsor shall also maintain complete and accurate records concerning all other financial interests of
investigators.
 A sponsor shall retain the records and reports required by this part for 2 years after a marketing
application is approved.
 A sponsor shall retain reserve samples of any test article and reference standard.
 312.58 Inspection of sponsor's records and reports.
 FDA inspection.
 A sponsor shall upon request from any properly authorized officer or employee of the FDA permit
such officer or employee to have access to and copy and verify any records and reports relating to a
clinical investigation.
 Controlled substances.
 If an investigational new drug is a substance listed in any schedule of the Controlled Substances Act,
records concerning shipment, delivery, receipt, and disposition of the drug, which are required to be
kept shall, upon the request of a properly authorized employee be made available by the investigator
or sponsor to whom the request is made, for inspection and copying.
 312.59 Disposition of unused supply of investigational drug.
 The sponsor shall assure the return of all unused supplies of the investigational drug from each
individual investigator whose participation in the investigation is discontinued or terminated.
 312.60 General responsibilities of investigators.
 An investigator is responsible for:
i. ensuring that an investigation is conducted according to the signed investigator statement
ii. the investigational plan, and applicable regulations
iii. for protecting the rights, safety, and welfare of subjects under the investigator's care
iv. for the control of drugs under investigation
 An investigator shall obtain the informed consent of each human subject to whom the drug is
administered.
 312.61 Control of the investigational drug.
 An investigator shall administer the drug only to subjects under the investigator's personal supervision or
under the supervision of a sub-investigator responsible to the investigator.
 The investigator shall not supply the investigational drug to any person not authorized under this part to
receive it.
 312.62 Investigator recordkeeping and record retention.
 An investigator is required to maintain adequate records of the disposition of the drug, including dates,
quantity, and use by subjects.
 An investigator is required to prepare and maintain adequate and accurate case histories that record all
observations and other data pertinent to the investigation on each individual.
 An investigator shall retain records required to be maintained under this part for a period of 2 years
following the date a marketing application is approved.
 312.64 Investigator reports.
 The investigator shall furnish all reports to the sponsor of the drug who is responsible for collecting
and evaluating the results obtained.
 An investigator must immediately report to the sponsor any serious adverse event, whether or not
considered drug related, including those listed in the protocol or investigator brochure.
 An investigator shall also provide the sponsor with an adequate report shortly after completion of the
investigator's participation.
 The clinical investigator shall provide the sponsor with sufficient accurate financial information to
allow an applicant to submit complete and accurate certification or disclosure statements.
 312.66 Assurance of IRB review.
 An investigator shall assure that an IRB will be responsible for the initial and continuing review and
approval of the proposed clinical study.
 The investigator shall promptly report to the IRB all changes in the research activity.
 312.68 Inspection of investigator's records and reports.
 An investigator shall upon request from FDA permit such officer or employee to have access to, and
copy and verify any records or reports made by the investigator
 312.69 Handling of controlled substances.
 If the investigational drug is subject to the Controlled Substances Act, the investigator shall take
adequate precautions, including storage of the investigational drug in a securely locked, substantially
constructed cabinet, or other securely locked, substantially constructed enclosure, access to which is
limited, to prevent theft or diversion of the substance into illegal channels of distribution.
 312.62 Investigator recordkeeping and record retention.
 An investigator is required to maintain adequate records of the disposition of the drug, including dates,
quantity, and use by subjects.
 An investigator is required to prepare and maintain adequate and accurate case histories that record all
observations and other data pertinent to the investigation on each individual.
 An investigator shall retain records required to be maintained under this part for a period of 2 years
following the date a marketing application is approved.
 312.64 Investigator reports.
 The investigator shall furnish all reports to the sponsor of the drug who is responsible for collecting
and evaluating the results obtained.
 An investigator must immediately report to the sponsor any serious adverse event, whether or not
considered drug related, including those listed in the protocol or investigator brochure.
 An investigator shall also provide the sponsor with an adequate report shortly after completion of the
investigator's participation.
 The clinical investigator shall provide the sponsor with sufficient accurate financial information to
allow an applicant to submit complete and accurate certification or disclosure statements.
 312.66 Assurance of IRB review.
 An investigator shall assure that an IRB will be responsible for the initial and continuing review and
approval of the proposed clinical study.
 The investigator shall promptly report to the IRB all changes in the research activity.
 312.68 Inspection of investigator's records and reports.
 An investigator shall upon request from FDA permit such officer or employee to have access to, and
copy and verify any records or reports made by the investigator
 312.69 Handling of controlled substances.
 If the investigational drug is subject to the Controlled Substances Act, the investigator shall take
adequate precautions, including storage of the investigational drug in a securely locked, substantially
constructed cabinet, or other securely locked, substantially constructed enclosure, access to which is
limited, to prevent theft or diversion of the substance into illegal channels of distribution.
 312.70 Disqualification of a clinical investigator.
 If FDA has information indicating that an investigator (including a sponsor-investigator) has
repeatedly or deliberately failed to comply with the requirements, or has repeatedly or deliberately
submitted to FDA or to the sponsor false information in any required report the Center for Drug
Evaluation and Research or the Center for Biologics Evaluation and Research will furnish the
investigator written notice of the matter complained of and offer the investigator an opportunity to
explain the matter in writing.
 After evaluating all available information, including any explanation presented by the investigator, if
the Commissioner determines that the investigator has repeatedly or deliberately failed to comply with
the requirements the Commissioner will notify the investigator, the sponsor of any investigation in
which the investigator has been named as a participant, and the reviewing institutional review boards
(IRBs) that the investigator is not eligible to receive test articles.
Subpart E - Drugs Intended to Treat Life-threatening and Severely-debilitating Illnesses
 312.80 Purpose.
 The purpose of this section is to establish procedures designed to expedite the development, evaluation,
and marketing of new therapies, especially where no satisfactory alternative therapy exists.
 312.81 Scope.
 This section applies to new drug and biological products that are being studied for their safety and
effectiveness in treating life-threatening or severely-debilitating diseases.
 Term "life-threatening" means Diseases or conditions where the likelihood of death is high.
 Term "severely debilitating" means diseases or conditions that cause major irreversible morbidity.
 312.82 Early consultation.
 For products intended to treat life-threatening or severely-debilitating illnesses, sponsors may request
to meet with FDA-reviewing officials early in the drug development process.
 Pre-investigational new drug (IND) meetings.
 Prior to the submission of the initial IND, the sponsor may request a meeting with FDA-reviewing
officials.
 The meeting is to review and reach agreement on the design of animal studies needed to initiate human
testing.
 End-of-phase 1 meetings.
 When data from phase 1 clinical testing are available, the sponsor may again request a meeting with
FDA-reviewing officials.
 The meeting is to review and reach agreement on the design of phase 2 controlled clinical trials, with
the goal that such testing will be adequate to provide sufficient data on the drug's safety and
effectiveness to support a decision on its approvability for marketing.
 312.83 Treatment protocols.
 If the preliminary analysis of phase 2 test results appears promising, FDA may ask the sponsor to
submit a treatment protocol to be reviewed
 312.84 Risk-benefit analysis in review of marketing applications for drugs to treat life-
threatening and severely-debilitating illnesses.
 FDA's application of the statutory standards for marketing approval shall recognize the need for a
medical risk-benefit judgment in making the final decision on approvability.
 In making decisions on whether to grant marketing approval for products that have been the subject of
an end-of-phase 1 meeting, FDA will usually seek the advice of outside expert scientific consultants
or advisory committees.
 If FDA concludes that the data presented are not sufficient for marketing approval, FDA will issue a
complete response letter.
 312.85 Phase 4 studies.
 Concurrent with marketing approval, FDA may seek agreement from the sponsor to conduct certain
post-marketing (phase 4) studies to delineate additional information about the drug's risks, benefits,
and optimal use.
 These studies could include:
i. studying different doses or schedules of administration than were used in phase 2 studies
ii. use of the drug in other patient populations or other stages of the disease
iii. use of the drug over a longer period of time.
 312.86 Focused FDA regulatory research.
 FDA may undertake focused regulatory research on critical rate-limiting aspects of the preclinical,
chemical/manufacturing, and clinical phases of drug development and evaluation.
 When initiated, FDA will undertake such research efforts as a means for meeting a public health need
in facilitating the development of therapies to treat life-threatening or severely debilitating illnesses.
 312.87 Active monitoring of conduct and evaluation of clinical trials.
 The Commissioner and other agency officials will monitor the progress of the conduct and evaluation
of clinical trials and be involved in facilitating their appropriate progress.
 312.88 Safeguards for patient safety.
 All of the safeguards incorporated are designed to ensure:
i. the safety of clinical testing and the safety of products following marketing approval.
ii. review of animal studies prior to initial human testing
iii. monitoring of adverse drug experiences through the requirements of IND safety reports
iv. safety update reports during agency review of a marketing application and post-marketing adverse
reaction reporting
Subpart F – Miscellaneous
 312.110 Import and export requirements.
 An investigational new drug offered for import into the United States complies with the requirements
if:
i. The consignee in the United States is the sponsor of the IND
ii. the consignee is a qualified investigator named in the IND
iii. the consignee is the domestic agent of a foreign sponsor, is responsible for the control and distribution
of the IND.
 Exports:
 An investigational new drug may be exported from the United States for use in a clinical investigation
under any of the following conditions:
i. An IND is in effect with the laws of the country to which it is being exported
ii. The drug is manufactured, processed, packaged, and held in substantial conformity with current good
manufacturing practices
iii. The drug does not present an imminent hazard to public health
 There may be instances where exportation of an investigational new drug is needed so that the drug
may be stockpiled and made available for use by the importing country if and when a national
emergency arises.
 Exportation may not proceed until FDA has authorized exportation of the investigational new drug.
 312.120 Foreign clinical studies not conducted under an IND.
 FDA will accept as support for an IND or application for marketing approval a well-designed and well-
conducted foreign clinical study not conducted under an IND, if the following conditions are met:
i. The study was conducted in accordance with good clinical practice (GCP)
ii. FDA is able to validate the data from the study through an onsite inspection.
 312.130 Availability for public disclosure of data and information in an IND.
 The existence of an investigational new drug application will not be disclosed by FDA unless it has
previously been publicly disclosed or acknowledged.
 The availability for public disclosure of all data and information in an INDA for a new drug will be
handled in accordance with the provisions for the confidentiality of data and information in
applications submitted in part 314.
 312.140 Address for correspondence.
 A sponsor must send an initial IND submission to the Center for Drug Evaluation and Research
(CDER) or to the Center for Biologics Evaluation and Research (CBER)
 312.145 Guidance documents.
 FDA has made available guidance documents under § 10.115 of this chapter to help you to comply
with certain requirements of this part.
 The Center for Drug Evaluation and Research (CDER) and the Center for Biologics Evaluation and
Research (CBER) maintain lists of guidance documents that apply to the centers' regulations.
 The lists are maintained on the Internet and are published annually in the Federal Register.
Subpart G - Drugs for Investigational Use in Laboratory Research Animals or In Vitro Tests
 312.160 Drugs for investigational use in laboratory research animals or in vitro tests.
 A person may ship a drug intended solely for tests in vitro or in animals used only for laboratory
research purposes if it is labelled as; ‘CAUTION: Contains a new drug for investigational use only in
laboratory research animals, or for tests in vitro. Not for use in humans’ and a biological product for
investigational in vitro diagnostic use as; ‘CAUTION: Contains a biological product for
investigational in vitro diagnostic tests only.’
 A person who ships a drug shall maintain adequate records showing the name and post office address
of the expert to whom the drug is shipped and the date, quantity, and batch or code mark of each
shipment and delivery.
 FDA may terminate authorization to ship a drug if; investigation has failed to comply with any of the
conditions or continuance of the investigation is unsafe
Subpart-H [Reserved]
Subpart I - Expanded Access to Investigational Drugs for Treatment Use
 312.300 General.
 This subpart contains the requirements for the use of investigational new drugs and approved drugs
where availability is limited.
 The aim is to facilitate the availability of such drugs to patients with serious diseases or conditions
when there is no comparable or satisfactory alternative therapy to diagnose, monitor, or treat the
patient's disease or condition.
 The following definitions of terms apply to this subpart:
i. Immediately life-threatening disease or condition means a stage of disease in which there is reasonable
likelihood that death will occur
ii. Serious disease or condition means a disease or condition associated with morbidity that has
substantial impact on day-to-day functioning.
 312.305 Requirements for all expanded access uses.
 The criteria, submission requirements, safeguards, and beginning treatment information set out in this
section apply to all expanded access uses described in this subpart.
 Criteria:
i. The patient or patients to be treated have a serious or immediately life-threatening disease or condition
ii. The potential patient benefit justifies the potential risks
iii. Providing the investigational drug for the requested use will not interfere with the initiation, conduct,
or completion of clinical investigations that could support marketing approval.
 An expanded access submission is required for each type of expanded access described in this subpart.
The submission may be a new IND or a protocol amendment to an existing IND.
 312.310 Individual patients, including for emergency use.
 FDA may permit an investigational drug to be used for the treatment of an individual patient by a
licensed physician.
 The physician must determine that the probable risk to the person from the investigational drug is not
greater than the probable risk from the disease or condition.
 If there is an emergency that requires the patient to be treated before a written submission can be made,
FDA may authorize the expanded access use to begin without a written submission.
 312.315 Intermediate-size patient populations.
 FDA may permit an investigational drug to be used for the treatment of a patient population.
 FDA may ask a sponsor to consolidate expanded access under this section when the agency has
received a significant number of requests for individual patient expanded access to an investigational
drug for the same use.
 Need for expanded access:
i. The drug is not being developed, for example, because the disease or condition is so rare that the
sponsor is unable to recruit patients
ii. The drug is being studied in a clinical trial, but patients requesting the drug for expanded access use
are unable to participate in the trial
iii. The drug is an approved drug product that is no longer marketed for safety reasons.
 Criteria:
i. There is enough evidence that the drug is safe
ii. There is at least preliminary clinical evidence of effectiveness
 Submission:
i. The expanded access submission must state whether the drug is being developed or not
ii. If the drug is being studied in a clinical trial
 Safeguards:
 Upon review of the IND annual report, FDA will determine whether it is appropriate for the expanded
access
 312.320 Treatment IND or treatment protocol.
 FDA may permit an investigational drug to be used for widespread treatment use.
 Criteria
i. The drug is being investigated in a controlled clinical trial under an IND designed to support a
marketing application
ii. All clinical trials of the drug have been completed
iii. When the expanded access use is for a serious disease or condition, there is sufficient clinical evidence
of safety and effectiveness to support the expanded access use.
iv. Submission.
v. The expanded access submission must include information adequate to satisfy FDA
vi. Safeguard.
vii. The sponsor is responsible for monitoring the treatment protocol to ensure that licensed physicians
comply with the protocol and the regulations applicable to investigators.
ANDA 505 (j) FD & c act
 An abbreviate new drug application (ANDA) contain data which when submitted to FDA’s , CDER office
of generics drugs , provide for the review and ultimate approval of a generic drug product .
 Once approved , an applicant may manufacture and market the generic drug product to provide a safe ,
effective , low cost alternative to the public .
 All approved products , innovator and generic , are listed in FDA’s approved drug with therapeutic
equivalence evaluation (orange book).
 It termed “abbreviate ’’ because they generally not required to include preclinical study and clinical study
to establish safety and effectiveness.
 Generic drug application are termed as “abbreviated ’’.
GOAL of ANDA
 To reduce the price of the drug
 To reduce the time development
 Increase the bioavailability of the drug in comparison to the reference list drug
Basic generic drug requirements are :
 Same active ingredients
 Same route of administration
 Same dosage form
 Same strength
 Same condition of use
 Inactive ingredients are approved in a similar NDA
INNOVATOR VS GENERIC:
Generic drug approval:
INDISPENSABILITY ground for Generics:
 Contain the same active ingredient as the innovator drug ( inactive ingredient may vary).
 Must be identical in strength ,dosage form, and route of administration .
 Must have same use and indication .
 Must be bioequivalent .
 Must have same batch requirement for identity , safety and purity.
 Must follow strict standard of FDA’s GMP .
Hatch Waxman Act:
 Commonly known as “Drug Price Competition & patent term Restoration Act ’’ of 1948.
 It is an act dealing with the approval of generic drug and associated conditions for getting their approval
from FDA ,marketing exclusively , rights of exclusivity, patent term extension and orange book listing .
 Required by :
1. Absence of generic drug manufacturing
2. Un manageable regulatory procedures
3. Patient were denied the option of the cheaper drug
Recent addition of Hatch Waxman Act:
Under the “Medicare prescription drug and modernization act’’ ,2003 :
 Non extension of the 30 month period
 Time limit for informing patent owner
 Provision for allowing declaratory judgement
 Benefits of exclusively for several ANDASs filled on same day allowed
Objectives of the act :
 Reduce the cost associated with approval of generic drug.
 Allowing the early experimental use.
 Compensating the branded drug manufactures for the time lost from the patent term because of the
regulatory approval formality.
 Motivating the generic drug manufactures.
Format of ANDA
1. Application form :
 The application shall submit a complete and signed application form .
2. Table of content :
 The archival copy of ANDA application is required to contain a table of content that shows the volume
number and page number of the content of the submission .
3. Basis of ANDA submission :
 Name of reference drug its dosage form and strength.
 For an ANDA application , a reference to FDA assigned docket number for the petition and a copy of
FDA’s correspondence approving the petition .
4. Condition of use :
 A statement that the condition of use prescribe , recommended or suggested in the labelling proposed for
the drug product that have been previously approved for the reference listed drug .
5. Active ingredient :
 A statement that active ingredient is same as that of reference listed drugs and for the combination product
this must be shown for both the active ingredient .
6. Route of administration, dosage form and strength :
 A statement that route of administration , Dosage form and strength is same as the reference listed drug .
 If the route of administration , Dosage form and strength is different from the reference listed drug then
the ANDA should contain information about all that the FDA may require .
7. Bioequivalence :
 Information that shows drug product is bioequivalent to the reference listed drug upon which the applicant
relies .
 A complete study report must be submitted to for the bioequivalence study upon which the applicant can
relies for approval.
8. Labelling :
 A copy for labelling reference listed drug .
 Copies for proposed labelling for the new drug product .
 Statement on the proposed labelling .
9. Chemistry , manufacturing and controls :
 The information require shall contain the proposed or actual MFR including a description of the equipment
to be used for manufacturing of a commercial lot of the drug product .
10. Samples :
 Sample need not to be submitted until requested by FDA .
Patent certification :
Module in a CTD:
MODULE I: Administrative and Prescribing Information
1.Table of Contents
2.Includes data of Administrative Documents entailing
 Patent Information on patented product.
 Patent Certifications.
 Debarment certification
3. Prescribing information like Package and container labels, packaging inserts, patient leaflets etc
4. Labelling Comparison between Innovator and Generic drug.
MODULE II: SUMMARIES AND OVERVIEWS
1. Table of Content
2. Introduction to Summary Documents
3. Overviews and Summaries: Module II should contain documents like:
 M4Q: The CTD- quality
 M4S: The CTD- safety
 M4E: The CTD- efficacy
MODULE Ill: information on product quality
1.Table of Content
2. Body of Data
3.Literature Reference
MODULE IV: NON CLINICAL STUDY REPORTS
 Not required in ANDA Filing
MODULE V: CLINICAL STUDY REPORTS
1. Table of Contents
2. Study Reports including Case Report Forms and Case Report Tabulations
Information required of ANDA:
 Products information
 Manufacturers procedure
 Control procedure
 Testing
 Facilities
 Dissolution profile
 Labelling
Recommendation for E –c t d:
1. PDF file with version 3.0 of Acrobat reader .
2. Use of embedded fonts in the portable document format .
3. A print area of 8.5 inches by 11 inches and margin of 1 inches is ensured on side.
4. Scanned documents should be avoided as a source document .
5. Hypertext can be indicated by blue –text or by rectangles using thin lines.
6. Numbering on the PDF and document should be included as same .
7. Security or password should not be included .
8. Full indexes should be included.
9. Electronic signature may be added , procedures are being employed for archival of the same .
Patent challenge successfully – award of 180 – days exclusivity period
 Awarded to first ANDA holder to file a complete application with patent challenge .
 Protection from other generic competition – blocks approval of subsequent ANDAs
 Protection triggered by :
First commercial marketing
Forfeiture provision
CFR 21 PART 50 (PROTECTION OF HUMAN SUBJECTS)
 Subpart A General Provisions
§ 50.1 Scope
§ 50.3 Definitions
 Subpart B Informed Consent of Human Subjects
§ 50.20 General requirements for informed consent
§ 50.23 Exception from general requirements
§ 50.24 Exception from informed consent requirements for emergency research
§ 50.25 Elements of informed consent
§ 50.27 Documentation of informed consent
 Subpart C Reserved
 Subpart D Additional Safeguards for Children in Clinical Investigations
§ 50.50 IRB duties
§ 50.51 Clinical investigations not involving greater than minimal risk
§ 50.52 Clinical investigations involving greater than minimal risk but presenting the prospect of direct
benefit to individual subjects
§ 50.53 Clinical investigations involving greater than minimal risk and no prospect of direct benefit to
individual subjects, but likely to yield generalizable knowledge about the subjects' disorder or condition.
§ 50.54 Clinical investigations not otherwise approvable that present an opportunity to understand,
prevent, or alleviate a serious problem affecting the health or welfare of children
§ 50.55 Requirements for permission by parents or guardians and for assent by children
§ 50.56 Wards
Subpart A General Provisions:
§ 50.1 Scope:
 This part applies to all clinical investigations regulated by the Food and Drug Administration under
sections 505(i) and 520(g) of the Federal Food, Drug, and Cosmetic Act, as well as clinical
investigations that support applications for research or marketing permits for products regulated by the
Food and Drug Administration, including foods, including dietary supplements, that bear a nutrient
content claim or a health claim, infant formulas, food and colour additives, drugs for human use,
medical devices for human use, biological products for human use, and electronic products. Additional
specific obligations and commitments of, and standards of conduct for, persons who sponsor or
monitor clinical investigations involving particular test articles may also be found in other parts (e.g.,
parts 312 and 812).
 Compliance with these parts is intended to protect the rights and safety of subjects involved in
investigations filed with the Food and Drug Administration pursuant to sections 403, 406, 409, 412,
413, 502, 503, 505, 510, 513-516, 518-520, 721, and 801 of the Federal Food, Drug, and Cosmetic Act
and sections 351 and 354-360F of the Public Health Service Act.
 References in this part to regulatory sections of the Code of Federal Regulations are to chapter I of title
21, unless otherwise noted.
§ 50.3 Definitions
 Act:
The Federal Food, Drug, and Cosmetic Act.
 Clinical Investigation:
Any experiment that involves a test article and one or more human subjects and that either is subject to
requirements for prior submission to the Food and Drug Administration under section 505(i) or 520(g) of the
act, or is not subject to requirements for prior submission to the Food and Drug Administration under these
sections of the act, but the results of which are intended to be submitted later to, or held for inspection by, the
Food and Drug Administration as part of an application for a research or marketing permit. The term does not
include experiments that are subject to the provisions of part 58 of this chapter, regarding nonclinical
laboratory studies.
 Human Subject:
An individual who is or becomes a participant in research, either as a recipient of the test article
or as a control. A subject may be either a healthy human or a patient.
 Institutional Review Board (IRB):
Any board, committee, or other group formally designated by an institution to review biomedical
research involving humans as subjects, to approve the initiation of and conduct periodic review of such
research.
Subpart B Informed Consent of Human Subjects:
§ 50.20 General Requirements for Informed Consent
 Except as provided in § 50.23 and § 50.24, no investigator may involve a human being as a subject in
research covered by these regulations unless the investigator has obtained the legally effective
informed consent of the subject or the subject's legally authorized representative.
 An investigator shall seek such consent only under circumstances that provide the prospective subject
or the representative sufficient opportunity to consider whether or not to participate and that minimize
the possibility of coercion or undue influence. The information that is given to the subject or the
representative shall be in language understandable to the subject or the representative.
 No informed consent, whether oral or written, may include any exculpatory language through which
the subject or the representative is made to waive or appear to waive any of the subject's legal rights,
or releases or appears to release the investigator, the sponsor, the institution, or its agents from liability
for negligence.
§ 50.23 Exception from general requirements
 The obtaining of informed consent shall be deemed feasible unless, before use of the test article both
the investigator and a physician who is not otherwise participating in the clinical investigation certify
in writing all of the following:
i. The human subject is confronted by a life-threatening situation necessitating the use of the test
article.
ii. Informed consent cannot be obtained from the subject because of an inability to communicate
with, or obtain legally effective consent from, the subject.
iii. Time is not sufficient to obtain consent from the subject's legal representative.
iv. There is available no alternative method of approved or generally recognized therapy that
provides an equal or greater likelihood of saving the life of the subject.
 The documentation required in this section shall be submitted to the IRB within 5 working days after
the use of the test article.
 The extent and strength of evidence of the safety and effectiveness of the investigational new drug in
relation to the medical risk that could be encountered during the military operation supports the drug's
administration under an IND.
 A duly constituted institutional review board (IRB) established and operated in accordance with the
requirements of this section, responsible for review of the study, has reviewed and approved the
investigational new drug protocol and the administration of the investigational new drug without
informed consent.
 Department of Défense (DOD) request is to include the documentation required by § 56.115(a)(2) of
this chapter
 DOD has explained:
I. The context in which the investigational drug will be administered, e.g., the setting or whether it
will be self-administered or it will be administered by a health professional.
II. The nature of the disease or condition for which the preventive or therapeutic treatment is intended.
III. To the extent there are existing data or information available, information on conditions that could
alter the effects of the investigational drug.
 DOD's recordkeeping system is capable of tracking and will be used to track the proposed treatment
from supplier to the individual recipient.
 Medical records of members involved in the military operation will accurately document the receipt
by members of any investigational new drugs in accordance with FDA regulations including part 312
of this chapter.
 DOD is pursuing drug development, including a time line, and marketing approval with due diligence.
 FDA has concluded that the investigational new drug protocol may proceed subject to a decision by
the President on the informed consent waiver request.
 The duly constituted institutional review board, described of this section, must include at least 3 non-
affiliated members who shall not be employees or officers of the Federal Government (other than for
purposes of membership on the IRB) and shall be required to obtain any necessary security clearances.
 The duly constituted institutional review board, described of this section, must review and approve:
I. The required information sheet.
II. The adequacy of the plan to disseminate information, including distribution of the information
sheet to potential recipients, on the investigational product (e.g., in forms other than written).
 DOD is to submit to FDA summaries of institutional review board meetings at which the proposed
protocol has been reviewed.
 Nothing in these criteria or standards is intended to preempt or limit FDA's and DOD's authority or
obligations under applicable statutes and regulations.
 Obtaining informed consent for investigational in vitro diagnostic devices used to identify chemical,
biological, radiological, or nuclear agents will be deemed feasible unless, before use of the test article,
both the investigator (e.g., clinical laboratory director or other responsible individual) and a physician
who is not otherwise participating in the clinical investigation make the determinations and later certify
in writing all of the following:
I. The human subject is confronted by a life-threatening situation necessitating the use of the
investigational in vitro diagnostic device to identify a chemical, biological, radiological, or
nuclear agent that would suggest a terrorism event or other public health emergency.
II. There was no reasonable way for the person directing that the specimen be collected to know,
at the time the specimen was collected, that there would be a need to use the investigational in
vitro diagnostic device on that subject's specimen.
III. Time is not sufficient to obtain consent from the subject's legally authorized representative.
 The investigator must submit the written certification of the determinations made by the investigator
and an independent physician required in paragraph of this section to the IRB and FDA within 5
working days after the use of the device.
 An investigator must disclose the investigational status of the in vitro diagnostic device and what is
known about the performance characteristics of the device in the report to the subject's health care
provider and in any report to public health authorities.
 No State or political subdivision of a State may establish or continue in effect any law, rule, regulation
or other requirement that informed consent be obtained before an investigational in vitro diagnostic
device may be used to identify chemical, biological, radiological, or nuclear agent in suspected
terrorism events and other potential public health emergencies that is different from, or in addition to,
the requirements of this regulation.
§ 50.24 Exception from informed consent requirements for emergency research.
 The IRB responsible for the review, approval, and continuing review of the clinical investigation
described in this section may approve that investigation without requiring that informed consent of all
research subjects be obtained if the IRB finds and documents each of the following:
I. The human subjects are in a life-threatening situation, available treatments are unproven or
unsatisfactory, and the collection of valid scientific evidence, which may include evidence obtained
through randomized placebo-controlled investigations, is necessary to determine the safety and
effectiveness of particular interventions.
II. The clinical investigation could not practicably be carried out without the waiver.
III. The investigator will summarize efforts made to contact legally authorized representatives and make
this information available to the IRB at the time of continuing review.
IV. The IRB has reviewed and approved informed consent procedures and an informed consent document
consistent with § 50.25.
V. Additional protections of the rights and welfare of the subjects will be provided.
 The IRB is responsible for ensuring that procedures are in place to inform, at the earliest feasible
opportunity, each subject, or if the subject remains incapacitated, a legally authorized representative
of the subject, or if such a representative is not reasonably available, a family member, of the subject's
inclusion in the clinical investigation, the details of the investigation and other information contained
in the informed consent document.
 The IRB determinations required by this section and the documentation required by this section are to
be retained by the IRB for at least 3 years after completion of the clinical investigation, and the records
shall be accessible for inspection and copying by FDA in accordance with § 56.115(b) of this chapter.
 Protocols involving an exception to the informed consent requirement under this section must be
performed under a separate investigational new drug application (IND) or investigational device
exemption (IDE) that clearly identifies such protocols as protocols that may include subjects who are
unable to consent.
 If an IRB determines that it cannot approve a clinical investigation because the investigation does not
meet the criteria in the exception provided under because of other relevant ethical concerns, the IRB
must document its findings and provide these findings promptly in writing to the clinical investigator
and to the sponsor of the clinical investigation.
 The sponsor of the clinical investigation must promptly disclose this information to FDA.
§ 50.25 Elements of informed consent.
 Basic elements of informed consent. In seeking informed consent, the following information shall be
provided to each subject:
I. A statement that the study involves research, an explanation of the purposes of the research and the
expected duration of the subject's participation, a description of the procedures to be followed, and
identification of any procedures which are experimental.
II. A description of any benefits to the subject or to others which may reasonably be expected from the
research.
III. A disclosure of appropriate alternative procedures or courses of treatment, if any, that might be
advantageous to the subject.
 Additional elements of informed consent. When appropriate, one or more of the following elements of
information shall also be provided to each subject:
I. A statement that the particular treatment or procedure may involve risks to the subject which are
currently unforeseeable.
II. Anticipated circumstances under which the subject's participation may be terminated by the
investigator without regard to the subject's consent.
III. Any additional costs to the subject that may result from participation in the research.
IV. The approximate number of subjects involved in the study.
§ 50.27 Documentation of informed consent
 Except as provided in § 56.109(c), informed consent shall be documented are approved by the IRB
and signed and dated by the subject or the subject's legally authorize representative at the time of
consent. A copy shall be given to the person signing the form.
 Except as provided in § 56.109(c), the consent form may be either of the following:
I. A written consent document that embodies the elements of informed consent required by § 50.25. This
form may be read to the subject or the subject's legally authorized representative.

II. A short form written consent document stating that the elements of informed consent required by §
50.25 have been presented orally to the subject or the subject's legally authorized representative. Also,
the IRB shall approve a written summary of what is to be said to the subject or the representative. A
copy of the summary shall be given to the subject or the representative in addition to a copy of the
short form.
Subpart D Additional Safeguards for Children in Clinical Investigations:
§ 50.50 IRB duties
 In addition to other responsibilities assigned to IRBs under this part and part 56 of this chapter, each
IRB must review clinical investigations involving children as subjects covered by this subpart D and
approve only those clinical investigations that satisfy the criteria described in § 50.51, § 50.52, or §
50.53 and the conditions of all other applicable sections of this subpart D.
§ 50.51 Clinical investigations not involving greater than minimal risk
 Any clinical investigation within the scope described in §§ 50.1 and 56.101 of this chapter in which
no greater than minimal risk to children is presented may involve children as subjects only if the IRB
finds that:
I. No greater than minimal risk to children is presented.
II. Adequate provisions are made for soliciting the assent of the children and the permission of
their parents or guardians as set forth in § 50.55.
§ 50.52 Clinical investigations involving greater than minimal risk but presenting the prospect of direct
benefit to individual subjects
 Any clinical investigation within the scope described in §§ 50.1 and 56.101 of this chapter in which
more than minimal risk to children is presented by an intervention or procedure that holds out the
prospect of direct benefit for the individual subject, or by a monitoring procedure that is likely to
contribute to the subject's well-being, may involve children as subjects only if the IRB finds that:
I. The risk is justified by the anticipated benefit to the subjects.
II. The relation of the anticipated benefit to the risk is at least as favourable to the subjects as that
presented by available alternative approaches.
III. Adequate provisions are made for soliciting the assent of the children and permission of their
parents or guardians as set forth in § 50.55.
§ 50.53 Clinical investigations involving greater than minimal risk and no prospect of direct benefit to
individual subjects, but likely to yield generalizable knowledge about the subjects' disorder or condition
 The risk represents a minor increase over minimal risk.
 The intervention or procedure presents experiences to subjects that are reasonably commensurate with
those inherent in their actual or expected medical, dental, psychological, social, or educational
situations.
 The intervention or procedure is likely to yield generalizable knowledge about the subjects' disorder
or condition that is of vital importance for the understanding or amelioration of the subjects' disorder
or condition.
 Adequate provisions are made for soliciting the assent of the children and permission of their parents
or guardians as set forth in § 50.55.
§ 50.54 Clinical investigations not otherwise approvable that present an opportunity to understand,
prevent, or alleviate a serious problem affecting the health or welfare of children
 If an IRB does not believe that a clinical investigation within the scope described in §§ 50.1 and 56.101
of this chapter and involving children as subjects meets the requirements of § 50.51, § 50.52, or §
50.53, the clinical investigation may proceed only if:
I. The IRB finds that the clinical investigation presents a reasonable opportunity to further the
understanding, prevention, or alleviation of a serious problem affecting the health or welfare of
children.
II. The Commissioner of Food and Drugs, after consultation with a panel of experts in pertinent disciplines
(for example: science, medicine, education, ethics, law) and following opportunity for public review
and comment.
§ 50.55 Requirements for permission by parents or guardians and for assent by children
 In addition to the determinations required under other applicable sections of this subpart D, the IRB
must determine that adequate provisions are made for soliciting the assent of the children when in the
judgment of the IRB the children are capable of providing assent.
 In determining whether children are capable of providing assent, the IRB must take into account the
ages, maturity, and psychological state of the children involved. This judgment may be made for all
children to be involved in clinical investigations under a particular protocol, or for each child, as the
IRB deems appropriate.
 The assent of the children is not a necessary condition for proceeding with the clinical investigation if
the IRB determines.
 Even where the IRB determines that the subjects are capable of assenting, the IRB may still waive the
assent requirement if it finds and documents.
 In addition to the determinations required under other applicable sections of this subpart D, the IRB
must determine, in accordance with and to the extent that consent is required under part 50, that the
permission of each child's parents or guardian is granted.
 Permission by parents or guardians must be documented in accordance with and to the extent required
by § 50.27.
 When the IRB determines that assent is required, it must also determine whether and how assent must
be documented.
§ 50.56 Wards
 Children who are wards of the State or any other agency, institution, or entity can be included in clinical
investigations approved under § 50.53 or § 50.54 only if such clinical investigations are:
I. Related to their status as wards.
II. Conducted in schools, camps, hospitals, institutions, or similar settings in which the majority of
children involved as subjects are not wards.
 If the clinical investigation is approved under paragraph (a)of this section, the IRB must require
appointment of an advocate for each child who is a ward.
I. The advocate will serve in addition to any other individual acting on behalf of the child as guardian or
in loco parentis.
II. One individual may serve as advocate for more than one child.
III. The advocate must be an individual who has the background and experience to act in, and agrees to
act in, the best interest of the child for the duration of the child's participation in the clinical
investigation.
IV. The advocate must not be associated in any way (except in the role as advocate or member of the IRB)
with the clinical investigation, the investigator(s), or the guardian organization.
CFR 21 PART 314 - Application for FDA approval to market a new drug.
 Subpart A: General provisions
 314.1 scope of this part.
 314.2 purpose.
 314.3 definition.
 Subpart B: Application
 314.50 content and format of an NDA.
 314.52 notice of certification of invalidity, unenforceability, or noninfringement of a patent.
 314.53 submission of patent information.
 314.54 procedure for submission of a 505(b)(2) application requiring investigation for approval
of a new indication for, or other change from, a listed drug.
 314.55 pediatric use information.
 314.60 Amendments to an unapproved NDA, supplement, or resubmission.
 314.65 Withdrawal by the application of an unapproved application.
 314.70 Supplement and other changes to an approved NDA.
 314.71 Procedures for submission of a supplement to an approved application.
 314.72 Change in ownership of an application
 314.80 Post marketing reporting of adverse drug experience.
 314.81 Other post marketing reports.
 314.90 Waivers.
 Subpart C : Abbreviated Application
 314.92 Drug product for which abbreviated applications may be submitted.
 314.93 Petition to request a change from a listed drug.
 314.94 Content and format of an ANDA.
 314.95 Notice of certification of invalidity, unenforceability, or noninfringement of a patent.
 314.96 Amendment to an unapproved ANDA.
 314.97 Supplements and other change to an approved ANDA.
 314.98 Post marketing reports.
 314.99 Other responsibilities of an application of an ANDA.
 Subpart D : FDA Action on Application and Abbreviated Application.
 314.100 Timeframe for reviewing application and abbreviated application.
 314.101 Filling and NDA and receiving an ANDA.
 314.102 Communications between FDA and applicants.
 314.103 Dispute resolution.
 314.104 Drug with potential for abuse.
 314.105 Approval of an NDA and an ANDA.
 314.106 Foreign data.
 314.107 Date of approval of a 505(b)(2) application or ANDA.
 314.108 New drug product exclusivity.
 314.110 Complete response letter to the applicant.
 314.120 [Reserved]
 314.122 Submitting an abbreviated application for, or a 505(b)(2)(c) petition that relies on, a
listed drug longer marketed.
 314.125 Refusal to approved an NDA.
 314.126 Adequate and well-controlled studies.
 314.127 Refusal to approved an ANDA.
 314.150 Withdrawal of approval of an application or abbreviated application.
 314.151 Withdrawal of approval of an abbreviated new drug application under section
505(j)(5)of the act.
 314.152 Notice of withdrawal of approval of an application or abbreviated application for a
new drug.
 314.153 Suspension of approval of an abbreviated new drug application.
 314.160 Approval of an application or abbreviated application for which approval was
previously refused, suspended, or withdrawn.
 314.161 Determination of reasons for voluntary withdrawal of a listed drug.
 314.162 Removal of a drug product from the list.
 314.170 Adulteration and misbranding of an approval drug.
 Subpart E : Hearing producer for new drugs.
 314.201 Procedure for hearings.
 Judicial review.
 Subpart F : [Reserved]
 Subpart G : Miscellaneous provisions
 314.410 Imports and exports of new drug.
 314.420 Drug master files.
 314.430 Availability for public disclosure of data and information in an application or
abbreviated application.
 314.440 Addresses for application and abbreviated application.
 314.445 Guidance document.
 Subpart H : Accelerated Approval of New Drug for Serious or Life-Threatening iii nesses.
 314.500 Scope.
 314.510 Approval based on a surrogate endpoint or on an effect on a clinical endpoint other
than survival or irreversible morbidity.
 314.520 Approval with restriction to assure safe use.
 314.530 Withdrawal procedures.
 314.540 Post marketing safety reporting.
 314.550 Promotional material.
 314.560 Termination of requirements.
 Subpart I : Approval of New Drug When Human Efficacy Studies are not Ethical or Feasible.
 314.600 Scope.
 314.610 Approval based on evidence of effectiveness from studies in animal.
 314.620 Withdrawal procedures.
 314.630 Post marketing safety reporting.
 314.640 Promotional materials.
 314.650 Termination of requirements.
Subpart A :General provisions
 314.1 scope of this part :
• This part sets forth procedure and requirement for the submission to, and the review by, the food and
drug administration of application and abbreviated application to market a new drug under section 505
of the federal food, drug, and cosmetic Act, as well as amendment, supplement, and post marketing
reports to them.
• This part dose not apply to drug product subject to licensing by FDA under the public health service
act.
 314.2 Purpose :
• The purpose of this part to establish an efficient and thorough drug review process in order to :
a) Facilitate the approval of drug shown to be safe and effective.
b) Ensure the disapproval of drug not shown to be safe and effective.
• These regulations are also intended to establish an effective system for FDA's surveillance of marketed
drugs.
 314.3 Definition :
• ANDA holder is the applicant that owns an approved ANDA.
• Applicant is any person who submits an NDA (including a 505(b)(2) application) or ANDA or an
amendment or supplement to an NDA or ANDA under this part to obtain FDA approval of a new drug
and any person who owns an approved NDA (including a 505(b)(2) application) or ANDA.
• Application, new drug application, or NDA is the application described under § 314.50, including all
amendments and supplements to the application. An NDA refers to “stand-alone” applications
submitted under section 505(b)(1) of the Federal Food, Drug, and Cosmetic Act and to 505(b)(2)
applications.
• Approval letter is a written communication to an applicant from FDA approving an NDA or an ANDA.
• Date of approval is the date on the approval letter from FDA stating that the NDA or ANDA is
approved, except that the date of approval for an NDA described in section 505(x)(1) of the Federal
Food, Drug, and Cosmetic Act is determined as described in section 505(x)(2) of the Federal Food,
Drug, and Cosmetic Act. “Date of approval” refers only to a final approval and not to a tentative
approval.
• Efficacy supplement is a supplement to an approved NDA proposing to make one or more related
changes from among the following changes to product labeling:
• Add or modify an indication or claim.
• Revise the dose or dose regimen.
• Provide for a new route of administration.
• Significantly alter the intended patient population.
• NDA holder is the applicant that owns an approved NDA.
• Original application or original NDA is a pending NDA for which FDA has never issued a complete
response letter or approval letter, or an NDA that was submitted again after FDA had refused to file it
or after it was withdrawn without being approved.
• Postmark is an independently verifiable evidentiary record of the date on which a document is
transmitted, in an unmodifiable format, to another party.
Subpart B - Applications
314.50 content and format of an NDA.
• NDAs and supplements to approved NDAs are required to be submitted in the form and contain
the information, as appropriate for the particular submission, required under this section.
• Three copies of the NDA are required:
• An archival copy.
• A review copy
• A field copy.
• An NDA for a new chemical entity will generally contain an application form, an index, a summary,
five or six technical sections, case report tabulations of patient data, case report forms, drug samples,
and labeling, including, if applicable, any Medication Guide required under part 208 of this chapter.
a) Application form :
• The name and address of the applicant.
• The date of the NDA
• The NDA number if previously issued (for example, if the NDA is a resubmission or an
amendment or supplement).
• The name of the drug product including its established, proprietary, code, and chemical names.
• The dosage form and strength
• The route of administration.
• The identification numbers of all IND.
• the identification numbers of all drug master files and other applications under this part that
are referenced in the NDA.
• A statement whether the applicant proposes to market the drug product as a prescription or an
over the-counter product.
• A check-list identifying what enclosures required under this section the applicant is submitting.
b) Summary.
• A summary of the chemistry, manufacturing, and controls section of the NDA.
• A summary of the nonclinical pharmacology and toxicology section of the NDA.
• A summary of the human pharmacokinetics and bioavailability section of the NDA.
• A summary of the microbiology section of the NDA (for anti-infective drugs only).
• A summary of the clinical data section of the NDA, including the results of statistical analyses
of the clinical trials.
c) Technical sections:
• Each technical section is required to contain data and information in sufficient detail to permit
the agency to make a knowledgeable judgment about whether to approve the NDA or whether
grounds exist under section 505(d) of the Federal Food, Drug, and Cosmetic Act to refuse to
approve the NDA.
• Chemistry, manufacturing, and controls section.
• Nonclinical pharmacology and toxicology section.
• Human pharmacokinetics and bioavailability section
• Microbiology section
• Clinical data section
• Statistical section.
• Pediatric use section.
d) Samples and labeling:
• FDA generally will ask applicants to submit samples directly to two or more Agency
laboratories that will perform all necessary tests on the samples and validate the applicant's
analytical procedures.
e) Case report forms and tabulations:
• Case report tabulations.
• Case report forms.
• Additional data.
f) Patent information:
• Patents claiming drug substance, drug product, or method of use.
• No relevant patents.
• Method-of-use patent.
• Licensing agreements.
• Untimely filing of patent information.
• Disputed patent information.
• Amended certifications.
 314.52 Notice of certification of invalidity, unenforceability, or noninfringement of a patent.
a)Notice of certification : Each owner of the patent that is the subject of the certification or the representative
designated by the owner to receive the notice.
b)Sending the notice :
c)Amendment or supplement to a 505(b)(2) application:
d)Documentation of timely sending and receipt of notice
(f) Forty-five day period after receipt of notice
(g) Designated delivery services.
 314.53 Submission of patent information.
• This section applies to any applicant who submits to FDA an NDA or an amendment to it under
section 505(b) of the Federal Food, Drug, and Cosmetic Act.
Sec. 314.53 Submission of patent information.
(a) Who must submit patent information
(b) Patents for which information must be submitted and patents for which information must not be
submitted –
(1) General requirements.
(2) Test data for submission
(c) Reporting requirements –
(1) General requirements
(2) Drug substance (active ingredient), drug product (formulation or composition)
(d) When and where to submit patent information –
(1) Original NDA
(2) Supplements
(3) Newly issued patents.
(4) Submission of Forms FDA
(5) Submission date
(6) Identification
(e) Public disclosure of patent information
(f) Correction of patent information errors
 314.55 Pediatric use information.
(a) Required assessment.
(b) Deferred submission
(c) Waivers
(1) General. (2) Full waiver (3) Partial waiver (4)FDA action on waiver.
 314.60 Amendments to an unapproved NDA, supplement, or resubmission.
(a) Submission of NDA.
(b) Submission of major amendment.
(c) Limitation on certain amendments
(d) Field copy
(e) Different drug.
(f) Patent certification requirements
 314.65 Withdrawal by the applicant of an unapproved application:
• An applicant may at any time withdraw an application that is not yet approved by notifying the
Food and Drug Administration in writing.
• If, by the time it receives such notice, the agency has identified any deficiencies in the
application, we will list such deficiencies in the letter we send the applicant acknowledging the
withdrawal.
• A decision to withdraw the application is without prejudice to refilling. The agency will retain
the application and will provide a copy to the applicant on request under the fee schedule in
20.45 of FDA's public information regulations.
 314.70 Supplements and other changes to an approved NDA.
(a) Changes to an approved NDA
(b) Changes requiring supplement submission and approval prior to distribution of the product made using the
change (major changes).
(c) Changes requiring supplement submission at least 30 days prior to distribution of the drug product made
using the change (moderate changes).
(d) Changes to be described in an annual report (minor changes).
(e) Protocols.
(f) Patent information
(h) Different drug
Sec. 314.72 Change in ownership of an application.
(a) An applicant may transfer ownership of its application.
(b) The new owner shall advise FDA about any change in the conditions in the approved application under
314.70 except the new owner may advise FDA in the next annual report about a change in the drug product's
label or labeling to change the product's brand or the name of its manufacturer, packer, or distributor.
 314.80 Post-marketing reporting of adverse drug experiences.
(a) Definitions
Adverse drug experience.
Any adverse event associated with the use of a drug in humans, whether or not considered drug related,
including the following:
1. An adverse event occurring,in the course of the use of a drug product in professional practice;
2. an adverse event occurring from drug overdose whether accidental or intentional;
3. an adverse event occurring from drug abuse;
4. an adverse event occurring from drug withdrawal;and any failure of expected pharmacological action.
(b) Review of adverse drug experiences.
(c) Reporting requirements
(d) Scientific literature
(e) Post marketing studies.
(f) Information reported on ICSRs(Individual case safety report)
(g) Electronic format for submissions
(h) Multiple reports
(i) Patient privacy.
(j) Recordkeeping
(k) Withdrawal of approval.
Subpart C - Abbreviated Applications
 314.92 Drug products for which abbreviated applications may be submitted.
Abbreviated applications are suitable for the following drug products within the limits set forth under 314.93:
• Drug products that are the same as a listed drug. A "listed drug" is defined in 314.3. For determining
the suitability of an abbreviated new drug application, the term "same as" means identical in active
ingredient(s), dosage form, strength, route of administration, and conditions of use, except that
conditions of use for which approval cannot be granted because of exclusivity or an existing patent
may be omitted. If a listed drug has been voluntarily withdrawn from or not offered for sale by its
manufacturer, a person who wishes to submit an abbreviated new drug application for the drug shall
comply with 314.122.
FDA will publish in the list listed drugs for which abbreviated applications may be submitted.
 314.94 Content and format of an ANDA
ANDAs are required to be submitted in the form and contain the information required under this section. Three
copies of the ANDA are required, an archival copy, a review copy, and a field copy. FDA will maintain
guidance documents on the format and content of ANDAs to assist applicants in their preparation.
• includes the following:
(1) Application form
(2) Table of contents.
(3) Basis for ANDA submission
(4) Conditions of use.
(6) Route of administration
(7) Bioequivalence.
(8) Labeling
(9) Chemistry, manufacturing, and controls.
(10) Samples.
(11) Other.
(12) Patent certification
(13) Financial certification or disclosure statement.
 314.96 Amendments to an unapproved ANDA.
(a) ANDA
(b) Field copy.
(c) Different listed drug .
 314.97 Supplements and other changes to an approved ANDA.
(a) General requirements
(b) Different listed drug.
 314.98 Post marketing reports.
(a) Each applicant having an approved abbreviated new drug application under 314.94 that is effective must
comply with the requirements of 314.80 regarding the reporting and recordkeeping of adverse drug
experiences.
(b) Each applicant must make the reports required under 314.81 and section 505(k) of the Federal Food, Drug,
and Cosmetic Act for each of its approved abbreviated applications.
Subpart D - FDA Action on Applications and Abbreviated Applications.
 314.100 Timeframes for reviewing applications and abbreviated applications.
(a) Except as provided in paragraph (c) of this section, within 180 days of receipt of an application for a new
drug under section 505
(b) of the act or an abbreviated application for a new drug under section 505(j) of the act, FDA.
 314.101 Filing an NDA and receiving an ANDA
(a) Filing an NDA.
(b)Receiving an ANDA
(c) [Reserved]
(d) NDA or ANDA deficiencies
(e) Regulatory deficiency
(f) Outcome of FDA review.
 314.102 Communications between FDA and applicants.
(a) General principles.
(b) Notification of easily correctable deficiencies
(c) Ninety-day conference
(d) End-of-review conference
(e) Other meetings
 314.103 Dispute resolution
(a) General.
(b) Administrative and procedural issues
(c) Scientific and medical disputes.
 314.104 Drugs with potential for abuse.
The Food and Drug Administration will inform the Drug Enforcement Administration under section 201(f) of
the Controlled Substances Act (21 U.S.C. 801) when an application or abbreviated application is submitted
for a drug that appears to have an abuse potential.
 314.106 Foreign data.
(a) General. The acceptance of foreign data in an application generally is governed by 312.120 of this chapter.
(b) As sole basis for marketing approval.
(c) Consultation between FDA and applicants.
 314.107 Date of approval of a 505(b)(2) application or ANDA
(a) General. A drug product may be introduced or delivered for introduction into interstate commerce when
the 505(b)(2) application or ANDA for the drug product is approved.
(b) Effect of patent(s) on the listed drug.
(c) Timing of approval of subsequent ANDA.
(d) Delay due to exclusivity.
(e) Notification of court actions or written consent to approval.
(f) Forty-five day period after receipt of notice of paragraph IV certification
(g) Conversion of approval to tentative approval.
 314.110 Complete response letter to the applicant.
(a) Complete response letter.
(b) Applicant actions.
(c) Failure to take action.
 314.125 Refusal to approve an NDA.
(a) The Food and Drug Administration will refuse to approve the NDA and for a new drug give the applicant
written notice of an opportunity for a hearing under 314.200 on the question of whether there are grounds for
denying approval of the NDA under section 505(d) of the Federal Food, Drug, and Cosmetic Act .
(b) For drugs intended to treat life-threatening or severely-debilitating illnesses that are developed in
accordance with 312.80 through 312.88 of this chapter, the criteria contained in paragraphs (b) (3), (4), and
(5) of this section shall be applied according to the considerations contained in 312.84 of this chapter.
 314.152 Notice of withdrawal of approval of an application or abbreviated application for a new
drug.
If the Food and Drug Administration withdraws approval of an application or abbreviated application for a
new drug, FDA will publish a notice in the Federal Register announcing the withdrawal of approval. If the
application or abbreviated application was withdrawn for grounds described in 314.150(a) or 314.151, the
notice will announce the removal of the drug from the list of approved drugs published under section 505(j)(6)
of the act and shall satisfy the requirement of 314.162(b).
 314.153 Suspension of approval of an abbreviated new drug application.
(a) Suspension of approval
(b) Procedures for suspension of abbreviated new drug applications when a listed drug is voluntarily
withdrawn for safety or effectiveness reasons.
 314.160 Approval of an application or abbreviated application for which approval was
previously refused, suspended, or withdrawn.
Upon the Food and Drug Administration's own initiative or upon request of an applicant, FDA may, on the
basis of new data, approve an application or abbreviated application which it had previously refused,
suspended, or withdrawn approval. FDA will publish a notice in the Federal Register announcing the approval.
 314.162 Removal of a drug product from the list.
(a) FDA will remove a previously approved new drug product from the list for the period
(b) FDA will publish in the Federal Register a notice announcing the removal of a drug from the list.
(c) At the end of the period specified in paragraph (a)(1) or (a)(2) of this section, FDA will relist a drug that
has been removed from the list. The agency will publish in the Federal Register a notice announcing the
relisting of the drug.
Subpart E - Hearing Procedures for New Drugs.
 314.200 Notice of opportunity for hearing; notice of participation and request for hearing; grant
or denial of hearing.
(a) Notice of opportunity for hearing.
(b) FDA will provide the notice of opportunity for a hearing to applicants and to other persons subject to the
notice under 310.6, as follows:
(1) To any person who has submitted an application or abbreviated application, by delivering the notice in
person or by sending it by registered or certified mail to the last address shown in the application or abbreviated
application.
(2) To any person who has not submitted an application or abbreviated application but who is subject to the
notice under 310.6 of this chapter, by publication of the notice in the Federal Register.
(c) The person requesting a hearing is required to submit under paragraph (c)(1)(ii) of this section the studies
on which the person relies to justify a hearing with respect to the drug product.
(d) Separation of functions.
(g) Summary judgment.
 314.235 Judicial review.
(a) The Commissioner of Food and Drugs will certify the transcript and record. In any case in which the
Commissioner enters an order without a hearing under 314.200(g), the record certified by the Commissioner
is required to include the requests for hearing together with the data and information submitted and the
Commissioner's findings and conclusion.
(b) A manufacturer or distributor of an identical, related, or similar drug product under 310.6 may seek judicial
review of an order withdrawing approval of a new drug application, whether or not a hearing has been held,
in a United States court of appeals under section 505(h) of the act.
Subpart F [Reserved]
Subpart G - Miscellaneous Provisions
 314.410 Imports and exports of new drugs.
Imports:
(1) A new drug may be imported into the United States if: (i) It is the subject of an approved application
under this part; or (ii) it complies with the regulations pertaining to investigational new drugs under
part 312; and it complies with the general regulations pertaining to imports under subpart E of part 1.
 314.410 Imports and exports of new drugs.
Imports:
(1) A new drug may be imported into the United States if: (i) It is the subject of an approved application under
this part; or (ii) it complies with the regulations pertaining to investigational new drugs under part 312; and it
complies with the general regulations pertaining to imports under subpart E of part 1.
 314.420 - Drug master files
A drug master file is a submission of information to the Food and Drug Administration by a person (the drug
master file holder) who intends it to be used.
A drug master file may contain information of the kind required for any submission to the agency, including
information about the following:
(1) [Reserved]
(2) Drug substance, drug substance intermediate, and materials used in their preparation, or drug product;
(3) Packaging materials;
(4) Excipient, colorant, flavor, essence, or materials used in their preparation;
(5) FDA-accepted reference information
 314.445 Guidance documents.
(a) FDA has made available guidance documents under 10.115 of this chapter to help you to comply with
certain requirements of this part.
(b) The Center for Drug Evaluation and Research (CDER) maintains a list of guidance documents that apply
to CDER's regulations. The list is maintained on the Internet and is published annually in the Federal Register.
A request for a copy of the CDER list should be directed to the Office of Training and Communications,
Division of Drug Information, Center for Drug Evaluation and Research, Food and Drug Administration.
Subpart H - Accelerated Approval of New Drugs for Serious or Life-Threatening Illnesses
 314.500 Scope.
 This subpart applies to certain new drug products that have been studied for their safety and
effectiveness in treating serious or life-threatening illnesses and that provide meaningful
therapeutic benefit to patients over existing
 treatments (e.g., ability to treat patients unresponsive to, or intolerant of, available therapy, or
improved patient response over available therapy).
 314.520 Approval with restrictions to assure safe use.
(a) If FDA concludes that a drug product shown to be effective can be safely used only if distribution or use
is restricted, FDA will require such post-marketing restrictions as are needed to assure safe use of the drug
product, such as:
(1) Distribution restricted to certain facilities or physicians with special training or experience; or
(2) Distribution conditioned on the performance of specified medical procedures.
(b) The limitations imposed will be commensurate with the specific safety concerns presented by the drug
product.
 314.530 Withdrawal procedures.
(a) For new drugs approved under 314.510 and 314.520, FDA may withdraw approval, following a hearing as
provided in part 15 of this chapter, as modified by this section, if:
(1) A post-marketing clinical study fails to verify clinical benefit;
(2) The applicant fails to perform the required post-marketing study with due diligence;
(3) Use after marketing demonstrates that post-marketing restrictions are inadequate to assure safe use
of the drug product;
(4) The applicant fails to adhere to the post-marketing restrictions agreed upon.
(5) The promotional materials are false or misleading.
(6) Other evidence demonstrates that the drug product is not shown to be safe or effective under its
conditions of use.
(b) Notice of opportunity for a hearing.
(c) Submission of data and information.
(d) Separation of functions.
(e) Procedures for hearings.
(f) Judicial review.
 314.540 Post marketing safety reporting.
 Drug products approved under this program are subject to the post marketing recordkeeping and safety
reporting applicable to all approved drug products, as provided in 314.80 and 314.81.
Subpart I - Approval of New Drugs When Human Efficacy Studies Are Not Ethical or Feasible.
 314.600 Scope.
 This subpart applies to certain new drug products that have been studied for their safety and
efficacy in preventing serious or life-threatening conditions caused by exposure to lethal or
permanently disabling toxic biological, chemical, radiological, or nuclear substances.
 314.620 Withdrawal procedures.
(a) Reasons to withdraw approval.
(b) Notice of opportunity for a hearing
(c) Submission of data and information
(d) Separation of functions
(e) Procedures for hearings
(f) Judicial review.
 314.630 Post marketing safety reporting.
 Drug products approved under this subpart are subject to the post marketing recordkeeping and safety
reporting requirements applicable to all approved drug products, as provided in 314.80 and 314.81.
CFR-21 PART 822 (POST-MARKET SURVEILLANCE)
 Subpart A General provisions
§ 822.1 what dose this part cover ?
§ 822.2 what is the purpose of this part?
§ 822.3 how do you define the terms used in this part ?
§ 822.4 does this part apply to me?
 SUBPART B notification
§ 822.5 how will I know if I must conduct post market surveillance?
§ 822.6 when will you notify me that I am required to conduct post market surveillance?
§ 822.7 what should I do if I do not agree that post market surveillance is appropriate?
 Subpart C post market surveillance plan
§ 822.8 when ,where and how must I submit my postmarket surveillance plan?
§ 822.9 what must I include in my submission?
§ 822.10 what must I include in my surveillance plan?
§ 822.11 what should I consider when designing my plan to conduct postmarket surveillance?
§ 822.12 do you have any information that will help me prepare my submission or design my
postmarket surveillance plan?
§ 822.13 [reserved]
§ 822.14 may I reference information previously submitted instead of submitting it again?

§ 822.15 how long must I conduct postmarket surveillance of my device?
 SUBPART D FDA review and action
§ 822.16 what will you consider in the review of my submission take?
§ 822.17 how long will you review of my submission take?
§ 822.18 how will I be notified of your decision?
§ 822.19 What kinds of decisions may you make?
§ 822.20 what are the consequences if I fail to submit a postmarket surveillance plan is disapproved
and I fail to submit a new plan,or I fail to conduct surveillance in accordance with my approved plan?
§ 822.21 what must I do if I want to make changes to my postmarket surveillance plan after you have
approved plan?
§ 822.22 what recourse do I have if I do not agree with your decision?
§ 822.23 Is the information in my submission considered confidential?
 Subpart E responsibilities of manufacturers
§ 822.24 what are my responsibilities once I an notified that I am required to conduct postmarket
surveillance?
§ 822.25 what are my responsibilities after my postmarket surveillance plan has been approved?
§ 822.26 if my company changes ownership, what must I do?
§ 822.27 if I go out of business,what must I do?
§ 822.28 if I stop marketing the device subject to postmarket surveillance,what must I do?
Subpart F waivers and exemption
§ 822.29 may I request a waiver of a specific requirement of this part?
§ 822.30 may I request exemption from the requirement to conduct postmarket surveillance?
Subpart G records and reports
§ 822.31 what records am I required to keep?
§ 822.32 what records are the investigatigators in my surveillance plan required to keep?
§ 822.33 how long must we keep the records?
§ 822.34 what must I do with the records if the sponsor of the plan or an investigator in the plan or an
investigator in the plan changes?
§ 822.35 can you insepct my manufacturing site or other sites involved in my postmarket surveillance
plan?
§ 822.36 can you insepct and copy the records releted to my postmarket surveillance plan?
§ 822.37 under what circumstances would you inspect records identifying subjects?
§ 822.38 what reports must I submit to you?
Subpart A General provisions:
 § 822.1 what dose this part cover ?
This part implements section 522 of the Federal Food, Drug, and Cosmetic Act (the act) by providing
procedures and requirements for postmarket surveillance of class II and class III devices that meet any of the
following criteria:
A. Failure of the device would be reasonably likely to have serious adverse health consequences;
B. The device is intended to be implanted in the human body for more than 1 year; or
C. The device is intended to be used outside a user facility to support or sustain life. If you fail to comply
with requirements that we order under section 522 of the act and this part, your device is considered
misbranded under section 502(t)(3) of the act and you are in violation of section 301(q)(1)(C) of the
act.
 § 822.2 what is the purpose of this part?
The purpose of this part is to implement our postmarket surveillance authority to maximize the likelihood
that postmarket surveillance plans will result in the collection of useful data. These data can reveal unforeseen
adverse events, the actual rate of anticipated adverse events, or other information necessary to protect the
public health.
 § 822.3 how do you define the terms used in this part ?
Some of the terms we use in this part are specific to postmarket surveillance and reflect the language used
in the statute (law). Other terms are more general and reflect our interpretation of the law. This section of the
part defines the following terms:
1.act
2.designated person
3.device failure
4. general plan guideline
5.human cell, tissue or cellular or tissue-based product
6.investigator
7. life-supporting or life-sustaining device used facility
8.manufacturer
9.postmarket surveillance
10.prospective surveillance
11.serious adverse health consequences
12.specific guidance
13.surveillance question
14.unforeseen adverse event
15.unique device identifier(UDI)
Subpart B- Notification:
§ 822.5 how will I know if I must conduct post market surveillance?
We will send you a letter (the postmarket surveillance order) notifying you of the requirement to conduct
postmarket surveillance. Before we send the order, or as part of the order, we may require that you submit
information about your device that will allow us better to define the scope of a surveillance order. We will
specify the device(s) subject to the surveillance order and the reason that we are requiring postmarket
surveillance of the device under section 522 of the act. We will also provide you with any general or specific
guidance that is available to help you develop your plan for conducting postmarket surveillance.
Subpart C post market surveillance plan
§ 822.8 when ,where and how must I submit my postmarket surveillance plan?
You must submit your plan to conduct postmarket surveillance within 30 days of the date you receive the
postmarket surveillance order. For devices regulated by the Center for Biologics Evaluation and Research,
send your submission to the Food and Drug Administration, Center for Biologics Evaluation and Research,
Document Control Center, 10903 New Hampshire Ave., Bldg. 71, Rm. G112, Silver Spring, MD 20993-0002.
For devices regulated by the Center for Drug Evaluation and Research, send your submission to the Central
Document Room, Center for Drug Evaluation and Research, Food and Drug Administration, 5901-B,
Ammendale Rd., Beltsville, MD 20705-1266. For devices regulated by the Center for Devices and
Radiological Health, send your submission to the Document Mail Center, 10903 New Hampshire Ave., Bldg.
66, Rm. G609, Silver Spring, MD 20993-0002. When we receive your original submission, we will send you
an acknowledgment letter identifying the unique document number assigned to your submission. You must
use this number in any correspondence related to this submission.
§ 822.9 what must I include in my submission?
Your submission must include the following:
(a) Organizational/administrative information:
(1) Your name and address;
(2) Generic and trade names of your device;
(3) Name and address of the contact person for the submission;
(4) Premarket application/submission number and device identifiers for your device;
(5) Table of contents identifying the page numbers for each section of the submission;
(6) Description of the device (this may be incorporated by reference to the appropriate premarket
application/submission);
(7) Product codes and a list of all relevant model numbers; and
(8) Indications for use and claims for the device;
(b) Postmarket surveillance plan;
(c) Designated person information;
(1) Name, address, and telephone number; and
(2) Experience and qualifications.
§ 822.10 what must I include in my surveillance plan?
Your surveillance plan must include a discussion of:
(a) The plan objective(s) addressing the surveillance question(s) identified in our order;
(b) The subject of the study, e.g., patients, the device, animals;
(c) The variables and endpoints that will be used to answer the surveillance question, e.g., clinical
parameters or outcomes;
(d) The surveillance approach or methodology to be used;
(e) Sample size and units of observation;
(f) The investigator agreement, if applicable;
(g) Sources of data, e.g., hospital records;
(h) The data collection plan and forms;
(i) The consent document, if applicable;
(j) Institutional Review Board information, if applicable;
(k) The patient followup plan, if applicable;
(l) The procedures for monitoring conduct and progress of the surveillance;
(m) An estimate of the duration of surveillance;
(n) All data analyses and statistical tests planned;
(o) The content and timing of reports.
§ 822.15 how long must I conduct postmarket surveillance of my device?
The length of postmarket surveillance will depend on the postmarket surveillance question identified in our
order. We may order prospective surveillance for a period up to 36 months; longer periods require your
agreement. If we believe that a prospective period of greater than 36 months is necessary to address the
surveillance question, and you do not agree, we will use the Medical Devices Dispute Resolution Panel to
resolve the matter. You may obtain guidance regarding dispute resolution procedures from the Center for
Devices and Radiological Health's (CDRH’).
The 36-month period refers to the surveillance period, not the length of time from the issuance of the order.
Subpart D FDA review and action:
§ 822.16 what will you consider in the review of my submission take?
First, we will determine that the submission is administratively complete. Then, in accordance with the law,
we must determine whether the designated person has appropriate qualifications and experience to conduct
the surveillance and whether the surveillance plan will result in the collection of useful data that will answer
the surveillance question.
§ 822.18 how will I be notified of your decision?
We will send you a letter notifying you of our decision and identifying any action you must take.
§ 822.21 what must I do if I want to make changes to my postmarket surveillance plan after you have
approved plan?
You must receive our approval in writing before making changes in your plan that will affect the nature or
validity of the data collected in accordance with the plan. To obtain our approval, you must submit the request
to make the proposed change and revised postmarket surveillance plan to the applicable address listed in §
822.8. You may reference information already submitted in accordance with § 822.14. In your cover letter,
you must identify your submission as a supplement and cite the unique document number that we assigned in
our acknowledgment letter for your original submission, specifically identify the changes to the plan, and
identify the reasons and justification for making the changes. You must report changes in your plan that will
not affect the nature or validity of the data collected in accordance with the plan in the next interim report
required by your approval order.
§ 822.22 what recourse do I have if I do not agree with your decision?
(a) If you disagree with us about the content of your plan or if we disapprove your plan, or if you believe there
is a less burdensome approach that will answer the surveillance question, you may request review of our
decision by:
(1) Requesting a meeting with the individual who issued the order for postmarket surveillance;
(2) Seeking internal review of the order under § 10.75 of this chapter;
(3) Requesting an informal hearing under part 16 of this chapter; or
(4) Requesting review by the Medical Devices Dispute Resolution Panel of the Medical Devices
Advisory Committee.
(b) You may obtain guidance documents that discuss these mechanisms from the Center for Devices and
Radiological Health's (CDRH's) Web site.
Subpart E responsibilities of manufacturers:
§ 822.24 what are my responsibilities once I an notified that I am required to conduct postmarket
surveillance?
You must submit your plan to conduct postmarket surveillance to us within 30 days from receipt of the order
(letter) notifying you that you are required to conduct postmarket surveillance of a device.
§ 822.26 if my company changes ownership, what must I do?
You must notify us within 30 days of any change in ownership of your company. Your notification should
identify any changes to the name or address of the company, the contact person, or the designated person (as
defined in § 822.3(b)). Your obligation to conduct postmarket surveillance will generally transfer to the new
owner, unless you and the new owner have both agreed that you will continue to conduct the surveillance. If
you will continue to conduct the postmarket surveillance, you still must notify us of the change in ownership.
Subpart F waivers and exemption:
§ 822.29 may I request a waiver of a specific requirement of this part?
You may request that we waive any specific requirement of this part. You may submit your request, with
supporting documentation, separately or as a part of your postmarket surveillance submission to the address
in § 822.8.
Subpart G records and reports:
§ 822.31 what records am I required to keep?
You must keep copies of:
(a) All correspondence with your investigators or FDA, including required reports;
(b) Signed agreements from each of your investigators, if your surveillance plan uses investigators, stating
the commitment to conduct the surveillance in accordance with the approved plan, any applicable FDA
regulations, and any conditions of approval for your plan, such as reporting requirements;
(c) Your approved postmarket surveillance plan, with documentation of the date and reason for any deviation
from the plan;
(d) All data collected and analyses conducted in support of your postmarket surveillance plan; and
(e) Any other records that we require to be maintained by regulation or by order, such as copies of signed
consent documents, evidence of Institutional Review Board review and approval, etc.
§ 822.33 how long must we keep the records?
You, the designated person, and your investigators must keep all records for a period of 2 years after we have
accepted your final report, unless we specify otherwise.
§ 822.35 can you insepct my manufacturing site or other sites involved in my postmarket surveillance
plan?
We can review your postmarket surveillance programs during regularly scheduled inspections, inspections
initiated to investigate recalls or other similar actions, and inspections initiated specifically to review your
postmarket surveillance plan. We may also inspect any other person or site involved in your postmarket
surveillance, such as investigators or contractors. Any person authorized to grant access to a facility must
permit authorized FDA employees to enter and inspect any facility where the device is held or where records
regarding postmarket surveillance are held.
§ 822.38 what reports must I submit to you
You must submit interim and final reports as specified in your approved postmarket surveillance plan. In
addition, we may ask you to submit additional information when we believe that the information is necessary
for the protection of the public health and implementation of the act. We will also state the reason or purpose
for the request and how we will use the information.
EUDRALEX VOLUME -3 (Scientific guidelines for medicinal products for human use)
Volume 3 (The rules governing medicinal products in the European Union)
• Volume 3 of the publications "The rules governing medicinal products in the European Union"
contains scientific guidelines prepared by the Committee for Medicinal Products for Human Use
(CHMP) in consultation with the competent authorities of the EU Member States, to help applicants
prepare marketing-authorization applications for medicinal products for human use.
PURPOSE Of EudraLex:
• The guidelines are intended to provide a basis for practical harmonization of the manner in which the
EU Member States and the EMA interpret and apply the detailed requirements for the demonstration
of quality, safety and efficacy contained in the Community Directives.
• They also help to ensure that applications for marketing authorization are prepared in a manner that
will be recognized as valid by the EMA.
Scientific guidelines:
• The European Medicines Agency's Committee for Medicinal Products for Human Use prepares
scientific guidelines in consultation with regulatory authorities in the European Union (EU) Member
States, to help applicants prepare marketing authorization applications for human medicines.
• Guidelines reflect a harmonized approach of the EU Member States and the Agency on how to interpret
and apply the requirements for the demonstration of quality, safety and efficacy set out in the
Community directives.
• The Agency strongly encourages applicants and marketing authorization holders to follow these
guidelines.
• Applicants need to justify deviations from guidelines fully in their applications at the time of
submission.
• Before that, they should seek scientific advice , to discuss any proposed deviations during medicine
development.
Compilation of European Commission and Agency guidelines:
• This section of the website updates and replaces the previous volume 3 of the rules governing medicinal
products in the European Union (EudraLex), published by the European Commission.
• It contains:
• all valid guidelines originally published in volume 3;
• all valid guidelines published by the Agency since 1995;
• these guidelines' revisions and supplements.
DOCUMENTS available
• Depending on each guideline's status, one or more of the following documents are available:
 concept paper;
 draft guideline;
 overview of comments received during the consultation period; adopted guideline
• However, only adopted guidelines form part of volume 3 of EudraLex.
• The presentational order of the guidelines in this compilation was adapted following the introduction
of the Common Technical Document(CTD) format in the EU.
• While the overall structure of Annex I to Directive 2001/83/EC has been followed, some adjustments
have been made to account for the specific nature of certain areas or guidelines.
SPECIFIC REQUIREMENTS FOR INDIVIDUAL SECTIONS:
Quality :
• As far as possible, the structure of the CTD has been followed.
• The structure has been adapted where a different method of consolidation was considered to be more
appropriate, as in the case of guidelines which applyto both the active substance and to the finished product
(which, in the CTD format, are independent headings).
Biologicals :
• Because of the particular nature of these guidelines, the detailed CTD structure is not entirely applicable.
Therefore, a distinction between biologicals, plasma-derived products and vaccines has also been added
within the section 'manufacture, characterization and control of the drug substance'.
• Non-clinical: The CTD structure has been followed.
Clinical safety and efficacy :
• Generally, the CTD structure has been followed.
• In addition, guidelines have been organized into therapeutic groups.
ICH : This section includes guidelines that are harmonized through the International Council on
Harmonization of Technical Requirements for Registration of Pharmaceuticals for Human Use (ICH). The
CTD structure has been followed.
Multidisciplinary: This section contains guidelines that apply to more than one specific area or have been
prepared through the collaboration of several working parties. Where applicable, these guidelines are also
listed in the specific section to which they relate (e.g. the 'quality' section).
Herbal medicinal product guidelines: The Committee on Herbal Medicinal Products prepares the
'Community list of herbal substances, preparations and combinations thereof for use in traditional herbal
medicinal products', and establishes Community herbal monographs. Although these documents are excluded
from the scope of the procedure for EU guidelines, they have relevance for the registration as well as the
authorization of herbal medicinal products. Therefore, they are listed under a specific heading among
multidisciplinary guidelines.
Related document types:
• Historical documents such as 'notes for guidance' are included in the compilation where they have the
regulatory status of a guideline. Following the implementation of the procedure on EU guidelines,
however, the use of these terms has been discontinued.
• The compilation also includes other related documents, such as reflection papers, public
statements and questions and answers.
• They provide additional information on topics of particular concern and/or clarification in areas where
scientific knowledge is fast evolving or experience is limited.
• Other guidelines, such as regulatory guidelines, good-manufacturing-practice guidelines and
pharmacovigilance guidelines, were excluded from this re-organization exercise.
• They continue to be published by the European Commission.
Scientific advice and protocol assistance:
Table of contents
• How scientific advice works
• When scientific advice is most useful
• Types of questions addressed
• Protocol assistance
• Scientific advice on post-authorization safety studies (PASS)
• Parallel scientific advice with the United States
• Parallel consultations from regulators and HTA bodies
• Scientific advice on biosimilars
• Fees and fee reductions
• What EMA publishes on outcomes of scientific advice
objectives
• The European Medicines Agency (EMA) can provide medicine developers advice on the most appropriate
way to generate robust evidence on a medicine's benefits and risks. EMA provides scientific advice to
support the timely and sound development of high-quality, effective and safe medicines, for the benefit of
patients.
• At any stage of a medicine's development, a developer can ask guidance and direction from EMA on the
best methods and study designs to generate robust information on how well a medicine works and how
safe it is, regardless of whether the medicine is eligible for the centralized authorization procedure or not.
SCIENTIFIC ADVICE:
• It helps to ensure that developers perform the appropriate tests and studies, so that no major
objections regarding the design of the tests are likely to be raised during the evaluation of the
marketing authorization application.
• This also helps avoid patients taking part in studies that will not produce useful evidence.
• For human medicines, scientific advice and protocol assistance are given by the Committee for
Medicinal Products for Human Use (CHMP) on the recommendation of the Scientific Advice Working
Party (SAWP).
How scientific advice works ?
• EMA gives scientific advice by responding to specific questions posed by the medicine developer on
the development of a particular medicine.
• The developer of a medicine presents the way it plans to develop its medicine and identifies questions
and possible solutions. EMA then gives advice on the developer’s proposals.
• Scientific advice is prospective in nature. EMA does not pre-evaluate the results of the studies and in
no way concludes on whether the benefits of the medicine outweigh the risks.
• Scientific advice from EMA is not legally binding on EMA or on the medicine developer with regard
to any future marketing authorization applications for the medicine concerned.
When scientific advice is most useful ?
Scientific advice and protocol assistance are particularly useful to medicine developers when :
• They are developing an innovative medicine and there appears to be no or insufficient relevant detail
in EU guidelines or guidance documents, or in Pharmacopoeia monographs, including draft documents
or monographs released for consultation;
• The developer chooses to deviate from scientific guidelines in its development plan;
• The medicine developer has limited knowledge about medicine regulation, such as some academic
groups or micro, small and medium sized enterprises (SMEs).
• Medicine developers can request scientific advice or protocol assistance either during the initial
development of a medicine before submission of a marketing authorization application or later on,
during the post-authorization phase.
Types of questions addressed:
Questions during scientific advice can relate to :
• quality aspects (manufacturing, chemical, pharmaceutical and biological testing of the medicine);
• non-clinical aspects (toxicological and pharmacological tests designed to show the activity of the
medicine in the laboratory);
• clinical aspects (appropriateness of studies in patients or healthy volunteers, selection of endpoints, i.e.
how best to measure effects in a study, post-authorization activities including risk management plans);
• methodological issues (statistical tests to use, data analysis, modeling and simulation).
Protocol assistance
• Protocol assistance is the special form of scientific advice available for developers of designated
orphan medicines for rare diseases.
• In addition to scientific advice, developers of orphan medicines can receive answers to questions
relating to the criteria for authorisation of an orphan medicine. These include:
• The demonstration of significant benefit within the scope of the designated orphan indication;
• similarity or clinical superiority over other medicines. This is relevant if other orphan medicinal
products exist that might be similar to the product concerned and which have market exclusivity in the
same indication.
Scientific advice on post-authorization safety studies (PASS)
• EMA encourages medicine developers to seek scientific advice for PASS protocols. This voluntary,
optional procedure will help to improve the design of studies meant to collect further information on a
medicine's safety once it is on the market.
• EMA ran a 12-month pilot for this procedure between July 2015-2016.
Parallel scientific advice with the United States
• The Agency provides scientific advice and protocol assistance in parallel with the United States Food
and Drug Administration (FDA).
Parallel consultations from regulators and HTA bodies
• EMA offers consultations in parallel with European Network for Health Technology
Assessment (EUnetHTA) as of July 2017. This aims to allow medicine developers to obtain feedback
from regulators and HTA bodies on their evidence-generation plans to support decision-making
on marketing authorization and reimbursement of new medicines at the same time.
• The procedure is a single gateway for parallel consultations with EMA, EUnetHTA and HTA bodies
on their evidence-generation plans.
• Consultations can take place before or after the product is made available on the market. The objective
is to help generate optimal and robust evidence that satisfies the needs of both regulators and HTA
bodies.
• This initiative replaces the parallel scientific advice procedure by EMA and HTA bodies which
required medicine developers to contact Member States' HTA bodies individually.
scientific advice on biosimilars:
• EMA is running a tailored scientific advice pilot project to support the development of new biosimilars
.
• The tailored procedure advises developers on the studies they should conduct, based on a review of the
quality, analytical and functional data they already have available.
• The pilot is open to all types of biosimilars and companies are encouraged to request a pre-submission
meeting to review the suitability of the data package. Applicants should note that the SAWP will need
an extra month in addition to normal scientific advice timelines to review applications.
• EMA plans to run the pilot until it has completed six scientific advice requests. The Agency will
analyze the outcome after completing the pilot.
Fee and fee reductions:
• EMA charges a fee for scientific advice , which varies depending on the scope of the advice.
• Reductions apply for certain types of medicines and applicants, including a 75% fee reduction for
medicines for orphan medicines and a 90% fee reduction for SMEs.
What EMA publishes on outcomes of scientific advice
• During the development and assessment phases, the detailed advice given to a medicine developer is
not made public. This is because disclosing information at this stage may undermine research and
development efforts and discourage research in new medicines.
• However, information is made available after a medicine obtains marketing authorization. All
medicines whose assessment report report was finalized after 1 January 2019 include a summary of
the developer’s questions and key elements of EMA's advice and whether or not the developer
complied with this advice within the assessment report.
• In addition, the full advice can be made available upon request.
• Scientific advice is also one of the main sources for updating EMA scientific guidelines on medicine
development, including, in particular, disease-specific guidelines.
Committee for Medicinal Products for Human Use (CHMP)
• The Committee for Medicinal Products for Human Use (CHMP) is the European Medicines Agency's
(EMA) committee responsible for human medicines.
• The CHMP replaced the former Committee for Proprietary Medicinal Products (CPMP) in May 2004.
Role of the CHMP:
The CHMP plays a vital role in the authorization of medicines in the European Union (EU). In the centralized
procedure, the CHMP is responsible for :
• conducting the initial assessment of EU-wide marketing authorization applications;
• assessing modifications or extensions ('variations') to an existing marketing authorization;
The CHMP also evaluates medicines authorized at national level referred to EMA for a harmonized
position across the EU.
• considering the recommendations of the Agency's Pharmacovigilance Risk Assessment Committee on
the safety of medicines on the market and when necessary, recommending to the European
Commission changes to a medicine's marketing authorization, or its suspension or withdrawal from
the market.
• In addition, the CHMP and its working parties contribute to the development of medicines and
medicine regulation, by :
 providing scientific advice to companies researching and developing new medicines;
 preparing scientific guidelines and regulatory guidance to help pharmaceutical companies
prepare marketing authorization applications for human medicines;
 cooperate with international partners on the harmonization of regulatory requirements.
Assessments
• The CHMP's assessments are based on a comprehensive scientific evaluation of data. They determine
whether the medicine meets the necessary quality, safety and efficacy requirements and that it has a
positive risk-benefit balance.
• An internal peer-review system safeguards the accuracy and validity of the opinions of the committee.
EUROPEAN MEDICINES AGENCY
What is the European Medicines Agency (EMA)?
 The EMA is the EU regulatory body responsible for the scientific evolution and supervision of
medicines developed by pharmaceutical companies for use in the European union(human and
veterinary).
 The European medicines agency is the regulatory body in Europe that ensure that medicines are safe
and that they work as expected.
 Located in London, the agency is responsible for both human and veterinary medicines and has an
important role in protecting human health in the EU.
HISTORY OF EMA:
 European medical agency was founded in 1995, has worked across the European union(EU) and
globally to protect public and animal health by assessing medications to rigorous scientific standards
and by providing partners and stakeholders with independent, science-based information on medicines.
 EMA has a 20 years track record of ensuring efficacy and safety of human and veterinary medicines
across Europe, and promoting research and innovation in the development of medicines.
 In its first two decades, the agency recommended the authorization of a total of 975 human and 188
veterinary medicines
MISSION OF EMA:
 The mission of the European medicines agency (EMA) is to foster scientific excellence in the
evaluation and supervision of medicines, for the benefit of public and animal health in the European
union(EU).
European Regulatory Network
 The European regulatory system for medicines is unique model in the global regulatory environment.
 This system is based on a network that includes all national medicines regulatory authorities(for both
human and veterinary medicines) from member states in the EU and European economic area, united
in the heads of medicines agencies(HMA), and the European medicines agency working closely
together in an integrated fashion.
 Working together with the national authorities of the 28 EU member states as well as Iceland ,Norway
and Lichtenstein, the agency is a key part of the European regulatory system for medicines.
EU Members:
 Austria  Belgium  Cyprus
 Czech republic
 Denmark
 Estonia
 Finland
 France
 Germany
 Greece
 Hungry
 Ireland
 United kingdom
 Italy
 Latavia
 Lithuania
 Luxembourg
 Malta
 Netherlands
 Poland
 Portugal
 Slovakia
 Slovenia
 Spain
 Sweden
What does the EMA do?
 The agency’s main responsibility is the protection and promotion of public and animal health, by
carrying out scientific evaluations of medicines for human and veterinary use.
 The agency also supervises the safety of medicines in the EU after they have been authorized. It can
also give scientific opinions on medicines at the request of member states or the European commission.
 Provide information to healthcare professionals and patients.
What the EMA does not do?
The European medicines agency does not control:
 Pricing of medicines
 Access to medicines
 Advertising of medicines
 Patents of medicines
 Medical devices
 Homeopathic medicines
 Food supplements
 cosmetics
DRUG APPROVAL PROCESS
 There are two regulatory steps to go through before a drug is approved to be marketed in the European
union.
 These two steps are:
– clinical trial application
– marketing authorization application
 Clinical trial application are approved at the member state level.
 Marketing authorization application are approved at both the member state or centralized levels.
CLINICAL TRIAL APPLICATION:
 EU directive 2001/20/EC(April 2001) sets out the new rules and regulations for the approval and
conducted of clinical trials in Europe.
 A sponsor submits a clinical trial application to the competent authority in each member state where
the trials are to be conducted.
 The component authority has 60 days to review and approve or reject the application.
 Application is in prescribed forms and covers the proposed clinical trial protocol ,manufacturing and
quality controls on the drug, and supporting data, such as,
a) chemical, pharmaceutical and biological date,
b) non-clinical pharmacological and toxicological data,
c) clinical data and previous human experience.
MARKETING AUTHORIZATION:
 Following successful clinical trials, the sponsor has to apply for authorization to market the drug in
Europe.
 Depending on the type of drug product and the intended market, there are, four different types of
marketing authorization application.
1. Centralized procedure.
2. Mutual recognition procedure.
3. National authorization procedures.
4. Decentralized procedure.
Scientific committees:
The EMA committees contain nominated by the medicines regulatory authorities of the EU member states(the
national competent authorities’)
Four committees COMP, CAT, PRAC, PDCO representing patients organizations and these provide important
opportunities for patients to contribute their knowledge and experience in the disease area of interest.
There are many different types of experts who work with the agency’s committees,
• Patients and consumers
• Healthcare professionals
• Academics
• Representatives of learned societies
How the committees work?
 The European Medicines Agency (EMA) has seven scientific committees and a number of working
parties and related groups which conduct the scientific work of the Agency.
 The committee's evaluations of marketing- authorization applications submitted through
the centralized procedure provide the basis for the authorization of medicines in Europe.
 The committees and working parties also contribute to the development of medicines and medicine
regulation, by:
• Providing scientific advice to company researching and developing new medicine.
• Prepare scientific guidelines and regulatory guidance.
• contributing to the harmonization of regulatory requirements n the EU and internationally.
COMMITTEE FOR HUMAN MEDICINAL PRODUCTS(CHMP)
The CHMP is responsible for preparing the agency’s opinion all questions concerning medicines for human
use, in accordance with regulation (EC) no 726/2004.
ROLE OF CHMP: the CHMP vital roles play in marketing procedure for medicines in the European union:
Centralised procedure:
 conducting the initial assessment of medicines for which an EU wide marketing authorization is
sought.
 Post authorization and maintenance activities, including the assessment of any modification or
extensions to an existing marketing authorization.
In cases of mutual recognition procedure:
 The CHMP arbitrates In cases where there is disagreement between member states concerning the
marketing authorization of a particular medicines.
OTHER IMPORTANT ROLES OF CHMP:
 The CHMP publishes a European public assessment report(EPAR) for every centrally authorized
medicines that is granted a marketing authorization;
 It provide provision of assistance to companies researching and developing new medicines.
 The preparation of scientific and regulatory guidelines for the pharmaceutical industry;
 Cooperation with international partners on the harmonisation of regulatory requirement for medicines.
THE COMMITTEE FOR MEDICINAL PRODUCTS FOR VETERINARY USE(CVMP)
• CVMP is responsible for preparing opinions on questions concerning medicines for veterinary use.
ROLE OF CVMP:
The CVMP plays a vital role in the authorization of veterinary medicines in the European Union (EU). In
the centralized procedure the CVMP is responsible for:
• conducting the initial assessment of EU-wide marketing authorization applications;
• post- authorization and maintenance activities, including the assessment of any modifications
or variations to an existing marketing authorization;
• safety monitoring of veterinary medicines on the market and when necessary, recommending to the
European Commission changes to a medicine's marketing authorization, or its suspension or
withdrawal from the market. For more information, see veterinary pharmacovigilance.
COMMITTEE FOR ORPHAN MEDICINAL PRODUCTS(COMP)
The COMP is responsible for evaluating applications for orphan designation. This designation is for medicines
to be developed for the diagnosis, prevention or treatment of rare diseases that are life-threatening or very
serious. In the European Union (EU), a disease is defined as rare if it affects fewer than 5 in 10,000 people
across the EU.
The COMP also advises and assists the European Commission on matters related to orphan medicines,
including:
• developing and establishing an EU-wide policy;
• drawing up detailed guidelines;
• liaising internationally.
COMMITTEE ON HERBAL MEDICINAL PRODUCTS(HMPC)
• HMPC committee responsible for compiling and assessing scientific data on herbal substances,
preparations and combinations, to support the harmonization of the European market.
• The HMPC replaced the Committee for Proprietary Medicinal Products' Working Party on Herbal
Medicinal Products in September 2004.
ROLE OF HMPC:
• The HMPC prepares the Agency's opinions on herbal substances and preparations, along with
information on recommended uses and safe conditions.
• This work supports the harmonization of the European market: national competent authorities are able
to refer to one unique set of information on a herbal substance or preparation when evaluating
marketing applications for herbal medicines.
To support EU Member States, the HMPC focuses on two main tasks:
• establishing EU monographs covering the therapeutic uses and safe conditions of well-established
and/or traditional use for herbal substances and preparations;
• drafting an EU LIST of herbal substances, preparations and combinations thereof for use in traditional
herbal medicinal products.
COMMITTEE FOR ADVANCED THERAPIES(CAT)
• The Committee for Advanced Therapies (CAT) is the European Medicines Agency's (EMA)
committee responsible for assessing the quality, safety and efficacy of advanced therapy medicinal
products (ATMPs) and following scientific developments in the field.
ROLE OF CAT:
• The committee's main responsibility is to prepare a draft opinion on each ATMP application submitted
to EMA,
The CAT also;
• participates in certifying quality and non-clinical data for small and medium-sized enterprises
developing ATMPs;
• participates in providing scientific recommendations on the classification of ATMPs;
• contributes to scientific advice, in cooperation with the Scientific Advice Working Party (SAWP);
• takes part in any procedure delivering advice on the conduct of efficacy follow-
up, pharmacovigilance or risk-management systems for ATMPs;
• advises the CHMP on any medicinal product that may require expertise in ATMPs for the evaluation
of its quality, safety or efficacy;
PHARMACOVIGILANCE RISK ASSESSMENT COMMITTEE(PRAC)
• PRAC is the European Medicines Agency's (EMA) committee responsible for assessing and
monitoring the safety of human medicines.
• The PRAC was formally established in line with the pharmacovigilance legislation which came into
effect in 2012 to help strengthen the safety monitoring of medicines across Europe.
ROLE OF PRAC:
The PRA is responsible for assessing all aspects of risk management of human medicines, including:
• the detection, assessment, minimization and communication of the risk of adverse reactions, while
taking the therapeutic effect of the medicine into account;
• design and evaluation of post-authorisation safety studies;
• pharmacovigilance audit.
PAEDIATRIC COMMITTEE(PDCO)
• The Pediatric Committee (PDCO) is the European Medicines Agency's (EMA) scientific committee
responsible for activities on medicines for children and to support the development of such medicines
in the European Union by providing scientific expertise and defining pediatric needs.
• Established in 2007
ROLE OF PDCO:
• The PDCO's main role is to assess the content of pediatric investigation plans (PIPs), which determine
the studies that companies must carry out in children when developing a medicine. This includes
assessing applications for a full or partial waiver and for deferrals.
The committee other roles include;
• assessing data generated in accordance with agreed PIPs;
• adopting opinions on the quality, safety or efficacy of a medicine for use in the pediatric population,
at the request of the Committee for Medicinal Products for Human Use (CHMP) or a
medicines regulatory authority in a European Union (EU) Member State. The PDCO can give an
opinion if the data have been generated in accordance with an agreed PIP;
Medicines that are mandatory for evaluation at EMA
• Rare diseases
• HIV, cancer, neurodegenerative disorder, diabetes
• Auto-immune diseases, viral diseases
• All biotech products
• Gene therapy
• Monoclonal antibodies
• Other innovative products
The various roles of the EMA:
The Agency responsible for:
• Evaluation of marketing authorization for human and veterinary application submitted by
pharmaceutical companies.
• Coordination of European pharmacovigilance.
• Provision of scientific advice on the development of medicines.
• Evaluation of application for orphan designation in EU.
• Evaluation of pediatrics investigation plans.
• Coordination of member states inspection.
• Provision of good quality and independent information on the medicines it evaluates to patients and
healthcare professionals.
FDA CLINICAL TRIAL GUIDANCE DOCUMENT: GOOD CLINICAL TRIAL PRACTICE
INTRODUCATION
Guidance documents listed below represent the agency's current thinking on the conduct of clinical trials, good
clinical practice and human subject protection.
Guidance documents are not binding for FDA or the public. Guidance should be viewed as recommendations
unless specific regulatory or statutory requirements are cited. An alternative approach may be used if the
approach satisfies the requirements of the applicable statute and regulations.
1. Considerations for the Design and Conduct of Externally Controlled Trials for Drug and Biological
Products
• Provides recommendations to sponsors and investigators considering the use of externally controlled
clinical trials to provide evidence of the safety and effectiveness of a drug product.
• In an externally controlled trial, outcomes in participants receiving the test treatment according to a
protocol are compared to outcomes in a group of people external to the trial who had not received the same


treatment. The external control arm can be a group of people, treated or untreated, from an earlier time
(historical control), or during the same time period (concurrent control) but in another setting.
2. Clinical Investigator Administrative Actions – Disqualification (Guidance for Institutional
Review Boards, Clinical Investigators, and Sponsors)
– Intended to inform institutional review boards (IRBs), clinical investigators, and sponsors about the
administrative action of disqualifying a clinical investigator from participating in studies involving
investigational new drugs (including biologics) or devices.
– FDA may disqualify a clinical investigator from receiving investigational drugs (including biologics) and
devices if FDA determines that the investigator has repeatedly or deliberately violated the agency’s
regulations, or has repeatedly or deliberately submitted false information to the sponsor or FDA in any
required report.
3. Acute Myeloid Leukemia: Developing Drugs and Biological Products for Treatment (Guidance
for Industry; Availability)
– To assist sponsors in the clinical development of drugs and biological products for the treatment of acute
myeloid leukemia (AML).
– Specifically, this guidance addresses FDA’s current thinking regarding the overall development program
and clinical trial designs for the development of drugs to support an indication of treatment of AML,
including indications limited to an individual phase of treatment (e.g., maintenance, transplantation
preparative regimen, etc.).
4.Tissue Agnostic Drug Development in Oncology(Draft Guidance for Industry)
• This guidance provides recommendations to sponsors regarding considerations for tissue agnostic drug
development in oncology. This guidance describes the development of tissue agnostic drugs, scientific
considerations in determining when tissue agnostic oncology drug development may be appropriate, and,
if appropriate, issues to be addressed during such development.
5. Characterizing, Collecting, and Reporting Immune-Mediated Adverse Reactions in Cancer
Immunotherapeutic Clinical Trials
• Adverse events that are consistent with an autoimmune etiology should be evaluated as potential immune-
mediated adverse reactions (imAR) to guide patient management and inform the drug labeling or
investigator brochure, as applicable.
• The purpose of this guidance, the term imAR refers to adverse reactions that occurred in the context of
exposure to a cancer immunotherapeutic drug and are consistent with the development of an autoimmune
reaction, and are not attributable to another cause (e.g., infection, trauma, other drugs).
6. Ethical Considerations for Clinical Investigations of Medical Products Involving Children (Draft
Guidance for Industry, Sponsors, and IRBs)
• This guidance describes the FDA’s current thinking regarding ethical considerations for clinical
investigations of medical products in children.
• Clinical investigations in children are essential for obtaining data on the safety and effectiveness of drugs,
biological products, and medical devices in children and to protect children from the risks associated with
exposure to medical products that may be unsafe or ineffective.
• Children are a vulnerable population who cannot consent for themselves and who therefore are afforded
additional safeguards when participating in a clinical investigation. Such safeguards are an essential
requirement for the initiation and conduct of pediatric investigations as part of a medical product
development program.
7. Submitting Documents Using Real-World Data and Real-World Evidence to FDA for Drug and
Biological Product
• This guidance encourages sponsors and applicants to identify in their submission cover letters certain uses
of RWD/RWE. This guidance does not address FDA’s substantive review of the RWD/RWE submitted as
part of the Agency’s standard review process.
• This guidance applies to submissions for investigational new drug applications (INDs), new drug
applications (NDAs), and biologics license applications (BLAs) that contain RWD/RWE intended to
support a regulatory decision regarding product safety and/or effectiveness.
8. Digital Health Technologies for Remote Data Acquisition in Clinical Investigations
• This guidance provides recommendations to sponsors, investigators, and other stakeholders on the use of
digital health technologies (DHTs) to acquire data remotely from participants in clinical investigations
evaluating medical products.
• DHTs may take the form of hardware and/or software and may be used to gather health-related information
from study participants and transmit that information to study investigators and/or other authorized parties
to evaluate the safety and effectiveness of medical products.
9. Investigator Responsibilities – Safety Reporting for Investigational Drugs and Devices (Draft
Guidance for Industry)
• This guidance is intended to help clinical investigators comply with the following safety reporting
requirements: (1)Investigational new drug
application (IND) studies under § 312.64(b) (21 CFR 312.64(b).
(2) Investigational device exemption (IDE) studies under § 812.150 (21 CFR 812.150).
• Recommendations are provided to help investigators identify the following:
1. For drugs — Identify safetyinformation that is considered an unanticipated problem involving risk to human
subjects or others and that therefore requires prompt reporting to institutional review boards (IRBs) under §
312.66 (21 CFR 312.6)
2. For devices — Identify safety information that meets the requirements for reporting unanticipated adverse
device effects (UADEs) to sponsors and IRBs under § 812.150(a)(1) (21 CFR 812.150(a)(1))
10. Sponsor Responsibilities - Safety Reporting Requirements and Safety Assessment for IND and
Bioavailability/Bioequivalence Studies Draft Guidance for Industry
• This guidance provides recommendations to help sponsors comply with the expedited safety reporting
requirements for human drug and biological products that are being investigated .
(1) under an investigational new drug application (IND) (21 CFR 312.32) or
(2) as part of a bioavailability (BA) or bioequivalence (BE) study that is exempt from the IND
requirements (21 CFR 312.64(b) and 320.31(d)(3)).
• This guidance defines terms used for safety reporting, makes recommendations on when and how to submit
a safety report, and provides information on other safety reporting issues raised by sponsors
11. Information Sheet Guidance for Sponsors, Clinical Investigators, and IRBs Frequently Asked
Questions Statement of Investigator (Form FDA 1572) (Revision 1)Draft Information
• This guidance is intended to assist sponsors, clinical investigators, and institutional review boards (IRBs)
involved in clinical investigations of investigational drugs and biological products. This guidance applies
to clinical investigations conducted under 21 CFR part 312 (investigational new drug application (IND)
regulations) and describes how to complete the Statement of Investigator (Form FDA 1572).
12. Certificates of Confidentiality Guidance for Sponsors, Sponsor-Investigators, Researchers,
Industry, and Food and Drug Administration Staff
This guidance describes FDA implementation of the revised provisions applicable to the request for, and
issuance of, a Certificate of Confidentiality (CoC).
A CoC is intended to help protect the privacy of human subject research participants from whom identifiable,
sensitive information is being collected or used in furtherance of the research
13. Enhancing the Diversity of Clinical Trial Populations — Eligibility Criteria, Enrollment Practices,
and Trial Designs Guidance for Industry
• This guidance recommends approaches that sponsors of clinical trials intended to support a new drug
application or a biologics license application can take to increase enrollment of underrepresented
populations in their clinical trials.
14. Civil Money Penalties Relating to the ClinicalTrials.gov Data Bank Guidance for Responsible
Parties, Submitters of Certain Applications and Submissions to FDA, and FDA Staff
• The guidance is intended for FDA staff, responsible parties, and submitters of certain applications and
submissions to FDA.
• This guidance document is intended to describe the current thinking of FDA regarding civil money
penalties. That section authorizes FDA to assess civil money penalties against responsible parties and/or
submitters of certain applications and submissions to FDA regarding drug products, biological products,
and device products.
15.Demonstrating Substantial Evidence of Effectiveness for Human Drug and Biological Products
• This document is intended to provide guidance to applicants planning to file new drug applications
(NDAs), biologics license applications (BLAs), or applications for supplemental indications on the
evidence to be provided to demonstrate effectiveness
• This guidance complements and expands on the 1998 guidance entitled Providing Clinical Evidence of
Effectiveness for Human Drug and Biological Products (the 1998 guidance).
16. Pregnancy, Lactation, and Reproductive Potential: Labeling for Human Prescription Drug and
Biological Products-Content and Format
• This guidance is intended to assist applicants in complying with the content and format requirements for
the Pregnancy, Lactation, and Females and Males of Reproductive Potential subsections of labeling for
human prescription drug and biological products.
• This draft guidance is intended to advance scientific research in pregnant women, and discusses issues
that should be considered within the framework of human subject protection regulations.
• This guidance provides information and recommendations for preparing subsections 8.1 Pregnancy, 8.2
Lactation, and 8.3 Females and Males of Reproductive Potential of the USE IN SPECIFIC
POPULATIONS section.
17. Use of Electronic records and Electronic signatures in Clinical Investigation:
• The goals of the draft guidance are to clarify and update recommendations for applying and implementing
part 11 requirements in the current environment of electronic systems used in clinical investigations and
to encourage and facilitates the use of electronic records and systems to improve the quality and efficiency
of clinical investigations.
• The guidance discusses the procedures that may be followed to help ensure that electronic records and
electronic signatures meet FDA requirements
18. Adaptive Design Clinical Trials for Drugs and Biologics Guidance for Industry
• This document provides guidance to sponsors and applicants submitting investigational new drug
applications (INDs), new drug applications (NDAs), biologics licensing applications (BLAs), or
supplemental applications on the appropriate use of adaptive designs for clinical trials to provide evidence
of the effectiveness and safety of a drug or biologic.
• The guidance describes important principles for designing, conducting, and reporting the results from an
adaptive clinical trial.
• The guidance also advises sponsors on the types of information to submit to facilitate FDA evaluation of
clinical trials with adaptive designs, including Bayesian adaptive and complex trials that rely on computer
simulations for their design.
19.Postmarketing Studies and Clinical Trials—Implementation of Section 505(o)(3) of the Federal
Food, Drug, and Cosmetic Act Guidance for Industry
• This guidance provides information on the implementation of section 505(o)(3) of the Federal Food, Drug,
and Cosmetic Act (the FD&C Act) (21 U.S.C. 355(o)(3)), which authorizes FDA to require certain
postmarketing studies and clinical trials for prescription drugs approved under section 505(c) of the FD&C
Act and biological products approved under section 351 of the Public Health Service Act (the PHS Act)
(42 U.S.C. 262)
20.Humanitarian Device Exemption (HDE) Programme
• This programmatic guidance addresses commonly asked questions about HDEs and Humanitarian Use
Devices (HUDs), including FDA actions on HDE applications, post-approval requirements, and special
considerations for devices marketed under the HDE Program.
21. A Risk-Based Approach to Monitoring of Clinical Investigations Questions and Answers
• The draft guidance provides information to sponsors on risk-based approaches to monitoring of
investigational studies of human drug and biological products, medical devices, and combinations thereof.
This guidance expands on the guidance for industry entitled “Oversight of Clinical Investigations—A
Risk-Based Approach to Monitoring” (August 2013) (the RBM Guidance) by providing additional
guidance to facilitate sponsors' implementation of risk-based monitoring.
22. Enrichment Strategies for Clinical Trials to Support Approval of Human Drugs and Biological
Products
• The purpose of this guidance is to assist industry in developing enrichment strategies that can be used in
clinical investigations intended to demonstrate effectiveness (and in some cases safety) of human drugs
and biological products.
• This guidance defines several types of enrichment strategies, provides examples of potential clinical trial
designs, and discusses potential regulatory considerations when using enrichment strategies in clinical
trials.
25. E17 General Principles for Planning and Design of Multi-Regional Clinical Trials
• With the increasing globalization of drug development, it has become important that data from
multiregional clinical trials (MRCTs) can be accepted by regulatory authorities across regions and
countries as the primary source of evidence to support marketing approval of drugs (medicinal products).
The purpose of this guidance is to describe general principles for the planning and design of MRCTs with
the aim of increasing the acceptability of MRCTs in global regulatory submissions.
26. Institutional Review Board (IRB) Written Procedures
• This guidance is intended for institutions and institutional review boards (IRBs) responsible for review
and oversight of human subject research under the HHS and FDA regulations.
• The purpose of this guidance is to assist staff at institutions and IRBs who are responsible for preparing
and maintaining written procedures. The guidance includes a Written procedures Checklist (also referred
to in this guidance as the Checklist) that incorporates the HHS and FDA regulatory requirements for
written procedures for the IRB and recommendations on the type of operational details to include to
support each of these requirements. In addition, the Checklist includes some additional topics the
institution/IRB may consider when developing comprehensive procedures.
27. E11(R1) Addendum: Clinical Investigation of Medicinal Products in the Pediatric Population
• This addendum does not alter the scope of the original guidance. ICH E11 (2000), including this addendum
(R1); is not intended to be comprehensive; other ICH guidances , as well as documents from regulatory
authorities worldwide, the World Health Organization (WHO), and pediatric societies, provide additional
detail. The purpose of the addendum is to complement and provide clarification and current regulatory
perspective on topics in pediatric drug development.
28.Pregnant Women: Scientific and Ethical Considerations for Inclusion in Clinical Trials
• This guidance supports an informed and balanced approach to gathering data on the use of drugs and
biological products during pregnancy through judicious inclusion of pregnant women in clinical trials and
careful attention to potential fetal risk.
• This draft guidance is intended to serve as a focus for continued discussions among various entities such
as the Agency, pharmaceutical manufacturers, the academic community, institutional review boards
(IRBs), and others who are involved with the conduct of clinical trials in pregnant women.
29. E6(R2) Good Clinical Practice: Integrated Addendum to ICH E6(R1)
• Good Clinical Practice (GCP) is an international ethical and scientific quality standard for designing,
conducting, recording and reporting trials that involve the participation of human subjects. Compliance
with this standard provides public assurance that the rights, safety, and well-being of trial subjects are
protected, consistent with the principles that have their origin in the Declaration of Helsinki, and that the
clinical trial data are credible.
• The objective of this ICH GCP guidance is to provide a unified standard for the European Union, Japan,
and the United States to facilitate the mutual acceptance of clinical data by the regulatory authorities in
these jurisdictions.
30.Investigational IVDs Used in Clinical Investigations of Therapeutic Products
• This guidance documents is intended to 32 inform stakeholders, including institutional review boards or
institutional review 33 committees (referred to hereafter as IRBs) reviewing clinical investigations, and
sponsors 34 that therapeutic product4 trials that include investigational IVDs are subject to FDA’s 35
Investigational Device Exemption (IDE) regulation (21 CFR Part 812), regardless of the 36 source or
manufacturer of the device, in addition to the Investigational New Drug (IND) 37 regulation (21 CFR Part
312).
31. Waiver of IRB Requirements for Drug and Biological Product Studies
• This document supersedes Waiver of IRB Requirements (September 1998) Office of Health Affairs, Food
and Drug Administration. That document has been revised to make it consistent with the Agency’s good
guidance practices regulations (21 CFR 10.115).
32. Individual Patient Expanded Access Applications: Form FDA 3926
• This guidance describes From FDA 39262
(Individual Patient Expanded Access - Investigational New
Drug Application (IND)), which is available for licensed physicians to use for expanded access requests
for individual patient INDs.
• This guidance and Form FDA 3926 do not apply to other types of expanded access requests, including
request for expanded access for medical devices.
33. Clinical Considerations for Investigational Device Exemptions (IDEs) for Neurological Devices
Targeting Disease Progression and Clinical Outcomes
• This guidance is intended to apply to neurological medical devices that are designed to slow, stop, or
reverse the progression of disease and result in clinically meaningful patient outcomes. This guidance
provides general study design considerations for clinical trials that investigate neurological devices using
biological markers and clinical outcome assessments.
34. IRB Waiver or Alteration of Informed Consent for Clinical Investigations Involving No More Than
Minimal Risk to Human Subjects
• This guidance is for immediate implementation.
• FDA is issuing this guidance for immediate implementation in accordance with 21 CFR 10.115(g)(3)
without initially seeking prior comment. The Agency has determined that prior public participation is not
feasible or appropriate because this guidance presents a less burdensome policy that is consistent with the
public health.
• Although this guidance document is immediately in effect, it remains subject to public comment in
accordance with the Agency’s good guidance practices regulation (21 CFR 10.115).You may submit
comments or suggestions at any time. Submit electronic comments to https://www.regulations.gov.
35. Use of Electronic Records and Electronic Signatures in Clinical Investigations Under 21 CFR Part
11 – Questions and Answers
• The purpose of this guidance is to assist industry in developing enrichment strategies that can be used in
clinical investigations intended to demonstrate effectiveness (and in some cases safety) of human drugs
and biological products.
• This guidance defines several types of enrichment strategies, provides examples of potential clinical trial
designs, and discusses potential regulatory considerations when using enrichment strategies in clinical
trials.
36.Use of Electronic Informed Consent in Clinical Investigations – Questions and Answers
• This document provides guidance to sponsors, clinical investigators, institutional review boards (IRBs),
contract research organizations (CROs), and other interested parties on the use of electronic records and
electronic signatures in clinical investigations of medical products under 21 CFR part 11, Electronic
Records; Electronic Signatures.
• This guidance clarifies, updates, and expands upon recommendations in the guidance for industry Part 11,
Electronic Records; Electronic Signatures – Scope and Application (referred to as the 2003 part 11
guidance) that pertain to clinical investigations conducted under 21 CFR parts 312 and 812. Thus, this
guidance is limited to outlining the scope and application of part 11 requirements for clinical investigations
of medical products.
37. Collection of Race and Ethnicity Data in Clinical Trials
• The purpose of this guidance is to provide FDA expectations for and recommendations on use of a
standardized approach for collecting and reporting race and ethnicity data in submissions for clinical trials
for FDA regulated medical products conducted in the United States and abroad.
• Using standard terminology for age, sex, gender, race, and ethnicity helps ensure that subpopulation data
is collected consistently.
38. Early Clinical Trials With Live Biotherapeutic Products: Chemistry, Manufacturing, and Control
Information
• This guidance is intended to provide sponsors of Investigational New Drug Applications (INDs) with
recommendations on submissions for early clinical trials with live biotherapeutic products (LBPs) in the
United States (U.S.), including LBPs lawfully marketed as foods (such as conventional foods and dietary
supplements) in the U.S. and proposed for clinical uses regulated under section 351 of the Public Health
Service (PHS) Act (42 U.S.C. 262).
39. Expanded Access to Investigational Drugs for Treatment Use - Questions and Answers
• This guidance provides information for industry, researchers, physicians, institutional review boards
(IRBs), and patients about the implementation of FDA’s regulations on expanded access to investigational
drugs for treatment use under an investigational new drug application (IND) (21 CFR part 312, subpart I),
which went into effect on October 13, 2009. Since 2009, FDA has received a number of questions
concerning implementation of the regulations. As a result, FDA is providing guidance in a question and
answer format, addressing the most frequently asked questions and separate document for answer.
40. Informed Consent
• This draft guidance is intended to assist IRBs, clinical investigators, and sponsors involved in clinical
investigations of FDA-regulated products in carrying out their responsibilities related to informed consent.
The guidance provides the Agency's recommendations and requirements for informed consent to assure
the protection of the rights and welfare of human subjects in clinical investigations.
41.Evaluation of Sex-Specific Data in Medical Device Clinical Studies - Guidance for Industry and Food
and Drug Administration Staff
• This documents provides guidance on the study and evaluation of sex-specific data in medical device
clinical studies. The purpose of this guidance is to outline the FDA’s expectations regarding sex-specific
patient enrollment, data analysis, and reporting of study information. The primary intent is to improve the
quality and consistency of available data regarding the performance of medical devices in both sexes by
encouraging appropriate enrollment by sex in clinical studies of devices, and that data from such studies
is appropriately analyzed by sex. This information can be of benefit to patients and their medical providers,
as well as clinical researchers and others.
42. Distribution of In Vitro Diagnostic Products Labeled for Research Use Only or Investigational Use
Only
• FDA is issuing this guidance document to provide the current thinking of the Center for Devices and
Radiological Health (CDRH) and the Center for Biologics Evaluation and Research (CBER) on when in
vitro diagnostic (IVD) products are properly labeled “for research use only” (RUO) or “for investigational
use only” (IUO).
43. Design Considerations for Pivotal Clinical Investigations for Medical Devices
• This guidance is intended to provide guidance to those involved in designing clinical studies intended to
support pre-market submissions for medical devices and FDA staff who review those submissions.
• This guidance document describes different study design principles relevant to the development of medical
device clinical studies that can be used to fulfill pre-market clinical data requirements. This guidance is
not intended to provide a comprehensive tutorial on the best clinical and statistical practices for
investigational medical device studies.
44. Electronic Source Data in Clinical Investigations
• This guidance promotes capturing source data in electronic form, and it is intended to assist in ensuring
the reliability, quality, integrity, and traceability of data from electronic source to electronic regulatory
submission.
• This guidance addresses source data in clinical investigations used to fill the predefined fields in an
electronic case report form (eCRF), according to the protocol. The guidance discusses the following topics
related to electronic source data:
a. Identification and specification of authorized source data originators
b. Creation of data element identifiers to facilitate examination of the audit trail by sponsors, FDA,
and other authorized parties
c. Ways to capture source data into the eCRF using either manual or electronic methods
d. Clinical investigator(s) responsibilities with respect to reviewing and retaining electronic data
e. Use and description of computerized systems in clinical investigations
45.Investigational New Drug Applications (INDs) - Determining Whether Human Research Studies Can
Be Conducted Without an IND
• This guidance describes when an IND is required, specific situations in which an IND is not required, and
a range of issues that, in FDA’s experience, have been the source of confusion or misperceptions about the
application of the IND regulations.3 This guidance addresses only whether an IND is needed. If your study
also involves the use of a device, you should determine whether such use is subject to 21 CFR part 812
(the IDE regulations).
46.E3 Structure and Content of Clinical Study Reports - Questions and Answers (R1)
• Since the ICH E3 guidance was made final, experiences implementing the guidance in the ICH regions
have given rise to requests for clarification. This question and answer (Q&A) document is intended to
facilitate implementing the ICH E3 guidance by clarifying key issues.
47. Exception from Informed Consent Requirements for Emergency Research
• The term “emergency research” is used throughout this guidance to refer to these investigations. These
investigations involve human subjects who have a life-threatening medical condition that necessitates
urgent intervention (for which available treatments are unproven or unsatisfactory), and who, because of
their condition (e.g., traumatic brain injury) cannot provide informed consent.
• These investigations involve human subjects who have a life-threatening medical condition that
necessitates urgent intervention (for which available treatments are unproven or unsatisfactory), and who,
because of their condition (e.g., traumatic brain injury) cannot provide informed consent. The research
must have the prospect of direct benefit to the patient and must involve an investigational product that, to
be effective, must be administered before informed consent from the subject or the subject’s legally
authorized representative can be obtained and in which there is no reasonable way to identify prospectively
individuals likely to become eligible for participation.
• This guidance finalizes the draft guidance entitled, “Guidance for Institutional Review Boards, Clinical
Investigators, and Sponsors: Exception from Informed Consent for Emergency Research,” dated July 2006
(published on August 29, 2006).
48.Financial Disclosure by Clinical Investigators
• This guidance is intended to assist clinical investigators, industry, and FDA staff in interpreting and
complying with the regulations governing financial disclosure by clinical investigators, 21 CFR part
54. This document is a revision of the Guidance for Industry: Financial Disclosure by Clinical
Investigators dated March 20, 2001.
• In order to address issues raised by the Office of the Inspector General (OIG), Department of Health and
Human Services, in its report, OEI-05-07-00730, The Food and Drug Administration’s Oversight of
Clinical Investigators’ Financial Information as well as questions FDA has received from industry and the
public, FDA issued a revised guidance in draft in May 2011 for public comment.
• Comments were received from 13 individuals and entities, which were considered in preparing this final
guidance.
• FDA encourages applicants and sponsors to contact the agency for advice concerning specific
circumstances regarding financial disclosures that may raise concerns as early in the product development
process as possible.
49.Safety Reporting Requirements for INDs (Investigational New Drug Applications) and BA/BE
(Bioavailability/Bioequivalence) Studies
• This guidance is intended to help sponsors and investigators comply with the requirements for
investigational new drug (IND) safety reporting and safety reporting for bioavailability (BA) and
bioequivalence (BE) studies under 21 CFR 312.32, 312.64(b), and 320.31(d)(3).
• This document provides guidance to sponsors and investigators on expedited safety reporting requirements
for human drug and biological products that are being investigated under an IND and for drugs that are the
subjects of BA and BE studies that are exempt from the IND requirements. This guidance defines terms
used for safetyreporting, makes recommendations on when and how to submit a safety report, and provides
advice on other safety reporting issues that have arisen from sponsors and investigators.
50. FDA Acceptance of Foreign Clinical Studies Not Conducted Under an IND: Frequently Asked
Questions
• This addendum does not alter the scope of the original guidance. ICH E11 (2000), including this addendum
(R1); is not intended to be comprehensive; other ICH guidances , as well as documents from regulatory
authorities worldwide, the World Health Organization (WHO), and pediatric societies, provide additional
detail. The purpose of the addendum is to complement and provide clarification and current regulatory
perspective on topics in pediatric drug development.
51. E7 Studies in Support of Special Populations; Geriatrics; Questions and Answers
• The ICH guidance E7 Studies in Support of Special Populations: Geriatrics provides recommendations on
special considerations that apply in the design and conduct of clinical trials of medicines that are likely to
have significant use in the elderly. Since the E7 guidance was made final, experiences implementing the
guidance in the ICH regions have given rise to requests for clarification. This question and answer (Q&A)
document is intended to clarify key issues.
52. IRB Continuing Review After Clinical Investigation Approval
• This guidance is intended to assist institutional review boards (IRBs) in carrying out their continuing
review responsibility under 21 CFR 56.108(a) and 56.109(f) by providing recommendations regarding the
criteria, process, and frequency of continuing review to assure the protection of the rights and welfare of
human subjects enrolled in clinical investigations.
• This guidance should also help clinical investigators and sponsors better understand their responsibilities
related to continuing review. This document supersedes the Information Sheet, Continuing Review After
Study Approval (September 1998, Office of Health Affairs, FDA). To enhance human subject protection
and reduce regulatory burden, the Department of Health and Human Services (HHS), Office for Human
Research Protections (OHRP) and FDA have been actively working to harmonize the agencies’ regulatory
requirements and guidance for human subject research. This guidance document was developed as a part
of these efforts.
53. Questions and Answers on Informed Consent Elements, 21 CFR § 50.25(c)
• FDA has prepared this guidance in accordance with section 212 of the Small Business Regulatory
Enforcement Fairness Act. It is intended to help small businesses better understand the new informed
consent requirements set forth in 21 CFR § 50.25(c).
54. Exculpatory Language in Informed Consent
• This document provides guidance on the regulatory prohibition on the inclusion of exculpatory language
in informed consent. The document includes examples of language that OHRP and FDA consider
acceptable as well as examples of language that the agencies would consider exculpatory.
55. Radioactive Drug Research Committee: Human Research Without An Investigational New Drug
Application
• This guidance is intended to provide information for those using radioactive drugs for certain research
purposes to help determine whether research studies can be conducted under 21 CFR 361. Prescription
Drugs for Human Use Generally Recognized as Safe and Effective and Not Misbranded: Drugs Used in
Research, or whether research studies must be conducted under 21 CFR part 312, Investigational New
Drug Application (IND).
56. In Vitro Diagnostic (IVD) Device Studies - Frequently Asked Questions
• The information in this guidance document is also pertinent to investigators who participate in IVD studies
and to institutional review boards (IRB) that review and approve such studies. The document is intended
to facilitate the movement of new IVD technology from the investigational stage to the marketing stage.
57. Frequently Asked Questions – Statement of Investigator (Form FDA 1572)
• This guidance is intended to assist sponsors, clinical investigators, and institutional review boards (IRBs)
involved in clinical investigations of investigational drugs and biologics. This guidance applies to clinical
investigations conducted under 21 CFR Part 312 (Investigational New Drug Applications or IND
regulations). It describes how to complete the Statement of Investigator form (Form FDA 1572).
• The Food and Drug Administration (FDA or agency) has received a number of questions about Form FDA
1572. The most frequently asked questions are answered below. If you do not see your question answered
here, you may submit it to gcp.questions@fda.hhs.gov or druginfo@fda.hhs.gov
58. FDA Inspections of Clinical Investigators
• This guidance is intended to provide information about FDA inspections of clinical investigators
conducted under FDA’s Bioresearch Monitoring (BIMO) Program. This document supersedes FDA’s
Information Sheet Guidance, "FDA Inspections of Clinical Investigators," dated January 2006. This
document has been revised to provide updated information and is being issued in accordance with the
agency’s regulations on Good Guidance Practices (21 CFR 10.115).
59.Patient-Reported Outcome Measures: Use in Medical Product Development to Support Labeling
Claims
• This guidance describes how the Food and Drug Administration (FDA) reviews and evaluates existing,
modified, or newly created patient-reported outcome (PRO) instruments used to support claims in
approved medical product labeling. A PRO instrument (i.e., a questionnaire plus the information and
documentation that support its use) is a means to capture PRO data used to measure treatment benefit or
risk in medical product clinical trials.
• This guidance does not address the use of PRO instruments for purposes beyond evaluation of claims made
about a medical product in labeling. This guidance also does not address disease-specific issues. Guidance
on clinical trial endpoints for specific diseases can be found on various FDA Web sites.
60.Investigator Responsibilities — Protecting the Rights, Safety, and Welfare of Study Subjects
• This guidance provides an overview of the responsibilities of a person who conducts a clinical
investigation of a drug, biological product, or medical device (an investigator as defined in 21 CFR
312.3(b) and 21 CFR 812.3(i)). The goal of this guidance is to help investigators better meet their
responsibilities with respect to protecting human subjects and ensuring the integrity of the data from
clinical investigations. This guidance is intended to clarify for investigators and sponsors FDA’s
expectations concerning the investigator’s responsibility (1) to supervise a clinical study in which some
study tasks are delegated to employees or colleagues of the investigator or other third parties and (2) to
protect the rights, safety, and welfare of study subjects.
61. Frequently Asked Questions - IRB Registration
• This guidance is intended to assist institutional review boards (IRBs) in complying with the new
requirement for IRB registration. (See 74 FR 2358 (Jan. 15, 2009)) This requirement is an amendment to
Part 56, Institutional Review Boards, (21 CFR 56.106), that requires each IRB in the United States (U.S.)
that reviews FDA-regulated studies to register.
• IRB registration information is entered into an Internet-based registration system maintained by the
Department of Health and Human Services (HHS). This system is a modification of the one used by the
Office for Human Research Protections (OHRP) for registration of IRBs that are designated by institutions
under Federal wide Assurances (FWAs). OHRP has issued a similar rule requiring IRBs designed under
FWAs to register or update their registration information at this modified site. (See 74 FR 2399 (Jan. 15,
2009))
62.Adverse Event Reporting to IRBs — Improving Human Subject Protection
• This guidance is intended to assist the research community in interpreting requirements for submitting
reports of unanticipated problems, including certain adverse events reports, to the institutional review
board (IRB) under Title 21 of the Code of Federal Regulations (21 CFR) part 56 (Institutional Review
Boards), part 312 (Investigational New Drug Application), and part 812 (Investigational Device
Exemptions). Specifically, the guidance provides recommendations for sponsors and investigators
conducting investigational new drug (IND) trials to help them differentiate between those adverse events
that are unanticipated problems that must be reported to an IRB and those that are not. The guidance also
makes suggestions about how to make communicating adverse events information to IRBs more efficient.
63. Data Retention When Subjects Withdraw from FDA-Regulated Clinical Trials
• This guidance is intended for sponsors, clinical investigators and institutional review boards (IRBs). It
describes the Food and Drug Administration’s (FDA) longstanding policy that already-accrued data,
relating to individuals who cease participating in a study, are to be maintained as part of the study data.
This pertains to data from individuals who decide to discontinue participation in a study, who are
withdrawn by their legally authorized representative, as applicable, or who are discontinued from
participation by the clinical investigator. This policy is supported by the statutes and regulations
administered by FDA as well as ethical and quality standards applicable to clinical research. Maintenance
of these records includes, as with all study records, safeguarding the privacy and confidentiality of the
subject’s information.
64.Current Good Manufacturing Practice for Phase 1 Investigational Drugs
• This guidance is intended to assist in applying current good manufacturing practice (CGMP) required
under section 501(a)(2)(B) of the Federal Food, Drug, and Cosmetic Act (FD&C Act) in the manufacture
of most investigational new drugs (IND) used in phase 1 clinical trials. These drugs, which include
biological drugs, are exempt from complying with 21 CFR part 211 under 21 CFR 210.2(c) (referred to as
phase 1 investigational drugs).
• Because a phase 1 clinical trial initially introduces an investigational new drug into human subjects,
appropriate CGMP help ensure subject safety. This guidance applies, as part of CGMP, quality control
(QC) principles to the manufacture of phase 1 investigational drugs (i.e., interpreting and implementing
CGMP consistent with good scientific methodology), which foster CGMP activities that are more
appropriate for phase 1 clinical trials, improve the quality of phase 1 investigational drugs, and facilitate
the initiation of investigational clinical trials in humans while continuing to protect trial subjects.
65. Guidance on Informed Consent for In Vitro Diagnostic Device Studies Using Leftover Human
Specimens that are Not Individually Identifiable
• FDA is issuing this guidance to inform sponsors, institutional review boards (IRBs), clinical investigators,
and agency staff that the FDA intends to exercise enforcement discretion, under certain circumstances,
with respect to its current regulations governing the requirement for informed consent when human
specimens are used for FDA-regulated in vitro diagnostic (IVD) device investigations. As described below,
FDA does not intend to object to the use, without informed consent, of leftover human specimens --
remnants of specimens collected for routine clinical care or analysis that would otherwise have been
discarded -- in investigations that meet the criteria for exemption from the Investigational Device
Exemptions (IDE) regulation at 21 CFR 812.2(c)(3), as long as subject privacy is protected by using only
specimens that are not individually identifiable. FDA also intends to include in this policy specimens
obtained from specimen repositories and specimens that are leftover from specimens previously collected
for other unrelated research, as long as these specimens are not individually identifiable.
66. Establishment and Operation of Clinical Trial Data Monitoring Committees
• This guidance discusses the roles, responsibilities and operating procedures of Data Monitoring
Committees (DMCs) (also known as Data and Safety Monitoring Boards (DSMBs) or Data and Safety
Monitoring Committees (DSMCs)) that may carry out important aspects of clinical trial monitoring. This
guidance is intended to assist clinical trial sponsors in determining when a DMC may be useful for study
monitoring, and how such committees should operate. We recognize that in many clinical trials the sponsor
delegates some decision-making regarding the design and conduct of the trial to some other entity such as
a steering committee (see Section 3.2) or contract research organization (CRO) (see 21 Code of Federal
Regulations (CFR) 312.3(b)). This document, while pertaining primarily to the sponsor with regard to trial
management and decision-making, may also be relevant to any individual or group to whom the sponsor
has delegated applicable management responsibilities (see Section 3). This guidance finalizes the draft
guidance entitled "Guidance for Clinical Trial Sponsors: On the Establishment and Operation of Clinical
Trial Data Monitoring Committees" dated November 2001.
67. Clinical Studies Section of Labeling for Human Prescription Drug and Biological Products —
Content and Format
• This guidance is intended to assist applicants in deciding (1) what studies should be included in the
CLINICAL STUDIES section of prescription drug labeling, (2) how to describe individual studies, and
(3) how to present study data, including presentation of data in graphs and tables. This guidance is intended
to make the CLINICAL STUDIES section of labeling, as described in the final rule amending the
requirements for the content and format of labeling for human prescription drug and biological products
(21 CFR 201.56 and 201.57), more useful, and to promote consistency in the content and format of the
section across drug product classes and within drug classes and indications.
• This guidance also calls attention to the advertising and promotional implications of data and statements
contained in the CLINICAL STUDIES section.
68. Exploratory IND Studies
• For the purposes of this guidance the phrase exploratory IND study is intended to describe a clinical trial
that is conducted early in phase 1, involves very limited human exposure, and has no therapeutic or
diagnostic intent (e.g., screening studies, microdose studies).
• Such exploratory IND studies are conducted prior to the traditional dose escalation, safety, and tolerance
studies that ordinarily initiate a clinical drug development program. The duration of dosing in an
exploratory IND study is expected to be limited (e.g., 7 days). This guidance applies to early phase 1
clinical studies of investigational new drug and biological products that assess feasibility for further
development of the drug or biological product
69. Frequently Asked Questions About Medical Devices
• This guidance is intended to assist clinical investigators and institutional review boards (IRBs) by
answering common questions FDA receives concerning medical devices. This document
supersedes Medical Devices, Frequently Asked Questions about IRB Review of Medical Devices,
and Emergency Use of Unapproved Medical Devices (September 1998) Office of Health Affairs, Food
and Drug Administration. This document was revised to make it consistent with the Agency’s good
guidance practices regulations (21 CFR 10.115).
70.Significant Risk and Nonsignificant Risk Medical Device Studies
• This guidance is intended to provide advice to sponsors, clinical investigators, and institutional review
boards (IRBs) on how to determine the differences between significant risk and non significant risk
medical device studies. This document supersedes Significant Risk and Non significant Risk Medical
Device Studies (September 1998) Office of Health Affairs, Food and Drug Administration.
• This document was revised to update the list of examples of significant and non significant risk devices,
to clarify the IRB’s responsibilities when making the risk determination for investigational medical
devices, and to make the guidance consistent with the Agency’s good guidance practices regulations (21
CFR 10.115).
71. FDA Institutional Review Board Inspections
• This guidance is intended to provide information about FDA inspections of Institutional Review Boards
(IRBs) conducted under FDA’s Bioresearch Monitoring (BIMO) Program. This document supersedes
another document, "FDA Institutional Review Board Inspections," issued in September 1998, by the
former Office of Health Affairs, FDA. This document has been revised to provide updated information
and is being issued in accordance with the Agency’s regulations on Good Guidance Practices (21 CFR
10.115).
72. Pre - marketing Risk Assessment
• This document provides guidance to industry on good risk assessment practices during the development
of prescription drug products, including biological drug products.2 This is one of three guidances that were
developed to address risk management activities. Specifically, this document discusses the generation,
acquisition, analysis, and presentation of premarketing safety data.
73. Development and Use of Risk Minimization Action Plans
• This document provides guidance to industry on the development, implementation, and evaluation of risk
minimization action plans for prescription drug products, including biological drug products. In particular,
it gives guidance on
(1) initiating and designing plans called risk minimization action plans or Risk MAPs to minimize
identified product risks,
(2) selecting and developing tools to minimize those risks,
(3) evaluating Risk MAPs and monitoring tools, and
(4) communicating with FDA about Risk MAPs, and
(5) the recommended components of a Risk MAP submission to FDA.
74. Good Pharmacovigilance Practices and Pharmaco epidemiologic Assessment
• This document provides guidance to industry on good pharmacovigilance practices and
pharmacoepidemiologic assessment of observational data regarding drugs, including biological drug
products (excluding blood and blood components). Specifically, this document provides guidance on
(1) safety signal identification,
(2) pharmacoepidemiologic assessment and safety signal interpretation, and
(3) pharmacovigilance plan development.
21 CFR: PART 320 (BIOAVAILABILITY AND BIOEQUIVALENCE)
Subpart A - General Provisions
§ 320.1 Definitions
Subpart B - Procedures for Determining the Bioavailability or Bioequivalence of Drug Products
§ 320.21 Requirements for submission of bioavailability and bioequivalence data.
§ 320.22 Criteria for waiver of evidence of in vivo bioavailability or bioequivalence.
§ 320.23 Basis for measuring in vivo bioavailability or demonstrating bioequivalence.
§ 320.24 Types of evidence to measure bioavailability or establish bioequivalence.
§ 320.25 Guidelines for the conduct of an in vivo bioavailability study.
§ 320.26 Guidelines on the design of a single-dose in vivo bioavailability or bioequivalence study.
§ 320.27 Guidelines on the design of a multiple-dose in vivo bioavailability study.
§ 320.28 Correlation of bioavailability with an acute pharmacological effect or clinical evidence.
§ 320.29 Analytical methods for an in vivo bioavailability or bioequivalence study.
§ 320.30 Inquiries regarding bioavailability and bioequivalence requirements and review of protocols by the
Food and Drug Administration.
§ 320.31 Applicability of requirements regarding an “Investigational New Drug Application.”
§ 320.32 Procedures for establishing or amending a bioequivalence requirement.
§ 320.33 Criteria and evidence to assess actual or potential bioequivalence problems.
§ 320.34 Requirements for batch testing and certification by the Food and Drug Administration.
§ 320.35 Requirements for in vitro testing of each batch.
§ 320.36 Requirements for maintenance of records of bioequivalence testing.
§ 320.38 Retention of bioavailability samples.
§ 320.63 Retention of bioequivalence samples.
320.1 DEFINITIONS:
(a) Bioavailability
It means the rate and extent to which the active ingredient or active moiety is absorbed from a drug product
and becomes available at the site of action. For drug products that are not intended to be absorbed into the
bloodstream, bioavailability may be assessed by measurements intended to reflect the rate and extent to
which the active ingredient or active moiety becomes available at the site of action.
(b) Bioequivalence
Bioequivalence is a term in pharmacokinetics used to assess the expected in vivo biological equivalence of
two proprietary preparations of a drug. If two products are said to be bioequivalent it means that they would
be expected to be, for all intents and purposes, the same.
§ 320.21 Requirements for submission of bioavailability and bioequivalence data.
Any person submitting a full NDA to the Food and Drug Administration (FDA) shall include in the
application either:
 Evidence measuring the in vivo bioavailability of the drug product that is the subject of the
application; or
 Information to permit FDA to waive the submission of evidence measuring in vivo bioavailability.
Any person submitting an ANDA to FDA shall include in the application either:
 Evidence demonstrating that the drug product that is the subject of the abbreviated new drug
application is bioequivalent to the reference listed drug .
 Information to show that the drug product is bioequivalent to the reference listed drug which would
permit FDA to waive the submission of evidence demonstrating in vivo bioequivalence as provided
in this section.
§ 320.22 Criteria for waiver of evidence of in vivo bioavailability or bioequivalence.
Any person submitting a full or ANDA, or a supplemental application proposing any of the changes set may
request FDA to waive the requirement for the submission of evidence measuring the in vivo bioavailability
or demonstrating the in vivo bioequivalence of the drug product that is the subject of the application.
For certain drug products, the in vivo bioavailability or bioequivalence of the drug product may be self-
evident and it is based on other data in the application if the product meets one of the following criteria:
• Is a parenteral solution intended solely for administration by injection, or an ophthalmic or optic
solution.
• Is administered by inhalation as a gas, e.g., a medicinal or an inhalation anesthetic.
• Is a solution for application to the skin, an oral solution, elixir, syrup, tincture, a solution for
aerosolization or nebulization, a nasal solution, or similar other solubilized form.
§ 320.23 Basis for measuring in vivo bioavailability or demonstrating bioequivalence.
Bioavailability :
 The in vivo bioavailability of a drug product is measured if the product's rate and extent of absorption, as
determined by comparison of measured parameters.
 Statistical techniques used must be of sufficient sensitivity to detect differences in rate and extent of
absorption that are not attributable to subject variability.
 A drug product that differs from the reference material in its rate of absorption, but not in its extent of
absorption, may be considered to be bioavailable.
Bioequivalence :
 Two drug products will be considered bioequivalent drug products if they are pharmaceutical
equivalents or pharmaceutical alternatives whose rate and extent of absorption do not show a
significant difference when administered at the same molar dose of the active moiety under similar
experimental conditions, either single dose or multiple dose.
 For drug products that are not intended to be absorbed into the bloodstream, bioequivalence may be
demonstrated by scientifically valid methods that are expected to detect a significant difference between
the drug and the listed drug in safety and therapeutic effect.
§ 320.24 Types of evidence to measure bioavailability or establish bioequivalence
Bioavailability may be measured or bioequivalence may be demonstrated by several in vivo and in vitro
methods. FDA may require in vivo or in vitro testing, or both, to measure the bioavailability of a drug product
or establish the bioequivalence of specific drug products. Information on bioequivalence requirements for
specific products is included in the current edition of FDA’s publication ‘‘Approved Drug Products with
Therapeutic Equivalence Evaluations’’ and any current supplement to the publication. Applicants shall
conduct bioavailability and bioequivalence testing using the most accurate, sensitive, and reproducible
approach available among those set forth. The method used must be capable of measuring bioavailability
or establishing bioequivalence, as appropriate, for the product being tested.
BIOAVAILABILITY METHODS:
1. - An in vivo test in humans in which the concentration of the active ingredient and its active metabolite
in whole blood, plasma, serum, or other appropriate biological fluid is measured as a function of time.
- An in vitro test that has been correlated with and is predictive of human in vivo bioavailability data.
2. An in vivo test in humans in which the urinary excretion of the active moiety and its active metabolite
are measured as a function of time.
3. An in vivo test in humans in which an appropriate acute pharmacological effect of the active moiety and
its active metabolite are measured as a function of time.
4. Well-controlled clinical trials that establish the safety and effectiveness of the drug product, for purposes
of measuring bioavailability, or appropriately designed comparative clinical trials, for purposes of
demonstrating bioequivalence. This approach is the least accurate, sensitive, and reproducible of the
general approaches for measuring bioavailability or demonstrating bioequivalence.
§ 320.25 Guidelines for the conduct of an in vivo bioavailability study.
Guiding Principles
 The basic principle in an in vivo bioavailability study is that no unnecessary human research should be
done.
 Critically ill patients shall not be included in an in vivo bioavailability study unless the attending
physician determines that there is a potential benefit to the patient.
Basic study design
Comparison to a reference material.
Previously unmarketed active drug ingredients or therapeutic moieties.
 An in vivo bioavailability study involving a drug product containing an active drug ingredient or
therapeutic moiety that has not been approved for marketing can be used to measure the following
pharmacokinetic data:
 The reference material in such a bioavailability study should be a solution or suspension containing the
same quantity of the active drug ingredient or therapeutic moiety as the formulation proposed for
marketing.
 The reference material should be administered by the same route as the formulation proposed for
marketing unless an alternative or additional route is necessary to answer the scientific question under
study.
New formulation of active drug ingredients or therapeutic moieties approved for marketing.
New dosage form can be used for:
 Measure the bioavailability ; and
 Define the pharmacokinetic parameters
Extended release formulation:
• The drug product meets the extended release claims made for it.
• The bioavailability profile established for the drug product rules out the occurrence of any dose
dumping.
• The drug product’s steady-state performance is equivalent to a currently marketed nonextended release
or extended release drug product.
• The drug product’s formulation provides consistent pharmacokinetic performance between individual
dosage units.
Use of a placebo as the reference material:
 The study measures the therapeutic or acute pharmacological effect of the active drug ingredient or
therapeutic moiety.
 The study is a clinical trial to establish the safety and effectiveness of the drug product.
Standards for test drug product and reference material:
 Both the drug product to be tested and the reference material, if it is another drug product, shall be
shown to meet all compendial or other applicable standards of identity, strength ,quality, and purity,
including potency and, where applicable, content uniformity, disintegration times, and dissolution rates.
 Samples of the drug product to be tested shall be manufactured using the same equipment and
under the same conditions as those used for full-scale production.
§ 320.26 Guidelines on the design of a single-dose in vivo bioavailability or bioequivalence study.
Basic principles:
• Bioavailability/Bioequivalence study should be a single dose comparison of drug product and conducted
in normal adults.
• Test product and reference material should be administered in fasting state.
Study Design:
• Should provide a drug elimination period.
• At least three times the half life of an active ingredient.
• At least three times the half life of decay of pharmacological effect.
Collection of blood samples:
 When comparison of the test product and the reference material is to be based on blood concentration
time curves, unless some other approach is more appropriate for valid scientific reasons, blood samples
should be taken with sufficient frequency to permit an estimate of both:
Collection of blood samples:
 Samples of the urine should be collected with sufficient frequency.
Measurement of an acute pharmacological effect:
 Measurements of this effect should be made with sufficient frequency to permit a reasonable estimate
of the total area under the curve for a time period at least three times the half-life of decay of the
pharmacological effect.
 The use of an acute pharmacological effect to determine bioavailability may further require
demonstration of dose-related response.
§ 320.27 Guidelines on the design of a multiple-dose in vivo bioavailability study.
Basic Principles:
 The test product and the reference material should be administered to subjects in the fasting or non
fasting state, depending upon the conditions reflected in the proposed labelling of the test product.
 There is a difference in the rate of absorption but not in the extent of absorption.
 There is excessive variability in bioavailability from subject to subject.
 The drug product is an extended release dosage form.
Study design:
 Should be crossover in design, if the study is to establish dose proportionality then crossover design is
not required.
 Should provide elimination period if required.
 At least five times the half-life of decay of the acute pharmacological effect.
Achievement of steady-state conditions:
 Whenever a multiple-dose study is conducted, unless some other approach is more appropriate for
valid scientific reasons, sufficient doses of the test product and reference material should be
administered in accordance with the labelling to achieve steady-state conditions.
Collection of blood or urine samples:
 To be based on blood concentration-time curves at steady state, appropriate dosage is required to
reach the steady state.
 To be based on cumulative urinary excretion-time curves at steady state, appropriate dosage is
required to reach the steady state.
Steady-state parameters:
 Blood clearances at steady-state obtained in a multiple-dose study should be compared to blood
clearances obtained in a single-dose study to support adequate dosage recommendations.
 In a linear system, the area under the blood concentration-time curve during a dosing interval in a
multiple-dose steady-state study is directly proportional to the fraction of the dose absorbed and is
equal to the corresponding ‘‘zero to infinity’’ area under the curve for a single-dose study.
 Other methods based on valid scientific reasons should be used to determine the bioavailability of a
drug product having dose-dependent kinetics (non-linear system).
Measurement of an acute pharmacological effect:
 to be based on acute pharmacological effect-time curves, measurements of this effect should be made
with sufficient frequency to demonstrate a maximum effect and a lack of significant difference between
the test product and the reference material.
§ 320.28 Correlation of bioavailability with an acute pharmacological effect or clinical evidence.
• It is required to establish the clinical significance of a special claim.
§ 320.29 Analytical methods for an in vivo bioavailability or bioequivalence study.
• It is used to measure the active ingredients in body fluids/excretory products.
§ 320.30 Inquiries regarding bioavailability and bioequivalence requirements and review of
protocols by the Food and Drug Administration.
FDA may review a proposed protocol for a bioavailability or bioequivalence study and will offer advice with
respect to whether the following conditions are met:
 The design
 The reference material
 The proposed chemical and statistical analytical methods are adequate.
§ 320.31 Applicability of requirements regarding an “Investigational New Drug Application.”
 Any person planning to conduct an in vivo BA/BE study in humans shall submit an “Investigational New
Drug Application”.
 Any person planning to conduct a BA/BE study in humans using a drug product that contains an
already approved, non-new chemical entity shall submit an IND.
 The provisions of parts 50, 56, and 312 of this chapter are applicable to any BA/BE study in humans
conducted under an IND.
 A BA/BE study in humans other than one described in paragraphs (A) through (C) of this section is
exempt from the requirements of part 312 of this chapter
§ 320.32 Procedures for establishing or amending a bioequivalence requirement.
The Food and Drug Administration, on its own initiative or in response to a petition by an interested person,
may propose and promulgate a regulation to establish a bioequivalence requirement for a product not subject
to section 505(j) of the act if it finds there is well-documented evidence that specific pharmaceutical
equivalents or pharmaceutical alternatives intended to be used interchangeably for the same therapeutic
effect:
 Are not bioequivalent drug products
 May not be bioequivalent drug products because they are members of a class of drug products that have
close structural similarity and similar physiochemical properties.
 If the rulemaking is proposed in response to a petition, FDA shall include in the proposal a summary and
analysis of the relevant information that was submitted in the petition.
§ 320.33 Criteria and evidence to assess actual or potential bioequivalence problems.
The Commissioner of Food and Drugs shall consider the following factors,
 Evidence from well-controlled clinical trials or controlled observations in patients.
 Evidence from well-controlled bioequivalence studies.
 Evidence that the drug products exhibit a narrow therapeutic ratio.
 Competent medical determination.
 Physicochemical evidence.
 Pharmacokinetic evidence.
§ 320.34 Requirements for batch testing and certification by the Food and Drug Administration.
 Commissioner shall include in the bioequivalence requirement, a requirement for manufacturers to submit
samples of each batch to the FDA and to withhold distribution of the batch until notified by the FDA that
the batch may be introduced into interstate commerce.
 The Commissioner will ordinarily terminate the above requirement if the manufacturer has produced four
consecutive batches that were tested by the FDA and found to meet the bioequivalence requirement.
§ 320.35 Requirements for in vitro testing of each batch.
• If a bioequivalence requirement specifies a currently available in vitro test or an in vitro bioequivalence
standard comparing the drug product to a reference standard, the manufacturer shall conduct the test on
a sample of each batch of the drug product to assure batch-to-batch uniformity
§ 320.36 Requirements for maintenance of records of bioequivalence testing.
• All records of in vivo or in vitro tests conducted on any marketed batch of a drug product to assure that
the product meets a bioequivalence requirement shall be maintained by the manufacturer for at least 2
years after the expiration date of the batch and submitted to the Food and Drug Administration on request.
§ 320.38 Retention of bioavailability samples.
 The applicant of an application submitted under section 505 of the Federal Food, Drug, and Cosmetic
Act.
 Each reserve sample shall consist of a sufficient quantity to permit FDA to perform five times all of the
release tests required in the application or supplemental application.
 Each reserve sample shall be adequately identified so that the reserve sample can be positively identified
as having come from the same sample as used in the specific bioavailability study.
 Each reserve sample shall be stored under conditions consistent with product labelling.
§ 320.63 Retention of bioequivalence samples
 The applicant of an abbreviated application or a supplemental application submitted under section 505 of
the Federal Food, Drug, and Cosmetic Act, or, if bioequivalence testing was performed under contract,
the contract research organization shall retain reserve samples of any test article and reference standard
used in conducting an in vivo or in vitro bioequivalence study required for approval of the abbreviated
application or supplemental application. The applicant or contract research organization shall retain the
reserve samples in accordance with, and for the period specified in, § 320.38 and shall release the reserve
samples to FDA upon request in accordance with § 320.38.
ISO 14155
HISTORY
• ISO 14155:2020(Current) - Clinical investigation of medical devices for human subjects — Good clinical
practice
• ISO 14155:2011 (Withdrawn)- Clinical investigation of medical devices for human subjects — Good
clinical practice
• ISO 14155:2011/Cor 1:2011 (Withdrawn)- Clinical investigation of medical devices for human subjects
— Good clinical practice — Technical Corrigendum 1
• ISO 14155-1:2003 (Withdrawn)- Clinical investigation of medical devices for human subjects — Part 1:
General requirements
• ISO 14155-2:2003 (Withdrawn)- Clinical investigation of medical devices for human subjects — Part 2:
Clinical investigation plans
• ISO 14155:1996 (Withdrawn)- Clinical investigation of medical devices
AMMENDMENTS in ISO 14155:2020
• Clinical quality management
• Addressing increased statistical requirements by notified bodies
• Clinical Investigation audits
• Risk based monitoring and related monitoring plan
• Ethics Committee
• In-vitro diagnostic medical devices (IVD’s)
• Increased emphasis on risk management (ISO 14971)
• Clinical investigation planning requires inclusion of personnel with relevant medical expertise
• Alignment with definitions with current updated GCP guidelines
• Emphasis on clinical evidence in European Regulation
Risk Management in Practice
• Implementation of ISO 14971 involves a system for risk management.
• Risk management plan indentifies, evaluates, ranks and control risks.
- RMP’s can be inclusive of risk from entire product life.
- Risk can be product related or patient related.
- Can be applied to project specific risks (clinical trials)
• Formal risk management processes is focus of ISO 14155: 2020
CLINICAL QUALITY MANAGEMENT
• Quality management process includes SOP’s , computerized quality system and personnel training.
• Sponsor is responsible for clinical study quality even if study management is outsourced to third party.
• Document control process for study files such as protocol, IDs , and so on
• Complete record maintenance
• Preparation for audits
• Identify, Justify and document expectations to requirements
1. SCOPE
Addresses GCP (design, conduct, recording, reporting) for clinical investigations in human subjects
(effectiveness and safety) of medical devices
• Protect the rights, safety and well-being of human subjects
• Defines responsibilities of Principal investigator , sponsor and other parties
• Ensure the scientific conduct of the clinical investigation and the credibility of the clinical investigation
results
• Assist sponsors, investigators, ethics committees, regulatory authorities and other bodies involved in the
conformity assessment of medical devices.
2. Normative References
• The following documents are referred to in the text in such a way that some or all of their content
constitutes requirements of this document.
• For dated references, only the edition cited applies.
• For undated references, the latest edition of the referenced document (including any amendments)
applies.
• ISO 14971, Medical devices — Application of risk management to medical devices
3. TERMS AND DEFINITIONS
• Adverse Device Effect (ADE)- Adverse events resulting from insufficient or inadequate instructions
for use, deployment, implantation, installation, or operation, or any malfunction of the investigational
medical device. Includes any event resulting from use error or from intentional misuse of the
investigational medical device.
• Case Report Form (CRF)- Set of printed, optical or electronic documents for each subject on which
information to be reported to the sponsor is recorded, as required by the CIP.
• Clinical Investigation Plan (CIP)- Document that states the rationale, objectives, design and pre-
specified analysis, methodology, organization, monitoring, conduct and record-keeping of the clinical
investigation
• Clinical Investigation Report- Document describing the design, execution, statistical analysis and
results of a clinical investigation
• Data Monitoring Committee (DMC)- Independent committee that can be established by
the sponsor to assess, at intervals, the progress of the clinical investigation, the safety data or the
critical clinical performance or effectiveness , endpoints and to recommend to the sponsor whether to
continue, suspend, modify, or stop the clinical investigation.
• Device Deficiency- Inadequacy of a medical device with respect to its identity, quality, durability,
reliability, usability, safety or performance. Include malfunctions, use errors, and inadequacy in the
information supplied by the manufacturer including labelling.
• Investigational Medical Device- Medical device being assessed for clinical
performance, effectiveness, or safety in a clinical investigation. Includes medical devices already on
the market that are being evaluated for new intended uses, new populations, new materials or design
changes. Includes medical devices already on the market that are being evaluated within their
intended use in a post-market clinical investigation (interventional or non-interventional).
• Medical Device- Instrument, apparatus, implement, machine, appliance, implant, reagent for in
vitro use, software, material or other similar or related article, intended by the manufacturer to be
used, alone or in combination, for human beings, for one or more of the specific purpose(s) of:
— diagnosis, prevention, monitoring, treatment or alleviation of disease;
— diagnosis, monitoring, treatment, alleviation of or compensation for an injury;
— investigation, replacement, modification, or support of the anatomy or of a physiological process;
— supporting or sustaining life;
— control of conception;
— disinfection of medical devices;
— providing information by means of in vitro examination of specimens derived from the human body;
and does not achieve its primary intended action by pharmacological, immunological or metabolic means,
in or on the human body, but which may be assisted in its intended function by such means
Products which may be considered to be medical devices in some jurisdictions but not in others include:
— disinfection substances, aids for persons with disabilities, devices incorporating animal and/or
human tissues, devices for in vitro fertilization or assisted reproduction technologies.
• Serious Adverse Device Effect (SADE)- Adverse device effect that has resulted in any of the
consequences characteristic of a serious adverse event
• Serious Health Threat- Signal from any adverse event or device deficiency that indicates an
imminent risk of death or a serious deterioration in the health in subjects, users or other persons, and
that requires prompt remedial action for other subjects, users or other persons. Include events that
are of significant and unexpected nature such that they become alarming as a potential serious health
hazard or possibility of multiple deaths occurring at short intervals.
• Unanticipated Serious Adverse Device Effect (USADE)- Serious adverse device effect which by
its nature, incidence, severity or outcome has not been identified in the current risk assessment
• Anticipated Serious Adverse Device Effect (ASADE)- Is an effect which by its nature, incidence,
severity or outcome has been identified in the risk assessment.
4.Summary of GCP
• Ethical Principles
• Risk benefit ratio
• Rights, safety, well-being of human subjects
• Scientifically sound
• Ethics Committee approval
• Expert advice and care
• Education or experience
• Privacy, Confidentiality
• Systems for quality control
5. ETHICS COMMITTEE (EC)
Ethical Considerations
• Principle in clause 4 must be understood, observed and applied in every step in the clinical investigation
• Coercion
• Compensation
• Registration and public access
• Responsibilities (all parties)
• Communication with EC (use this document and record)
• Information from EC (approval documents)
• Informed consent
Responsibilities (Annex G)
• Provides guidance on best practices for operation of EC reviewing clinical investigation of medical
devices.
Purpose
• Composed of members who collectively have experience/qualification to review/evaluate scientific
medical, methodological, statistical and ethical aspects of proposed clinical investigations.
6. CLINICAL INVESTIGATION PLANNING
6.1 General
• All involved with trial design and conduct must be qualified by education, training or experience.
• Qualification must be documented.
• The sponsor must have access to medical expertise relevant to the trial.
6.2 Risk Management
• Balance risk associated with device and related clinical procedure against anticipated benefits to subjects.
• The sponsor should predefine risk acceptability threshold, if threshold is reached or exceeded, risk
assessment to determine whether/what actions are needed.
6.2 Applications of ISO 14971 (Annex H)
• It is about risk management of medical devices.
• Risk control effectiveness evaluated by device lifecycle, including during trials.
• Trials provide data to support/refuse acceptability of benefit-risk ratio
6.3 Design of Clinical investigation
• Design trial to evaluate if device suitable for intended purpose and population.
• Based on preclinical data and clinical evaluation, aligned with risk assessment.
• Clinical evaluation includes analysis of clinical performance, effectiveness and safety data of
investigational device or similar device.
• Use to justify endpoints, confounding factors, choice of control groups, bias minimization and subject
selection.
6.4 Cinical Investigation Plan(CIP) (Annex A)
• Identification of CIP, sponsor, principle investigator, co-ordinating investigator and investigation sites.
• Objectives and hypothesis of clinical trials
• Synopsis of investigation.
• Identification and description of investigational device.
• Design of clinical investigation including: investigation devices & comparator, subjects, procedures and
monitoring plan.
• Justification of designs.
• Statistical design and analysis.
• Data management
• Benefits and risks of investigational device, clinical procedure and clinical investigation.
• Description of procedures to amend CIP
• Deviations from CIP
• Device accountability
• Statements of compliance
• Informed consent process
• Adverse events, adverse device effects, device defeciencies
• Vulnerable population
• Suspension or premature termination of investigation.
• Publication policy
• Bibliography
6.5 Investigator Brochure(IB) (Annex B)
• Purpose: To provide principal investigator and investigation site team with sufficient safety and
performance data to justify human exposure to investigational device. (Principal investigator acknowledge
receipt in writing and keep confidential).
• Update throughout investigation as new data becomes available.
• Update if investigational device design changes.
Components (Annex B)
• Identification of IB
• Sponsor/manufacturing
• Investigational device information
• Preclinical testing
• Existing clinical data
• Risk management of investigational device
• Regulatory and other references
6.6 Case Report Form (CRF) (Annex C)
• Captures data for each enrolled subject: 1) Condition of each subject at beginning and throughout
investigation. 2)Exposure to investigational device and other therapeutics.
• Format should minimize error.
• CRF completion guidelines provide instructions for accurate completion, correction and signature of
CRFs.
• If CIP amended, CRFs should be reviewed to determine if need revised.
Risk Disclosure
• Benefit-risk summary should be disclosed in relevant trial documents.
• Example: Residual risk in IB and Instructions for Use (IFU) , all anticipated AE device effects in CIP and
informed consent form (ICF), rationale for benefit-risk ratio in CIP
6.7 Monitoring Plan
• Determine appropriate monitoring based on risk assessment.
• Monitoring methods can differ between countries and should comply with national/regional regulations
regarding personal data protection.
DESCRIBES:
 Risks and risk control measures
 Monitoring methods
 Methods for documenting and communicating monitoring results
 Escalation process if continuous or egregious non-compliance
 Aspects of investigation needing special attention
 Processes to be monitored and data to be verified in source documents
6.8 Investigational Site Selection
• Identify criteria necessary for conduct of clinical investigation prior to start of site qualification.
• Eg: Facilities required, principal investigators qualification, type of environment.
• Principal investigators qualification and investigation site adequacy verified and documented in
investigation site selection report.
6.9 Agreements
• Written agreements between sponsor and principal investigator/investigation site and other relevant
parties should be signed and dated by all parties.
• Agreement should detail responsibilities of each party.
• Agreement should identify instances where parties share regulatory responsibilities with sponsor.
6.10 Labeling
• The device, IFU and packaging should state device is exclusively for use in clinical investigation.
• In US, investigational label as per 21 CFR 812.5
• Caution: Investigational device limited by Federal (or United States) law to investigational use.
7. Clinical Investigation Conduct
7.1 General
• Conducted in accordance with CIP
• Not to commence until EC and/or regulatory approvals are obtained
7.2 Investigational Site Initiation
• Initiation visit or meeting shall be conducted and documented by sponsor/monitor at start of clinical
investigation
Log with names, initials, signatures, functions and designated authorizations for principal investigator and
members of investigation site team
Can be done by telephone or other means
7.3 Investigation site monitoring
• Conduct of clinical investigation monitored according to monitoring plan
• All monitoring activities documented
7.4 Adverse events and device deficiencies
7.4.1
• AE or device deficiency potentially indicating a serious health threat are evaluated by sponsor.
• May require a specific reporting process according to regulatory requirements.
7.4.2
• All AE and any new information are documented in a timely manner and reported as specified.
• All AE are reported in interim and final reports.
7.4.3
• Device deficiencies documented throughout clinical investigation and managed by sponsor as specified
for control of non-conforming product.
• All deficient devices are returned for evaluation and reports submitted even if deficiency didn’t cause AE
but could have caused serious AE.
7.4.4
Arising risk during clinical investigation:
a) Any person identifying risk potentially impacting safety informs principal investigator and sponsor.
b) Sponsor shall perform risk analysis with PI to determine if information is reflected in current risk assessment
and risk remains acceptable. If unacceptable, and serious health threat is identified, sponsor shall suspend
trial immediately.
c) If a possible unacceptable risk, sponsor shall conduct risk assessment in compliance with ISO 14971 with
possibility of :
1) Risks remains acceptable
2) Corrective actions found not affecting validity of investigation with revised benefit-risk may continue
investigation
3) If corrective actions affect validity of trial, trial is to be terminated
4) If no corrective actions may be applied, investigation is to be terminated
7.5 Clinical Investigation Documents
• Amendments are made as needed throughout investigation following written procedures with
documentation reviewed and approved as specified.
• Subject identification log maintained at each investigation site with an identification code linked to their
private information.
• Source documents are maintained by investigation site team throughout clinical investigation
7.6 Additional members of the investigation site team
• New members added to investigational site teams will only start their assignment after receiving adequate
training and training is documented
7.7 Subject privacy and confidentiality of data
• Confidentiality observed by all involved parties and data is secured against unauthorized access.
• Privacy of subjects is preserved in all reports and publiction
7.8 Document and Data control
1) Traceability of documents and data:
• All documents produced and maintained ensuring reliability, integrity, control and traceability including all
versions of document.
• Source documents are verified and signed.
2) Recording data:
• Data on CRFs from source documents and discrepancies explained in writing.
• All CRFs are signed and dated.
3) Electronic Clinical data system:
• Written procedures are used to describe system validation, data collection, security, backup and recovery.
• Ensured no deletion of entered data and changes can be followed via an audit trial.
7.9 Investigational device accountability
• Access to device is controlled and only used in clinical investigation following CIP.
• Physical location of all devices documented.
• Records shall be kept on:
a) name of person received, used, returned or disposed of device;
b) date of receipt, identification and quality of device ;
c) date of use ;
d) subject identification ;
e) expiry date if applicable ;
f) date device returned ;
g) return date of unused, expired or malfunctioning device.
7.10 Accounting for subjects
• All subjects accounted for are documented
• If subjects discontinued, the reason shall be recorded.
• Investigator should use exciting data on the subject and may ask for permission to obtain follow-up
information
7.11 Auditing (Annex J)
• Audits may be conducted to evaluate compliance to CIP, ISO 14155 and applicable regulatory
requirements.
• It may cover all involved parties and are separate from quality control or routine monitoring functions.
• Auditors shall be independent of the clinical investigation.
8. Suspension, termination and close-out of the clinical investigation
8.1 Completion of clinical investigation
• May be pre-specified by the plan or terminated early
• Completion coincides with :
1) Last visit of last subject
2) When follow up is completed
8.2 Suspension/Premature termination
• May suspend entire investigation/single site
• May be suspended/terminated by: sponsor, PI, EC or regulatory authority
• Justify in writing and inform all parties
• Sponsor is responsible for obligations to participants
• Reasons: Suspicion of unacceptable risk, Suspend for risk assessment (terminate if risk is unacceptable),
Serious or repeated
8.2.2 Resuming after temporary suspension
• After problem analysis and corrective actions in place:
- Inform PI, EC and regulatory authority (as and when required), provide with reasoning and support data.
- EC & regulatory authority must concur before clinical investigation resumes
8.3 Routine close-out activities
• PI records and sponsor file complete and up to date CRF complete , AE status to be documented
• Record retention and archival in place
• Disposal of remaining material : devices, samples and other materials
• All identified issues resolved and all parties should be notified
8.4 Clinical investigation report (Annex D)
• Include: device information, methodology, clinical investigation design, CIP deviations, data analysis,
result compared to investigation objectives.
• Reports cover all participants at all sites
• No identifiable participant information
• Sponsor and PI or co-ordinating investigator sign off – report provided to all parties involved
• Results updated in clinical investigation database and published
• Annex D outlines a detail format for the clinical investigation report to follow and specifies the content
required for the report
8.5 Risk assessment and conclusions
• Risk information should be formally reviewed; data and conclusions should be updated in risk analysis
and clinical evaluation documents
8.6 Document retention
• Both sponsor and PI are responsible for maintaining clinical investigation documents.
• Custody may be formly transferred if necessary
• CIP, IB, CRF and final reports should be kept in the manufacturers Quality management system and
incorporated in the device technical document
Essential clinical investigation documents (Annex E)
• Table E.1 – E.3 contains list of documents to be maintained
• Includes document names, purposes, who needs to keep them, where to find in ISO 14155
• Regulatory bodies may require a list of all documents:
- Record location of essential documents
- Version history required
- Easy to search and retrieve
9. Sponsor Responsibility
Ensure quality, planning, conduct, monitoring, management and regulatory approval of studies
9.1 Clinical Quality Management
• Create and maintain quality procedure documents
• Maintain compliance records
• If applicable, ensure auditing requirements are met per ISO 14155
• Document and justify significant exceptions to ISO 14155 requirements
9.2 Clinical investigation planning and conduct
• Selection and training of clinical personnel
• Preparation of documents and materials according to clauses 5-7
• Conduct of clinical investigation
• Monitoring – should be documented and recorded
• Safety evaluation and reporting
• Clinical investigation close-out
9.3 Outsourcing of duties and functions
• Sponsor may transfer duties and functions to external organization
• Sponsor responsible for verifying external organization adheres to written procedures
9.4 Communication with regulatory authorities
• Obtain regulatory authority approval/non-objection
• Report process and status of investigation