Timeline
• Introdution
• Background
•Zygosity & Chorionicity
• Diagnosis
• Complications of Twin
• Complications specific to Monochorionic Twin
• Management
• Bottomline
3.
Introduction
• A monochorionicpregnancy is a multiple pregnancy, most commonly a
twin pregnancy (99% of cases), in which babies are dependent on a
single shared placenta
• Placental anastomoses conjoining the fetal circulations
• Monochorionic placentation can also occur in rarer, higher-order
multiples, especially triplets
4.
Introduction contd...
• Increasein all types of multiple pregnancies with:
the use of assisted reproductive technology
to defer pregnancy to a later maternal age
• Day 5 blastocyst transfers seems to be associated with a significantly
higher rate of monozygotic twinning compared with cleavage stage
day 3 transfers
5.
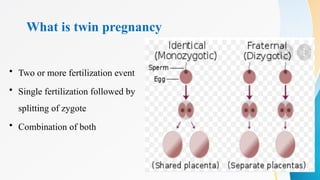
What is twinpregnancy
• Two or more fertilization event
• Single fertilization followed by
splitting of zygote
• Combination of both
6.
Background
Incidence of twin:1 in 52 or 1.9%
Incidence is highest in Nigeria (1 in 20) and lowest in Japan (1 in200)
Frequency of monozygotic twin births: 1 per 250 births (relatively
constant worldwide)
In India:1 in 80
Hellin’s rule: Twin 1 in 80
Triplet 1 in 802
Quadruplets 1 in 803
& so on
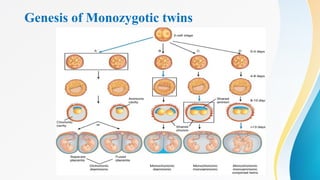
Genesis of Monozygotictwins (contd…)
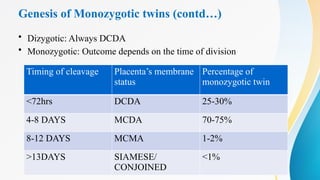
• Dizygotic: Always DCDA
• Monozygotic: Outcome depends on the time of division
Timing of cleavage Placenta’s membrane
status
Percentage of
monozygotic twin
<72hrs DCDA 25-30%
4-8 DAYS MCDA 70-75%
8-12 DAYS MCMA 1-2%
>13DAYS SIAMESE/
CONJOINED
<1%
9.
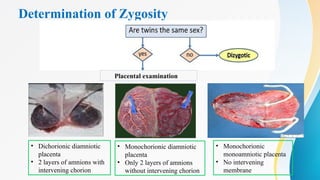
Determination of Zygosity
Placentalexamination
• Dichorionic diamniotic
placenta
• 2 layers of amnions with
intervening chorion
• Monochorionic diamniotic
placenta
• Only 2 layers of amnions
without intervening chorion
• Monochorionic
monoamniotic placenta
• No intervening
membrane
10.
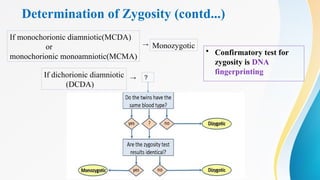
Determination of Zygosity(contd...)
• Confirmatory test for
zygosity is DNA
fingerprinting
If monochorionic diamniotic(MCDA)
or
monochorionic monoamniotic(MCMA)
Monozygotic
If dichorionic diamniotic
(DCDA)
?
→
→
11.
Determination of Chorionicity
•At 11 +2
– 14+1
weeks of gestation (CRL 45–84 mm) sonographic
assessment of chorionicity is determined using following four features:
1. Number of placental masses
2. The appearance of the intertwin membrane attachment to the placenta
3. Thickness of that membrane
4. Fetal gender
12.
Determination of Chorionicity(contd…)
• Two separate placentas → Dichorionic (3% of Monochorionic twin have
Bilobed placenta )
Single placenta → may be Dichorionic (two fused placenta) or
Monochorionic
• Sex discordance indicates Dichorionicity
• Thickness of dividing membrane :
≥2 mm → Dichorionic pregnancy
< 2 mm → Monochorionic pregnancy
13.
Determination of Chorionicity(contd...)
• Dichorionic pregnancy → Membrane composed of four layers
2 amnions and 2 chorions
• Monochorionic pregnancy → Membrane composed of 2 layers
amnion and amnion
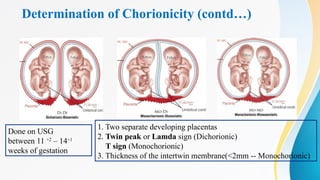
• The twin peak sign or lambda sign → Dichorionic twin
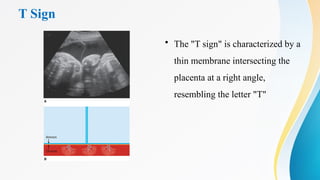
• T sign → Monochorionic twin
14.
Determination of Chorionicity(contd…)
Done on USG
between 11 +2
– 14+1
weeks of gestation
1. Two separate developing placentas
2. Twin peak or Lamda sign (Dichorionic)
T sign (Monochorionic)
3. Thickness of the intertwin membrane(<2mm -- Monochorionic)
15.
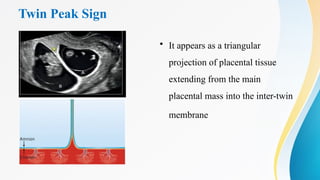
Twin Peak Sign
•It appears as a triangular
projection of placental tissue
extending from the main
placental mass into the inter-twin
membrane
16.
T Sign
• The"T sign" is characterized by a
thin membrane intersecting the
placenta at a right angle,
resembling the letter "T"
17.
Nomenclature of Twins
•On ultrasound, the fetuses in twin pregnancies should be
be assigned nomenclature
• Fetus A should be with amniotic sac closest to the
maternal cervix
• Document cord insertions and relation to placenta
• Labelling critical for anomaly tracking and delivery
planning
• Standardize labelling from early scans for clarity
upper
lower
left
right
18.
Screening for ChromosomalAnomalies in
Monochorionic Twin Pregnancies
• Aneuploidy screening:
Nuchal translucency + first-trimester serum markers (combined screening
test)
Done at 11 +2
– 14+1
weeks of gestation (CRL 45–84 mm)
• Sensitivity - 90%
• False-positive rate (up to 10%) is higher than in singletons (2.5%) and
dichorionic twins (5%)
19.
Screening for ChromosomalAnomalies in
Monochorionic Twin Pregnancies (contd...)
• Women who ‘miss’ or who have unsuccessful 1st trimester screening
Second-trimester screening with quadruple test to be done
DR: 80% and a false-positive rate of 3%
• Cell free fetal (cff) DNA testing (also known as NIPT), contingent on the
results of the first-trimester combined test for major autosomal trisomies
also recommended
20.
Increased Nuchal Translucency
•Associated with TTTS, cardiac dysfunction, congenital defects
• 20% discordance in NT values increases complication risk
• NT >95th percentile: consider genetic testing and anomaly scan
• Predictive of structural anomalies even without aneuploidy
• Recommend combined screening test (NT + serum markers)
• Early referral to fetal medicine when increased NT noted
21.
Screening for StructuralAbnormalities in
Monochorionic Twin Pregnancies
• Incidence of anomalies is higher in monozygotic twins due to the
unusual nature of the cleavage of the conceptus
• Monozygotic twins are monochorionic in 70% of cases; hence the higher
rates of anomaly in monochorionic twins
• Anomalies specific to monozygotic twins are often midline such as
holoprosencephaly, neural tube defects and cardiac abnormalities
22.
Screening for StructuralAbnormalities in
Monochorionic Twin Pregnancies (contd..)
• All monochorionic twins should undergo a routine detailed ultrasound
scan between 18 +0
and 20 +6
weeks of gestation, which includes extended
views of the fetal heart anatomy
23.
Optimum Ultrasound Regimenfor
Monochorionic Twin Pregnancies
• Fetal ultrasound assessment should take place every 2 weeks in
uncomplicated monochorionic pregnancies from 16 +0
weeks of gestation
onwards until birth
Parameters to beseen at each Ultrasound
• Liquor volume in each of the amniotic sac
• The deepest vertical pocket (DVP) depth
• Umbilical artery pulsatility index(UA-PI) at every scan from 16 +0
weeks
• Middle cerebral artery peak systolic velocity (MCA PSV) from 20 weeks
• Fetal bladders should also be visualised
• From 16 +0
weeks of gestation, fetal biometry, estimated fetal weight
(EFW) and the difference in EFW (as there is risk of sGR)
26.
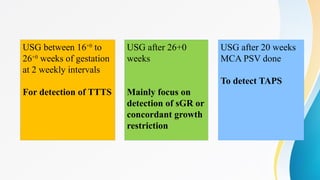
USG between 16+0
to
26+0
weeksof gestation
at 2 weekly intervals
For detection of TTTS
USG after 26+0
weeks
Mainly focus on
detection of sGR or
concordant growth
restriction
USG after 20 weeks
MCA PSV done
To detect TAPS
27.
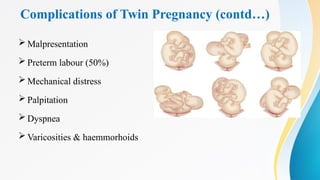
Complications of TwinPregnancy
• Maternal Complications
During pregnancy:
Nausea and vomiting
Anaemia
Unexplained weight gain
Preeclampsia (25%)
Hydramnios (10%): severe hydramnios can lead to obstructive uropathy
Antepartum haemorrhage
Complications of TwinPregnancy (contd…)
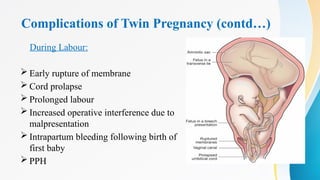
During Labour:
Early rupture of membrane
Cord prolapse
Prolonged labour
Increased operative interference due to
malpresentation
Intrapartum bleeding following birth of
first baby
PPH
30.
Complications of TwinPregnancy (contd…)
During puerperium:
Retained placenta
Subinvolution
Infection due to operative interference
Lactation failure
Depression
Placental vascular anastomoses
•All monochorionic placentas contain vascular anastomoses running
between the two fetal umbilical cords within & on the surface of the
placenta
• Four types: (i) arterial–arterial (ii) arterial–venous (iii) Veno-arterial and
(iv) venous–venous
• The nomenclature describes the donor fetal vessel first & then recipient
fetal vessel
34.
Placental vascular anastomoses(contd...)
• Anastomosis are also 2 types: Superficial and Deep
• Superficial anastomoses → bidirectional and balanced
• Deep anastomoses → unidirectional and unbalanced
• AA and VV anastomoses are superficial & end to end → allow
bidirectional blood flow & do not cause TTTS
• AV and VA anastomoses are deep → cause haemodynamic imbalance
between the fetal circulations
• AA anastomoses are protective
35.
Twin to twinTransfusion Syndrome (TTTS)
• Complicates up to 15%–20% of monochorionic twins (mostly MCDA
twins)
• Placenta has a predominance of unidirectional, arterial–venous
anastomoses
• Cause haemodynamic imbalance within the fetal circulations
• Adversely affect fetal cardiac function, fetoplacental perfusion and
causing fetal endocrine dysfunction
• Severity is graded by Quintero staging
36.
Pathophysiology of TTTS
Thethree major factors in the pathogenesis of TTTS are:
1. Unbalanced flow volume
2. Release of vasoactive mediators
3. Lack of AA anastomosis
37.
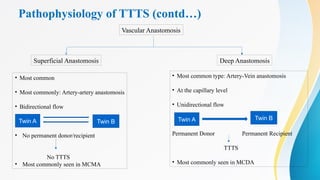
Vascular Anastomosis
Superficial AnastomosisDeep Anastomosis
• Most common
• Most commonly: Artery-artery anastomosis
• Bidirectional flow
• No permanent donor/recipient
No TTTS
• Most commonly seen in MCMA
Twin A Twin B
• Most common type: Artery-Vein anastomosis
• At the capillary level
• Unidirectional flow
Permanent Donor Permanent Recipient
TTTS
• Most commonly seen in MCDA
Twin A Twin B
Pathophysiology of TTTS (contd…)
38.
Pathophysiology of TTTS(contd…)
• AV anastomoses → chorionic plate surface arterial vessels from one
twin and chorionic plate surface venous vessels from other twin connect
in the underlying cotyledon
• The cotyledon is supplied by the artery of one twin & blood is drained
through vein of the co-twin
• Lack of AA anastomoses aggravate the condition
39.
Pathophysiology of TTTS(contd…)
• Increased natriuretic peptides in recipient worsen effects
• Imbalance activates RAAS in donor twin
• Donor twin: hypovolemia → oliguria → oligohydramnios → stuck twin
• Recipient twin: hypervolemia → stretching of cardiac atria→release of
ANP→Stretching of ventricle → release of BNP→vasodilation &
natriuresis → inhibition of RAAS → polyuria → polyhydramnios
40.
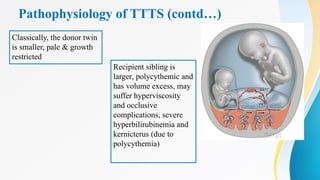
Pathophysiology of TTTS(contd…)
Classically, the donor twin
is smaller, pale & growth
restricted
Recipient sibling is
larger, polycythemic and
has volume excess, may
suffer hyperviscosity
and occlusive
complications, severe
hyperbilirubinemia and
kernicterus (due to
polycythemia)
41.
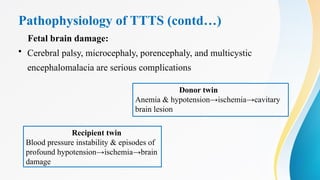
Pathophysiology of TTTS(contd…)
Fetal brain damage:
• Cerebral palsy, microcephaly, porencephaly, and multicystic
encephalomalacia are serious complications
Donor twin
Anemia & hypotension→ischemia→cavitary
brain lesion
Recipient twin
Blood pressure instability & episodes of
profound hypotension→ischemia→brain
damage
42.
Pathophysiology of TTTS(contd…)
Death of one twin in TTTS
Severe hypotension in surviving twin
Irreversible brain damage of surviving
twin that makes successful intervention for
the survivor nearly impossible
43.
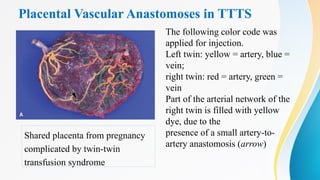
Placental Vascular Anastomosesin TTTS
The following color code was
applied for injection.
Left twin: yellow = artery, blue =
vein;
right twin: red = artery, green =
vein
Part of the arterial network of the
right twin is filled with yellow
dye, due to the
presence of a small artery-to-
artery anastomosis (arrow)
Shared placenta from pregnancy
complicated by twin-twin
transfusion syndrome
44.
Quintero Staging ofTTTS
Stage I
• A significant discordance in amniotic fluid volume
• Oligohydramnios with DVP < 2 cm in donor sac
• Polyhydramnios in the recipient sac (DVP > 8 cm before 20+0
weeks of
gestation and > 10 cm after 20+0
weeks of gestation)
• The Donor bladder is visible on ultrasound and the Umbilical Artery
Doppler velocimetry is normal
45.
Quintero Staging ofTTTS (contd...)
Stage II
• The bladder is not visible on ultrasound
• Severe oligohydramnios due to anuria of the donor twin
• Umbilical Artery Doppler studies are minimally abnormal
Stage III
• Abnormal doppler studies in either the donor or recipient fetus (or both)
• Abnormal (absent or reversed) UA doppler and/or abnormal venous
doppler velocities in the recipient
46.
Quintero Staging ofTTTS (contd...)
Stage IV
• The presence of fetal effusions (ascites, pericardial or pleural effusions)
with scalp oedema or overt hydrops fetalis present in either twin (but
usually in the recipient)
Stage V
• One or both babies have died (not amenable to therapy)
47.
Twin anaemia polycythemiasequence (TAPS)
• Up to 2% of uncomplicated monochorionic diamniotic (MCDA) and
~13% of monochorionic twins post-fetoscopic laser ablation
• Signs of fetal anaemia in the donor and polycythaemia in the recipient
• Without significant oligohydramnios/polyhydramnios
• Types of TAPS:
Spontaneous TAPS
Post laser ablation TAPS (develops within 5 weeks of the procedure)
48.
Pathophysiology of TAPS
SpontaneousTAPS:
• Few minuscule arterio-venous vascular anastomoses
• Unbalanced unidirectional slow transfusion of red blood cells through
very small (<1 mm diameter) placental AV anastomoses
• Large intertwin Hb difference
• 5-15 ml of RBC transfusion in 24 hours from donor to recipient twin
• Donor twin: Anaemia → hydrops fetalis
• Recipient twin: Polycythemia → fetal and placental thrombosis
49.
Pathophysiology of TAPS(contd...)
• The slowness of the process allows haemodynamic compensation, hence
there is absence of amniotic fluid discordance
• Donor twin → increased MCA PSV
• Recipient twin → decreased MCA PSV
• The difference in MCA PSV ≥ 1.0 MoM
50.
Pathophysiology of TAPS(contd...)
Post laser ablation TAPS:
• Sequelae of use of laser ablation for treatment of TTTS
• Discordance of liquor volumes must be excluded, as if present would
indicate a recurrence of TTTS (most often due to treatment failure)
51.
Diagnosis of TAPS
•5 stages: I (discordant MCA-PSV) to V (IUFD)
• Can be diagnosed antenatally or postnatally
• Antenatal: MCA-PSV ≥ 1.5 MoM (donor)
≤ 0.8 MoM (recipient) or
Difference in MCA PSV ≥ 1.0 MoM
• Postnatal: Haematological diagnostic criteria-
Inter-twin haemoglobin difference > than 80 g/L
Reticulocyte ratio >1.7
Confirm with placental histopathology postnatally
52.
Discordant Twin
• Significantintrauterine fetal size discordance in monochorionic twins:
Difference in estimated fetal weight [EFW] of greater than 20%
and
Smaller twin with EFW or abdominal circumference (AC) on ultrasound
of < 10th centile for gestation
• It is associated with marginally increased perinatal risk
• Calculate percentage EFW discordance using the following formula:
[larger twin EFW—smaller twin EFW]/larger twin EFW) × 100
53.
Selective Growth Restriction(sGR)
• When the selective fetal discordance is greater than 25%, it is termed
‘selective growth restriction’ (sGR)
• Present in up to 20% of monochorionic twins
60% of monochorionic twins complicated by TTTS
• Due to unequal placental sharing or perfusion
• UA Doppler vital for classification
• Associated with fetal demise and neurologic injury
• Early recognition improves intervention planning
54.
Diagnosis of SelectiveGrowth Restriction (sGR)
Estimated fetal weight [EFW] of one twin is less than 3rd centile
OR
there are 2 of the following 3 parameters—
(i) A growth discordance of greater than 25% difference in EFW between
the fetuses
(ii) The smaller fetus having an EFW or AC less than 10th centile for
gestation
(iii) Abnormal umbilical artery (UA) Doppler of the smaller fetus (UA-PI
of greater than 95th centile or shows absent or reversed end-diastolic
velocity)
55.
sGR Types Basedon UA Doppler
• Type I: Growth discordance but positive diastolic velocities in both fetal
umbilical arteries
• Type II: Growth discordance with absent or reversed end-diastolic
velocities (AREDV) in one or both fetuses
• Type III: Growth discordance with “cyclical” umbilical artery diastolic
waveforms
56.
Diagnostic difficulty insGR
• May be a diagnostic ‘overlap’ between mild TTTS and sGR
• Liquor volumes as DVP should be measured to differentiate from TTTS
Amniotic fluid (DVP) in TTTS Amniotic fluid (DVP) in sGR
Donor twin → oligohydramnios
Recipient twin → polyhydramnios
Oligohydramnios in one of the
amniotic sacs
Normal liquor in the other amniotic
sac
57.
Prognosis of babywith sGR
• Type I sGR: Relatively good, more than 90% perinatal survival
• Type II sGR: High risk (up to 29%) of intrauterine demise of the
growth-restricted twin and/or preterm birth
• Type III sGR:
Smaller twin: 10%–20% risk of the unexpected fetal demise (even if
stable USG and/or normal CTG hours or days before)
Larger twin: 10%–20% risk of neurological injury
58.
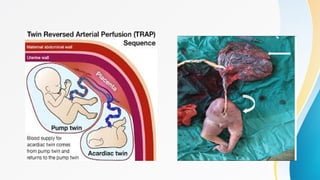
Twin reversed arterialperfusion (TRAP) sequence
• Approximately 1% of monochorionic twins are affected
• 1acardiac twin, 1 pump twin
• Acardiac twin lacks heart, fed by pump twin
• Reverse flow via AA anastomosis
• Poor prognosis if acardiac twin >50% pump twin size
• Early diagnosis key to improving outcome
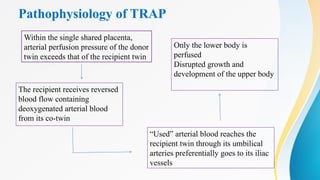
59.
Pathophysiology of TRAP
Withinthe single shared placenta,
arterial perfusion pressure of the donor
twin exceeds that of the recipient twin
The recipient receives reversed
blood flow containing
deoxygenated arterial blood
from its co-twin
“Used” arterial blood reaches the
recipient twin through its umbilical
arteries preferentially goes to its iliac
vessels
Only the lower body is
perfused
Disrupted growth and
development of the upper body
60.
Pathophysiology of TRAP(contd...)
• Failed head growth → Acardius acephalus
• Partially developed head with identifiable limbs → Acardius
myelacephalus
• Failure of any recognizable structure → Acardius amorphous
Normal donor twin supports its own circulation & also must pump
blood to the acardiac recipient
Cardiomegaly and high-output heart failure in donor twin
62.
TRAP Diagnosis
• Ultrasoundshows absent cardiac activity in acardiac twin
• Reversed umbilical artery flow in acardiac twin
• Large size discrepancy with pump twin
• Risk stratification by acardiac:pump size ratio
• Subcutaneous edema, abnormal morphology typical
• Confirmed via Doppler and structural scan
63.
Single Fetal Demise
•IUFD in one twin affects co-twin via shared circulation
• After a single fetal death in a monochorionic pregnancy:
Risks of death to the surviving twin 15%
Risk of neurological abnormality 26%
64.
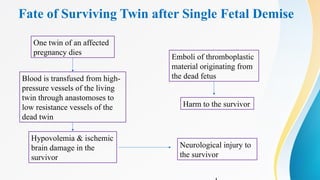
Fate of SurvivingTwin after Single Fetal Demise
One twin of an affected
pregnancy dies
Blood is transfused from high-
pressure vessels of the living
twin through anastomoses to
low resistance vessels of the
dead twin
Hypovolemia & ischemic
brain damage in the
survivor
Emboli of thromboplastic
material originating from
the dead fetus
Neurological injury to
the survivor
Harm to the survivor
65.
Single Fetal Demise(contd…)
Diagnosing Neurological Damage:
• MRI with diffusion-weighted imaging (DWI)
• Best after 4 weeks post-IUFD
• Detects ischemic lesions earlier than ultrasound
• Ultrasound may miss early hypoxic injury
• Types: porencephaly, encephalomalacia, hydrocephalus
• Important for prognostication and parental counselling
Antenatal Care Principles
•Specialist-led care recommended
• Regular emotional support and reassurance
• Early counselling regarding twin risks
• Discuss screening complexity and options at booking
• Tertiary care referral for complications
• Nutritional advice, weight monitoring & hydration
68.
Supplements and AspirinUse
• Iron folic acid & calcium supplementation
• Vitamin D supplementation if deficient
• Aspirin 100–150 mg from 12–36 weeks as per guideline
• Reduces risk of preeclampsia and placental dysfunction
• Encourage compliance and monitor blood pressure regularly
69.
Antenatal Visit Schedule
•Determination of chorionicity & screening for chromosomal anomaly at
11 +2
– 14+1
weeks of gestation
• Every 2-week scans from 16 to 36 weeks
• Biometry, amniotic fluid (DVP), Doppler studies
• Cervical length monitoring at 20–24 weeks
• Detailed anomaly scan at 20 weeks
• Delivery planning at 36 weeks if uncomplicated
Management of TTTS
•Stage I: Expectant with close follow-up
• Stages II–IV: Fetoscopic laser coagulation (preferred)
Laser superior to amnioreduction for survival/neuroprotection
Post-26 weeks: amnioreduction may be considered
• Stage V: Palliative care, no active intervention
• Decision guided by gestational age and expertise availability
TTTS presenting before 26 +0 weeks of gestation should be treated by
fetoscopic laser ablation rather than amnioreduction or septostomy. After
26 +0 weeks of gestation care should be individualised
T
72.
Foetoscopic Laser Types
•Selective: Coagulates only visible AV connections
• Sequential: Prioritizes AV over AA/VV anastomoses
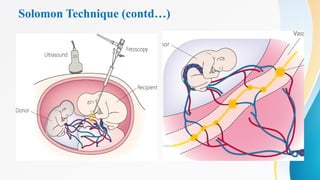
• Solomon: Equatorial laser dichorionisation
Coagulate the entire vascular equator of the placenta, effectively creating a
barrier between the twins' circulations and minimizing the risk of residual
anastomoses
73.
Solomon Technique
Advantage
1. Improvedsurvival rate
2. Reduces the risk of residual
anastomoses→ decreased
recurrence of TTTS or the
development of TAPS
Risk
1. Higher risk of placental
damage
2. Placental abruption
3. PROM, PPROM, preterm
labour
Post-laser Follow-up
• Weeklyultrasound assessment (including examination of the fetal brain,
heart and limbs)
• Serial measurements of UA-PI, MCA PSV and Ductus Venosus Doppler
velocities
• After 2 weeks post-treatment, the ultrasound interval may be increased to
every 2 weeks (UA-PI, MCA PSV, DVP and EFW)
• In treated TTTS pregnancies, an ultrasound examination of the fetal heart
should be performed by the fetal medicine specialist to exclude
functional and acquired structural heart anomalies
76.
Outcomes of LaserTherapy
• 70–88% survival of at least one twin
• Both twins survive in ~60% cases
• Reduced rates of neurological damage compared to amnioreduction
• TAPS can still occur after incomplete coagulation
• Higher complications if done <17 or >26 weeks
• Early intervention improves prognosis
77.
Amnioreduction
• Reduces intra-amnioticpressure
• Improves uteroplacental perfusion transiently
• Not curative—symptomatic relief only
• Indicated post-26 weeks or where laser unavailable
• Requires multiple procedures often
• Risks include PPROM, infection, fetal loss
78.
Septostomy
• Intentional ruptureof intertwin septum
• Equalizes amniotic pressures between sacs
• May create monoamniotic environment → cord entanglement
• Rarely used due to complications
• May reduce frequency of repeat interventions
• Limited evidence for routine use
79.
Timing of Deliveryin Monochorionic Twin with
TTTS
• Delivery of monochorionic twin pregnancies with treated TTTS should
be at 36 completed weeks of gestation, unless there are complications
• The role of delayed umbilical cord clamping is controversial because of
the theoretical risks of feto-fetal transfusion with ‘intact’ placental
anastomoses
80.
TAPS Management
• Careoptions may include:
(i) Conservative management with close observation and surveillance
(ii) In utero transfusion [of the anaemic twin] with or without exchange
transfusion [of the polycythaemic fetus]
(iii) Fetoscopic laser ablation
(iv) Selective termination of pregnancy (in some circumstances)
81.
TAPS: Neonatal Outcomes
•Common issues: anemia, polycythemia, thrombocytopenia
• Donor twin: Transfusion needs postnatally
• Recipient twin: Polycythemia & hyperviscosity: limb ischemia & NEC
risk
• Neurologic impairment in 10–17% survivors
• No difference in impairment between donor/recipient
• Close pediatric follow-up essential
82.
Management of sGR
•Evaluation in a fetal medicine centre
• Ultrasound at an interval of 2 weeks with fetal Doppler assessment (UA
PI, MCA PI, PSV and Ductus venosus) weekly
• In early-onset sGR with poor fetal growth velocity and abnormal
Doppler → selective reduction or fetoscopic laser ablation considered to
save the appropriately grown co-twin
83.
Management of sGR(contd...)
• Longer ‘latency period’ between diagnosis and timing of birth in MC
twins complicated by sGR because of:
The placental anastomoses in monochorionic twins paradoxically may be
beneficial for the smaller twin as a transfusion from the larger twin may
compensate for the placental insufficiency
Associated artery–artery anastomoses also helps
Latency period is 10 weeks compared to 3-4 weeks in FGR
84.
Management of sGR(contd...)
Timing of birth: Following are considered:
Abnormal DV Doppler waveforms
Computerised CTG (STV)
Fetal biometric measurement and growth velocities
• In type I sGR → 34 +0
–35 +6
weeks of gestation
(if satisfactory fetal growth velocity and normal UA doppler)
• In type II and III sGR → 32 weeks of gestation
(unless fetal growth velocity is significantly abnormal or there is a
worsening of the fetal doppler)
85.
Management of sGR(contd...)
• Inform parents that in sGR and TTTS (even after successful treatment)
there can be acute and serious complications like
Sudden transfusional events (neither predictable nor preventable)
Neurological morbidity
• Despite regular monitoring, there may still be adverse perinatal outcomes
86.
TRAP Management
• Expectantmanagement if small acardiac twin
• Intervene if acardiac twin large or pump twin shows cardiovascular
impairment
• Cord occlusion or RFA between 12–16 weeks ideal
• Goal: Prevent pump twin heart failure or IUFD
• TRAPIST trial evaluating early vs late intervention
• ~80% pump twin survival with intervention
87.
Single Fetal Demise:Management
• Weekly monitoring: CTG, MCA Doppler, BPP
• Coagulation profile at 1 and 3 weeks post-death
• Deliver at 34–36 weeks if stable
• Timing and mode of birth should be individualised
• Corticosteroids for lung maturity
• Avoid invasive interventions unless indicated
• Involve multidisciplinary team (FMU, neurology, neonatology)
88.
Timing of Birthin Uncomplicated MC Twin
• Plan delivery at 36+0
weeks if uncomplicated
• Earlier if complications: TTTS, sGR, IUFD
• If preterm birth planned :
(i) up to 34 +6
weeks of gestation → Antenatal corticosteroid
(ii) before 34 +0
weeks of gestation → Magnesium sulfate
• Avoid delay beyond 36 weeks due to IUFD risk
• Mode of delivery depends on fetal presentation and parity
• Vaginal delivery unless specific indication for CS
• Decision based on risks and parental preference
89.
Complications Specific toMonoamniotic Twin
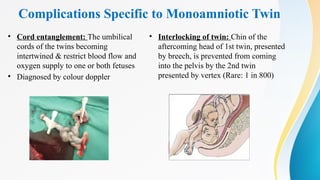
• Cord entanglement: The umbilical
cords of the twins becoming
intertwined & restrict blood flow and
oxygen supply to one or both fetuses
• Diagnosed by colour doppler
• Interlocking of twin: Chin of the
aftercoming head of 1st twin, presented
by breech, is prevented from coming
into the pelvis by the 2nd twin
presented by vertex (Rare: 1 in 800)
90.
Timing of Deliveryin MCMA Twin
• MCMA twins have a high risk of fetal demise and should be a
planned caesarean birth between 32 +0
and 34 +0
weeks of
gestation
91.
Delivery of LockedTwin
Delivery of aftercoming head of first twin is done followed by
pushing the head of second twin out of the pelvis.
If fails
CS is done & after unlocking 2nd
twin is delivered abdominally &
1st
twin vaginally
By Zavanelli manoeuvre the first twin is returned to pelvis & CS
is done to deliver both babies
If 1st
foetus is dead, decapitation of first twin and delivered vaginally, then delivery
of second twin & finally delivery of the head of first twin is accomplished
If fails
If fails
92.
Indication of UrgentDelivery of Second Twin
• Severe vaginal bleeding
• Cord prolapse
• Inadvertent use of IV oxytocics with the delivery of anterior shoulder of
the first baby
• First baby delivered under general anaesthesia
• Appearance of fetal distress
93.
Bottomline
• Incidence oftwins is on the rise
• Being a high risk condition, requires vigilant management.
• Chorionicity determination is important
• Complications are more in monochorionic twins
• Twin management require multidisciplinary approach
Editor's Notes
#27 nausea and vomiting occurs with increased frequency and severity
Prevalence of anaemia is more due to greater blood volume expansion of 50-60%, red cell mass and increase iron and folate requirements
Unexplained weight gain not explained by pe or obesity
Bp- early in pregnancy dbp will be lower than singleton pregnancy and it rises to a greater degree at term
Also preeclampsia is a common association
Women with twin pregnancies have levels of antiangiogenic soluble fms like tk-1(sflt-1) twice that of singleton pregnancy and decreased levels of pigf. Hypertension not only develops often but also earlier and more severe.
hydramnios-mc in mz twins and usually involves 2nd sac( increased renal perfusion and urine output)
Antepartum haemmorhage – increase incidence of placenta previa due to bigger size of placenta encroaching to lower segment , increased incidence of preeclampsia, sudden escape of liquor following rupture of amniotic sac
#28 Malpresentation –more common in second baby
Preterm labour- due to overdistension of uterus hydramnios and prom
Mechanical distress , palpitation, dyspnea , varicosities and haemmorhoids may be increased as compared to singleton pregnancy
gdm
#29 Early rupture of membrane and cord proplapse –increased in second baby
Prolonged labour
Increased operative interference due to malpresentation
Intrapartum bleeding following birth of first baby due to separation of placenta following reduction of placental site
Pph due to atony of uterus because of overdistension , longer time taken by big placenta to separate, bigger surface area of placenta exposing more sinuses , implantation of placenta in lower segment which is less retractile
#31 Size discordancy in dizygotic usually results from unequal placentation with one placental site receiving more perfusion than others.
Degree of growth restriction in monozygotic twins is greater ..generally due to unequal allocation of blastomeres, unequal distribution of nutrients and oxygen within a single placenta and discordant structural anomalies.