Government funded health care: Medicare and Medicaid
Medicare and Medicaid Similarities: Both are federally supported programs enacted in 1965 to provide health care coverage to vulnerable populations Services provided under each program are mandated by the federal government, i.e. feds decide what gets covered under each program and state or local governments have no input
Differences in MCare & MCaid Population covered Medicare provides services to elderly (over 65) and disabled Medicaid provides services to poor Funding mechanism Medicare is funded totally by federal government Medicaid cost is shared between federal government and individual states
Other differences Drug coverage Until recent law, Medicare did not contribute to cost of prescribed drugs Medicaid covered prescribed drugs
Medicare
How does Medicare work Who is eligible? Everyone in the U.S. over the age of 65 who has paid threshold amount (40 quarters) into social security People who are under age 65 and disabled based on criteria set up by Medicare Anyone with End Stage Renal Failure requiring dialysis
Two parts to Medicare: Part A Part A: hospital coverage Covered if patient or spouse has worked 40 or more quarters and paid SS taxes Premium of $189/mo if worked 31-39 quarters  Premium of $343/mo if worked less than 31 quarters
Part B Part B: outpatient coverage Optional Recipient must contribute a premium each month to maintain coverage ($93.53/month) plus $131 deductible Starting 2007, premium will be ‘needs based’ – those earning more than $80,000 a year ($160,000 for a couple) will pay more
Part C Covers up to 30 days of long-term care Who pays after that?  The patient (or no one if the patient can’t afford it) Nursing homes at are risk for not getting paid after the 30 days of Part C run out That’s why it’s so hard to get Medicare patients into nursing homes!
Part D Medication coverage Started January 1, 2006 Does not offer single drug plan: instead lets marketplace develop drug plans with stated formularies and co-pays Legislation specifically forbids federal government from using purchasing power to negotiate for reduced costs of drugs

Part D  Patients must go to Web site and select individual plan Patients directed to sign on by specified period to participate in plan If patient did not sign on by deadline, there is a financial penalty to participate in future Benefits consist of payment for drugs up to $1,500 then catastrophic coverage (>$3,000)
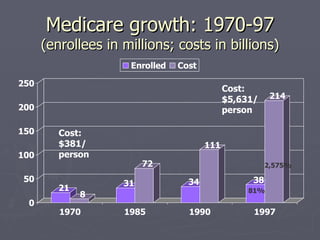
Medicare growth: 1970-97 (enrollees in millions; costs in billions) Cost: $381/ person Cost: $5,631/ person
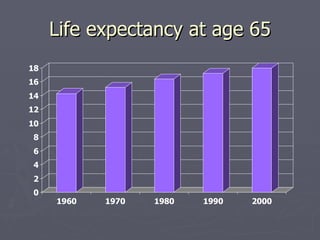
Life expectancy at age 65
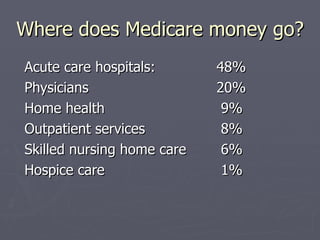
Where does Medicare money go? Acute care hospitals: 48% Physicians 20% Home health  9% Outpatient services  8% Skilled nursing home care  6% Hospice care  1%
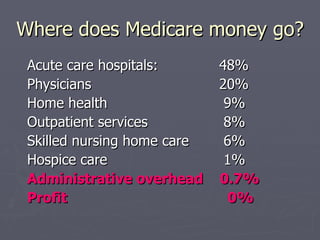
Where does Medicare money go? Acute care hospitals: 48% Physicians 20% Home health  9% Outpatient services  8% Skilled nursing home care  6% Hospice care  1% Administrative overhead  0.7% Profit   0%

What do you get? Hospital care Medicare pays 80% of  the Medicare  allowable  costs for “ medically necessary ” services Patient has a $876 annual deductible before Medicare pays anything (for stays <60 days) Ambulatory care Only covered if recipient elects to pay for Part B Covers 80% of medically necessary services after $100 annual deductible

What do you get? Long term care Medicare only covers up to 30 days in a nursing home Pharmaceuticals Medicare only pays part of pharmacy costs if patient enrolls in Part D Part D supported by additional premium from patient plus co-pay on medications
Medicare payments Who pays the other 20% that Medicare doesn’t cover The patient or Private insurance either paid for by the patient (Medigap insurance) or by pension plan What is the “Medicare allowable cost”? Whatever Medicare says it will pay for that service – Hint: it’s usually a lot lower than you charge!
Who decides what is “medically necessary”? Medicare does Some services are never covered Others are covered on scheduled timeline only  Pap smear covered every year – but must be more than 365 days! Mammogram covered every 2 years
What does Medicare pay? Depends on who you are Original Medicare fee schedule based on usual and customary fee (UCF) in 1965  As new services were established, fee schedule based on providers’ recommendation Resulted in discrepancy between cognitive services (pre-1965) and most procedural services (post-1965)
What if your fee is more than the “Medicare allowable” You can choose to “participate” in Medicare or be a “non-participating” provider Participating providers agree to accept the Medicare allowable as their full compensation – can only bill patient the other 20% Non-participating providers can bill the entire difference to the patient
Medicare reimbursement Reimbursement has been revised periodically over last 40 years Payments to hospitals generally very good Payments to physicians generally bad Reimbursement to MUSC/UMA doctors from Medicare around 25% of charges Other insurers often base their payments on Medicare fee schedule
Medicare reimbursement reform In 1990, Medicare recognized disparity in reimbursement Commissioned a study to look at the relative worth of each service covered by Medicare Worth took into account amount of training needed for the service, time required, risk inherent in the service, and other factors  (study done at Harvard and headed by Bill Hsaio)
RBRVS What was developed was the “Resource based Relative Value System” Each service assigned an RVU (relative value unit) Rationale behind RVU: something that either requires twice as much training, time or risk should be paid twice as much
Payment reform Idea was to gradually shift Medicare payment from arbitrary amounts to some multiple of RVU. Each year Medicare raising rates for underpaid services and reducing payment for overvalued services
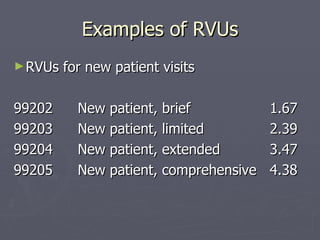
Examples of RVUs RVUs for new patient visits 99202 New patient, brief 1.67 99203 New patient, limited 2.39 99204 New patient, extended 3.47 99205 New patient, comprehensive  4.38
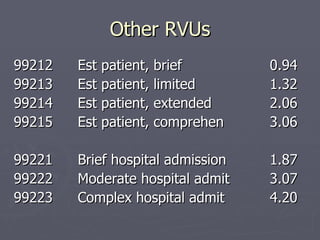
Other RVUs 99212 Est patient, brief 0.94 99213 Est patient, limited 1.32 99214 Est patient, extended 2.06 99215 Est patient, comprehen 3.06 99221 Brief hospital admission 1.87 99222 Moderate hospital admit 3.07 99223 Complex hospital admit 4.20
So how does this work? You submit your bill with the appropriate CPT code (eg. 99214) Medicare then multiplies the RVUs by a conversion factor (2006= $37.8975/RVU) and that’s what is “reasonable cost” But what determines if a visit is a 99212 or  a 99214? – Medicare has rules for that!
Upcoming changes in RVUs CMS updates RVUs periodically For 2007, CMS changed for RVUs for several  services (called CPT codes). RVUs of several procedure codes decreased and RVUs for routine E&M codes increased Projected impact of these on payments vary:  Nuclear med  - 6.34% Diag Rad  - 0.07% Dermatology  2.80%  Opthalmol  5.08% Hem/Onc  20.91%  Fam Med  25.27%
Hospital payment: Prospective payment (DRG) system In 1983, Medicare changed way it reimbursed hospitals for care Prior to 1983, Medicare paid fee-for-service based on charges  Medicare paid more for long stays or excessive use of diagnostic services In 1983, Medicare started paying based on “Diagnostic Related Groups” Shifted risk of cost to hospitals
What is a DRG? DRGs are the 500 most common reasons why people are hospitalized Eg.  “Myocardial infarction without complication”  is assigned a DRG code Every time a Medicare recipient is hospitalized with this diagnosis, the hospital gets a set fee (~$2,400) If the hospital’s cost is less than $2,400 then they make a profit; if it exceeds $2,400 then these lose money
Example DRGS DRG  Dx  Reimbursement  LOS  391 Normal newborn  $622  2.3 127 Heart failure/shock  $4,154  5.5 143 Chest pain  $2,158  2.3 88  COPD  $3,907  5.4 88  Simple pneumonia  $4,444  6.3 (based on 2001 data)
How are DRG costs set? Based on average cost of caring for patient with that clinical condition Adjusted for local differences in costs Adjusted for teaching hospital status Adjusted for disproportionate share of caring for poorer patients Not applied for “outliers”, defined as people whose episode of care is very long or extremely expensive
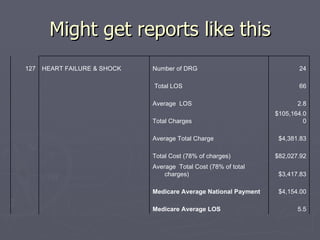
Might get reports like this 127 HEART FAILURE & SHOCK Number of DRG 24     Total LOS 66     Average  LOS 2.8     Total Charges $105,164.00     Average Total Charge $4,381.83     Total Cost (78% of charges) $82,027.92     Average  Total Cost (78% of total charges) $3,417.83     Medicare Average National Payment $4,154.00     Medicare Average LOS 5.5
Shift in Medicare concerns Prior to 1983, Medicare hired utilization reviewers to make sure patients were not staying too long or getting too many tests After 1983, Medicare shifted emphasis to assure that patients were not being discharged too quickly by hospitals Unintended consequence of DRG was the birth and flourishing of “home health care”
Other feature of Medicare: GME Gov’t provides an add-on to teaching hospitals to pay for GME (residency) training Hospitals get a premium (25-40%) increase in every DRG depending on the number and types of residents in their hospital Direct training expenses: salaries, call rooms, etc. Indirect training expenses: added cost of care to patient because residents are caring for them
Future of Medicare Payment will be linked to quality of service Hospitals that provide good care will get “raises” Hospitals that provide poor care will get reimbursement decreased Results of quality measures will be made public Next initiative to look at physician quality (P4P = pay for performance) Currently, standards for good care being developed
Report cards Medicare has started public web sites so that consumers can compare hospital performance for several diseases We can look today at  www.HospitalCompare.hhs.gov  and compare hospitals in the same city In the near future, patients will be able to do the same and compare doctors
Medicaid
Medicaid Federal-state partnership Federal gov’t matches money put up by state Match depends on program and wealth of state Ranges from a 2/1 match ($2 fed/$1 state) to a 4/1 match
Program available for M’caid AFDC (Aid to Families with Dependent Children)  SCHIP (state children’s health insurance program) Family planning services HIV care coverage Disability coverage
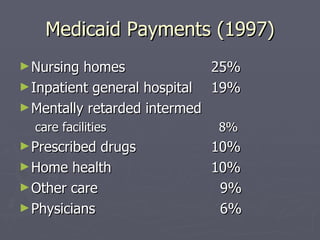
Medicaid Payments (1997) Nursing homes 25% Inpatient general hospital 19% Mentally retarded intermed care facilities   8% Prescribed drugs 10% Home health 10% Other care   9% Physicians   6%
Medicaid funding Total amount of funding for state depends on how wealthy they are (for match) and how much they put up Poorer states that can afford to put up less money for Medicaid then have less to spend for services So how do they provide care for Medicaid recipients if they have less money?
Dealing with lack of MCaid funds Because services covered by Medicaid are mandated by federal government, cannot cut back on what is available to patients Only ways to deal with less money:  Cover fewer people  Pay less for service
Eligibility requirements Usually set at different levels for different services AFDC usually most restrictive Pregnancy covered up to 185% of FPL sCHIP covered up to 200% of FPL HIV care covered regardless of income
Medicaid payments Usually very little compared to private payers Often less than even Medicare payments for same services Results in fewer doctors wanting to care for Medicaid patients (less access to care)
How do states stack up http://www2.citizen.org/hrg/medicaid/
Oregon Health Plan In mid-1990’s, Oregon proposed a new way of offering Medicaid (and health coverage in general) Instead of restricting eligibility, they proposed to make everyone eligible but limit what they paid for And what they would cover, they would pay for well so that patients would have access
The Oregon Plan Put together their plan based on the threat to health and evidence of benefit of treatment and ranked all common health care services Provide coverage to everyone under the federal poverty level for all approved services Decide how far down on the list the state could go based on the funding provided
Example of the list Pneumococcal Pneumonia Acute Appendicitis ……… 81. Otitis media age > 6 month 82. Acne vulgaris 83. Ingrown toenails 84. Plantar fasciitis 85. Tinea capitus
Legislature provides $200 million Pneumococcal Pneumonia Acute Appendicitis ……… 81. Otitis media age > 6 month 82. Acne vulgaris 83. Ingrown toenails 84. Plantar fasciitis 85. Tinea capitus
Legislature provides $210 million Pneumococcal Pneumonia Acute Appendicitis ……… 81. Otitis media age > 6 month 82. Acne vulgaris 83. Ingrown toenails 84. Plantar fasciitis 85. Tinea capitus
Other key component of plan Plan required all Oregon employers to offer either insurance that covered the same service of Medicaid  Or employers could pay state equivalent of Medicaid cost and employees would be covered by Medicaid
Future of Medicaid States struggling to fund Medicaid costs Most have moved to restrictive drug access such as formularies or pre-authorization Many states have mandated managed care for Medicaid or offered patients incentives to participate in managed care programs Access continuing to be an issue because of poor payment