MECHANISM OF BREATHING
INSPIRATION AND EXPIRATION
NEHA ANSARI
B.PHARM 3RD
YEAR
ASHA PHARMACY COLLEGE
MECHANISM OF BREATHING
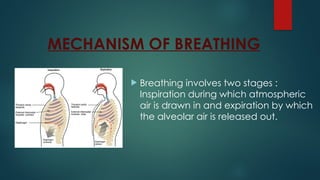
 Breathing involves two stages :
Inspiration during which atmospheric
air is drawn in and expiration by which
the alveolar air is released out.
INSPIRATION
 The process of intake of atmospheric air is known as inspiration. It
is an active process.
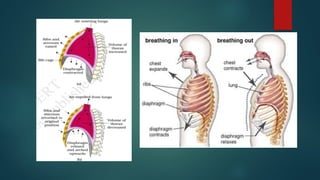
 In the process of inspiration, there would be a contraction of
muscles attached to the ribs on the outer side which pulls out the
ribs and results in the expansion of the chest cavity.
 Later, the diaphragm, contracts, moves downwards and
expands the chest cavity resulting in the contraction of the
abdominal muscles.
 The expansion of the chest cavity produces a partial vacuum
which sucks air into the lungs and fills the expanded alveoli.
MECHANISM OF INSPIRATION
 When the volume of the thorasic cavity increases and the air
pressure decreases, inspiration takes place.
 Contraction of external intercostal muscles increases the
volume of the thorasic cavity.
 Contraction of the diaphragm further increases the size of the
thorasic cavity. Simultaneously, the lungs expands.
 With the expansion of the lungs, the air pressure inside the
lungs decreases.
 The pressure equalizes and the atmospheric air rushes inside
the lungs.
INHALATION
Brain respiratory center activated ( Medulla & Pons)
Nerve signals sent through phrenic & intercostal muscles
contract.
Diaphragm contracts – moves downward
External intercostal muscles contracts
Rib cage moves upwards & outwards
Volume of Thorasic cavity increases & pressure in
alveoli decreases
Air flows into lungs
EXPIRATION
 The process of exhaling carbon dioxide is called
expiration. It is a passive process.
 The expiration process is considered once after the
gaseous exchange occurs in the lungs and the air is
expelled out.
 During this process, muscles attached to the ribs
contract, the muscles of the diaphragm and the
abdomen relax which leads to a decrease in the volume
of the chest cavity and increases the pressure of the
lungs, causing the air in the lungs to be pushed out
through the nose.
MECHANISM OF EXPIRATION
 It occurs when the size of the thorasic cavity decreases and the
air pressure increases.
 Now the external intercostal muscles relax and the internal
intercostal muscles contract.
 As a result, the ribs are pulled inwards and the size of the thorasic
cavity is reduced.
 The diaphragm is relaxed and the lungs get compressed.
 Consequently, the pressure increases and the air is forced
outside.
EXHALATION
Internal intercostal muscles contracts
External intercostal muscles relax ,Diaphragm relax
Rib cage moves downwards & inwards
Volume of thorasic cavity decreases
Pressure in alveoli increase
Air moves out.
MUCUS
 Mucus is a thick, slippery secretion
produced by submucosal glands and
goblet cells, located in the airway
epithelium.
COMPOSITION OF MUCUS
Mucus is mostly water, plus :
 Mucins ( Glycoproteins ) give thickness and elasticity
 Electrolytes
 Antibodies ( IgA )
 Enzymes
 Trapped particles ( dust, microbes ).
HOW MUSUS SECRETS IN LUNGS ?
 Production mechanism : Goblet Cells in the
surface epithelium and glands in the large airways
produce mucins, which are released via exocytosis.
 Structure : It forms a two - layer system : a high -
viscosity gel layer on top and a low – viscosity, watery
layer below, which helps the cilia beat properly.
 Regulation : Secretion is controlled by
neurotransmitters and inflammatory mediators.
- Infections, allergies and irritants like smoke
trigger increased production.
 Pathology : Conditions like COPD, Asthma and cystic
fibrosis can cause excessive , thick mucus production
( hypersecretion ) that overwhelms the cilia , leading
to coughing and breathing difficulties.
 Clearance : Tiny hair - like structures called cilia
constantly beat in a coordinated way.
- They push the mucus upward toward the throat.
- This is called the mucocilliary escalator.
FUNCTIONS
-Traps dust, germs , smoke, bacteria, viruses and
pollutants , so they don’t reach deep lung tissue.
Drugs Used in Treatment of Cough
EXPECTORANTS & ANTITUSSIVES
COUGH
 Cough is a protective reflex, its purpose being expulsion of
respiratory secretions or foreign particles from air passages.
 It occurs due to stimulation of mechano - or
chemoreceptors in throat, respiratory passages or stretch
receptors in the lungs. Cough may be useful or useless.
 Useless ( nonproductive ) cough should be suppressed.
 Useful ( productive ) cough serves to drain the airway, its
suppression is not desirable, may even be harmful, except if
the amount of expectoration achieved is small compared
to the effort of continuous coughing.
MECHANISM OF COUGH
Stimulation of mechano – or chemoreceptors ( throat, respiratory
passages or stretch receptors in lungs )
Afferent impulses to cough center (medulla )
Efferent impulses via parasympathetic & motor nerves to diaphragm,
intercostal muscles & lung
Increased contraction of diagrammatic, abdominal & intercostal
(ribs) muscles noisy expiration ( cough )
DRUGS FOR COUGH
PHARYNGEAL DEMULCENTS
 Pharyngeal demulcents sooth the throat and reduce afferent
impulses from the inflamed/irritated pharyngeal mucosa, thus
provide symptomatic relief in dry cough arising from throat.
Lozenges
Syrups
Glycerine
Liquorice
LOZENGES
 Throat lozenges are medicated,
dissolvable tablets designed to soothe
sore throats, reduce irritation and
suppress coughs by increasing saliva
and delivering ingredients like menthol,
honey, or antiseptics directly to the
throat.
EXPECTORANTS
 Expectorants are the drugs that help in removing sputum from
respiratory tract either by increasing fluidity of sputum or
increasing the volume of fluid. That have to be expel from the
respiratory tract by coughing.
 These are the agents which enhance the secretion of sputum
from trachea, bronchi or lungs and hence they are used in
treatment of cough.
CLASSIFICATION OF EXPECTORANTS
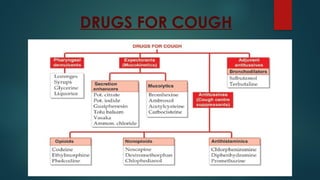
 Based on MOA they are categorized into two types:
1. Secretion Enhancer
Pot. Citrate
Pot. iodide
2. Mucolytics
Bromhexine
Acetylcystein
SECRETION ENCENCER
Expectorants
Increase bronchial secretion or decreases viscosity of cough
Easy removal of cough
MUCOLYTICS
These agents dissolve thick mucous
Helps to relieve respiratory difficulties
By breaking disulfide bonds in mucopolysaccharides
Decreases the viscosity of secretions
Easy expulsion of mucous
ANTITUSSIVES
 Antitussives are drugs that suppress coughing, possibly
by reducing the activity of the cough center in the
brain.
 Antitussives agents are used to relieve dry cough.
CLASSIFICATION OF ANTITUSSIVES
 1.Opioids: Ex- Codeine, Ethyl morphine, pholcodine
 2.Nonopiods: Ex- Noscapine, Dextromethorphan
 3.Antihistaminics: Ex- Chorpheniramine
 4.Adjuvant antitussives/Bronchodilators:
Ex- Salbutamol, Terbutaline
OPIOIDS
 Opioids suppress the cough reflex by acting on the cough
center in the medulla.
CODEINE
 Selectively suppress cough center in medulla oblongata.
 Pharmacokinetics :
1.Well absorbed from oral and injection.
2.10% converted to morphine through demethylation.
NONOPIOIDS
 Suppress the cough reflex by numbing the stretch receptors in
the respiratory tract and preventing the cough reflex from
being stimulated.
ANTIHISTAMINICS
 It is a sedative and have anticholinergic action.
 They have lack selectivity for cough center.
ADJUVANT ANTITUSSIVES/BRONCHODILATORS
 Bronchospasm can induce or aggravate cough. Stimulation of
pulmonary receptors can trigger both cough and
bronchoconstriction, especially in individuals with bronchial hyper
reactivity.
 Bronchodilators relieve cough in such individuals and improve the
effectiveness of cough in clearing secretions by increasing surface
velocity of airflow during the act of coughing.
SALBUTAMOL
Salbutamol
Activates beta-2 receptor in bronchial smooth muscle
Activates adenyl cyclase activity
increase cAMP
smooth muscle relaxation
Bronchodilation
THANK YOU