MANAGEMENT OF
POSTMENOPAUSAL
SYNDROME
BY DR. DEVANSHI THAKKAR
JUNIOR RESIDENT 1
DEPT OF PHARMACOLOGY AND THERAPEUTICS
KGMU, LUCKNOW
INTRODUCTION
• Menopause is defined as the time of cessation of ovarian function resulting in
permanent amenorrhea.
• It usually occurs between 45 to 60 years of age, 47 being the average age.
• The age at menopause appears to be genetically determined and is
unaffected by race, socioeconomic status, age at menarche, or number of
prior ovulations.
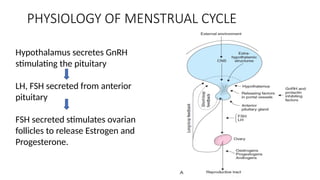
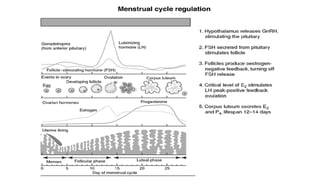
PHYSIOLOGY OF MENSTRUAL CYCLE
Hypothalamus secretes GnRH
stimulating the pituitary
LH, FSH secreted from anterior
pituitary
FSH secreted stimulates ovarian
follicles to release Estrogen and
Progesterone.
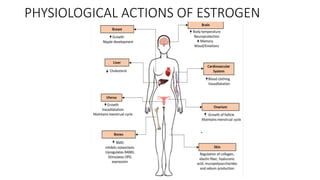
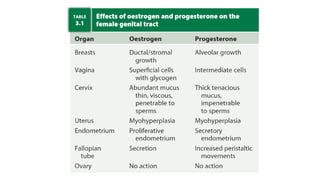
PHYSIOLOGICAL ACTIONS OF ESTROGEN
PHYSIOLOGY OF MENOPAUSE
• During onset of menopause stage, ovarian activity declines.
• As ovulation fails, no corpus luteum forms and no progesterone is secreted
by the ovary. Therefore all the cycles are anovulatory and irregular.
• Later, Graafian follicles also fail to develop, estrogenic activity is reduced
and endometrial atrophy leads to amenorrhea.
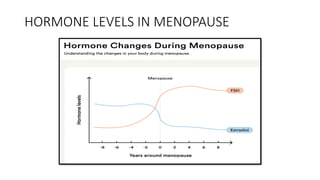
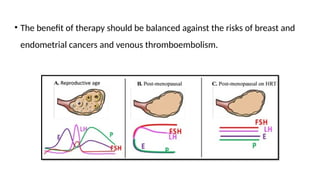
• Cessation of ovarian activity and a fall in the estrogen cause a rebound
increase in the secretion of FSH and LH by the anterior pituitary gland.
• The FSH level may rise as much as 50-fold and LH 3-4 fold.
• With further advancing years, gonadotropin activity of the pituitary gland
also ceases, and a fall in FSH level eventually occurs.
• There is 50% reduction in androgen production and in estrogen at
menopause.
HORMONE LEVELS IN MENOPAUSE
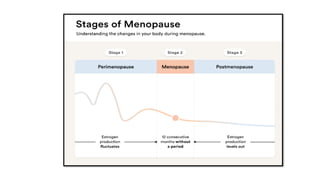
PERIMENOPAUSE
• Menopausal transition, or ‘perimenopause’, is a defined period of time
beginning with the onset of irregular menstrual cycles until the last
menstrual period. It is a period of 3–4 years before menopause.
• This period is associated with declining estrogen levels.
INVESTIGATIONS FOR MENOPAUSE
• History of various symptoms.
• General examination includes blood pressure recording, weight
measurement.
• Blood sugar, lipid profile, ECG.
• Mammography, pelvic ultrasound.
• Bone density study. DEXA is the test used.
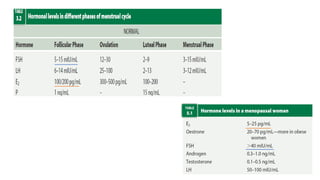
• Oestrogen (E2) and FSH levels to decide on the need of HRT.
• Endometrial biopsy in women on HRT.
POSTMENOPAUSAL SYMPTOMS
• Hot flushes
• Headache
• Mood swings
• Insomnia
• Difficulty in concentration
• Mental confusion
• Depression
• Stress incontinence
• Urge incontinence
• Osteoporotic symptoms
• Irritability
• Tiredness
• Dyspareunia
VASOMOTOR SYMPTOMS
• Vasomotor symptoms affect up to 75% of peri-menopausal women and hot
flushes and sweating are the most common and most noticeable symptoms
for women to seek care for.
• Hot flushes are the waves of vasodilation affecting the face and the neck
and these last for 2–5 min each. These are followed by severe sweating.
• Several of these flushes occur in a day, but are more severe during the night, and
can disturb sleep.
• Mental depression due to disturbed sleep therefore cause irritability and lack of
concentration.
• Palpitation and anginal pains may even be felt.
TREATMENT
• Natural estrogens are used for short duration of
time as 3 to 6 months.
• Oral Premarin (E1-natural equine-conjugated
estrogen) in the dose of 0.625 mg daily, increasing
to 1.25 mg if necessary, ethinyl estradiol 0.01 mg,
micronized estrogen (1-2 mg) or Evalon 1-2 mg are
effective.
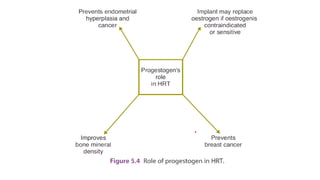
• Progesterone such as Duphaston (medroxyprogesterone)
10 mg for 10-12 days each month should be added to
prevent endometrial hyperplasia and carcinoma caused by
estrogen.
• Combined estrogen and progesterone is given to avoid
endometrial hyperplasia and carcinoma in the form of
tablet like Femoston (1mg+5mg) is available.
OTHER DRUGS
• Agents that decrease central noradrenergic tone, such as clonidine,
relieve hot flushes.
• Clonidine may be used orally (0.1-0.2 mg/day) or as a weekly
transdermal patch (0.1 mg/day). Potential side effects include
orthostatic hypotension and drowsiness.
• Gabapentin is a non-hormonal anticonvulsant that reduces hot flushes
by 50% if given in a dose of 900-2400 mg daily.
UROGENITAL ATROPHY
• Urogenital atrophy results in vaginal dryness and pruritus, dyspareunia,
dysuria, and urinary urgency.
• The stress incontinence is caused by poor vascularity and tone of the
internal urinary sphincter.
• Prolapse of genital tract and stress incontinence of urine and feces are
mostly menopausal related.
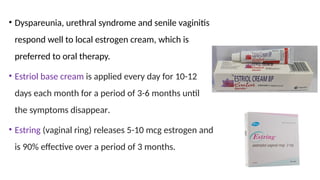
• Dyspareunia, urethral syndrome and senile vaginitis
respond well to local estrogen cream, which is
preferred to oral therapy.
• Estriol base cream is applied every day for 10-12
days each month for a period of 3-6 months until
the symptoms disappear.
• Estring (vaginal ring) releases 5-10 mcg estrogen and
is 90% effective over a period of 3 months.
OSTEOPOROSIS
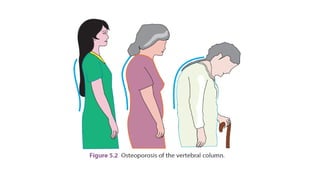
• It is an incipient slowly progressing skeletal disorder characterized by
microarchitectural deterioration of bone mass resulting in increased fragility
and predilection to fracture in the absence of significant trauma.
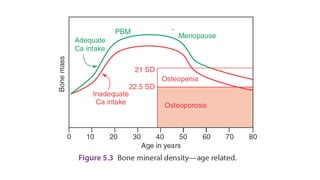
• Osteoporosis is defined as a condition in which there is a fall in bone mass
exceeding 2.5 standard deviations (SD) below the mean for young adults.
• It is important to consider bone mineral density screening for high-risk
women.
• Musculoskeletal symptoms characterized by backache, fractures on
minimal trauma, decreased height, and mobility are common due to
osteoporosis.
• Estrogen deficiency is the dominating factor contributing to osteoporosis
in women.
• Additional contributing factors such as calcium and vitamin D deficiency
also need consideration.
TREATMENT
• Drug therapies for the prevention and treatment of
osteoporosis are principally anti-resorptive drugs that reduce
bone loss and anabolic agents that stimulate new bone
formation.
• Raloxifene, a nonsteroidal compound, is a selective estrogen
receptor modulator (SERM), which reduces the risk of
fracture by 50%, especially vertebra by increasing BMD by 2-
3%.
• Bisphosphonates such as Alendronate (5 mg daily or 35 mg weekly) and
Risedronate (5 mg daily or 35 mg once a month) reduce bone resorption
through the inhibition of osteoclastic activity.
• Bisphosphonates should not be given with calcium, because its absorption
is reduced.
• Calcium should be taken in the morning and alendronate swallowed (not
chewed) in the afternoon, on an empty stomach with a glass of water in
the upright position. This reduces the esophageal irritation.
• Milk and antacid can reduce gastric irritation.
• After 60 years, osteoporosis should be managed with bisphosphonates.
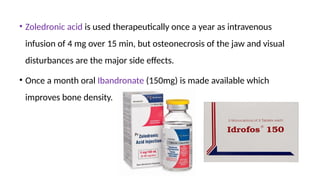
• Zoledronic acid is used therapeutically once a year as intravenous
infusion of 4 mg over 15 min, but osteonecrosis of the jaw and visual
disturbances are the major side effects.
• Once a month oral Ibandronate (150mg) is made available which
improves bone density. by 5-10%.
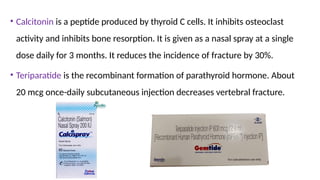
• Calcitonin is a peptide produced by thyroid C cells. It inhibits osteoclast
activity and inhibits bone resorption. It is given as a nasal spray at a single
dose daily for 3 months. It reduces the incidence of fracture by 30%.
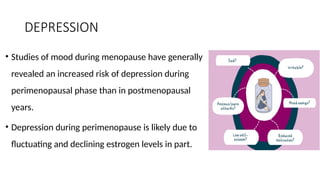
• Teriparatide is the recombinant formation of parathyroid hormone. About
20 mcg once-daily subcutaneous injection decreases vertebral fracture.
CARDIOVASCULAR DISEASES
• Estrogen is cardioprotective by maintaining a high level of high density
lipoprotein (HDL) and lowering the low density lipoprotein (LDL) and
triglycerides.
• Estrogen deficiency therefore can cause atherosclerosis, ischemic heart
disease and myocardial infarction.
• Estrogen prevents atherosclerosis through its antioxidant property.
• Oral Premarin (E1-natural equine-conjugated estrogen) in the dose of
0.625 mg daily, increasing to 1.25 mg if necessary, ethinyl estradiol 0.01
mg, micronized estrogen (1-2 mg) or Evalon 1-2 mg are effective.
• Raloxifene (SERM) causes 10% reduction in total cholesterol and LDL and
raises HDL level. It does not raise the level of triglycerides. It is therefore
cardioprotective in long term.
DEPRESSION
• Studies of mood during menopause have generally
revealed an increased risk of depression during
perimenopausal phase than in postmenopausal
years.
• Depression during perimenopause is likely due to
fluctuating and declining estrogen levels in part.
• Estrogen increases the effects of serotonin and norepinephrine by
decreasing monoamine oxidase (MAO) activity in the CNS, hindering the
breakdown of serotonin and norepinephrine.
• In addition, estrogen increases serotonin synthesis, upregulates 5-HT1
receptors, and downregulates 5-HT2 receptors. Estrogen also increases
norepinephrine activity in the brain.
TREATMENT
• SSRIs are the antidepressants most commonly used in the treatment of
perimenopausal depression.
• SSRIs are thought to be generally safe and effective. The onset of action is 4–6
weeks.
• Several common adverse effects such as gastrointestinal effects (nausea,
diarrhoea, and anorexia), excessive sweating, headache, jitteriness, dizziness,
sedation and insomnia
• For mild depression, hormone replacement therapy (HRT) alone may be
appropriate. Estrogen (0.45–0.625 mg) QD, medroxyprogesterone (1.5-
5 mg) QD.
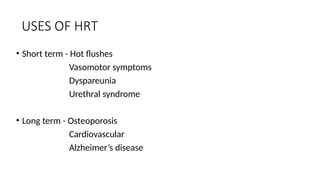
• Mild Tranquillizers - Venlafaxine 30–150 mg daily, Paroxetine 10–20 mg
daily, Gabapentin 300 mg three times a day.
SLEEP DISTURBANCES
• Insomnia occurs in 40–50% of women during the menopausal transition.
• Women with insomnia are more likely than others to report problems such as
anxiety, stress, tension, and depressive symptoms.
• Sleep disturbances during menopause have been associated with estrogen
deficiency or elevated LH levels during late menopause produce poor sleep
quality through a thermoregulatory mechanism, resulting in high core body
temperatures.
• Rates of a sleep apnea increase with age, theories include a relationship to
postmenopausal weight gain or to decreased progesterone levels because
progesterone stimulates respiration.
• In addition to undergoing changes in estrogen and progesterone levels,
postmenopausal women experience a decline in melatonin and growth
hormone levels, both of which have effects on sleep.
USES OF HRT
• Short term - Hot flushes
Vasomotor symptoms
Dyspareunia
Urethral syndrome
• Long term - Osteoporosis
Cardiovascular
Alzheimer’s disease
RISKS OF HRT
• Endometrial cancer
• Breast cancer
• Ovarian cancer
• Thromboembolism
• Lipid profile dysfunction
• Gall stones, liver dysfunction
HRT AND BREAST CARCINOMA
• The risk of breast cancer is not increased up to 3 years of HRT and 5 years of
estrogen alone replacement therapy.
• Lower risk is seen with use of Progesterone in HRT.
• HRT can cause recurrence of breast cancer and is therefore contraindicated in
a woman who has been treated for breast cancer.
• HRT increases the density of breast tissue and impede screening programme
of mammography subsequently.
HRT AND ENDOMETRIAL CARCINOMA
• Estrogen Replacement Therapy can cause well-differentiated carcinoma.
• The risk of cancer with ERT is dose and duration dependent.
• Minimum of 12 days of progesterone added to ERT reduces the risk of
endometrial cancer to 2%.
• Combined estrogen and progesterone provides a better protection
against endometrial cancer.
CONCLUSION OF HRT
• Not every menopausal woman needs HRT.
• A symptomatic woman due to estrogen deficiency requires HRT for 3–6
months. The duration and route of HRT depend upon the purpose for
which the therapy is prescribed.
• Total duration of prophylactic therapy beyond 8–10 years has not proved
beneficial, but side effects may harm the woman.
• The benefit of therapy should be balanced against the risks of breast and
endometrial cancers and venous thromboembolism.
REFERENCES
• Howkins J, Bourne G, editors. Shaw's Textbook of Gynaecology. 16th ed. New Delhi: Elsevier;
2014.
• Brunton LL, Knollmann BC, editors. Goodman & Gilman's: The Pharmacological Basis of
Therapeutics. 14th ed. New York: McGraw-Hill Education; 2018.
• Dalal PK, Agarwal M. Postmenopausal syndrome. Indian J Psychiatry. 2015 Jul;57(Suppl
2):S222-32. doi: 10.4103/0019-5545.161483. PMID: 26330639; PMCID: PMC4539866.
THANK YOU