MENOPAUSE – RAJO NIVRUTTI
DR. JASHANVIR KAUR (PG FIRST YEAR )
DEFINATION
• Permanent cessation of menstruation at the end of reproductive life
due to loss of ovarian follicular activity
• Clinical diagnosis is confirmed following stoppage of menstruation for
twelve consecutive months without any pathology
• FSH level is found elevated around the menopause
• Menopause Transition – when women passes from reproductive to
non reproductive stage ( covers 4-7 years on either side of transition)
• Postmenopause – phase of life that comes after the menopause

AGE OF MENOPAUSE
• Genetically predetermined
• Not related to number of
pregnancy , lactation , use of
oral pill, race , height , weight
• Cigarette smoking and severe
malnutrition may cause early
menopause
• Age of menopause ranges b/w
45-55 years , average being 50
years
CLINICAL IMPORTANCE
Diagnostic Milestone
• Marks the end of reproductive life; defined
as 12 months of amenorrhea without
other cause, usually around age 45–55.
Hormonal Shift Indicator
• Signals a significant decline in estrogen and
progesterone levels, impacting multiple
organ systems and requiring clinical
attention.
Risk Factor for Chronic Diseases
• Increases risk of osteoporosis,
cardiovascular diseases, type 2 diabetes,
and urogenital atrophy due to estrogen
deficiency.
ENDOCRINOLOGY OF MENOPAUSAL TRANSITION AND
MENOPAUSE
HYPOTHALAMO PITUITARY GONADAL AXIS
• Ovarian follicular depletion: With age, the ovarian reserve declines →
fewer responsive follicles.
• Estrogen production drops: Decline in granulosa cells leads to reduced
estradiol synthesis.
• Loss of negative feedback: Low estrogen & inhibin → less suppression of
GnRH → increased GnRH pulsatility.
• FSH & LH levels rise: Chronic elevation due to loss of negative feedback.
FSH rises more than LH (because inhibin mainly suppresses FSH).
• Anovulatory cycles: Follicular development is inadequate → no dominant
follicle → no ovulation.
• Progesterone declines: Due to lack of corpus luteum formation.
ESTROGEN
• Following menopause, the predominant estrogen is estrone and to a lesser
extent estradiol.
• Serum level of estrone (30-70 pg/mL) is higher than that of estradiol (10-20
pg/ml.).
• The major source of estrone is peripheral conversion (aromatization) of
androgens from adrenals (mainly) and ovaries.
• The aromatization occurs at the level of muscle and adipose tissue. The
trace amount of estradiol is derived from peripheral conversion of estrone
and androgens.
• With times, the sources fail to supply the precursors of estrogen and about
5-10 years after menopause, there is a sharp fall in estrogen and also the
trophic hormones. The woman is said to be in a state of true menopause.
ANDROGENS
• After menopause, the stromal cells of the ovary continue to produce
androgens because of increase in LH.
• The main androgens are androstenedione and testosterone. Though the
secretion of androgens from postmenopausal ovary are more, their
peripheral levels are reduced due to conversion of androgens to estrone in
adipose tissue.
• However, the cumulative effect is decrease in-estrogen: androgen ratio.
• This results in increased facial hair growth and change in voice.
• As the obese patient converts more androgens into estrone, they are less
likely to develop symptoms of estrogen deficiency and osteoporosis. But,
they are vulnerable to endometrial hyperplasia and endometrial carcinoma.
GONADOTROPINS
• The secretions of both FSH and LH are increased due to absent
negative feedback effect of estradiol and inhibin or due to enhanced
responsiveness of pituitary to gonadotropin-releasing hormone
(GnRH).
• Rise in FSH is about 10-20 fold whereas that of LH is about 3-fold.
GnRH pulse section is increased both in frequency and amplitude.
During menopause, there is fall in the level of prolactin and inhibin.
• Fall in the level of inhibin, lead to increase in the level of FSH from the
pituitary. Ultimately, due to physiologic aging GnRH and both FSH, LH
decline along with decline of estrogens.
ORGAN CHANGES
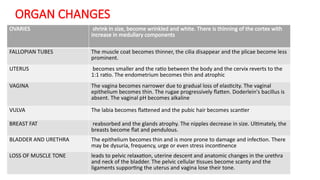
OVARIES shrink in size, become wrinkled and white. There is thinning of the cortex with
increase in medullary components
FALLOPIAN TUBES The muscle coat becomes thinner, the cilia disappear and the plicae become less
prominent.
UTERUS becomes smaller and the ratio between the body and the cervix reverts to the
1:1 ratio. The endometrium becomes thin and atrophic
VAGINA The vagina becomes narrower due to gradual loss of elasticity. The vaginal
epithelium becomes thin. The rugae progressively flatten. Doderlein's bacillus is
absent. The vaginal pH becomes alkaline
VULVA The labia becomes flattened and the pubic hair becomes scantier
BREAST FAT reabsorbed and the glands atrophy. The nipples decrease in size. Ultimately, the
breasts become flat and pendulous.
BLADDER AND URETHRA The epithelium becomes thin and is more prone to damage and infection. There
may be dysuria, frequency, urge or even stress incontinence
LOSS OF MUSCLE TONE leads to pelvic relaxation, uterine descent and anatomic changes in the urethra
and neck of the bladder. The pelvic cellular tissues become scanty and the
ligaments supporting the uterus and vagina lose their tone.
BONE METABOLISM
• Estrogen plays a critical role by: Inhibiting osteoclast activity (reduces
bone breakdown) and Supporting osteoblast function (promotes bone
formation)
• Estrogen levels drop sharply after menopause.
• Loss of estrogen leads to:
• Increased osteoclast activity → More bone resorption
• Decreased osteoblast activity → Less bone formation
• Result: Net bone loss, weakening of bones, and increased risk of
osteopenia and osteoporosis
CARDIOVASCULAR SYSTEM
• Risk of cardiovascular disease is high in postmenopausal women due
to deficiency of estrogen.
• Estrogen prevents cardiovascular disease by several ways. It increases
high- density lipoprotein (particularly HDL2) and decreases low-
density lipoprotein (LDL) and total cholesterol.
• lt inhibits platelet and macrophage (foam cell) aggregation at the
vascular intima. It stimulates the release of nitric oxide (NO) and
prostacyclin from vascular endothelium to dilate the blood vessels.
• It prevents atherosclerosis by its antioxidant property.
MENOPAUSAL SYMPTOMS
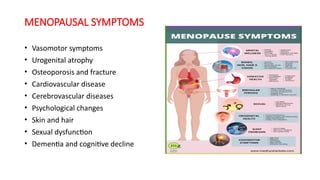
• Vasomotor symptoms
• Urogenital atrophy
• Osteoporosis and fracture
• Cardiovascular disease
• Cerebrovascular diseases
• Psychological changes
• Skin and hair
• Sexual dysfunction
• Dementia and cognitive decline
DIAGNOSIS OF MENOPAUSE
• Cessation of menstruation for consecutive 12 months during
climacteric.
• Average age of menopause: 50 years.
• Appearance of menopausal symptoms 'hot flash' and ‘night sweats’
• Vaginal cytology-showing maturation index of at least 10/85/5
(features of low estrogen).Serum estradiol <20 pg/ml.
• Serum FSH and L 40 mlU/mL (three values weeks interval required)
MANAGEMENT
• PREVENTIONS
Spontaneous menopause is unavoidable. However, artificial menopause
induced by surgery (bilateral oophorectomy) or radiation (gonadal) or
chemotherapy during reproductive period can to some extent be
prevented or delayed.
Counseling: Every woman with postmenopausal symptoms should be
adequately explained about the physiologic events.
TREATMENT
Lifestyle Modifications
Diet:
• Calcium (1000–1200 mg/day), Vitamin D (800–1000 IU/day)
• High fiber, phytoestrogens (soy, flaxseeds), less saturated fats
Exercise:
• Weight-bearing and resistance training → bone health
• Yoga, tai chi → balance and mood
• Sleep hygiene and stress reduction
Non-Hormonal Pharmacological Options
Drug Class Examples Uses
SSRIs / SNRIs Paroxetine, Venlafaxine
Reduce hot flashes and mood
symptoms
Gabapentin Neurontin
Used for hot flashes, sleep
disturbances
Clonidine Centrally acting agent Reduces hot flashes (less common)
Bisphosphonates Alendronate Prevent osteoporosis
SERMs Raloxifene
Prevents bone loss, may reduce
breast cancer risk
Hormone Replacement Therapy (HRT)
Most effective for vasomotor symptoms (hot flashes, night sweats)
Types:
• Estrogen-only (for women without uterus)
• Estrogen + Progesterone (for women with uterus)
Benefits:
• Reduces hot flashes, vaginal dryness, mood swings
• Prevents bone loss and fractures
Risks (especially with long-term use):
• ↑ Risk of breast cancer, blood clots, stroke
• Not recommended for women with history of hormone-sensitive cancers
ABNORMAL MENOPAUSE
PREMATURE MENOPAUSE
• loss of ovarian function and cessation of menstruation before age 40,
leading to early estrogen deficiency.
• It may result from genetic conditions, autoimmune diseases, medical
treatments (like chemotherapy or surgery), or may be idiopathic
• Confirmed by high FSH, low estrogen, and clinical history; further
tests may be done to rule out autoimmune or genetic causes.
• Management - Includes Hormone Replacement Therapy (HRT),
calcium & vitamin D, lifestyle changes, and fertility counseling.
DELAYED MENOPAUSE
• Delayed menopause refers to the onset of natural
menopause after age 55, when menstrual cycles stop
later than average.
• Can be due to genetic factors, obesity, high estrogen
levels, thyroid disorders, or reproductive health
conditions (e.g., PCOS).
• Associated with reduced risk of osteoporosis but
increased risk of estrogen-dependent cancers like
breast, endometrial, and ovarian cancer.
• Management: Focuses on regular cancer screenings,
healthy weight management, and monitoring
cardiovascular and hormonal health.
रजो निवृत्तिः
• सुश्रुत संहिता सूत्रस्थानम् ३५/१६
“ ”
स्त्रीणां पञ्चाशते वर्षे रजो निवृत्तिः।
• अष्टाङ्ग हृदयम् शारीरस्थानम् १/११
“ ”
ततः पञ्चाशते वर्षे स्त्रीणां रजो निवृत्तिः।
• —
धातुक्षय और वृद्धावस्था चरक संहिता, चिकी्त्सास्थानम् १५/५
“ ”
सर्वेषां धातूनां क्षयो वृद्धिरिति स्थिरा।
M2 U3 - menopause traditional medicine .pptx