Lower limb orthotics
MR JALIL SK
Prosthetist &Orthotist
Orthotic Basics
 Derived from the greek worth ORTHO meaning
straight, upright or correct.
 It refers to a static or dynamic device and is preferable
to splint or brace which refers only to a static device.
 Three point pressure principle: forms the mechanical
basis for orthotic correction; a single force is placed at
the area of deformity or angulation; two additional
counter forces act in the opposing direction.
Functions of Orthotics
 Prevent Deformity
 Assist function of a weak limb
 Maintain proper alignment of joints
 Inhibit tone
 Protect against injury of a weak joint
 Allow for maximal functional independence
 Facilitate Motion
Orthotic Consideration
 Cost
 Energy efficiency
 Cosmesis
 Temporary versus permanent
 Dynamic versus static
 Encourage normal Movement
Orthotic Intervention
 Ensure continued proper fit
 Donning/doffing orthosis
 Implement progressive wearing schedule
 Patient/caregiver teaching:
 Skin Inspection
 Care of orthosis
 Mobility training with orthosis
Orthotic Goals
 Maximize functional mobility skills with orthosis
 Maximize independence with donning/doffing
 Maximize independence with wearing schedule
 Maximize independence with skin inspection
 Maximize competence with care of orthosis
Alignment
 Correct alignment permits effective function
 a. minimizes movement between limb and orthoses
(pistoning)
 b. minimizes compression on pressure sensitive tissues
Foot Orthoses (FO)
Common pathological
condition of foot
 Flat feet / Pes planus
 Calcaneal spur
 Planter fascitis
 Metatarsalgia
 Forefoot adduction
 Foot pain
 Ulcer
 Charcot foot
FO
 A semi-rigid or rigid insert worn inside a shoe that
corrects foot alignment and improves function may also
be used to relieve pain. Foot orthotics are custom
molded and are often designed for a specific level of
functioning.
 May be attached to the interior of the shoe (an inserted
pad) or exterior to the shoe.
 Soft inserts (viscoelastic plastic or rubber pads or relief
cut-outs) reduce areas of high loading, restrict forces,
and protect painful or sensitive areas of the feet.
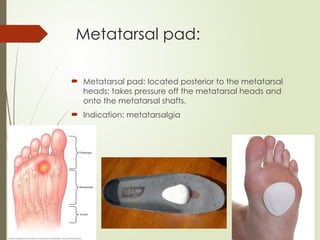
Metatarsal pad:
 Metatarsal pad: located posterior to the metatarsal
heads; takes pressure off the metatarsal heads and
onto the metatarsal shafts.
 Indication: metatarsalgia
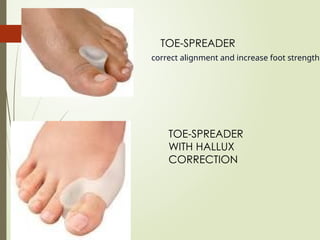
TOE-SPREADER
TOE-SPREADER
WITH HALLUX
CORRECTION
correct alignment and increase foot strength.
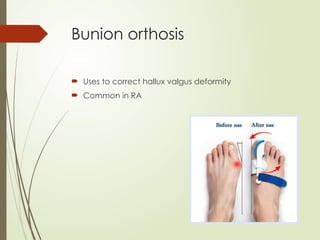
Bunion orthosis
 Uses to correct hallux valgus deformity
 Common in RA
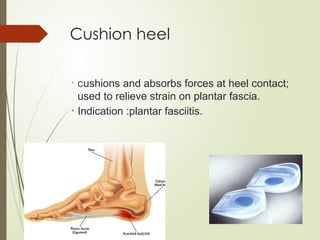
Cushion heel
• Cushions and absorbs forces at heel contact;
used to relieve strain on plantar fascia.
• Indication :plantar fasciitis.
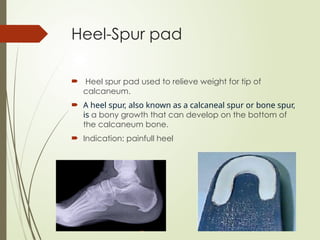
Heel-Spur pad
 Heel spur pad used to relieve weight for tip of
calcaneum.
 A heel spur, also known as a calcaneal spur or bone spur,
is a bony growth that can develop on the bottom of
the calcaneum bone.
 Indication: painfull heel
Longitudinal Arch
Supports
Prevent depression of the subtalar joint and correct
for pes planus (flat foot)
Pes planus
 Pes planus is a common condition in which the medial
longitudinal arches have been lost.
 It is formed by the calcaneus, talus, navicular, three
cuneiforms and first three metatarsal bones.
 Arches do not develop until about 2-3 years of age,
meaning flat feet during infancy is normal.
 This shape allows them to act in the same way as
a spring, bearing the weight of the body and absorbing
the shock produced during locomotion.
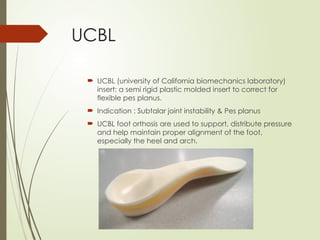
UCBL
 UCBL (university of California biomechanics laboratory)
insert: a semi rigid plastic molded insert to correct for
flexible pes planus.
 Indication : Subtalar joint instability & Pes planus
 UCBL foot orthosis are used to support, distribute pressure
and help maintain proper alignment of the foot,
especially the heel and arch.
Scaphoid Pad:
 used to support the medium longitudinal arch.
 A scaphoid pad is a Myolite padding added to the
medial side of the superior frame and runs along its
medial longitudinal arch.
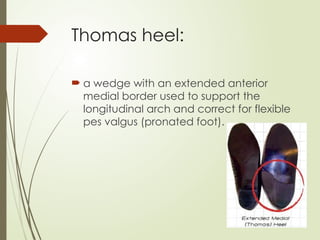
Thomas heel:
 a wedge with an extended anterior
medial border used to support the
longitudinal arch and correct for flexible
pes valgus (pronated foot).
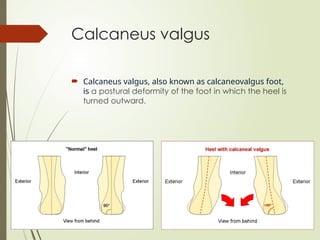
Calcaneus valgus
 Calcaneus valgus, also known as calcaneovalgus foot,
is a postural deformity of the foot in which the heel is
turned outward.
Medial wedge
 Rearfoot posting alters the position of the subtalar joint
or rearfoot from heel strike to foot flat. Must be
dynamic, control but not eliminate STJ function.
 Varus Post (medial wedge): limits or controls eversion of
the calcaneus and internal rotation of the tibia after
heelstrike. Reduces calcaneal eversion during running
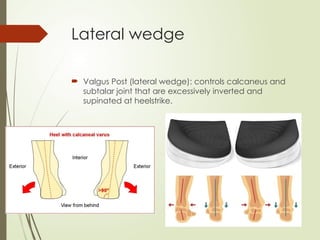
Lateral wedge
 Valgus Post (lateral wedge): controls calcaneus and
subtalar joint that are excessively inverted and
supinated at heelstrike.
Forefoot Posting
 Forefoot posting: suports the forefoot
 Medial wedge prescribed for forefoot varus
 Lateral wedge prescribed for forefoot valgus
 Contraindicated for insensitive foot
Heel raise/ Heel Lifts
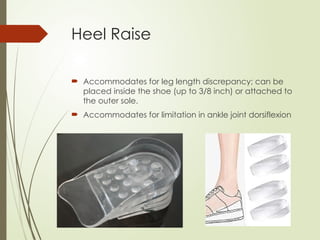
Heel Raise
 Accommodates for leg length discrepancy; can be
placed inside the shoe (up to 3/8 inch) or attached to
the outer sole.
 Accommodates for limitation in ankle joint dorsiflexion
Rocker bar & rocker
bottom
Rocker bar
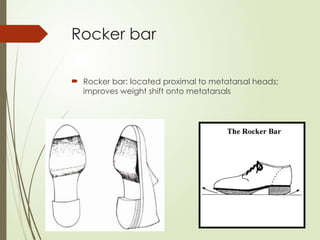
 Rocker bar: located proximal to metatarsal heads;
improves weight shift onto metatarsals
Rocker bottom
 Rocket bottom: builds up the sole over the metatarsal
heads and improves push off in weak or inflexible feet.
May also be used with insensitive feet.
Supramalleolar orthosis
SMO
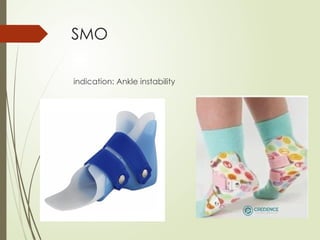
 It supports the foot up to just above the ankle bone,
otherwise known as the malleolus.
 SMOs are typically prescribed to children who have foot
and ankle instability which cannot be controlled by
insoles or footwear.
 The SMO allows dorsiflexion and plantarflexion whilst
stopping mediolateral (side to side) movements.
 It is designed to maintain a neutral heel alignment,
whilst supporting the arch of the foot. The SMO is
proven to help ambulation by helping to improve
standing and walking balance.
SMO
indication: Ankle instability
Ankle-foot orthosis (AFO)
ANKLE-FOOT ORTHOSES
 Used to control the lower extremity during each phase
of the gait cycle for individuals with neuromuscular or
musculoskeletal impairments.

 Categories
1. Static
2. Dynamic
AFO
Conventional Molded
AFO
COMPONENTS
 Foundation- Consists of shoe and plastic/ metal
component
 Ankle control
 Foot control
 Superstructure
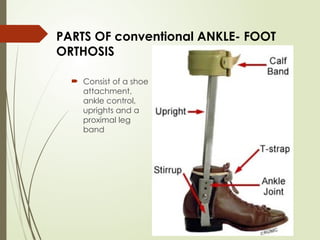
PARTS OF conventional ANKLE- FOOT
ORTHOSIS
 Consist of a shoe
attachment,
ankle control,
uprights and a
proximal leg
band
Shoe attachments & Stirrups
 Foot Plate: a molded plastic shoe insert; allows
application of the brace before insertion into the shoe,
ease of changing shoes of same heel height.
 Stirrup: a metal attachment riveted to the sole of the
shoe; split stirrups allow for shoe interchange solid
stirrups are fixed permanently to the shoe and provide
maximum stability
Uprights and attachments
Conventional AFOs have metal uprights
(aluminum, carbon graphite or steel)
and a hinged ankle joint allowing
plantarflexion and dorsiflexion. Provides
maximum support if the patients
condition is changing (e.g. peripheral
edema), conventional metal AFOs may
be easier to alter to accommodate
changes than molded AFOs.
Uprights and attachments
(bands or shells)
Uprights and attachments
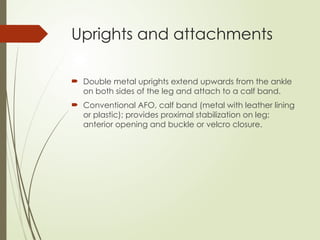
 Double metal uprights extend upwards from the ankle
on both sides of the leg and attach to a calf band.
 Conventional AFO, calf band (metal with leather lining
or plastic); provides proximal stabilization on leg;
anterior opening and buckle or velcro closure.
Varus or valgus correction straps
(T Straps)
T Straps
Control for varus or valgus forces
at the ankle.
Medial strap buckles around the
lateral upright and correct for valgus
Lateral strap buckles around the
medial upright and corrects for varus
TYPES OF MOULDED AFO
 Static AFO
 Dynamic AFO
 Supramalleolar Orthosis
 Tone reducing Orthosis
 Floor reaction Orthosis
 Posterior leaf spring Orthosis
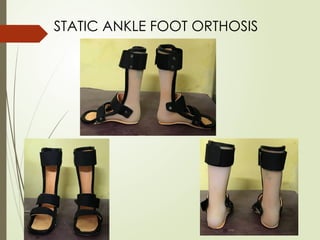
STATIC ANKLE FOOT ORTHOSIS
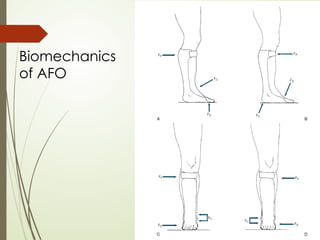
Biomechanics
of AFO
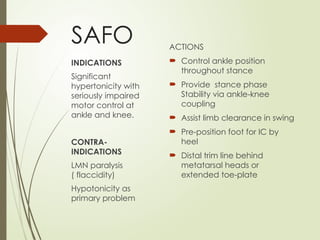
SAFO ACTIONS
 Control ankle position
throughout stance
 Provide stance phase
Stability via ankle-knee
coupling
 Assist limb clearance in swing
 Pre-position foot for IC by
heel
 Distal trim line behind
metatarsal heads or
extended toe-plate
INDICATIONS
Significant
hypertonicity with
seriously impaired
motor control at
ankle and knee.
CONTRA-
INDICATIONS
LMN paralysis
( flaccidity)
Hypotonicity as
primary problem
Dynamic
AFO
DAFO
ACTIONS
 Stabilize sub-talar and tarsal
joints in stance
INDICATIONS
•FLEXIBLE PES PLANUS
•MILD TO MODERATE
SPASTIC DIPLEGIC
•HEMIPLEGIC CP
•HYPOTONIC CP
CONTRAINDICATIONS
•RIGID FOOT
DEFROMITY
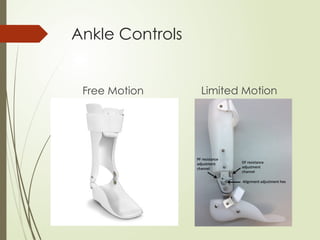
Ankle Controls
 Free motion: provides mediolateral stability that allows
free motion in dosiflexion and plantarflexion
 Solid ankle: allows no movement indicated with sever
pain or instability
 Limited motion: allows motion to be restricted in one or
both directions
Ankle Controls
Free Motion Limited Motion
Limited Motion Ankle Control
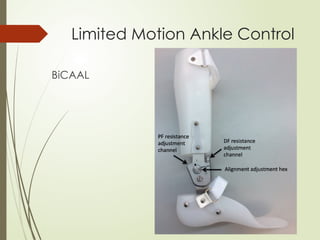
 Bichannel adjustable ankle lock (BiCAAL): an ankle joint with the
anterior and posterior channels that can be fit with pins to reduce
motion or springs to assist motion
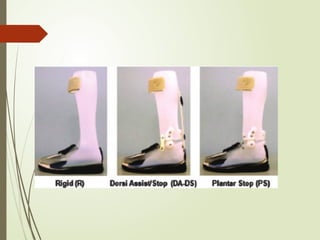
 Anterior Stop (dorsiflexion stop): determines the limits of ankle
dorsiflexion. In an AFO, if the stop is set to allow slight dorsiflexion
(~5degrees), knee flexion results; can be used to control for knee
hyperextension; if the stop is set to allow too much dorsiflexion, knee
buckling could result
 Posterior stop (plantarflexion stop): determines the limits of ankle
plantar flexion. In an AFO if the stop is set to allow slight plantar
flexion (~5degrees), knee extension results; can be used to control
for an unstable knee that buckles; if the stop is set to allow too much
plantar flexion, recurvatum or knee hyperextension could result
Limited Motion Ankle Control
BiCAAL
Dorsiflexion assistance
Spring Assist
Spring Assist
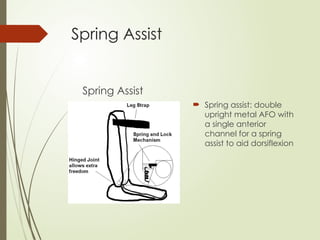
 Spring assist: double
upright metal AFO with
a single anterior
channel for a spring
assist to aid dorsiflexion
Posterior Leaf Spring
 Posterior leaf spring (PLS):
has a flexible narrow
posterior shell; functions
as dorsiflexion assist;
holds foot at 90degree
angle during swing;
displaced during stance;
provides no medial-
lateral stability.
 a plastic AFO that inserts
into the shoe; widely
used to prevent foot
drop.
Specialized AFOs
Floor reaction orthosis
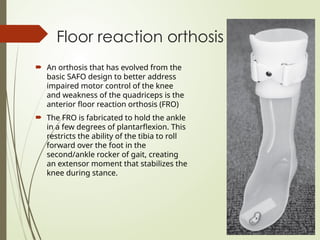
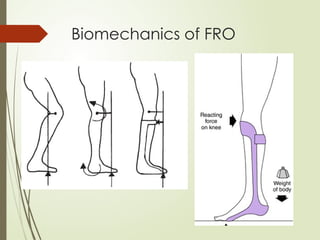
 An orthosis that has evolved from the
basic SAFO design to better address
impaired motor control of the knee
and weakness of the quadriceps is the
anterior floor reaction orthosis (FRO)
 The FRO is fabricated to hold the ankle
in a few degrees of plantarflexion. This
restricts the ability of the tibia to roll
forward over the foot in the
second/ankle rocker of gait, creating
an extensor moment that stabilizes the
knee during stance.
Biomechanics of FRO
 Modified AFO: has a wider posterior shell with trimlines just
posterior to malleoli; foot plate includes more medial-
lateral stability (control of calcaneal and forefoot
inversion and eversion)
 Solid AFO: has widest posterior shell with trimlines
extending forward to malleoli; controls (prevents)
dorsiflexion, plantarflexion, inversion and eversion.
 Spiral AFO: a molded plastic AFO that winds (spirals)
around the calf; provides limited control of motion in all
planes
Patellar-tendon-bearing
AFO
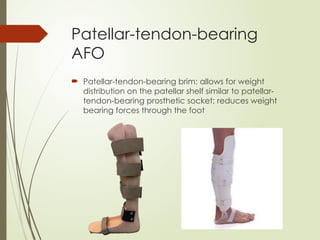
 Patellar-tendon-bearing brim: allows for weight
distribution on the patellar shelf similar to patellar-
tendon-bearing prosthetic socket; reduces weight
bearing forces through the foot
Tone-reducing orthosis
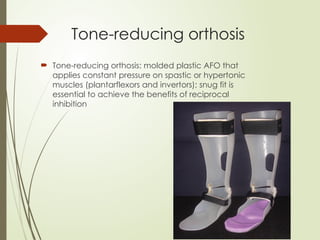
 Tone-reducing orthosis: molded plastic AFO that
applies constant pressure on spastic or hypertonic
muscles (plantarflexors and invertors); snug fit is
essential to achieve the benefits of reciprocal
inhibition
Knee-ankle-foot orthosis
(KAFO)
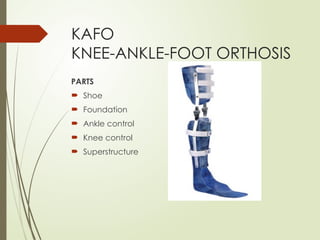
KAFO
KNEE-ANKLE-FOOT ORTHOSIS
PARTS
 Shoe
 Foundation
 Ankle control
 Knee control
 Superstructure
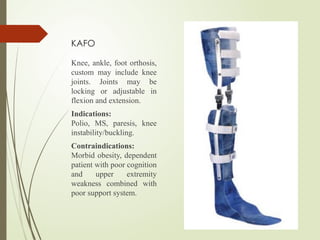
KAFO
Knee, ankle, foot orthosis,
custom may include knee
joints. Joints may be

locking or adjustable in
flexion and extension.
Indications:
Polio, MS, paresis, knee
instability/buckling.
Contraindications:
Morbid obesity, dependent
patient with poor cognition
and upper extremity
weakness combined with
poor support system.
Knee Control
 Hinge joint
 Offset joint
 Provide medial-lateral
and hyperextension
restriction while
permitting knee flexion
 Hinge placed posterior
to midline of leg.
Weight falls anterior to
offset joints, stabilizing
knee in extension
during early stance
phase.
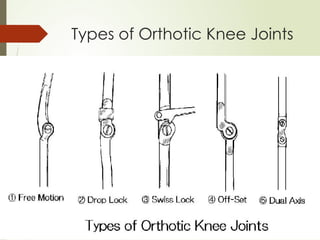
 Drop ring lock
 Pawl lock with bail
release
 When client sands with
full knee extension, the
ring drops, preventing
knee from bending.
 Provides simultaneous
locking of both uprights.
The pawl is a spring-
loaded projection that
fits into a notched disk.
The patient unlocks the
brace by pulling upward
on the posterior bail.
Types of Orthotic Knee Joints
Functions of KAFO
 Knee stability
 Sagittal stability achieved by bands or straps used to
provide a posteriorly directed force.
 Anterior band or strap (knee cap): attaches by four buckles
to metal uprights; may restrict sitting, increases difficulty in
putting on KAFO
 Anterior bands: pretibial or suprapatellar or both
 Frontal plane controls: for control of genu varum or
valgum
 Posterior plastic shell
 Older braces utilize valgum (medial) or varum (lateral)
correction straps which buckle around the opposite metal
upright; less effective as controls than plastic shell
 Thigh bands
 Proximal thigh band
 Quadrilateral or ischeal weight bearing brim: reduces
weight bearing through the limb
 Pattern bottom: a distal attachment added to keep the foot
off the floor provides 100% unweighting of the limb; a life is
required on the opposite leg.
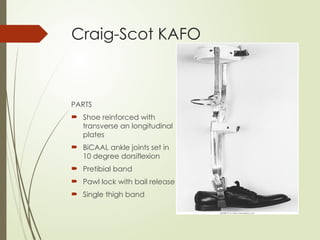
Craig-Scot KAFO
PARTS
 Shoe reinforced with
transverse an longitudinal
plates
 BiCAAL ankle joints set in
10 degree dorsiflexion
 Pretibial band
 Pawl lock with bail release
 Single thigh band
CRAIG SCOTT KAFO
INDICATIONS
 Paraplegics
 Thoracic spinal cord
injury
GAIT PATTERN
 Swing-to or swing-
through with aid of
crutches or a walker
ADVANTAGES
 Medio-lateral foot stability
provided by metatarsal bar
 Enable a patient to stand
with sufficient backward
lean so as to prevent
untoward hip or trunk
flexion.
 Functional
 Easy to don and doff
 Light weight as compared
to standard KAFO
Knee-ankle-foot orthosis
(KAFO)
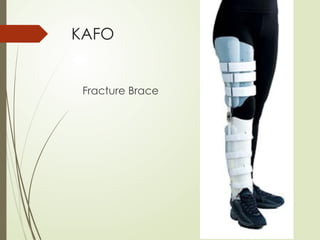
 Fracture braces: a KAFO device with a calf or thigh shell
that encompasses the fracture site and provides support.
 Standing frames
 Allows standing without crutch support may be stationary
or attached to a wheeled mobility base
 Parapodium
 allows for standing without crutch support; also allows for
ease in sitting with the addition of hip and knee joints that
can be unlocked can be used on children with
myelodysplasia
KAFO
Fracture Brace
Parapodium
Standing Frame
Standing frame
 Standing frame orthosis developed at
Gillette Children's Hospital.
 The tubular frame has hip and knee
joints, allowing the child to transfer
into the device and then raise into
standing.
 The fulcrum of the three-force system
used to ensure hip extension is the
broad posterior pelvic pad (at the
center, without Velcro straps), with
counterforces delivered by the
anterior thoracic corset and the
anterior knee pads.

Standing frame
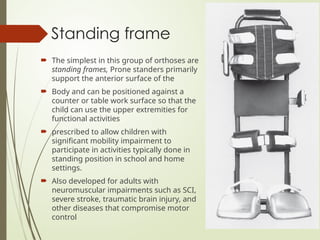
 The simplest in this group of orthoses are
standing frames, Prone standers primarily
support the anterior surface of the
 Body and can be positioned against a
counter or table work surface so that the
child can use the upper extremities for
functional activities
 prescribed to allow children with
significant mobility impairment to
participate in activities typically done in
standing position in school and home
settings.

 Also developed for adults with
neuromuscular impairments such as SCI,
severe stroke, traumatic brain injury, and
other diseases that compromise motor
control
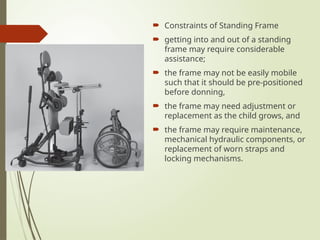
 Constraints of Standing Frame
 getting into and out of a standing
frame may require considerable
assistance;
 the frame may not be easily mobile
such that it should be pre-positioned
before donning,
 the frame may need adjustment or
replacement as the child grows, and
 the frame may require maintenance,
mechanical hydraulic components, or
replacement of worn straps and
locking mechanisms.

Specialized Knee
Orthoses (ko)
Specialized Knee Orthoses
(KO)
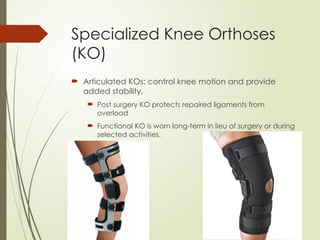
 Articulated KOs: control knee motion and provide
added stability.

 Post surgery KO protects repaired ligaments from
overload
 Functional KO is worn long-term in lieu of surgery or during
selected activities.
Swedish knee cage:
provides mild control
for excessive
hyperextension of the
knee
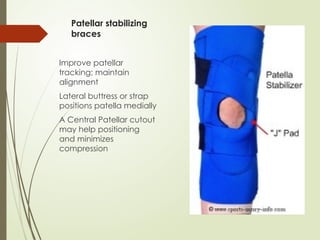
Patellar stabilizing
braces
Improve patellar
tracking; maintain
alignment
Lateral buttress or strap
positions patella medially
A Central Patellar cutout
may help positioning
and minimizes
compression
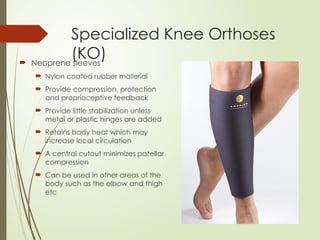
Specialized Knee Orthoses
(KO)
 Neoprene sleeves
 Nylon coated rubber material
 Provide compression, protection
and proprioceptive feedback
 Provide little stabilization unless
metal or plastic hinges are added
 Retains body heat which may
increase local circulation
 A central cutout minimizes patellar
compression
 Can be used in other areas of the
body such as the elbow and thigh
etc
Hip-knee-ankle-foot orthoses
(hkafo)
Contain a hip joint and pelvic band added to a
KAFO
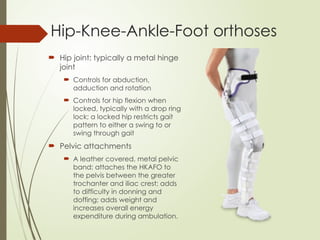
Hip-Knee-Ankle-Foot orthoses
 Hip joint: typically a metal hinge
joint
 Controls for abduction,
adduction and rotation
 Controls for hip flexion when
locked, typically with a drop ring
lock; a locked hip restricts gait
pattern to either a swing to or
swing through gait
 Pelvic attachments
 A leather covered, metal pelvic
band; attaches the HKAFO to
the pelvis between the greater
trochanter and iliac crest; adds
to difficulty in donning and
doffing; adds weight and
increases overall energy
expenditure during ambulation.
Specialized THKAFO
Contains a trunk band added to a HKAFO
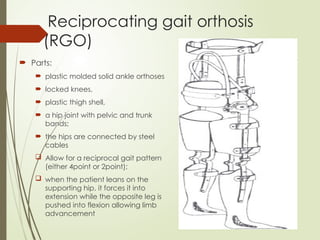
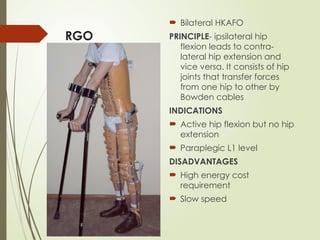
Reciprocating gait orthosis
(RGO)
 Parts:
 plastic molded solid ankle orthoses
 locked knees,
 plastic thigh shell,
 a hip joint with pelvic and trunk
bands;
 the hips are connected by steel
cables
 Allow for a reciprocal gait pattern
(either 4point or 2point);
 when the patient leans on the
supporting hip, it forces it into
extension while the opposite leg is
pushed into flexion allowing limb
advancement
RGO
 Bilateral HKAFO
PRINCIPLE- ipsilateral hip
flexion leads to contra-
lateral hip extension and
vice versa. It consists of hip
joints that transfer forces
from one hip to other by
Bowden cables
INDICATIONS
 Active hip flexion but no hip
extension
 Paraplegic L1 level
DISADVANTAGES
 High energy cost
requirement
 Slow speed
Specialized lower limb
devices
Specialized lower limb
devices
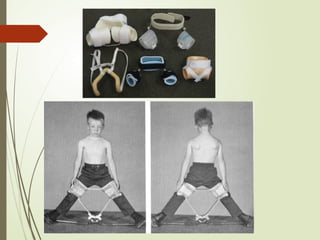
 Denis Browne splint: a bar that connects two shoes
that can swivel; used for correction of club foot or pes
equinovarus in young children
 Frejka pillow: keeps hips abducted used for hip
dysplasia or other conditions with tight adductors in
young children
 Toronto hip abduction orthosis: abducts the hip; used
in treating LCPD
Specialized lower limb
devices
Denis Browne
Splint Frejka Pillow
Selected orthotic gait
deviations
Selected orthotic gait
deviations
 Lateral trunk bending: patient leans toward the
orthotic side during stance. Possible causes: KAFO
medial upright too high; insufficient shoe lift; hip pain,
weak or tight abductors on the orthotic side; short leg;
poor balance
 Circumduction during swing, leg swings out to the side
in an arc. Possible causes: locked knee; excessive
plantar flexion; weak flexors or dorsiflexors. All of these
could also cause vaulting
 Anterior trunk bending: patient leans forward during
stance. Possible causes: inadequate knee lock; weak
quadriceps; hip or knee flexion contracture
Selected orthotic gait
deviations
 Posterior trunk bending: patient leans backward during
stance. Possible causes: inadequate hip lock; weak
gluteus maximus; knee ankylosis
 Hyperextended knee: excessive extension during stance.
Possible causes: inadequate plantar flexion stop;
inadequate knee lock; poor fit of calf band; weak
quadriceps; loose knee ligaments or extensor spasticity;
pes equinus
 Knee instability: excessive knee flexion during stance.
Possible causes: inadequate dorsiflexion stop,
indadequate knee lock, knee and/or hip flexion
contracture; weak quadriceps or insufficient knee lock;
knee pain
Selected orthotic gait
deviations
 Foot Slap: foot hits the ground during early stance. Possible
causes: inadequate dorsiflexor assist; inadequate
plantarflexor stop; weak dorsiflexors
 Toes first: on toes posture during stance. Possible causes:
inadequate dorsiflexor assist; inadequate plantarflexor
stop; inadequate heel lift; heel pain, extensor spasticity;
pes equinus; short leg
 Flat foot: contact with entire foot. Possible causes:
inadequate longitudinal arch support: pes planus
 Pronation: excessive medial foot contact during stance,
valgus position of calcaneus. Possible causes: transverse
plan malalignment; weak invertors; pes valgus; spasticity;
genu valgum
Selected orthotic gait
deviations
 Supination: excessive lateral foot contact during
stance, varus position of the calcaneus. Possible
causes: transverse plan malalignment; weak evertors;
pes varus; genu varum
 Excessive stance width: patient stands or walks with a
wide base of support. Possible causes: KAFO height of
medial upright too high; HKAFO hip joint aligned in
excessive abduction; knee is locked; abduction
contracture; poor balance; sound limb is too short
Thank You for your Attention!