Hepatobiliary changes
Physiological Changes
Impaired gallbladder (GB) motility: Sex hormones →
increased smooth muscle relaxation in the biliary tree
gallbladder volume and decreased contractility.
Impaired motility of the gastrointestinal tract: Pregnancy
induces hypomotility throughout the gastrointestinal tract,
probably via high progesterone levels. Lower esophageal
sphincter pressure also decreases progressively to very low
levels during pregnancy. Impaired small bowel and large
bowel transit occurs in preg-nancy.
Lithogenic changes in the composition of bile: Bile
lithogenicity is increased because of the effects of sex
hormones on the relative concentrations of cholesterol,
phospholipids and bile acids with an increase in choles-terol
synthesis and excretion into bile.
4.
ANATOMIC CHANGES
Anatomic Changes
On liver USG, the biliary tract is usually normal
though GB volume may be increased.
On hepatic Doppler USG, there are some
changes in the hepatic venous flow pattern and
portal flow veloc-ity, due to haemodynamic
changes during pregnancy. The absolute hepatic
blood flow is unchanged even after a 40%
increase in blood volume and cardiac output.
5.
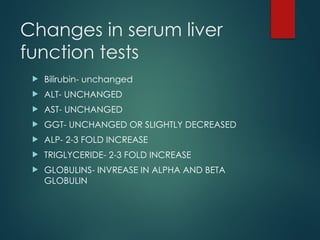
Changes in serumliver
function tests
Bilirubin- unchanged
ALT- UNCHANGED
AST- UNCHANGED
GGT- UNCHANGED OR SLIGHTLY DECREASED
ALP- 2-3 FOLD INCREASE
TRIGLYCERIDE- 2-3 FOLD INCREASE
GLOBULINS- INVREASE IN ALPHA AND BETA
GLOBULIN
6.
CAUSES OF JAUNDICEIN
PREGNANCY
Unrelated to pregnancy
Hepatic causes
Acute viral hepatitis
Drug-induced hepatitis
Chronic viral and autoimmune
hepatitis Wilson's disease
Cirrhosis
Budd-Chiari syndrome
Pre-hepatic causes
Haemolytic anaemia
Post-hepatic causes
Common bile duct stone/stricture
Biliary parasitosis
7.
Pregnancy related
Pregnancy specific
Hyperemesis gravidarum
Intrahepatic cholestasis of pregnancy
Pre-eclampsia/eclampsia
HELLP syndrome
Acute fatty liver of pregnancy
Definition- intrahepatic cholestasisof pregnancy is a
reversible type of hormonally influenced cholestasis
developing in late pregnancy characterized by
generalized itching , and total bile acid >= 19
micromole/l ( RCOG AUGUST 2022)
Incidence - 2/ 10000 in US
1.24% in India
prevalence - 0.3 and 5.6%
In 2nd and 3rd trimester
10.
RISK FACTORS
Advancedmaternal age,
GENETIC ETIOLOGY
History of cholestasis secondary to
oral contraceptives,
Personal or family history of IHCP
Multiple pregnancy
ENVIRONMENTAL factors like
selenium deficiency
11.
PATHOGENESIS
Mutations ofABCB4 gene ( Adenosine
triphosphate binding casette subfamily B
membrane 4)
It encodes for multi drug resistance protein 3
(MDR 3) ,
Which further encodes for canalicular
phospholipid pump transport
MDR3 associated mutations associated with
progressive familial intrahepatic cholestasis
12.
Bile acidsare cleared incompletely
Accumulate in plasma
13.
SYMPTOMS
PRURITUS
It isthe cardinal symptom
Usually persistent and generalized
Palms and soles
Worse at night leading to sleep disturbances
Due to Cholestasis
Bile salts in dermis
14.
It usuallyprecede icterus and
laboratory findings
Usually resolves within 1-2days
postnataly
On examination- scratch marks ,
excoriations
Jaundice develops in 14 to 25%
after 1- 4 weeks of onset of pruritis.
15.
CAUSES OF PRURITUSIN
PREGNANCY
Pregnancy specific
Pruritic urticarial papules and plaques of pregnancy
ICP
Pemphigoid gestationis
Atopic eruption of pregnancy
Pruritus folliculitis of pregnancy
Prurigo of pregnancy
Pregnancy nonspecific
Xerosis
Atopic dermatitis
Allergic contact dermatitis
Scabies or lice
FETAL
Fetal distress,
Preterm labour,
Prematurity,
Meconium stained amniotic fluid
RISK OF SUDDEN FETAL DEMISE-bile
salts acts on AV NODE of fetus
leading to sudden arrythmias
18.
INVESTIGATION
Rasied Sr.totalbilirubin
Sr.ALT and AST are raised in 60% of cases
Direct bilirubin exceeds 6mg /dl
Raised Bile Acids.
COAGULATION PROFILE
GDM AND PRE ECLAMPSIA SCREENING
LIVER USG- to exclude other causes of
cholestasis .gallstones are reported in upto 13% of
women with icp
19.
Management
If patienthas pruritis but lab
tests are normal, to repeat
bile acids and AST AND ALT
after 1 week
2 GOALS: TO REDUCE
SYMPTOMS
PERINATAL MORTALITY AND
MORBIDITY
20.
Non specific treatment
Topical emollients – safe in pregnancy , eg.
Lactocalamine lotion
Antihistamines- like fexofenadine ,
chlorphenamnine
21.
Ursodeoxycholic acid (UDCA)
a)Mechanism of action: Displacement of more hydro-phobic
endogenous bile salts from the bile acid pool. Taurocholic
and taurodeoxycholic acids are signifi-cantly decreased by
UCDA. It thus protects the hepa-tocyte membrane from the
damaging toxicity of bile salts, enhances bile acid clearance
across the placenta from the fetus.
b) Dose: UDCA 500 mg twice daily as the starting dose. It may
be increased by 250-500 mg/week, if there is no improvement
in symptoms or biochemistry, to a dose of 2 g/day in divided
doses.
Side effects: Mild to moderate gastrointestinal disturbance. It is
not teratogenic. It has no effect in reduction in adverse
perinatal outcomes (RCOG August 2022).
Specific treatment
DELIVERY
According to RCOGAugust 2022
guidelines:
Mild ICP (peak bile acids 19-39 µmol/L)
and no other risk factors: Consider options
of planned birth by 40 weeks' gestation with
ongoing antenatal care.
Moderate ICP with peak bile acids 40-99
µmol/L and no other risk factors: Consider
planned birth at 38-39 weeks' gestation.
Severe ICP with peak bile acids 100 µmol/L
or more: Consider planned birth at 35-36
weeks' gestation.
24.
OUTCOME
Usually improvesafter delivery
No residual hepatic defect is left
60-70% recur in subsequent
pregnancy
Long term association:
Gall stones
Hep c
Cholestasis, fibrosis, pancreatitis
25.
Postnatal Follow Up
LFT not to be repeated before 10 days after birth.
All women diagnosed with ICP should have their liver
function and serum bile acid level checked 6 weeks.
postpartum to ensure resolution (RCOG August 2022).
Contraception: Oral contraceptives containing estro-gen
should be used with caution and at the lowest possible
dose.
Recurrence Rate: High recurrence rate of 45-90%. At
booking in subsequent pregnancies, baseline
measurement of liver function tests and bile acid
concentrations should be performed in order to establish
that these are normal. They should only be repeated, if
clinically indicated (RCOG August 2022).
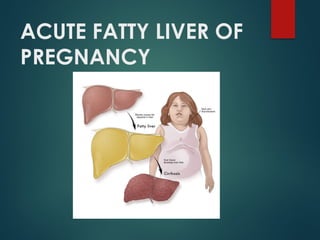
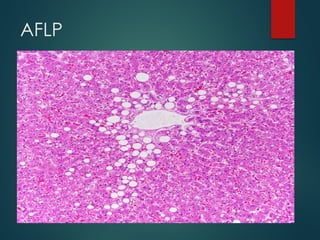
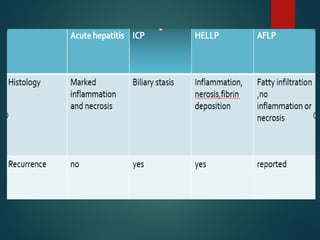
Micro vesicularfatty infiltration
It is rare and life threatening
Leads to hepatic failure and
encephalopathy
Incidence 1 /7000 TO 12000
Occurs at (30-38wks)
Third trimester
28.
RISK FACTOR
LCHADDEF( long chain hydroxy
acyl co enzyme A dehydrogenase)
Nulliparity
Male fetus
Twin pregnancy
Low body mass index
Primigravida
30.
PATHOPHYSIOLOGY
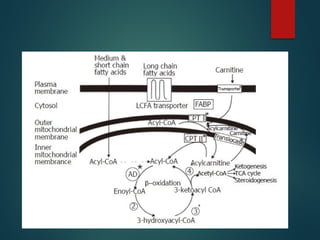
LCHAD, foundon the mitochondrial membrane is involved in the beta
oxidation of long chain fatty acids. LCHAD deficiency is in 20% of the women
suffering from AFLP. It is autosomal recessive in inheritance and mothers are
often found to be heterozygous for the affected mutation.
Heterozygous parents may carry a homozygous fetus for LCHAD deficiency →
accumulation of medium and long chain fatty acids in the fetus →
unmetabolized fatty acids will re-enter the maternal circulation through the
placenta → overwhelms the beta-oxidation enzymes of the heterozygous
mother → hepatic strain → AFLP.
These fatty acids are:
Toxic to pancreas → AFLP associated pancreatitis.
Cause placental dysfunction → hypoxaemic injury to the fetus.
Predisposes patients to the hepatotoxic effects of fatty acids → microvesicular
fatty steatosis of the liver → impairing downstream production of coagulation
factors, fibrinogen, and cholesterol and impairing detoxifying function of the
31.
SYMPTOMS
Most commonpresenation is usally in 3rd
trimester
(30-38th
week)
Non specific
Nausea, vomiting , headache, anorexia
HTN without pre eclampsia
20% have co existing HELLP
Encephalopathy
Hypoglycemia
Features of pancreatitis
Right upper quadrant pain and epigastric pain
Critical caresupport: Fluid status (aggressive fluid re-placement in a setting of low
plasma osmotic pressure can lead to pulmonary edema).
Monitor hypoglycaemia: Monitor glucose every 6-8 hrs, maintain plasma glucose
>65 mg/dL.
Monitor coagulopathy: PT, APTT every 6-8 hrs.
Avoid invasive haemodynamic monitoring as increased risk of coagulation
defects.
Continuous FHR monitoring.
MgSO if <32 weeks gestation for neuroprotection
₄
Prompt delivery of the fetus irrespective of gestational age:
a) IOL if vaginal birth anticipated within 24 hrs and disease not rapidly progressing
in that time frame. Cervical ripening agents may be used.
b) If unlikely that vaginal delivery will occur in 24 hrs, think about CS.
c) Prior to CS, stabilize the patient and correct coagulopathy.
d) Regional anaesthesia may be given, if no coagulopathy.
e) If coagulopathy, prefer GA, but avoid hepatotoxic drugs like halothane.
f) Isoflurane has no hepatotoxicity, and it improves hepatic blood flow
40.
DELIVERY
MODE OFDELIVERY depends on
maternal and fetal condition
Labour induction can be done if
tests for fetal well being are
reassuring
If not LSCS.
41.
Postpartum
management
a) Careful inspectionof genital tract after vaginal birth
b) In most cases, AFLP resolves completely after de-livery and LFT
may return to normal in 7-10 days Patient may show signs of
improvement after 2 days. In some, there is a transient worsening
followed by recovery.
c) Do LFT, creatinine every 6 hrs till a downward trend is observed.
d) Plasmapheresis, following delivery in patients who fail to
improve with delivery and supportive care within 2-8 days.
e) Genetic testing of newborns: Molecular testing for LCHAD as
early diagnosis in a newborn can be life-saving (test for G1528C
mutation). If negative for this mutation, do medium chain, short
chain acyl. CoA dehydrogenase testing. Long-term prognosis
depends on the defect in fatty acid oxidation in the offspring.
42.
OUTCOME
Maternal mortality- 7%
Perinatal mortality - 15% (Sibai study
2007)
Hepatic dysfunction resolves within 1wk
postpartum
If persists after 6wk, consider alternative
pathologies
OC pills can be used
Rarely recur in subsequent pregnancy,
recuurence rate is 25%
It isthe most common cause of
hepatic dysfunction in pregnancy
I-8.8%
II-19.4%
III-18.6%
(Harrison)
45.
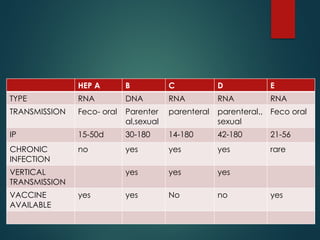
HEP A BC D E
TYPE RNA DNA RNA RNA RNA
TRANSMISSION Feco- oral Parenter
al,sexual
parenteral parenteral.,
sexual
Feco oral
IP 15-50d 30-180 14-180 42-180 21-56
CHRONIC
INFECTION
no yes yes yes rare
VERTICAL
TRANSMISSION
yes yes yes
VACCINE
AVAILABLE
yes yes No no yes
46.
HEPATITIS A
Pregnancydoesn't alter course of
acute HAV infection
It is not teratogenic
Preterm birth, prom, neonatal
Cholestasis
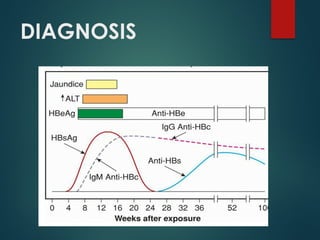
HEPATITIS B
Mostcommon cause of morbidity
and mortality related to Cirrhosis
and hepatocellular carcinoma
risk for development of chronic
HBV infection is strongly linked to
the age of exposure.
90% in infants,
50% in toddlers and young children
5% in adults
50.
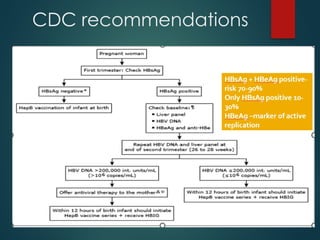
Vertical transmission
MTCTrates also vary significantly
according to the mother’s HBsAg
status (70–90% transmission rate for
HBsAg+ mothers
TRIMESTER
II -10%
III- 90%
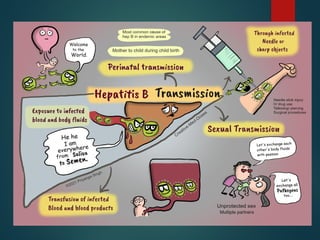
Pathogenesis of motherto child
transmission
Happens in two different mechanisms
Intrauterine- uncommon
Intrapartum or perinatal- it is the most
frequent route (95%)
Infection in 2nd
and 3rd
trimester carries
transmission risk of 10% and 90%
Maternal HBV replicative status determines the
mother’s infectivity.
54.
C-section shouldnot be
performed electively in HBV-
positive mothers to prevent fetal
infection
Women chronically infected with
HBV should be allowed to
breastfeed as recommended for
infant health
Breastfeeding is avoided if there is
cracked or bleeding nipple
55.
Discontinuation oftherapy at any point
during or after pregnancy requires
careful monitoring because of the
potential for HBV flares upon antiviral
therapy withdrawal.
56.
VACCINATION
Neonate –0(within 12hrs), 1, 6
Mother – 0, 4 , 24 wks
causes of immuno prophylaxis failure(8-30%)
(ACG) include high levels of maternal
viraemia, intrauterine infection, or mutations
of the HBV surface protein
HEPATITIS C
HepatitisC has little impact on pregnancy
Unlike HBV, postpartum flares of HCV
have not been described.
This risk is highest in pregnant women co-
infected with HIV
59.
Prevalence in pregnancyis 2.3-17%
Parenteral transmission, mother to
child transmission is most common
route of infection among infants
and children.
Vertical transmission 3-6%
Risk of transmission include HCV
viremia, maternal HIV HCV co
infection(3 times more).
60.
All pregnantwomen with risk factors for
HCV should be screened with anti-HCV
antibody.
Screening should not be performed in
women without risk factors for HCV
acquisition
Invasive procedures (e.g., amniocentesis,
invasive fetal monitoring) should be
minimized in infected mothers and their fetus
to prevent vertical transmission of hepatitis C
61.
C-section shouldnot be performed
electively in HCV-positive mothers to
prevent fetal infection
Women chronically infected with HCV
should be allowed to breastfeed as
indicated for infant health
Hepatitis C therapy (ribavarin and
interferon ) should not be offered to
pregnant women to either treat HCV or
decrease the risk for vertical transmission
62.
Infants –anti HCV IgG is present
due to passive transmission
If detectable after 18mnths or
HCV RNA is positive , it indicates
MTCT
63.
Hepatitis D
DELTAVIRUS, Defective RNA virus
Single stranded circular RNA virus
Must co-infect with HBV
Transmission similar to HBV
Chronic co-infection with HBV and
HDV is more severe
Neonatal transmission is unusual
64.
HEPATITIS E
Causeepidemic
Case fatality rate - 20%
Cause - fulminant hepatitis and
acute hepatic failure
Reason - higher hep E viral load in
pregnant women
increased cytokine secretion
in pregnant women
Complications – abortions , stillbirth
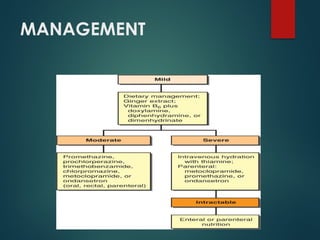
Definition –nausea and vomiting of
pregnancy severe enough to
produce weight loss, dehydration,
ketosis, alkalosis and hypokalemia
69.
Incidence - 0.3-2%(ACG)
Associated with 5% pre gravid
weight loss with dehydration and
ketosis
It is the diagnosis of exclusion
It is most common in 1st
trimester
Usually resolves by 16wks
CLINICAL FEATURES
Symptoms– nausea , vomiting
jaundice, Pruritis
About 15% of patients experience liver
dysfunction
Serum amino transferase levels increased,
but rarely exceed above 200 U/l
Usually mild and resolves with cessation of
vomiting
COMPLICATIONS
FETAL
Low birth weight(LBW) babies,
Small for gestational age babies,
Preterm birth, and
Poor 5-min Apgar scores
If WE supervens , risk of fetal death
is 40%
74.
INVESTIGATIONS
Hyponatremia
Hypokalemia
Hypochloremic metabolic alkolosis
Raised hematocrit
Raised TC
urea/creat ratio is elevated
LFT changes is the marker of severity
Urine – ketonuria
Liver biopsy – bile sludges
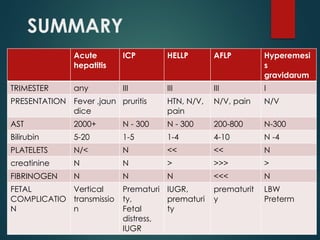
SUMMARY
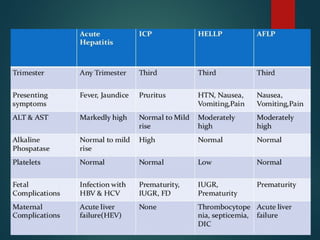
Acute
hepatitis
ICP HELLP AFLPHyperemesi
s
gravidarum
TRIMESTER any III III III I
PRESENTATION Fever ,jaun
dice
pruritis HTN, N/V,
pain
N/V, pain N/V
AST 2000+ N - 300 N - 300 200-800 N-300
Bilirubin 5-20 1-5 1-4 4-10 N -4
PLATELETS N/< N << << N
creatinine N N > >>> >
FIBRINOGEN N N N <<< N
FETAL
COMPLICATIO
N
Vertical
transmissio
n
Prematuri
ty,
Fetal
distress,
IUGR
IUGR,
prematuri
ty
prematurit
y
LBW
Preterm


 Most read