PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
1 | P a g e
drprabhatdevkota@gmail.com
Postgraduate Ophthalmology Exam Notes
© First Edition, 2026
Author
Dr. Prabhat Kiran Devkota, MBBS(TU), MD(NAMS)
MBBS – Chitwan Medical College Teaching Hospital, Institute of
Medicine, Tribhuvan University (TU), Nepal
MD (Ophthalmology) – Lumbini Eye Institute & Research Center,
National Academy of Medical Sciences (NAMS), Nepal
Email: drprabhatdevkota@gmail.com
All rights reserved.
No part of this publication may be reproduced, stored in a retrieval system,
transmitted, or distributed in any form or by any means, whether electronic,
mechanical, photocopying, recording, or otherwise, without prior written permission
of the author, except for brief quotations used for academic, educational, or review
purposes.
Disclaimer
This book is intended solely as an educational and revision resource for postgraduate
ophthalmology trainees and practitioners. While every effort has been made to ensure
the accuracy and reliability of the information presented, the author does not
guarantee that all content is free from errors or omissions. Readers are encouraged to
consult standard textbooks, peer-reviewed literature, institutional guidelines, and
current evidence-based recommendations before making clinical decisions.
The author shall not be held responsible for any consequences arising from the use of
information contained in this book.
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
2 | P a g e
drprabhatdevkota@gmail.com
Preface
This book is a compilation of notes gathered during my preparation for the Final MD
Examination in Ophthalmology. The material has been collected from standard
textbooks, lecture notes, journals, online resources, and personal study notes.
Topics have been organized in a chapter-wise format to facilitate quick revision and
easy reference. Although there are many excellent ophthalmology resources available,
I felt it worthwhile to compile and share these notes with future ophthalmology
trainees and colleagues.
This work represents a continuous learning process rather than a definitive textbook.
Suggestions, corrections, contributions, and constructive feedback are greatly
appreciated and will help improve future editions.
I sincerely hope this book serves as a useful companion in your postgraduate
ophthalmology journey.
Good Luck and Best Wishes!
For comments, suggestions, or contributions, please contact:
Dr. Prabhat Devkota, MD
drprabhatdevkota@gmail.com
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
3 | P a g e
drprabhatdevkota@gmail.com
TABLE OF CONTENT
S.N. TITLE
1 Anatomy & Physiology Of Lens
2 Cataract
3 Acquired Cataract
4 Congenital & Developmental Cataract
5 Traumatic Cataract
6 Glucose Metabolism In The Lens
7 Diabetic Cataract
8 Complicated Cataract
9 Management Of Cataract In Adults
10 Small Incision Cataract Surgery (Sics)
11 Phaco Machine & Phacodynamics
12 Phaco–Surgical Steps
13 Femtosecond Laser–Assisted Cataract Surgery (Flacs)
14 Cataract Surgery In Small Pupil
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
4 | P a g e
drprabhatdevkota@gmail.com
S.N. TITLE
15 Cataract Surgery In Subluxated Lens / Zonular Dialysis
16 Cataract Surgery In Uveitic Eye
17 Anaesthesia In Cataract Surgery
18 Iol Power Calculation
19 Types Of Iol
20 Complications Of Cataract Surgery
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
5 | P a g e
drprabhatdevkota@gmail.com
ANATOMY & PHYSIOLOGY OF LENS
INTRODUCTION
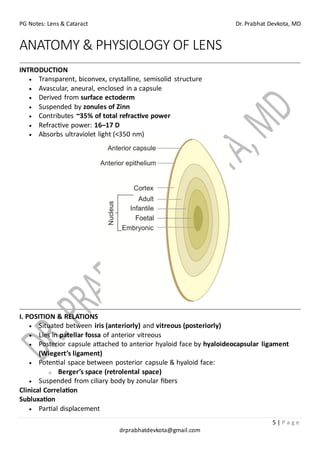
• Transparent, biconvex, crystalline, semisolid structure
• Avascular, aneural, enclosed in a capsule
• Derived from surface ectoderm
• Suspended by zonules of Zinn
• Contributes ~35% of total refractive power
• Refractive power: 16–17 D
• Absorbs ultraviolet light (<350 nm)
I. POSITION & RELATIONS
• Situated between iris (anteriorly) and vitreous (posteriorly)
• Lies in patellar fossa of anterior vitreous
• Posterior capsule attached to anterior hyaloid face by hyaloideocapsular ligament
(Wiegert’s ligament)
• Potential space between posterior capsule & hyaloid face:
o Berger’s space (retrolental space)
• Suspended from ciliary body by zonular fibers
Clinical Correlation
Subluxation
• Partial displacement
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
6 | P a g e
drprabhatdevkota@gmail.com
• Some zonules intact
Dislocation (Luxation)
• Complete displacement
• Into anterior chamber or vitreous cavity
II. DIMENSIONS & GROWTH
Parameter At Birth Adult Old Age
Equatorial diameter 6.5 mm 9–10 mm Slight ↑
Thickness (AP) 3.5 mm 4–4.5 mm ~5 mm
Weight 65 mg 150–200 mg 250–260 mg
• Grows throughout life
• No cell shedding
• Males slightly heavier than females
III. SURFACES, POLES & EQUATOR
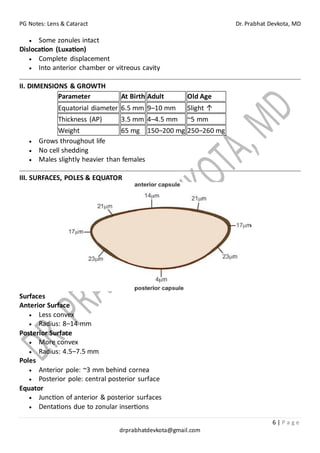
Surfaces
Anterior Surface
• Less convex
• Radius: 8–14 mm
Posterior Surface
• More convex
• Radius: 4.5–7.5 mm
Poles
• Anterior pole: ~3 mm behind cornea
• Posterior pole: central posterior surface
Equator
• Junction of anterior & posterior surfaces
• Dentations due to zonular insertions
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
7 | P a g e
drprabhatdevkota@gmail.com
• Zonular insertion:
o 1.5 mm anterior
o 1.25 mm posterior to equator
IV. OPTICAL PROPERTIES (GRADIENT INDEX LENS)
Region Refractive Index
Peripheral cortex 1.386
Central nucleus 1.41
Anterior capsule 1.36–1.38
Posterior capsule 1.33–1.35
• Gradient RI increases from periphery → center → decreases posteriorly
• Depends on protein concentration
• Reduces spherical aberration
V. AGE-RELATED CHANGES
• Colorless → yellow (after 30 yrs) → amber (old age)
• Progressive nuclear sclerosis
• Increased insoluble proteins
• Progressive loss of accommodation → presbyopia
MICROSCOPIC ANATOMY
Lens is:
• Avascular
• Aneural
• No connective tissue
• Enclosed by capsule
Three Components
1. Lens capsule
2. Lens epithelium
3. Lens fibers
1. LENS CAPSULE
• Thickest basement membrane in the body
• Type IV collagen (also I & III)
• Contains laminin, fibronectin, heparan sulfate
• PAS positive
• Highly elastic (no elastic fibers)
Thickness
• Anterior: 14 µm
• Posterior: 4 µm
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
8 | P a g e
drprabhatdevkota@gmail.com
• Thickest near equator
Functions
• Maintains shape
• Elastic recoil during accommodation
• Selective permeability
• Anchors zonules
Applied Capsule Pathology
• True exfoliation – IR radiation–induced lamellar splitting
• Pseudoexfoliation – fibrillogranular deposits → glaucoma, zonular weakness
• Vossius ring – iris pigment imprint after blunt trauma
2. LENS EPITHELIUM
• Single layer of cuboidal nucleated cells
• Present only anteriorly
• ~500,000 cells in adult
• Most metabolically active part of lens
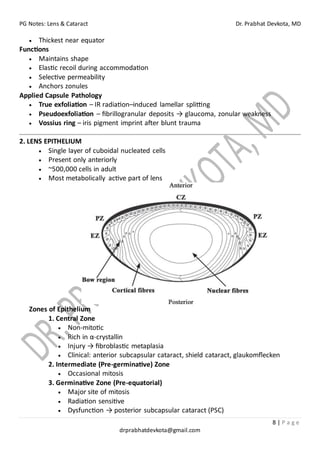
Zones of Epithelium
1. Central Zone
• Non-mitotic
• Rich in α-crystallin
• Injury → fibroblastic metaplasia
• Clinical: anterior subcapsular cataract, shield cataract, glaukomflecken
2. Intermediate (Pre-germinative) Zone
• Occasional mitosis
3. Germinative Zone (Pre-equatorial)
• Major site of mitosis
• Radiation sensitive
• Dysfunction → posterior subcapsular cataract (PSC)
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
9 | P a g e
drprabhatdevkota@gmail.com
Cellular Features
• Cytoskeleton: actin, vimentin, tubulin
• Gap junctions present
• Na⁺/K⁺-ATPase at apicolateral membrane
Applied Epithelium
• Elschnig pearls – proliferating epithelial cells (PCO)
• Soemmering ring – retained lens fibers in capsular bag
3. LENS FIBERS
• Derived from epithelial cells
• Primary fibers → embryonic nucleus
• Secondary fibers → lifelong formation
Structure
• Hexagonal cross-section
• Length: 8–10 mm
• Width: 10–12 µm
• Thickness: 1.5–2 µm
• Gap junctions
• Ball-and-socket & tongue-and-groove interdigitations
Differentiation
• Lose nucleus & organelles
• Form nuclear bow
• Stop elongation at sutures
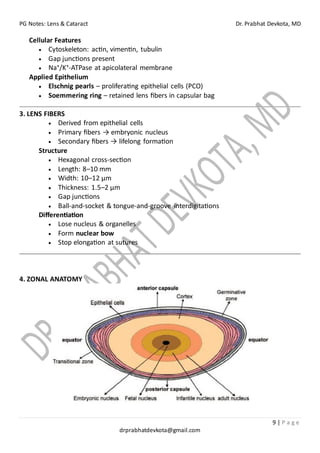
4. ZONAL ANATOMY
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
10 | P a g e
drprabhatdevkota@gmail.com
Zone Time of Formation
Embryonic nucleus 1–3 months IUL
Fetal nucleus 3–8 months
Infantile nucleus Birth–puberty
Adult nucleus Early adulthood
Cortex Lifelong
5. LENS SUTURES
• Fetal nucleus:
o Anterior: upright Y
o Posterior: inverted Y
• Adult: stellate pattern
Sutural cataract – Y-suture opacification, no visual impairment
SURGICAL ANATOMY
1. Hard nucleus
2. Epinucleus
3. Cortex
4. Capsule
Nuclear Hardness (Clinical)
• Grade I – Greenish yellow
• Grade II – Yellow
• Grade III – Amber
• Grade IV – Brown
• Grade V – Black
CILIARY ZONULE (ZONULES OF ZINN)
• Fibrillin microfibrils
• Diameter: 0.35–1 µm
• Glycoprotein composition
• Not elastic
Function
• Distance vision → zonules tense → lens flattens
• Accommodation → ciliary contraction → zonules relax → lens spherical
Clinical Associations
• Marfan syndrome → superotemporal subluxation
• Homocystinuria → inferonasal subluxation
• Pseudoexfoliation → zonular weakness
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
11 | P a g e
drprabhatdevkota@gmail.com
PHYSIOLOGY OF LENS
BIOCHEMICAL COMPOSITION
Component Percentage
Water 66%
Protein 33%
Others 1%
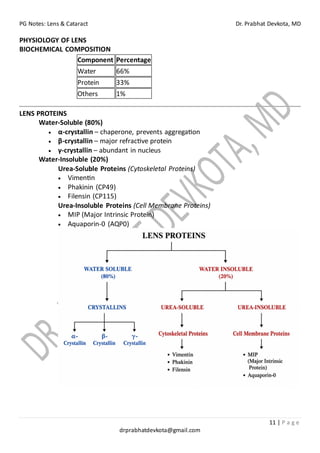
LENS PROTEINS
Water-Soluble (80%)
• α-crystallin – chaperone, prevents aggregation
• β-crystallin – major refractive protein
• γ-crystallin – abundant in nucleus
Water-Insoluble (20%)
Urea-Soluble Proteins (Cytoskeletal Proteins)
• Vimentin
• Phakinin (CP49)
• Filensin (CP115)
Urea-Insoluble Proteins (Cell Membrane Proteins)
• MIP (Major Intrinsic Protein)
• Aquaporin-0 (AQP0)
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
12 | P a g e
drprabhatdevkota@gmail.com
Age Changes
• ↓ α-crystallin
• ↑ insoluble proteins
• Disulfide bonding
• Brunescent cataract
METABOLISM
• Lens survives without oxygen but not without glucose
Glucose Pathways
1. Anaerobic glycolysis (major)
2. HMP shunt
3. Sorbitol (polyol) pathway
Metabolic Cataracts
• Diabetic cataract – snowflake opacities
• Galactosemia – galactitol accumulation
ELECTROLYTES
• High intracellular K⁺
• Low Na⁺
• Ca²⁺ normally low
• ↑ Ca²⁺ → lens opacification
OXIDATIVE PROTECTION
• Glutathione
• Ascorbic acid
• Superoxide dismutase
• Low oxygen tension
Hyperoxia → nuclear cataract
LENS TRANSPARENCY
Anatomical Factors
• Regular fiber arrangement
• Loss of organelles
• Avascularity
• Gradient refractive index
Physiological Factors
• Controlled hydration
• α-crystallin chaperone function
• Active ion pumps
• Antioxidant system
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
13 | P a g e
drprabhatdevkota@gmail.com
ACCOMMODATION
Mechanism
• Ciliary muscle contraction
• Zonular relaxation
• Increased lens curvature
Theories
❖ Helmholtz Theory (Relaxation Theory)
Ciliary muscle contraction → Forward & inward movement of ciliary body →
Zonular relaxation → Lens capsule elasticity acts → Lens becomes more
spherical (more convex) → ↑ Refractive power → Accommodation
❖ Schachar Theory
Ciliary muscle contraction → Increased equatorial zonular tension → Peripheral
lens flattening + Central lens steepening → ↑ Refractive power →
Accommodation
❖ Tscherning Theory
Ciliary muscle contraction → Increased zonular tension → Vitreous pressure on
lens → Central lens bulging → ↑ Refractive power → Accommodation
Amplitude of Accommodation
Age Power
Birth 14–16 D
25 yrs 7–8 D
50 yrs 1–2 D
Presbyopia – age-related loss due to lens sclerosis & reduced elasticity
APPLIED ANATOMY (VIVA FAVORITES)
• Lenticonus
o Anterior (bilateral) – Alport syndrome
o Posterior – usually unilateral
• Lentiglobus – spherical protrusion
• Microspherophakia – small spherical lens
• Lens coloboma – inferonasal, zonular absence
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
14 | P a g e
drprabhatdevkota@gmail.com
CATARACT
Cataract refers to any opacity in the lens or its capsule, sufficient in severity to impair vision
clinically.
Classification
I. Etiological Classification
A. Congenital and Developmental Cataract
• Congenital cataract — present at birth
• Developmental cataract — develops during infancy to adolescence
B. Acquired Cataract
1. Senile cataract
2. Traumatic cataract
3. Complicated cataract
4. Metabolic cataract
5. Electric cataract
6. Radiational cataract
7. Toxic cataract
o Corticosteroid-induced cataract
o Miotic-induced cataract
o Copper-induced cataract
o Iron-induced cataract
8. Dermatogenic cataract — associated with skin diseases
9. Cataract associated with osseous diseases
10.Cataract associated with miscellaneous syndromes
o Dystrophia myotonica (myotonic dystrophy)
o Down syndrome
o Lowe syndrome
II. Morphological Classification
1. Capsular Cataract
a. Anterior capsular cataract
b. Posterior capsular cataract
2. Subcapsular Cataract
a. Anterior subcapsular cataract
b. Posterior subcapsular cataract
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
15 | P a g e
drprabhatdevkota@gmail.com
3. Cortical Cataract
4. Supranuclear Cataract
5. Nuclear Cataract
6. Polar Cataract
a. Anterior polar cataract
b. Posterior polar cataract
CONGENITAL CATARACT
Congenital Cataract: Congenital cataract is a cataract in which the child is born with
lens opacity.
Developmental Cataract: Developmental cataract is a cataract that develops from
infancy to adolescence, involving the developing lens.
Causes
Approximately:
• 1/3 are idiopathic — cause unknown
• 1/3 are hereditary, with or without systemic disorders
• 1/3 are acquired
Maternal Causes
• Malnutrition
• Infections — especially TORCH
• Drugs
• Radiation
Fetal Causes
• Birth anoxia
• Trauma
• Metabolic defects
• Malnutrition
• Congenital disorders
Types of Congenital Cataract
A. Congenital Capsular Cataract
• Anterior capsular cataract
• Posterior capsular cataract
B. Polar Cataract
• Anterior polar cataract
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
16 | P a g e
drprabhatdevkota@gmail.com
• Posterior polar cataract
C. Congenital Nuclear Cataract
• Cataracta centralis pulverulenta
• Total nuclear cataract
D. Lamellar / Zonular Cataract
• Opacity involves a specific lamella or zone of the developing lens.
E. Sutural and Axial Cataracts
Types
• Floriform cataract — flower-like appearance
• Coralliform cataract — coral-like appearance
• Spear-shaped cataract
• Anterior axial embryonic cataract
• Dendritic sutural cataract
F. Generalized Cataract
1. Coronary Cataract
• Corona of club-shaped opacities
• Opacities show a radial distribution in the peripheral lens
• Usually located in the peripheral cortex
2. Blue-Dot Cataract
• Most common congenital/developmental cataract
• Multiple round blue-dot opacities
• Usually located in the peripheral lens
• Also known as cerulean cataract
3. Total Congenital Cataract
• Almost the entire lens is opaque
• Classically associated with congenital rubella
• Also called rubella cataract
4. Congenital Membranous Cataract
• Lens substance becomes absorbed
• Leaves behind an opaque membranous remnant
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
17 | P a g e
drprabhatdevkota@gmail.com
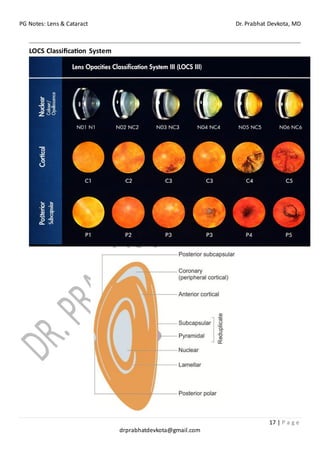
LOCS Classification System
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
18 | P a g e
drprabhatdevkota@gmail.com
ACQUIRED CATARACT
Acquired cataract refers to opacification of the lens occurring after normal lens fibres have
already formed, due to degeneration of previously transparent fibres, in contrast to
congenital/developmental cataract where abnormal fibres are formed from the outset.
CLASSIFICATION OF ACQUIRED CATARACT
A. Common Types
1. Age-related (Senile) cataract
2. Traumatic cataract
3. Metabolic cataract
4. Complicated cataract
5. Drug-induced cataract
o Corticosteroids (posterior subcapsular)
o Miotics
6. Radiational cataract
7. Electric cataract
8. Syndermatotic cataract (associated with skin diseases)
9. Cataract associated with osseous diseases
10.Cataract with miscellaneous syndromes
• Myotonic dystrophy
• Down’s syndrome
• Lowe’s syndrome
• Treacher–Collins syndrome
AGE-RELATED (SENILE) CATARACT
EPIDEMIOLOGY
• Most common acquired cataract
• Usually >50 years
• Bilateral, but asymmetrical
• Affects both sexes, slightly more common in females
MORPHOLOGICAL TYPES
1. Cortical cataract (Soft cataract)
o Cuneiform (70%)
o Cupuliform (5%)
2. Nuclear cataract (Hard cataract) – 25%
Mixed nuclear + cortical cataract is common
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
19 | P a g e
drprabhatdevkota@gmail.com
ETIOPATHOGENESIS OF SENILE CATARACT
A. RISK FACTORS
1. Age
• Strongest risk factor
• 90% develop cataract by 70 years
• Presenile cataract: onset <45–50 years
2. Sex
• Higher prevalence in females
• Possible reasons:
o Longer lifespan
o Post-menopausal hormonal changes
o Protective role of HRT against cortical cataract
o Higher association with diabetes, obesity, hypertension
3. Heredity
• Accounts for:
o 50% risk of cortical cataract
o 35–50% risk of nuclear cataract
• Likely single-locus genetic variation
• Influences age of onset, progression, type
4. Ultraviolet (UV-B) Radiation
• Strongly linked to cortical cataract
• UV-B range: 290–320 nm
• Mechanism:
o Photo-oxidative damage
o UV absorbed by tryptophan → kynurenine derivatives
o Generation of singlet oxygen
o Damage to:
▪ Na⁺/K⁺-ATPase
▪ Hexokinase
▪ Lens membranes
• Oxygen enhances damage
• Antioxidants (Vit E, Vit C, GSH) are protective
5. Dietary Deficiency
• Proteins
• Amino acids
• Vitamins: riboflavin, vitamin C, vitamin E
• Trace elements
6. Dehydrational Crisis
• Severe diarrhoea, cholera
• Alters lens hydration and electrolytes
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
20 | P a g e
drprabhatdevkota@gmail.com
7. Smoking
• Strong association with nuclear cataract
• Mechanisms:
o Accumulation of chromophores (3-hydroxykynurenine)
o Carbamylation by cyanates
o Protein denaturation
• Most important avoidable risk factor
PRESENILE CATARACT – CAUSES
1. Heredity
2. Diabetes mellitus
o Earlier onset
o Rapid progression
o Nuclear cataract common
3. Myotonic dystrophy
o Posterior subcapsular cataract
4. Atopic dermatitis
o Atopic cataract (~10%)
CLINICAL FEATURES OF CATARACT
A. SYMPTOMS
Cataract may remain asymptomatic initially and be detected on routine examination.
1. Glare (Dazzle)
• Earliest and commonest symptom
• Intolerance to:
o Bright sunlight
o Headlights of oncoming vehicles
• More marked in:
o Posterior subcapsular cataract (PSC)
o Anterior cortical cataract
Due to light scattering by lens opacity
2. Uniocular Diplopia / Polyopia
• Doubling or trebling of images
• Early symptom
• Caused by:
o Irregular refraction
o Variable refractive index of cataractous lens
3. Coloured Halos
• Perception of coloured rings around lights
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
21 | P a g e
drprabhatdevkota@gmail.com
• Due to:
o Dispersion of white light
o Presence of water droplets in lens
4. Black Spots
• Stationary dark spots perceived in front of eyes
• Due to localized lens opacities
5. Blurring and Distortion of Vision
• Misty vision
• Image distortion
• Occurs in early stages
6. Loss of Vision
Painless, gradual and progressive
Pattern of visual loss depends on location of opacity:
• Central opacities (PSC / cupuliform cataract)
o Early visual loss
o Worse in bright light
o Better in dim light (pupil dilates)
o → Day blindness
• Peripheral opacities (cuneiform cortical cataract)
o Delayed visual loss
o Vision better in bright light (pupil constricts)
• Nuclear sclerotic cataract
o Progressive deterioration of distance vision
o Myopic shift (index myopia)
o Improved near vision → “Second sight”
o May cause anisometropia if asymmetric
• Advanced cataract
o Vision reduces to:
▪ Perception of light (PL+)
▪ Accurate projection of rays
B. SIGNS
1. Visual Acuity
• Depends on:
o Type
o Location
o Maturity
• Ranges from 6/9 to PL+
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
22 | P a g e
drprabhatdevkota@gmail.com
2. Contrast Sensitivity
• Often reduced before Snellen acuity falls
• Non-specific but sensitive indicator
• Tested by:
o Arden grating
o Cambridge low-contrast grating
o Pelli–Robson chart
o Functional Acuity Contrast Test (FACT)
o Visittrak chart
Reduced contrast sensitivity is an early functional loss in cataract
3. Oblique Illumination Examination
• Reveals:
o Colour of lens in pupillary area
• Helps differentiate types of cataract
4. Iris Shadow Test
• Oblique light produces a crescentic shadow of iris margin on lens opacity
• Present when:
o Clear cortex exists between opacity and iris
• Sign of immature cataract
• Absent in:
o Clear lens
o Mature cataract
Presence of iris shadow = immature cataract
5. Distant Direct Ophthalmoscopy
• Clear lens → uniform red fundal glow
• Partial cataract → black shadows against red glow
• Complete cataract → absent red glow, white pupillary reflex
6. Slit-Lamp Examination (with Dilated Pupil)
Reveals:
• Site of opacity
• Size and shape
• Colour and pattern
• Hardness of nucleus
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
23 | P a g e
drprabhatdevkota@gmail.com
GRADING OF NUCLEAR HARDNESS (Slit-Lamp Based)
Grade Hardness Colour
Grade I Soft Greyish white
Grade II Soft–medium Yellowish
Grade III Medium-hard Amber
Grade IV Hard Brownish
Grade V Ultrahard Blackish
Essential for phacoemulsification planning
EXAM & VIVA PEARLS
• Glare is the earliest symptom of cataract
• PSC causes early visual loss and day blindness
• Second sight = nuclear cataract
• Iris shadow present only in immature cataract
• Contrast sensitivity reduces before Snellen acuity
• Nuclear colour predicts hardness and surgical difficulty
ETIOPATHOGENESIS OF CATARACT
Loss of lens transparency occurs due to:
• Abnormalities of lens proteins
• Disorganization of lens fibres
• Disturbance of water–electrolyte balance
• Derangement of the lens colloid system
Any physical, chemical, metabolic, or oxidative insult that disrupts:
• Intracellular–extracellular equilibrium
• Osmotic balance
• Antioxidant defense
→ leads to lens opacification (cataract)
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
24 | P a g e
drprabhatdevkota@gmail.com
CORE MECHANISMS OF CATARACT FORMATION
1. Degeneration of Lens Fibres
• Affects already formed fibres
• Leads to:
o Protein aggregation
o Increased light scattering
• Commonly seen in senile cataract
2. Formation of Aberrant Lens Fibres
• Due to dysfunction of lens germinal epithelium
• Produces structurally abnormal fibres
• Seen in:
o Posterior subcapsular cataract
o Complicated cataract
3. Fibrous Metaplasia of Lens Fibres
• Metaplastic transformation of fibres
• Occurs in:
o Complicated cataract
o Chronic uveitis
4. Lens Epithelial Cell Necrosis
• Produces focal epithelial opacities
• Example:
o Glaucomflecken
• Seen in:
o Acute angle-closure glaucoma
5. Deposition of Abnormal Material
Seen in:
• Metabolic diseases
o Wilson disease (copper)
o Fabry disease
• Toxic reactions
o Siderosis (iron)
o Chalcosis (copper)
• Drug-induced cataracts
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
25 | P a g e
drprabhatdevkota@gmail.com
BIOCHEMICAL BASIS & MECHANISMS OF CATARACTOGENESIS
I. HYDRATION & ELECTROLYTE IMBALANCE
(Early, potentially reversible – mainly cortical cataract)
Mechanism
• Failure of Na⁺/K⁺ ATPase pump
• ↑ Sodium & calcium
• ↓ Potassium
• Resultant osmotic imbalance → water influx
• Leads to:
o Subcapsular fluid droplets
o Lacunae between lens fibres
o Swelling and rupture of lens fibres (intumescence)
Biochemical Basis
• Altered semipermeability of lens capsule
• Polyol (sorbitol) accumulation → osmotic stress
• Increased intracellular calcium activates proteases
Examples
• Juvenile diabetic cataract
• Traumatic cataract (capsular breach)
• Dehydration-related cataract
Early stage may be reversible
Clinically produces SOFT CATARACT
Predominantly affects cortex
II. DENATURATION & AGGREGATION OF LENS PROTEINS
(Irreversible – final common pathway)
Normal Lens Protein State
• High concentration of soluble crystallins (α, β, γ)
• α-crystallin acts as a molecular chaperone
Pathological Changes
• ↓ Total soluble proteins
• ↑ Insoluble proteins
• Loss of α-crystallin function
• Selective loss of γ-crystallin
Mechanisms
• Oxidative stress
• Non-enzymatic glycation (diabetes)
• Disulphide cross-linking
• Proteolysis
• Racemization
• Carbamylation (renal failure, smoking)
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
26 | P a g e
drprabhatdevkota@gmail.com
• Toxic substances
Structural Outcome
• Protein unfolding, aggregation & cross-linking
• Dense, permanent opacification
• Increased light scattering
Occurs mainly in:
• Young lens
• Metabolically active cortical fibres
Irreversible change
Represents the final common pathway of cataractogenesis
III. NUCLEAR SCLEROSIS & PIGMENT FORMATION
(Age-related change – nuclear cataract)
Mechanism
• Gradual dehydration of lens nucleus
• Protein compaction
• Progressive increase in insoluble proteins
Pigment Accumulation
• Urochrome
• Melanin-like pigments
Site
• Older, metabolically inactive nuclear fibres
Clinical Effect
• Increased refractive index
• Brownish or black discoloration of nucleus
Produces HARD (NUCLEAR) CATARACT
Common in senile cataract
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
27 | P a g e
drprabhatdevkota@gmail.com
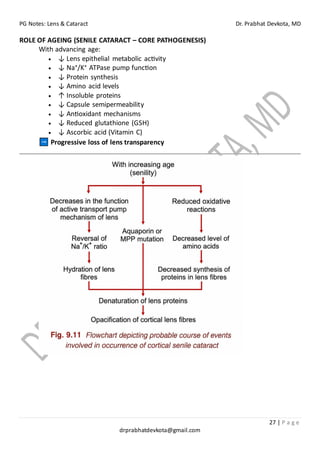
ROLE OF AGEING (SENILE CATARACT – CORE PATHOGENESIS)
With advancing age:
• ↓ Lens epithelial metabolic activity
• ↓ Na⁺/K⁺ ATPase pump function
• ↓ Protein synthesis
• ↓ Amino acid levels
• ↑ Insoluble proteins
• ↓ Capsule semipermeability
• ↓ Antioxidant mechanisms
• ↓ Reduced glutathione (GSH)
• ↓ Ascorbic acid (Vitamin C)
Progressive loss of lens transparency
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
28 | P a g e
drprabhatdevkota@gmail.com
OXIDATIVE STRESS THEORY (MOST IMPORTANT EXAM THEORY)
Normal Antioxidant Protection
• Reduced glutathione (GSH)
• Ascorbic acid (Vitamin C)
• Vitamin E
• Enzymes:
o Glutathione reductase
o Glutathione peroxidase
Reactive Oxygen Species
• Superoxide radicals
• Hydrogen peroxide
• Hydroxyl radicals
Effects of Oxidative Stress
• Oxidation of –SH groups of proteins
• Enzyme inactivation
• Lipid peroxidation of membranes
• Protein aggregation
Why GSH Falls with Age
• Reduced synthesis
• Increased membrane permeability
• Reduced glutathione reductase activity
• Increased protein disulphide bonding
Strong experimental & clinical evidence supports oxidative theory
HARDING’S FINAL COMMON PATHWAY OF CATARACTOGENESIS
Multiple insults converge causing:
Protein Changes
• Glycation
• Methionine oxidation
• Protein unfolding
• Disulphide cross-linking
• Racemization
Structural Changes
• Crystallin aggregation
• Membrane damage
• Enzyme dysfunction
Ionic Changes
• Sodium & calcium accumulation
• Osmotic shock
Lens opacification → Cataract
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
29 | P a g e
drprabhatdevkota@gmail.com
MECHANISM OF LOSS OF LENS TRANSPARENCY
A. CORTICAL SENILE CATARACT
(Hydration + Electrolyte + Protein changes)
1. Water Content
• Normal lens: ~65%
• Immature cataract: 68–70%
• Hypermature (Morgagnian): 78–80%
• Due to:
o Failure of Na⁺/K⁺ pump
o Increased Na⁺ influx
o Osmotic hydration
o Release of bound water from altered proteins (syneresis)
2. Protein Changes
• Total protein ↓ (normal ~34%)
• ↑ Water-insoluble proteins
• Major changes:
o Loss of α-crystallin
o Selective loss of γ-crystallin
• Mechanisms proposed:
o Leakage of proteins
o Insolubilization
o Decreased synthesis
o Increased catabolism
3. Free Amino Acids
• Progressive decrease
• Proteogenic amino acids ↓ more than non-proteogenic
• Due to membrane damage and leakage
4. Electrolyte Changes
• Na⁺ ↑
• K⁺ ↓
5. Calcium
• Markedly increased
• Salit classification:
o Incipient: <10 mg%
o Immature: 10–35 mg%
o Mature: >35 mg%
• Secondary phenomenon, not primary insult
FINAL PATHWAY
Na⁺/K⁺ pump failure → hydration → protein denaturation → cortical fibre
opacification
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
30 | P a g e
drprabhatdevkota@gmail.com
B. NUCLEAR CATARACT
(Protein compaction + Pigmentation)
• Increased nuclear sclerosis
• Dehydration and compaction of nucleus
• ↑ Water-insoluble proteins
• Normal Na⁺ and K⁺ levels
• Pigment deposition:
o Urochrome
o Melanin-like compounds
• Lens opacity due to:
o Light scattering by protein aggregates
o Light absorption by brown-coloured proteins
ROLE OF GLUTATHIONE & ASCORBIC ACID
NORMAL DEFENCE
Lens is protected from oxidative stress by:
• Glutathione (GSH)
• Ascorbic acid
• Enzymes:
o Glutathione reductase
o Glutathione peroxidase
OXIDATIVE STRESS
Reactive oxygen species:
• Superoxide (O₂⁻)
• Hydrogen peroxide (H₂O₂)
• Hydroxyl radicals
MECHANISM
• Ascorbate converts O₂⁻ → H₂O₂
• GSH detoxifies H₂O₂
• Depletion leads to:
o Oxidation of protein –SH groups
o Enzyme inactivation
o Protein aggregation
o Membrane damage
CAUSES OF ↓ GLUTATHIONE
• Decreased synthesis
• Increased membrane permeability
• Reduced glutathione reductase activity
• Increased protein–disulphide bonding
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
31 | P a g e
drprabhatdevkota@gmail.com
STAGES OF MATURATION OF SENILE CATARACT
Senile cataract matures gradually, and its stages differ in cortical and nuclear types.
A. MATURATION OF CORTICAL SENILE CATARACT
Cortical cataract progresses through five classical stages.
1. STAGE OF LAMELLAR SEPARATION
(Earliest, pre-clinical stage)
• Earliest senile change
• Cortical lens fibres become separated by fluid
• Due to early hydration of cortex
• Seen only on slit-lamp examination
• No visible opacity to naked eye
• Reversible stage
Exam point:
Lamellar separation represents reversible cortical hydration and precedes visible
cataract.
2. STAGE OF INCIPIENT CATARACT
(Early detectable opacities)
• Discrete opacities with clear areas between them
• Visual acuity may still be relatively preserved
• Two distinct patterns recognized:
a. Cuneiform Senile Cortical Cataract
Morphology
• Wedge-shaped opacities
• Start at lens equator
• Extend towards centre
• First appear in lower nasal quadrant
• Present in both anterior and posterior cortex
Clinical appearance
• On oblique illumination: → Radial spoke-like greyish-white opacities
• On distant direct ophthalmoscopy: → Dark lines against red fundal glow
• Seen clearly after pupillary dilatation
Visual symptoms
• Peripheral onset → late visual impairment
Most common type of cortical cataract
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
32 | P a g e
drprabhatdevkota@gmail.com
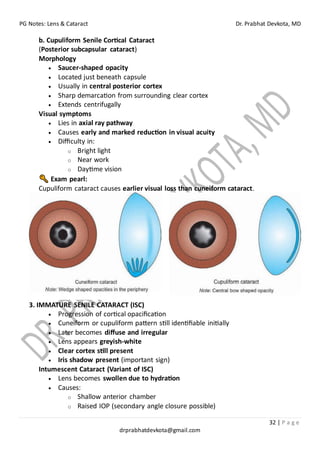
b. Cupuliform Senile Cortical Cataract
(Posterior subcapsular cataract)
Morphology
• Saucer-shaped opacity
• Located just beneath capsule
• Usually in central posterior cortex
• Sharp demarcation from surrounding clear cortex
• Extends centrifugally
Visual symptoms
• Lies in axial ray pathway
• Causes early and marked reduction in visual acuity
• Difficulty in:
o Bright light
o Near work
o Daytime vision
Exam pearl:
Cupuliform cataract causes earlier visual loss than cuneiform cataract.
3. IMMATURE SENILE CATARACT (ISC)
• Progression of cortical opacification
• Cuneiform or cupuliform pattern still identifiable initially
• Later becomes diffuse and irregular
• Lens appears greyish-white
• Clear cortex still present
• Iris shadow present (important sign)
Intumescent Cataract (Variant of ISC)
• Lens becomes swollen due to hydration
• Causes:
o Shallow anterior chamber
o Raised IOP (secondary angle closure possible)
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
33 | P a g e
drprabhatdevkota@gmail.com
Key distinguishing feature:
ISC = Iris shadow present
4. MATURE SENILE CATARACT (MSC)
• Complete opacification of cortex
• No clear cortex remains
• Lens appears uniformly pearly white
• Also called “ripe cataract”
• Iris shadow absent
Exam pearl:
MSC is the ideal stage for cataract surgery in classical teaching.
5. HYPERMATURE SENILE CATARACT (HMSC)
Occurs when a mature cataract is left untreated.
a. Morgagnian Hypermature Cataract
• Liquefaction of entire cortex
• Lens becomes a bag of milky fluid
• Small brown nucleus sinks inferiorly
• Nucleus shifts with head movement
• Calcium deposits may be seen on capsule
Classical description:
“Floating nucleus in milky cortex”
b. Sclerotic Type Hypermature Cataract
• Cortex disintegrates and water leaks out
• Lens becomes shrunken
• Anterior capsule:
o Thickened
o Wrinkled
o Proliferation of anterior epithelial cells
• Dense white capsular cataract in pupillary area
• Deep anterior chamber
• Iridodonesis present
Key signs
• Shrunken lens
• Tremulous iris
• Deep AC
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
34 | P a g e
drprabhatdevkota@gmail.com
B. MATURATION OF NUCLEAR SENILE CATARACT
Nuclear cataract shows progressive sclerosis, not hydration.
PATHOGENESIS
• Age-related nuclear sclerosis
• Dehydration and compaction of nucleus
• Increase in water-insoluble proteins
• Loss of elasticity → reduced accommodation
• Gradual obstruction to light transmission
CLINICAL PROGRESSION
• Begins centrally
• Slowly spreads peripherally
• May approach capsule
• Usually thin rim of clear cortex remains
COLOUR CHANGES (PIGMENTATION)
Due to deposition of pigments derived from amino acids:
• Yellow → early nuclear sclerosis
• Amber
• Brown – Cataracta brunescens
• Black – Cataracta nigra
• Rarely reddish – Cataracta rubra
Exam pearl:
Nuclear cataract may cause second sight due to increased refractive index (myopic
shift).
COMPARISON: CORTICAL vs NUCLEAR CATARACT (VIVA-READY)
Feature Cortical Nuclear
Main mechanism Hydration Sclerosis & compaction
Water content Increased Decreased
Na⁺/K⁺ imbalance Present Absent
Iris shadow Present till ISC Usually absent
Colour Grey-white Yellow → brown → black
Visual loss Late (cuneiform) Gradual
Refractive change Minimal Myopic shift
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
35 | P a g e
drprabhatdevkota@gmail.com
CONGENITAL & DEVELOPMENTAL CATARACT
Congenital and developmental cataracts result from disturbance in normal lens
development.
• Congenital cataract:
Present at birth → opacity involves embryonic or fetal nucleus.
• Developmental cataract:
Develops from infancy to adolescence → may involve infantile/adult nucleus, cortex,
or capsule.
Key concept:
The cataract affects the lens zone forming at the time of insult; fibers formed before
and after remain clear.
ETIOLOGY
I. Idiopathic (≈ 50%)
• Sporadic, unknown cause
• Often due to new mutations
• Familial pattern may appear in later generations
II. Hereditary (≈ ⅓ cases)
A. Without systemic association
• Mostly autosomal dominant
• Rarely AR or X-linked
Common familial cataracts:
• Cataracta pulverulenta
• Zonular (lamellar) cataract
• Coronary cataract
• Total soft cataract
B. With systemic disorders
• Chromosomal: Trisomy 21, 13–15, 16–18, Turner, Cri-du-chat
• Skeletal: Conradi-Hünermann, Stickler
• CNS: Marinesco-Sjögren, Norrie disease
• Renal: Lowe syndrome
• Dermatological: Ichthyosis, incontinentia pigmenti
• Muscular: Myotonic dystrophy
• Digital: Rubinstein-Taybi, Ellis-van-Creveld
III. Maternal Factors
• Malnutrition → non-familial zonular cataract
• Infections:
o Rubella (≈ 50%)
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
36 | P a g e
drprabhatdevkota@gmail.com
o Toxoplasmosis, CMV
• Drugs: Thalidomide, corticosteroids
• Radiation exposure
IV. Fetal / Infantile Factors
• Placental anoxia
• Birth trauma
• Metabolic: Galactosaemia, galactokinase deficiency, neonatal hypoglycaemia
• Associated ocular anomalies:
PHPV (PFV), aniridia, ROP, lenticonus posterior, microphthalmos, congenital
glaucoma, lens subluxation
• Early childhood malnutrition
MORPHOLOGICAL CLASSIFICATION
(Most Important for Exams)
A. Congenital Capsular Cataracts
1. Anterior capsular:
Non-axial, stationary, visually insignificant
2. Posterior capsular:
Rare; associated with persistent hyaloid artery
B. Congenital Polar Cataracts
1. Anterior Polar Cataract
• Central anterior capsule + superficial cortex
• Causes:
o Delayed AC development → bilateral, stationary
o Corneal perforation (ophthalmia neonatorum)
Morphological types:
• Anterior pyramidal cataract: Cone-shaped plaque
• Reduplicated cataract: Capsule opacity + buried imprint
2. Posterior Polar Cataract
• Small, circular opacity at posterior pole
Associations:
• Mittendorf dot
• Posterior lenticonus/lentiglobus
• PHPV
Types:
• Stationary
• Progressive (onion-whorl appearance)
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
37 | P a g e
drprabhatdevkota@gmail.com
C. Congenital Nuclear Cataracts
I. Embryonic Nucleus
Cataracta centralis pulverulenta
• Autosomal dominant
• Central powdery opacity
• Usually no visual impairment
II. Fetal Nucleus
1. Lamellar (Zonular) Cataract
• Most common visually significant congenital cataract (≈40%)
• Discrete opacity zone around embryonic nucleus
Etiology:
• Genetic (AD)
• Environmental: Vit D deficiency, hypocalcaemia, maternal rubella (7–8
weeks)
Features:
• Clear lens inside & outside opacity
• Peripheral spoke-like riders
• Usually, bilateral → severe visual loss
2. Sutural & Axial Cataracts
• Opacities around Y-sutures
• Usually bilateral, stationary, minimal visual effect
Types:
• Floriform
• Coralliform (fusiform spindle-shaped)
• Spear-shaped
• Dendritic suture cataract
• Anterior axial embryonic cataract
III. Whole Nuclear Cataract
1. Total Congenital Cataract
• Dense chalky white opacity
• Usually bilateral
• Causes: Hereditary, maternal rubella
Rubella cataract:
• Pearly white, progressive
• May become Morgagnian
• Virus persists up to 2 years → severe post-op inflammation
Rubella syndrome triad:
• Eye: Cataract, salt-pepper retinopathy
• Ear: Sensorineural deafness
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
38 | P a g e
drprabhatdevkota@gmail.com
• Heart: PDA, pulmonary stenosis, VSD
Prevention: Rubella vaccination ≥3 months before pregnancy
2. Congenital Membranous Cataract
• Absorbed cataract → thin membrane
• May mimic congenital aphakia
• Seen in Hallermann-Streiff syndrome
D. Cataracts Involving Adult Nucleus & Cortex
1. Coronary Cataract
• Appears around puberty
• Peripheral club-shaped opacities in corona
• Vision usually unaffected
2. Blue Dot Cataract (Cataracta punctata caerulea)
• Most common developmental cataract
• Bluish punctate peripheral opacities
• Stationary, asymptomatic
DIFFERENTIAL DIAGNOSIS OF LEUKOCORIA
1. Cataract
2. Coats disease
3. Coloboma
4. Retinoblastoma
5. Retinopathy of Prematurity (ROP)
6. Toxocariasis
7. Persistent Fetal Vasculature (PFV/PHPV)
8. Familial Exudative Vitreoretinopathy (FEVR)
9. Vitreous Hemorrhage (VH)
10. Retinal Detachment (RD)
11. Uveitis
12. Endophthalmitis
13. Norrie disease
14. Chorioretinal scar
15. Retinal dysplasia / congenital retinal folds
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
39 | P a g e
drprabhatdevkota@gmail.com
OCULAR & SYSTEMIC ASSOCIATIONS
Ocular Associations
Anterior Segment
• Microphthalmos – Rubella
• Microcornea, sclerocornea
• Cloudy cornea – Lowe, Fabry
• Glaucoma – Aniridia, Peters anomaly, Rubella
• Uveitis – Fuchs heterochromic iridocyclitis, JIA
• Iris coloboma
Posterior Segment
• Vitreous strands – Stickler syndrome
• Retinal pathology:
o ROP
o Salt-and-pepper retinopathy – Rubella
o Retinal flecks – Alport
o Retinoblastoma (usually fellow eye)
Systemic Associations
• Maternal infection (Rubella)
• Maternal drugs / radiation
• Hereditary syndromes (Neurofibromatosis)
• Metabolic disorders – Galactosemia, Fabry, Mannosidosis
• Chromosomal – Down, Nance-Horan
• Dermatological – Atopic dermatitis
• Musculoskeletal – Myotonic dystrophy
• Long-term steroid use
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
40 | P a g e
drprabhatdevkota@gmail.com
PATHOGENESIS OF CONGENITAL CATARACT
Congenital cataract results from disturbance of normal lens development,
transparency, or metabolism in utero or early infancy. The lens is avascular,
metabolically active, and highly sensitive to genetic, metabolic, infectious, and
environmental insults. Any disruption during primary lens fiber formation (4–7 weeks
gestation) or secondary fiber maturation leads to lens opacification.
NORMAL LENS DEVELOPMENT
• Lens placode forms at 4th week gestation
• Lens vesicle separates from surface ectoderm
• Posterior epithelial cells elongate → primary lens fibers (embryonic nucleus)
• Continued addition of secondary lens fibers throughout life
• Transparency maintained by:
o Regular fiber arrangement
o Crystallin protein stability
o Active ion pumps
o Anaerobic glycolysis
o Absence of organelles in mature fibers
Any factor disturbing these processes → cataract
MAJOR PATHOGENETIC MECHANISMS
1. GENETIC & MOLECULAR MECHANISMS
A. Crystallin Gene Mutations (Most Common)
Crystallins constitute 90% of lens proteins.
Gene Effect
α-crystallin Molecular chaperone failure → protein aggregation
β / γ crystallins Misfolding → light scattering
Pathogenesis
• Mutant crystallins lose solubility
• Protein aggregation → lens opacity
• Heat & oxidative stress accelerate aggregation
Clinical correlation
• Nuclear cataract
• Autosomal dominant inheritance common
B. Transcription Factor Mutations
Genes regulating lens development:
Gene Role
PAX6 Lens induction
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
41 | P a g e
drprabhatdevkota@gmail.com
Gene Role
PITX3 Lens fiber differentiation
FOXE3 Lens vesicle closure
Pathogenesis
• Abnormal lens morphogenesis
• Failure of fiber differentiation
• Structural cataracts (polar, nuclear)
C. Connexin Mutations (Gap Junctions)
• Connexin 46, Connexin 50
Mechanism
• Impaired intercellular communication
• Defective ion & metabolite transport
• Accumulation of Na⁺, Ca²⁺ → hydration → opacity
2. METABOLIC MECHANISMS
A. Galactosemia (Classic Exam Favorite)
Enzyme defect
• Galactose-1-phosphate uridyl transferase deficiency
Pathogenesis
• Galactose → galactitol via aldose reductase
• Galactitol is osmotically active
• Water influx → lens fiber swelling & rupture
Result
• Oil-droplet cataract
• Potential reversibility if treated early
B. Diabetes in Mother
• Excess fetal glucose
• Sorbitol accumulation
• Osmotic lens damage
C. Hypocalcemia
• ↓ Ca²⁺ dependent ATPase
• Altered membrane permeability
• Lens fiber degeneration
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
42 | P a g e
drprabhatdevkota@gmail.com
3. INTRAUTERINE INFECTIONS (TORCH)
A. Rubella (Most Important)
Timing: First trimester
Pathogenesis
• Viral replication in lens epithelium
• Inhibition of mitosis
• Persistence of nucleated lens fibers
• Failure of fiber maturation
Result
• Bilateral dense nuclear cataract
• Associated microphthalmos, PDA, deafness
B. CMV / Toxoplasmosis
• Direct cytopathic effect
• Inflammatory damage
• Less common than rubella
4. TOXIC & DRUG-INDUCED MECHANISMS
A. Maternal Drug Exposure
• Corticosteroids
• Thalidomide
• Anticonvulsants
Mechanism
• Interference with lens epithelial mitosis
• Oxidative stress
• Protein denaturation
B. Radiation
• DNA damage to lens epithelial cells
• Abnormal fiber differentiation
5. OXIDATIVE STRESS & ANTIOXIDANT FAILURE
Normal protection
• Glutathione
• Catalase
• Superoxide dismutase
Pathogenesis
• ROS accumulation
• Oxidation of crystallins
• Protein cross-linking
• Increased light scatter
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
43 | P a g e
drprabhatdevkota@gmail.com
Seen in:
• Genetic enzyme deficiencies
• Infections
• Metabolic disorders
6. DEVELOPMENTAL & MORPHOGENETIC DEFECTS
A. Failure of Lens Vesicle Separation
• Persistent connection with surface ectoderm
• Anterior polar cataract
• Anterior lenticonus
B. Persistent Fetal Vasculature (PFV)
• Failure of hyaloid artery regression
Mechanism
• Traction on posterior capsule
• Posterior capsular plaque
• Secondary lens opacification
7. CHROMOSOMAL & SYNDROMIC MECHANISMS
A. Down Syndrome
• Abnormal protein synthesis
• Increased oxidative stress
B. Lowe Syndrome
• Abnormal membrane transport
• Congenital cataract + glaucoma
C. Nance-Horan Syndrome
• X-linked
• Severe bilateral cataracts
8. INFLAMMATORY & IMMUNOLOGICAL MECHANISMS
• Fetal uveitis
• Inflammatory mediators damage lens epithelium
• Disruption of capsule permeability
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
44 | P a g e
drprabhatdevkota@gmail.com
MANAGEMENT OF PEDIATRIC CATARACT
AIMS OF MANAGEMENT
• Clear the visual axis early
• Prevent amblyopia
• Provide appropriate optical correction
• Ensure long-term visual rehabilitation
• Minimize complications
1. History
• Age of onset & progression
• Antenatal (fever, rash, drugs)
• Birth history (anoxia, prematurity, trauma)
• Developmental milestones
• Family history (cataract, thick glasses)
• Systemic symptoms (seizures, hematuria)
• Trauma / radiation / severe diarrhea
2. Visual Assessment (Age-based)
Age Method
Birth–3 yrs Fixation & following, Teller cards
<3 yrs OKN, VOR, VEP
3–6 yrs Picture charts
>6 yrs Snellen / LogMAR
3. Ocular Examination
• Red reflex test (screening)
• Pupillary reaction
• Retinoscopy
• IOP
• Ocular motility (strabismus, nystagmus)
• Slit-lamp (morphology)
• Fundus exam (undilated & dilated)
• B-scan USG if fundus not visible
• Examine parents & siblings
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
45 | P a g e
drprabhatdevkota@gmail.com
BIOMETRY & IOL POWER CALCULATION
Measurements
• Axial length: A-scan (immersion preferred)
• Keratometry: Hand-held keratometer
• IOL Master if cooperative
Formulae
• SRK/T, Holladay 2 → best for pediatric eyes
• IOL implantation considered if:
o Axial length >17 mm
o Corneal diameter >10 mm
Target Post-Op Refraction (Under correction)
❖ Dahan’s Rule
• <2 yrs → 20% under correction
• 2–8 yrs → 10% under correction
•
• 8 yrs → Full correction
❖ Prost et al: 20% under correction between 1 & 2 years, 15% under correction
between 2 & 4 years & 10% between 4 and 8 years of age
❖ Enyedi Rule of 7
Age + Post-op refraction = 7
Eg: 3-yr child → target +4 D
INDICATIONS FOR SURGERY
A cataract is visually significant if:
• 3 mm
• Central / pupillary axis
• Posterior location
• Dense nuclear / PSC
• Fundus not visible
• Poor fixation
• Nystagmus / strabismus
• Reduced near vision / glare / ↓ stereopsis
TIMING OF SURGERY
• Unilateral: 4–6 weeks
• Bilateral: 6–8 weeks
• After 6 weeks once fit for GA
Delay = irreversible amblyopia
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
46 | P a g e
drprabhatdevkota@gmail.com
POOR PROGNOSTIC FACTORS
• Dense central cataract
• Unilateral cataract
• Late presentation
• Nystagmus / strabismus
• Associated ocular anomalies
TREATMENT OPTIONS
NON-SURGICAL
• Mydriatics (anterior polar cataract)
• Optical correction
• Amblyopia therapy
SURGICAL MANAGEMENT
Anaesthesia
• General anesthesia
• Strict NPO protocol
Surgical Approaches
1. Pars Plana Lensectomy
• Neonates, <2 yrs
• No primary IOL planned
• Advantages: fast, less endothelial damage
• Disadvantage: vitreous incarceration
2. Corneolimbal Approach (Preferred)
• Lens aspiration via limbus
• Clear corneal (<3 mm) for foldable IOL
• Sclero-corneal tunnel for PMMA IOL
Key Surgical Steps
1. Trypan blue staining
2. Anterior capsulorhexis (elastic capsule!)
3. Lens aspiration (Simcoe/I&A)
4. Primary posterior capsulotomy + anterior vitrectomy
5. IOL implantation (if planned)
6. Wound closure with 10-0 nylon
PRIMARY POSTERIOR CAPSULOTOMY (PPC) – ideal 4 to 4.5mm
Indicated if:
• <8 years
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
47 | P a g e

drprabhatdevkota@gmail.com
• Posterior capsule plaque
• Nystagmus
• Poor fellow eye
• Poor follow-up
• Dense early PCO in other eye
• Corneal Scar (pupillary area)
• Mentally Challenged
• Dense PCO Yag Cap not possible
Purpose of Anterior Vitrectomy (AV):
• Intact vitreous face → scaffold for LEC migration, AV→ reduces scaffold for PCO &
secondary membrane formation
• Prevents vitreous prolapse into AC
• Maintains clear visual axis
IOL IMPLANTATION IN CHILDREN
Preferred
• 6 months age
• In-the-bag / sulcus
• Hydrophobic acrylic IOL
Contraindications
• Microcornea (<9.5 mm)
• Active uveitis (JIA)
• <6 months (relative)
• Poor zonular support
• ACIOL contraindicated
✔ Iris-fixated / SFIOL (secondary, later)
POSTOPERATIVE CARE
• Intensive steroid + antibiotic drops
• Mydriatics
• IOP monitoring
• Retinoscopy
• Follow-up: 2 weeks → 6 weeks → monthly → yearly
AMBLYOPIA MANAGEMENT
• Early patching
• Continue till 8–10 years
• Avoid over-patching
IATS regimen (unilateral):
• 1 hr/day per month of age (up to 8 months)
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
48 | P a g e
drprabhatdevkota@gmail.com
• Then 50% of waking hours
VISUAL REHABILITATION
Aphakia Correction
• Bilateral: Spectacles / contact lens
• Unilateral: Contact lens preferred
Pseudophakia
• Spectacles + bifocal
• Leave child mildly myopic
COMPLICATIONS
Intraoperative
• Capsulorhexis tear
• Iris prolapse
• Vitreous upthrust
• Wound leak
Early Post-op
• Uveitis
• Raised IOP
• Hyphema
• Endophthalmitis
Late
• PCO (most common)
• Secondary glaucoma
• IOL decentration
• Capsular phimosis
• Retinal detachment
POSTERIOR CAPSULE OPACIFICATION
• Faster & more aggressive in children
• Prevention: PPC + AV
• Nd:YAG if cooperative
• Surgical membranectomy if dense
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
49 | P a g e
drprabhatdevkota@gmail.com
PEDIATRIC VS ADULT CATARACT
Pediatric Adult
Small eye Normal size
Elastic capsule Rigid capsule
High inflammation Less
Rapid PCO Slower
Changing refraction Stable
Amblyopia risk None
Challenges of Pediatric Cataract Surgery
• Poor pupil dilation in pediatric eyes → due to strong parasympathetic innervation
• Small eye → difficult surgical manipulation
• Less scleral rigidity → wound leak, eye collapse, ↑ IOP
• Elastic capsule → difficult continuous curvilinear capsulorhexis (CCC)
• High risk of PCO → risk of amblyopia
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
50 | P a g e
drprabhatdevkota@gmail.com
Causes of Microspherophakia
Microspherophakia = Small, spherical crystalline lens due to defective zonular
development → causes high lenticular myopia, lens subluxation, secondary glaucoma.
1.Systemic (Syndromic / Metabolic / Genetic Causes)
A. Connective Tissue Disorders
• Weill–Marchesani syndrome (Most classically associated)
• Marfan syndrome
B. Metabolic Disorders
• Homocystinuria
• Hyperlysinemia
C. Genetic / Chromosomal Syndromes
• Lowe syndrome (Oculocerebrorenal syndrome)
• Klinefelter syndrome
• Cri-du-chat syndrome
D. Skeletal Dysplasia / Bone Disorders
• Microspherophakia–metaphyseal dysplasia
• Metaphyseal dysplasia
• Rhizomelic chondrodysplasia punctata
E. Renal / Basement Membrane Disorder
• Alport syndrome
F. Anterior Segment Developmental Syndromes
• Axenfeld–Rieger syndrome
• Peters anomaly
G. Craniofacial Disorders
• Mandibulofacial dysostosis
H. Intrauterine Infection
• Congenital rubella
2.Local (Ocular Associations)
Anterior Segment Disorders
• Aniridia
• Iridocorneal endothelial (ICE) syndrome
• Megalocornea
Posterior Segment / Optic Nerve
• Optic disc coloboma
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
51 | P a g e
drprabhatdevkota@gmail.com
Causes of Ectopia Lentis
1.Trauma (m/c)
2.Ocular Causes
A. Primary / Hereditary Ocular Disorders
• Simple ectopia lentis (AD / AR; ADAMTSL4, FBN1 mutations)
• Ectopia lentis et pupillae
B. Other Ocular Associations
• Aniridia
• Congenital glaucoma
• Pseudoexfoliation syndrome
• Syphilis
• Retinitis pigmentosa
• Intraocular tumors
• Axenfeld–Rieger syndrome
• Megalocornea
• Hypermature cataract
• High myopia
• Buphthalmos
• Anterior uveal tumors
3.Systemic Causes
A. Connective Tissue Disorders
• Marfan syndrome
• Ehlers–Danlos syndrome
• Weill–Marchesani syndrome
B. Metabolic Disorders
• Homocystinuria
• Sulfite oxidase deficiency
• Hyperlysinemia
C. Neurocutaneous / Vascular Disorders
• Sturge–Weber syndrome
D. Craniofacial / Skeletal Syndromes
• Mandibulofacial dysostosis
• Crouzon syndrome
• Pierre Robin sequence
• Conradi syndrome
• Pfaundler syndrome
• Wildervanck syndrome
• Sprengel deformity
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
52 | P a g e
drprabhatdevkota@gmail.com
Causes of Cloudy Cornea @STUMPED
• S: Sclerocornea
• T: Trauma: Birth trauma, DM tears
• U: Ulcers (Infective Keratitis)
• M: Metabolic Disorders: Mucopolysaccharidoses& Other storage disorders
• P: Peters Anomaly
• E: Endothelial Dystrophy:Congenital Hereditary Endothelial Dystrophy (CHED)
• D: Dermoid: Limbal dermoid
Why is there more inflammation after pediatric cataract surgery?
• Immature & hyperactive immune response → ↑ inflammation
• Blood–aqueous barrier less stable → ↑ protein & cells
• Rapid LEC proliferation
• Highly reactive uveal tissue → Strong immune response
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
53 | P a g e
drprabhatdevkota@gmail.com
TRAUMATIC CATARACT
Traumatic cataract refers to opacification of the crystalline lens resulting from
trauma.
Although trauma may include mechanical injury as well as physical agents
(radiation, chemicals, electricity), in clinical ophthalmology the term traumatic
cataract is reserved for cataract caused by mechanical ocular injuries.
CLASSIFICATION OF TRAUMATIC CATARACT
According to the mode of mechanical injury, traumatic cataract is classified into:
1. Cataract due to closed globe injury
2. Cataract due to open globe injury
3. Cataract due to intraocular foreign body (IOFB)
1. CATARACT CAUSED BY CLOSED GLOBE INJURY
(Blunt / Concussion trauma)
A blunt, non-penetrating injury may cause lens opacification either:
• Immediately, or
• As a delayed sequel
Blunt trauma may also cause lens subluxation or dislocation, with or without cataract
formation.
LENTICULAR CHANGES FOLLOWING BLUNT TRAUMA
i. VOSSIUS RING
• Circular ring of brown pigment on anterior lens capsule
• Formed by imprint of the contracted pupillary margin
• Occurs due to sudden apposition of iris to lens
• Ring is smaller than the pupillary diameter
• Does not cause significant visual impairment
• Often fades with time
Exam pearl:
Vossius ring is a sign of blunt trauma, not a true cataract.
ii. CONCUSSION CATARACT
Occurs due to:
• Imbibition of aqueous into lens fibres
• Direct mechanical damage to lens fibres
Forms of Concussion Cataract
a. Discrete Subepithelial Opacities
• Most common form
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
54 | P a g e
drprabhatdevkota@gmail.com
• Small, localized opacities beneath anterior capsule
• May remain stationary or progress
b. Early Rosette Cataract (Punctate)
• Most characteristic form
• Appears as feathery, star-shaped opacities
• Aligned along lens suture lines
• Typically located in posterior cortex
• Appears soon after injury
Classic description:
Star-shaped or rosette-like posterior cortical opacity
c. Late Rosette Cataract
• Develops 1–2 years after trauma
• Located in posterior cortex
• Sutural extensions are:
o Shorter
o More compact
• Represents delayed degeneration
d. Traumatic Zonular Cataract
• Rare
• Due to zonular damage affecting lens nutrition
• May be associated with lens instability
e. Diffuse (Total) Concussion Cataract
• Entire lens becomes opaque
• Common after severe blunt trauma
• Rapid progression
f. Membranous Cataract
• Seen especially in children
• Due to absorption of lens matter
• Leaves behind a fibrous capsular membrane
iii. EARLY MATURATION OF SENILE CATARACT
• Blunt trauma may accelerate maturation of a pre-existing senile cataract
• Important medicolegal implication
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
55 | P a g e
drprabhatdevkota@gmail.com
2. CATARACT CAUSED BY OPEN GLOBE INJURY
(Penetrating or perforating trauma)
Open globe injuries cause direct damage to lens capsule and fibres.
i. Massive Capsular Rupture
• Large perforation of lens capsule
• Release of lens matter into anterior chamber
• Lens becomes rapidly cataractous
• May cause:
o Phacolytic reaction
o Secondary glaucoma
o Severe inflammation
ii. Cortical Opacification at Site of Rupture
• Lens opacifies at site of capsular breach
• Rapid spread of opacity
• Often progresses to total cataract
iii. Small Capsular Perforation
• Capsule may seal spontaneously
• Results in:
o Stationary focal cortical cataract
• Vision may remain stable
Exam pearl:
Small capsular rents can heal → localized, non-progressive cataract.
3. CATARACT CAUSED BY INTRAOCULAR FOREIGN BODIES (IOFB)
Retained IOFBs can cause cataract by:
i. Direct Mechanical Injury
• Similar to penetrating lens injury
• Produces focal or total cataract
ii. Track-Related Opacity
• Foreign body produces an opaque tract through lens
• May progress to total cataract
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
56 | P a g e
drprabhatdevkota@gmail.com
iii. SPECIFIC METALLIC TOXIC REACTIONS
a. SIDEROSIS BULBI (Iron foreign body)
• Iron causes degenerative changes in ocular tissues
• Lenticular changes:
o Rust-coloured deposits
o Arranged radially in anterior epithelium and capsule
• Progresses to:
o Complete cortical cataract
Exam pearl:
Siderosis causes progressive, toxic cataract.
b. CHALCOSIS (Copper or copper-alloy foreign body)
• Deposition of copper ions
• Produces Sunflower cataract
o Located beneath posterior capsule
o Brilliant golden-green colour
o Petal-like radial pattern
Exam pearl:
Sunflower cataract = chalcosis due to copper IOFB.
SUMMARY TABLE (VIVA-READY)
Type Key Feature
Blunt trauma Concussion cataract
Typical opacity Rosette cataract
Pigment ring Vossius ring
Delayed cataract Late rosette
Children Membranous cataract
Iron IOFB Siderosis bulbi
Copper IOFB Sunflower cataract
EXAM TAKEAWAYS
• Traumatic cataract commonly follows mechanical injury
• Rosette cataract is pathognomonic of blunt trauma
• Small capsular tears may heal
• Metallic IOFBs cause toxic cataracts
• Trauma can accelerate senile cataract
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
57 | P a g e
drprabhatdevkota@gmail.com
GLUCOSE METABOLISM IN THE LENS
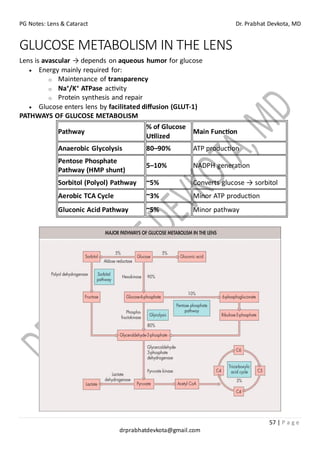
Lens is avascular → depends on aqueous humor for glucose
• Energy mainly required for:
o Maintenance of transparency
o Na⁺/K⁺ ATPase activity
o Protein synthesis and repair
• Glucose enters lens by facilitated diffusion (GLUT-1)
PATHWAYS OF GLUCOSE METABOLISM
Pathway
% of Glucose
Utilized
Main Function
Anaerobic Glycolysis 80–90% ATP production
Pentose Phosphate
Pathway (HMP shunt)
5–10% NADPH generation
Sorbitol (Polyol) Pathway ~5% Converts glucose → sorbitol
Aerobic TCA Cycle ~3% Minor ATP production
Gluconic Acid Pathway ~5% Minor pathway
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
58 | P a g e
drprabhatdevkota@gmail.com
MAJOR PATHWAYS OF GLUCOSE METABOLISM IN LENS
1. Glycolysis (Embden–Meyerhof Pathway) – ~70–80%
Principal energy pathway
Key points
• Occurs mainly in lens epithelium & superficial cortex
• Anaerobic glycolysis predominates
• End product → Lactate
Functions
• Produces ATP
• Maintains:
o Na⁺/K⁺ pump
o Lens hydration
o Transparency
Important enzymes
• Hexokinase
• Phosphofructokinase (rate-limiting)
• Pyruvate kinase
Clinical relevance
• ↓ ATP → membrane pump failure → lens swelling → cataract
2. Hexose Monophosphate Shunt (HMP / Pentose Phosphate Pathway) – ~5–10%
Protective pathway
Functions
• Generates NADPH
• NADPH maintains:
o Reduced glutathione (GSH)
Role of GSH
• Protects lens proteins from:
o Oxidation
o Free radicals
• Maintains sulfhydryl (–SH) groups of crystallins
Clinical relevance
• ↓ NADPH → ↓ GSH → protein oxidation → cataract
3. Polyol (Sorbitol) Pathway – Normally Minimal
Becomes dominant in diabetes
Steps
1. Glucose → Sorbitol (via aldose reductase, uses NADPH)
2. Sorbitol → Fructose (via sorbitol dehydrogenase – weak in lens)
Problems in lens
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
59 | P a g e
drprabhatdevkota@gmail.com
• Sorbitol is:
o Highly osmotic
o Poorly diffusible
Consequences
• Osmotic influx of water
• Lens fiber swelling & vacuolation
• ↓ NADPH → ↓ GSH
Major mechanism of diabetic cataract
4. Minor Pathways
• Glucose → Fructose → Glycolysis
• Glycoprotein & lipid synthesis
• Amino acid metabolism
EXAM PEARLS
• Most important pathway → Glycolysis
• Most important protective system → HMP shunt + GSH
• Key enzyme in diabetic cataract → Aldose reductase
• Osmotic agent → Sorbitol
• NADPH depletion links polyol pathway + oxidative damage
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
60 | P a g e
drprabhatdevkota@gmail.com
GLUCOSE METABOLISM UNDER NORMAL CONDITIONS
• Majority via glycolysis
• Adequate:
o ATP
o GSH
• Normal membrane permeability
• Transparent lens
GLUCOSE METABOLISM IN DIABETES
A. Excess Glucose Load
• Hexokinase becomes saturated
• More glucose diverted to polyol pathway
B. Sorbitol Accumulation Effects
• Osmotic stress → lens fiber swelling
• Formation of vacuoles
• Membrane damage
C. NADPH Depletion
• Used up by aldose reductase
• ↓ GSH regeneration
• ↑ oxidative damage
D. Non-enzymatic Glycosylation
• Glucose binds lens crystallins
• Formation of:
o Advanced glycation end products (AGEs)
• Results in:
o Protein unfolding
o Aggregation
o Increased light scattering
E. Protein Changes
• Mixed disulfide formation
• Non-SS crosslinking
• Aggregated insoluble proteins
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
61 | P a g e
drprabhatdevkota@gmail.com
DIABETIC CATARACT
Diabetic cataract is a metabolic cataract occurring due to biochemical derangements in
diabetes mellitus, affecting lens metabolism, hydration, protein structure, and redox
balance.
Classification in Diabetes
Diabetes is associated with two distinct cataract patterns:
1. True Diabetic Cataract (Snowflake / Snow-storm Cataract)
• Seen in young patients / juvenile diabetics
• Rare but characteristic
• Rapidly progressive
2. Senile Cataract in Diabetics
• Earlier onset
• Faster progression
• Morphologically resembles age-related cataract but with metabolic acceleration
1. TRUE DIABETIC CATARACT (SNOWFLAKE CATARACT)
Etiology
• Due to osmotic over-hydration of lens
• Caused by sorbitol accumulation from excess glucose metabolism
Pathogenesis (Osmotic / Polyol Pathway)
• Glucose enters lens (insulin-independent)
• Excess glucose → Aldose reductase
• Glucose → Sorbitol
• Sorbitol:
o Highly polar
o Poorly diffusible across lens capsule
• Leads to:
o ↑ Intracellular osmotic pressure
o Water influx
o Lens fiber swelling and vacuolization
Morphology
• Initial:
o Numerous subcapsular fluid vacuoles
o Both anterior and posterior
• Progression:
o Bilateral snowflake-like white opacities
o Superficial cortex, posterior cortex first
• Rapid maturation
• Intumescent lens
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
62 | P a g e
drprabhatdevkota@gmail.com
Clinical Features
• Young age
• Sudden visual loss
• Bilateral
• Rapid progression
2. SENILE CATARACT IN DIABETICS
Key Features
• Occurs earlier than non-diabetics
• Progresses faster
• Due to multiple interacting biochemical mechanisms
Major Contributing Factors
1. Sorbitol accumulation
2. Non-enzymatic glycosylation (glycation)
3. Oxidative stress
4. Altered lens metabolism
ETIOPATHOGENESIS OF DIABETIC CATARACT
Three major theories are described:
I. OSMOTIC THEORY (POLYOL PATHWAY)
(Important but not sufficient alone)
Biochemical Steps
• Glucose → Sorbitol (aldose reductase)
• Sorbitol → Fructose (polyol dehydrogenase – limited in lens)
Consequences
• Sorbitol accumulation
• ↑ Lens hydration
• Fiber swelling
• Membrane damage
• Vacuole formation
Limitations
• Explains acute snowflake cataract
• Does not fully explain chronic cataract formation
II. AUTO-OXIDATION OF SUGARS THEORY
(Less important / controversial)
Hypothesis
• Sugars undergo auto-oxidation
• Produce:
o Free radicals
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
63 | P a g e
drprabhatdevkota@gmail.com
o α-oxoaldehydes
• Cause oxidative lens damage
Arguments Against
• Significant glucose auto-oxidation not proven
• No specific alternative monosaccharide identified
• No definitive evidence of direct oxidative injury
Exam point: Role is uncertain and minor
III. NON-ENZYMATIC GLYCOSYLATION (GLYCATION) THEORY
Definition
Non-enzymatic covalent binding of glucose to amino groups of lens proteins,
especially crystallins.
Mechanism of Glycation
Initial Step
• Open-chain glucose reacts with:
o Lysine / arginine residues of lens proteins
• Formation of:
o Schiff base → Amadori products
Progressive Changes
• Advanced glycation end products (AGEs)
• Leads to:
o Structural protein damage
o Enzyme inactivation
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
64 | P a g e
drprabhatdevkota@gmail.com
Biochemical & Structural Consequences
1. Lens Protein Changes
• Conformational alteration
• Thiol (–SH) oxidation
• Disulfide cross-linking
• Non-SS covalent crosslinks
• Protein unfolding and aggregation
2. Crystallin Damage
• γ-crystallin glycation
• Aggregated proteins
• ↑ Light scattering → opacity
3. Membrane Damage
• Na⁺/K⁺ ATPase inhibition
• ↑ Na⁺ influx
• Cellular swelling
4. Oxidative Stress
• ↓ NADPH
• ↓ Reduced glutathione (GSH)
• ↑ Protein SH oxidation
Harding’s Concept
Non-enzymatic glycosylation is responsible not only for:
• Diabetic cataract
but also:
• Retinopathy
• Nephropathy
• Neuropathy
• Cardiovascular disease
(As shown in Harding’s schematic diagrams)
SPECULATIVE SCHEME OF DIABETIC CATARACT (Harding)
Key Events
• Diabetes → ↑ Glucose in lens
• ↑ Sorbitol + ↑ Glycation
• ↓ Myoinositol
• ↓ ATP
• ↓ Amino acid uptake
• Membrane damage
• Protein aggregation
• Light scattering
• Cataract formation
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
65 | P a g e
drprabhatdevkota@gmail.com
SUMMARY TABLE
Aspect True Diabetic Cataract Senile Cataract in Diabetes
Age Young Older
Onset Sudden Early
Progression Rapid Accelerated
Mechanism Osmotic (sorbitol) Glycation + oxidative stress
Morphology Snowflake Nuclear / cortical / PSC
Reversibility Rare No
KEY EXAM PEARLS
• Snowflake cataract = juvenile diabetes
• Sorbitol accumulation = osmotic lens damage
• Non-enzymatic glycosylation is the most important mechanism
• Harding linked glycation to systemic diabetic complications
• Diabetic cataracts mature faster → early surgery needed
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
66 | P a g e
drprabhatdevkota@gmail.com
COMPLICATED CATARACT
Complicated cataract refers to opacification of the crystalline lens occurring secondary to
other intraocular diseases, particularly those affecting the uvea, retina, vitreous, or ocular
circulation.
Pathophysiology (Basic Concept)
• The lens is avascular and depends on aqueous and vitreous humor for nutrition.
• Any condition causing:
o Disturbance of intraocular circulation
o Chronic inflammation
o Release of inflammatory toxins
o Metabolic imbalance
will impair lens nutrition → lens epithelial dysfunction → cortical
degeneration → cataract formation.
ETIOLOGY
1. Inflammatory Conditions (Most Common Cause)
• Chronic uveitis:
o Iridocyclitis
o Pars planitis
o Choroiditis
• Hypopyon corneal ulcer
• Endophthalmitis
Key exam facts
• Complicated cataract commonly develops in chronic uveitis
• Often aggravated by long-term corticosteroid therapy
• ~70% of Fuchs’ heterochromic uveitis cases develop complicated cataract
• Posterior subcapsular cataract (PSC) is the usual starting point
• Anterior subcapsular cataract may occur due to:
o Posterior synechiae
o Chronic inflammation
o Capsule thickening
2. Degenerative Ocular Disorders
• Retinitis pigmentosa
• Other pigmentary retinal dystrophies
• Myopic chorioretinal degeneration
• Essential iris atrophy
• Chronic hypotony
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
67 | P a g e
drprabhatdevkota@gmail.com
Features
• Usually begins as PSC
• May progress to total cataract
• Exact mechanism unclear, but likely due to:
o Altered metabolism
o Chronic retinal degeneration
o Vitreous biochemical changes
3. Retinal Detachment
• Seen in long-standing retinal detachment
• Due to:
o Altered vitreous composition
o Impaired lens nutrition
4. Glaucoma (Primary or Secondary)
Mechanism
• Raised IOP → compromised intraocular circulation → lens epithelial damage
Glaucoma Fleckens (Very Important Viva Point)
• Occur after markedly elevated IOP, especially:
o Acute angle-closure glaucoma
• Appear as:
o Grey-white anterior epithelial and anterior cortical opacities
Histopathology
• Necrotic lens epithelial cells
• Degenerated subepithelial cortex
5. Intraocular Tumours
• Retinoblastoma
• Choroidal melanoma
• Metastatic intraocular tumours
Mechanism
• Chronic inflammation
• Altered intraocular metabolism
• Seen in late stages
6. Ischaemic Ocular Conditions
• Pulseless disease (Takayasu arteritis)
• Thromboangiitis obliterans (Buerger disease)
• Anterior segment necrosis
Features
• Usually causes PSC
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
68 | P a g e
drprabhatdevkota@gmail.com
• Rapid progression to total cataract
CLINICAL FEATURES
A. Posterior Cortical Complicated Cataract (Typical Form)
Site
• Begins as posterior subcapsular cortical cataract
Slit-Lamp Appearance
• Irregularly shaped opacities
• Variable density
• Bread-crumb appearance in slit-lamp beam
• Polychromatic lustre:
o Iridescent colors — red, green, blue
o Highly characteristic sign
• Adjacent cortex shows diffuse yellowish haze
Progression
• Gradual spread to remaining cortex
• Eventually involves entire lens
• Final stage:
o Chalky white cataract
o Calcium deposition common
B. Anterior Cortical Complicated Cataract
Seen in
• Anterior segment pathology:
o Glaucoma
o Hypopyon corneal ulcer
o Acute iritis
Early Changes
• Vacuole formation just beneath anterior capsule
Later Changes
• Opacities in adjacent cortical fibers
• Thickening of anterior lens capsule
EXAM POINTS (High-Yield)
• Complicated cataract is always secondary to ocular disease
• Posterior subcapsular cataract is the earliest and most common form
• Polychromatic lustre is characteristic
• Chronic uveitis + steroids = major risk
• Glaucoma fleckens are epithelial necrosis, not true cataract initially
• Progression depends on control of primary disease
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
69 | P a g e
drprabhatdevkota@gmail.com
STEROID–INDUCED CATARACT
Steroid-induced cataract is a secondary cataract classically presenting as a Posterior
Subcapsular Cataract (PSC) due to prolonged steroid exposure.
Most characteristic cataract due to steroids = PSC
Important Facts
• Type: Posterior subcapsular cataract (PSC)
• Drugs: Topical, systemic, inhalational, periocular and intraocular steroids
• Risk: Dose and duration related, but exact relationship unclear
• Children: More susceptible than adults
• Reversibility: Some early PSCs (especially in children) may regress after stopping
steroid
Steroids Associated (Routes)
A. Systemic steroids
• Oral prednisolone
• IV methylprednisolone
B. Topical ocular steroids
• Prednisolone acetate
• Dexamethasone
• Betamethasone
C. Periocular / Intraocular steroids (high risk)
• Triamcinolone acetonide (intravitreal)
• Dexamethasone implant (Ozurdex)
• Fluocinolone implant
D. Inhalational steroids (important modern MCQ)
• Budesonide
• Fluticasone
(long-term asthma patients)
Epidemiology / Risk Factors
Major risk factors
• High dose steroids
• Prolonged therapy
• Children (more vulnerable)
• Repeated intraocular steroid injections/implants
• Chronic uveitis patients (double hit: inflammation + steroid)
Steroid cataract incidence has increased due to use of intravitreal steroids for
retinal diseases.
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
70 | P a g e
drprabhatdevkota@gmail.com
Pathogenesis-- imp
Harding & Crabbe mechanisms (Classic List)
Steroids may induce cataract by:
1. Elevation of glucose
2. Inhibition of Na⁺/K⁺ ATPase
3. Increased cation permeability
4. Inhibition of glucose-6-phosphate dehydrogenase (G6PD)
5. Inhibition of RNA synthesis
6. Loss of ATP
7. Covalent binding of steroids to lens proteins
Exam Trick:
If asked most important biochemical factor → Na-K ATPase inhibition + oxidative
damage
Harding Speculative Scheme
Steroid causes:
A. Metabolic disturbance
• ↑ glucose → ↑ G6P
• Altered phase separation temperature
→ lens protein instability
B. Oxidative stress pathway
• ↓ G6PD → ↓ NADPH
• ↓ glutathione (GSH) + ↓ ascorbate
→ oxidative damage
C. Ion pump failure
• ↓ Na-K ATPase
→ Na⁺ ↑, K⁺ ↓, water ↑
→ lens hydration + clefts
Final common pathway:
• Chemical modification of crystallins
• Conformational change
• Reactive SH groups → disulphide cross-linking
• Protein aggregation
PSC cataract formation
Final outcome = protein aggregation + hydration changes → PSC
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
71 | P a g e
drprabhatdevkota@gmail.com
Clinical Features (PSC Pattern)
Symptoms
• Early glare
• Halos
• Poor near vision (worse in bright light)
• Difficulty reading
• Night driving difficulty
Signs (Slit Lamp)
Early
• Subtle iridescent sheen in posterior cortex
Later
• Granular opacities
• Plaque-like axial opacity
• Typical central posterior subcapsular plaque
Clinical appearance resembles age-related PSC.
Histopathology
Hallmark
• Posterior migration of lens epithelial cells
(from equator → posterior pole)
Cellular changes
• Abnormal enlargement and swelling of epithelial cells
• Formation of Wedl cells / bladder cells
#Steroid PSC = Wedl (bladder) cells
Differential Diagnosis
Steroid PSC resembles:
• Age-related PSC
• Uveitic complicated cataract
• Radiation cataract (also PSC)
• Atopic dermatitis cataract (can show shield-like opacities)
If question says PSC in young with long-term steroid use → steroid cataract.
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
72 | P a g e
drprabhatdevkota@gmail.com
Prevention
Key preventive measures
• Regular slit lamp examination for all long-term steroid users
• Use lowest effective dose
• Prefer intermittent regimen over continuous therapy
• Use steroid-sparing agents when possible
(NSAIDs / immunomodulators like methotrexate, azathioprine, cyclosporine
depending on disease)
• Avoid unnecessary topical steroid misuse
#Screening recommendation: periodic ophthalmic follow-up is mandatory.
11. Reversibility / Prognosis
• Cataract progression may stop after steroid cessation
• Some early PSCs in children may partially resolve after stopping drug
• Advanced PSC is usually irreversible → requires surgery
12. Management (Clinical Approach)
Step 1: Identify steroid exposure
• Dose, duration, route
• Look for associated steroid side effects (IOP rise)
Step 2: Modify therapy
• Stop steroid if possible
• Switch to safer alternatives or taper dose
Step 3: Definitive treatment
• Phacoemulsification with PCIOL if visually significant
• Prognosis is generally good unless coexisting retinal/uveitic pathology
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
73 | P a g e
drprabhatdevkota@gmail.com
MANAGEMENT OF CATARACT IN ADULTS
Definitive treatment: Surgical removal of cataract
Non-surgical measures: Temporary / adjunctive, useful in selected situations
A. NON-SURGICAL MANAGEMENT
1. Treatment of Associated / Causative Disease
Important in acquired (non-senile) cataracts to slow progression and defer
surgery.
Examples:
• Diabetes mellitus: Strict glycemic control may retard progression.
• Drug-induced cataract: Withdrawal of cataractogenic drugs
(e.g. corticosteroids, phenothiazines, strong miotics).
• Radiation exposure: Avoidance of infrared or X-ray exposure.
• Ocular inflammation: Early and adequate treatment of uveitis prevents
complicated cataract.
Exam pearl: Treating the cause may halt progression, rarely cause partial
regression in early stages.
2. Measures to Delay Progression
No proven medical therapy to reverse or stop cataract progression.
• Topical iodide preparations (calcium/potassium iodide):
Commonly prescribed in early senile cataract → no conclusive evidence.
• Aldose reductase inhibitors: Prevent diabetic cataract in animals.
• Investigational agents:
Sorbitol-lowering drugs, aspirin, glutathione-enhancing agents.
• Antioxidants (Vit E, C, beta-carotene, zinc): Do not slow progression.
3. Measures to Improve Vision in Incipient & Immature Cataract
Useful for symptomatic relief until surgery.
• Frequent refraction: Rapid refractive changes are common.
• Illumination advice:
o Peripheral opacities: Bright illumination (small pupil).
o Central opacities: Dim light placed beside/behind the head.
• Dark goggles: Helpful in central cataract to reduce glare.
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
74 | P a g e
drprabhatdevkota@gmail.com
• Mydriatics:
o Indication: Small axial cataract
o Drugs:
▪ Phenylephrine 5% or
▪ Tropicamide 1%
o Dose: 1 drop b.i.d.
o Mechanism: Allows clear paraxial lens to aid vision.
Exam pearl: Mydriatics improve vision by utilizing clear peripheral lens fibers.
4. Low Vision Aids
Indicated when surgery is contraindicated or not feasible.
• Distance vision:
o Hand-held monoculars (2.5×, 2.8×, 4×)
• Near vision:
o High-add spectacles
o Hand/stand magnifiers
o Closed-circuit television (CCTV)
o Telescopic loupes
B. SURGICAL MANAGEMENT
Definitive and curative treatment
• Intracapsular Cataract Extraction (ICCE)
• Extracapsular Cataract Extraction (ECCE)
• Small Incision Cataract Surgery (SICS)
• Phacoemulsification
• FLACS
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
75 | P a g e
drprabhatdevkota@gmail.com
INTRACAPSULAR vs EXTRACAPSULAR CATARACT
EXTRACTION
Intracapsular Cataract Extraction (ICCE)
• Entire lens removed with intact capsule
• Requires weak / degenerated zonules
• No capsular support remains
Extracapsular Cataract Extraction (ECCE)
• Anterior capsule + nucleus + cortex removed
• Posterior capsule preserved
• Allows posterior chamber IOL (PCIOL) implantation
HISTORICAL PERSPECTIVE
• ICCE: Gold standard for ~100 years → now obsolete
• ECCE: Replaced ICCE over last 40 years
• Modern cataract surgery evolved from:
o ICCE → Conventional ECCE → SICS → Phacoemulsification
INDICATIONS & CONTRAINDICATIONS
ICCE
Indication:
• Markedly subluxated or dislocated lens
Why?
• Zonules already weak → easy lens delivery
Contraindications:
• Children & young adults
• Intact zonules
• Vitreoretinal pathology
ECCE
Indications:
• Surgery of choice for almost all cataracts
o Childhood cataract
o Adult senile cataract
Absolute Contraindication:
• Markedly subluxated / dislocated lens
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
76 | P a g e
drprabhatdevkota@gmail.com
TYPES OF ECCE
1. Planned large-incision ECCE
2. Manual Small Incision Cataract Surgery (SICS)
3. Phacoemulsification
ICCE vs ECCE
Feature ICCE ECCE
Capsule Entire capsule removed Posterior capsule preserved
Zonules Must be weak Must be intact
IOL ACIOL only PCIOL possible
Vitreous complications Common Rare
Endophthalmitis High Low
CME / RD Common Less common
Astigmatism High Less
Future glaucoma / keratoplasty Poor prognosis Better prognosis
Diabetic rubeosis More Less
Current status Obsolete Gold standard
ADVANTAGES OF ECCE OVER ICCE
1. Universal procedure (all ages)
2. Posterior chamber IOL implantation
3. Minimal vitreous-related complications
4. Lower incidence of:
o Endophthalmitis
o CME
o Retinal detachment
5. Less postoperative astigmatism
6. Better outcome for future:
o Trabeculectomy
o Keratoplasty
7. Reduced rubeosis in diabetics
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
77 | P a g e
drprabhatdevkota@gmail.com
MODERN ECCE vs SICS
Merit of ECCE over SICS
• Only merit: Easier to learn & Short learning curve
Demerits of ECCE
• Large incision (8–10 mm)
• Multiple sutures
• Open chamber surgery
• High risk of:
o Vitreous prolapse
o Expulsive choroidal hemorrhage
• High postoperative astigmatism
• Suture-related complications
• Delayed visual rehabilitation
SICS vs PHACOEMULSIFICATION
Merits of SICS over Phaco
1. Universal applicability
o Even hard cataracts (Grade IV–V)
2. Easier learning curve
3. Not machine dependent
4. Less disastrous complications
5. Shorter surgical time (ideal for mass surgery)
6. Cost-effective
o No phaco machine
o PMMA IOLs cheaper
Demerits of SICS
• Mild conjunctival congestion
• Scleral tenderness
• Occasional hyphaema
• More surgically induced astigmatism (~6 mm incision)
Merits of Phaco over SICS
1. Can be done under topical anesthesia
2. Minimal postoperative congestion
3. Small incision (≈3.2 mm)
4. Less corneal endothelial damage
5. Faster visual rehabilitation
6. Less postoperative astigmatism (foldable IOL)
Demerits of Phaco
1. Steep learning curve
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
78 | P a g e
drprabhatdevkota@gmail.com
2. Complications like nuclear drop are unforgiving
3. Totally machine dependent
4. Expensive equipment & maintenance
5. Difficult in very hard cataracts
6. Higher corneal complications due to excess phaco energy
CONCLUSION
• Phacoemulsification is the preferred technique worldwide in expert hands.
• Manual SICS is ideal for developing countries due to:
o Low cost
o Wider applicability
o Easier learning curve
SURGICAL STEPS – ICCE
Pre-operative Essentials
• Full pupillary dilatation
• Peribulbar anesthesia
• Lower IOP
Key Surgical Steps
1. Lid speculum
2. Superior rectus bridle suture
3. Conjunctival flap (optional)
4. Limbal groove (150°)
5. Corneoscleral section
6. Peripheral iridectomy
7. Lens delivery methods:
o Smith Indian method
o Cryoextraction (–40°C)
o Capsule forceps
o Wire vectis (subluxated lens)
8. Anterior chamber formation
9. ACIOL implantation
10.Wound closure (5–7 sutures)
11.Subconjunctival antibiotics + steroids
12.Eye patching
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
79 | P a g e
drprabhatdevkota@gmail.com
SURGICAL STEPS – PLANNED MODERN ECCE
Key Steps
1. Lid speculum
2. Superior rectus suture
3. Conjunctival flap
4. Partial thickness limbal groove
5. Anterior chamber entry
6. Viscoelastic injection
7. Anterior capsulotomy:
o Can-opener
o Linear (envelope)
o CCC (most common)
8. Removal of anterior capsule
9. Completion of corneoscleral section
10.Hydrodissection
11.Nucleus delivery
12.Cortex aspiration & PC polishing
13.PCIOL implantation
14.Wound closure (10-0 nylon)
15.Viscoelastic removal
16.Conjunctival closure
17.Subconjunctival injection
18.Patching
POSTOPERATIVE CARE (COMMON TO ICCE & ECCE)
• Supine rest 2–3 hours
• Analgesics if needed
• Next-day eye examination
• Antibiotic-steroid drops tapering over 6–8 weeks
• Suture removal: 6–8 weeks
• Final spectacles: after ~8 weeks
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
80 | P a g e
drprabhatdevkota@gmail.com
SMALL INCISION CATARACT SURGERY (SICS)
• Gold standard cataract surgery today → Phacoemulsification
• Manual SICS = effective, low-cost, sutureless alternative
• Developed in late 1980s
• Technique:
o ECCE + PCIOL
o Through self-sealing sutureless sclerocorneal tunnel
Especially important in developing countries & high-volume surgery
Manual SICS is a sutureless extracapsular cataract extraction with PCIOL
implantation performed through a self-sealing corneoscleral tunnel incision
without phaco machine.
COMPARISON
SICS vs Planned ECCE
Merits of SICS over ECCE
• Small incision (5.5–7 mm)
• Sutureless → faster healing
• Closed chamber surgery
• Less astigmatism
• Fewer wound-related complications
Demerits of Planned ECCE
• Large incision (10–12 mm)
• Multiple sutures
• Open chamber → ↑ vitreous loss, expulsive hemorrhage
• High postoperative astigmatism
• Suture-related problems
Only merit of ECCE: Easy learning curve
SICS vs Phacoemulsification
Merits of SICS over Phaco
1. Easy to learn
o Larger incision
o Can-opener capsulotomy acceptable
o No need for hand-foot coordination
2. Universal applicability
o Very hard cataracts (Grade IV–V)
o Post-vitrectomy eyes
o Traumatic cataract
o Combined with trabeculectomy
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
81 | P a g e
drprabhatdevkota@gmail.com
3. Not machine dependent
4. Fewer disastrous complications
o Less nucleus drop
o No phaco burn / iris chafing
5. Shorter operating time (hard cataracts)
6. Cost-effective
7. Ideal conversion technique from failed phaco
8. Ideal for mass surgery
Demerits of SICS
• Conjunctival congestion (5–7 days)
• Mild scleral tenderness
• Occasional hyphaema
• More surgically induced astigmatism (6 mm incision)
Merits of Phaco over SICS
• Smaller incision (≈3.2 mm)
• Faster visual recovery
• Less postoperative astigmatism
• Minimal inflammation
• Topical anesthesia possible
• Less corneal endothelial damage
Conclusion
• Phaco = preferred worldwide in expert hands
• Manual SICS =
o Low-cost
o Wide applicability
o Easier learning curve
o Best option for developing countries
INDICATIONS OF SICS
• Mass cataract surgery
• Non-availability / failure of phaco machine
• Surgeon not trained in phaco
• Patient cannot afford phaco
• Contraindications to phaco:
o Ultra-hard cataract
o Borderline endothelium
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
82 | P a g e
drprabhatdevkota@gmail.com
CONTRAINDICATIONS OF SICS
Absolute / Relative
1. Lens:
o Subluxated / dislocated lens
o Poor zonular support
2. Cornea:
o Microcornea
o Endothelial dystrophy
o Peripheral thinning
3. Sclera:
o Active or old scleritis
o Scleral ectasia
4. Conjunctiva:
o Severe scarring disorders
5. Bleeding disorders
6. Inexperienced surgeon
Clear corneal incision preferred in bleeding disorders
SURGICAL TECHNIQUE (STEPWISE)
1. Bridle Suture
• 3-0 silk
• Superior rectus (or lateral rectus in temporal SICS)
• Purpose:
o Fixation
o Counter-traction during nucleus delivery
2. Conjunctival Flap
• Fornix-based flap (10–2 o’clock)
• Exposure of ~4 mm sclera
• Gentle wet-field cautery
3. Sclerocorneal Tunnel Incision
Historical Contributors
• Kratz (1982) – scleral incision
• Girard & Hoffman (1984) – scleral tunnel
• McFarland (1989) – two-plane incision
• Paul Ernest (1990) – three-plane, internal corneal lip
• Paul Koch – incisional funnel concept
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
83 | P a g e
drprabhatdevkota@gmail.com
Components
1. External scleral incision
2. Sclerocorneal tunnel
3. Internal corneal incision
External Scleral Incision
• Depth: ⅓–½ scleral thickness
• Location: 1.5–2 mm behind limbus
• Length: 5.5–7.5 mm
• Shapes:
o Straight (more astigmatism)
o Frown (BEST)
o Chevron
o Trapezoid (large nucleus)
Sclerocorneal Tunnel
• Made with 2.8 mm crescent knife
• Extends 1–1.5 mm into clear cornea
• Uniform depth essential
• Avoid:
o Superficial → buttonhole
o Deep → premature entry
Scleral pockets for very hard nuclei
Internal Corneal Incision
• 2.8–3.2 mm keratome
• Forward cutting only
• Must be straight → self-sealing valve
Side Port Entry
• 2 × 2 mm clear corneal
• Uses:
o CCC
o OVD injection
o Subincisional cortex
o AC formation
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
84 | P a g e
drprabhatdevkota@gmail.com
Koch’s Astigmatic Neutral Funnel
Funnel:
• An imaginary pair of curved lines with their base at the limbus and diverging
posteriorly.
• Any incision within the funnel → minimal to negligible SIA.
Surgically Induced Astigmatism (SIA) depends on:
• Incision length: SIA ∝ incision length
• Distance from limbus: SIA ∝ 1 / distance from limbus
(Larger incisions → ↑ astigmatism, Posteriorly placed incisions → ↓
astigmatism)
→ Koch’s Astigmatic Neutral Funnel describes the relationship between incision
length, distance from the limbus, and SIA.
Principle
• Short incision close to the limbus
• Longer incision placed farther from the limbus
• Both produce approximately the same astigmatic effect.
→ Incisions within this funnel are considered astigmatically neutral.
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
85 | P a g e
drprabhatdevkota@gmail.com
4. ANTERIOR CAPSULOTOMY
Types
1. Can-opener
2. Linear (envelope)
3. Christmas tree
4. CCC (Gold standard)
Dyes
• Trypan blue – preferred
• ICG – expensive
CCC
• Ideal size: 6–6.5 mm
• Instruments:
o Cystitome
o Utrata forceps
o Combined technique
Methods
• Shearing → safer, controlled
• Ripping → faster, less control
5. HYDROPROCEDURES
Hydrodissection
• Separates cortex from capsule
• Essential before nucleus delivery
• In SICS → aim for hydroprolapse
Hydrodelineation
• Separates epinucleus from endonucleus
• Shows golden ring sign
• Limited role in SICS
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
86 | P a g e
drprabhatdevkota@gmail.com
6. NUCLEAR MANAGEMENT
A. Prolapse of Nucleus
• Hydroprolapse
• Sinskey hook prolapse
B. Nucleus Extraction Techniques
1. Irrigating vectis (Most common)
2. Blumenthal mini-nucleus technique
3. Fish-hook (Hennig / Lahan technique)
4. Phacosandwich
5. Phacofracture techniques:
o Bisector
o Trisector
o Chop-section
o Pre-chop
o Slider-pincer
o Quarter extraction
7. CORTICAL ASPIRATION
• Done using Simcoe cannula
• Golden rules:
o Never aspirate blindly
o Maintain AC depth
o Watch for posterior capsule folds
Special Situations
• 12 o’clock cortex → side port / J-cannula
• Small pupil → bimanual I/A
• PCR → dry aspiration ± anterior vitrectomy
8. IOL IMPLANTATION
Choice of IOL
• PMMA (6 mm optic) – most common
• Phacoprofile PMMA (5–5.25 mm)
• Foldable IOL – small incision techniques
Implantation Techniques
1. Dialling technique
2. Flexing / looping technique
Alternative Fixation
• Sulcus fixation
• Scleral fixation (sutured / glued)
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
87 | P a g e
drprabhatdevkota@gmail.com
9. WOUND CLOSURE
• Usually sutureless
• Sutures required if:
o Large tunnel (>6.5 mm)
o Leaky wound
o Premature entry
o Combined trabeculectomy
o Paediatric cataract
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
88 | P a g e
drprabhatdevkota@gmail.com
PHACO MACHINE & PHACODYNAMICS
• Phacoemulsification introduced by Charles D. Kelman (1967)
• First machine: Cavitron–Kelman Phacoemulsifier Mark I
o Bulky (refrigerator-sized)
• Modern machines:
o Compact, portable, microprocessor-controlled
o Same basic working principle
Basic Principle
→Ultrasonic vibration emulsifies the cataractous lens
→ Simultaneous I/A (irrigation–aspiration) maintains anterior chamber stability
and removes lens matter
→ Allows foldable IOL implantation through a small incision
Aims
1. Sculpting efficiency
2. Impaling / holding power
3. Followability
4. Anterior chamber stability
BASIC COMPONENTS
1. Console
2. Handpiece
3. Foot pedal
1. CONSOLE
Functions
The console houses a computerized control system regulating:
• Phaco power delivery
• Irrigation system
• Aspiration system
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
89 | P a g e
drprabhatdevkota@gmail.com
Modern Features
• Microprocessor with software algorithms
• Multimode memory panel (surgeon-specific settings)
• Adjustable parameters:
o Power
o Vacuum
o Flow rate
o Pulse/burst settings
2. HANDPIECES
Types
I. Phaco (Ultrasonic) handpiece
II. Irrigation–Aspiration (I/A) handpiece
I. PHACO HANDPIECE
Functions (THREE SYSTEMS)
• Power delivery
• Irrigation
• Aspiration
Power Generation
• Piezoelectric crystal
• Converts electrical → mechanical energy
• Produces ultrasonic vibration
PHACO TIP
Basic Structure
• Hollow titanium needle
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
90 | P a g e
drprabhatdevkota@gmail.com
• Frequency: 27,000–60,000 Hz
• Covered by silicone sleeve
o 2 irrigation ports (180° apart)
• Distal opening = aspiration port
TYPES OF PHACO TIPS
A. STANDARD PHACO TIPS (19G)
• OD: 1.1 mm, ID: 0.9 mm
Bevel Angle Cutting Holding Indication
0° Minimal Max Phaco chop
15° Low High Improved flowability
30° Balanced Balanced Most common, beginners
45° High Less Sculpting
60° Very high Minimal Rarely used
30°/60° Turbo — Hard nuclei
Most commonly used: 30°
B. KELMAN (BENT) TIP
• Distal bend → elliptical motion
• ↑ Cavitation + cutting efficiency
• Best for hard (Grade 4) nuclei
• Less wound stress → ergonomic
C. MICRO-TIP (21G)
• OD: 0.8 mm, ID: 0.6 mm
• Advantages:
o Smaller incision
o Better maneuverability
o Increased visibility
D. MACKOOL TIP (THERMAL SAFETY)
• Polyimide insulation (Microseal design)
• ↓ Heat transmission
• ↓ Thermal burns
• Available in: standard, micro, flared, ABS
E. FLARED TIP
• Proximal ID: 0.6 mm
• Distal ID: 0.9 mm
• Advantages:
o High vacuum with controlled flow
o Better hold + surge resistance
o Ideal for high vacuum chopping
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
91 | P a g e
drprabhatdevkota@gmail.com
F. ABS (Aspiration Bypass System) TIP
• Extra 0.18 mm side hole
• Continuous flow even during occlusion
• Advantages:
o ↓ Surge
o ↓ Heat
o Better chamber stability
G. MICRO-FLOW (BARRETT) TIP
• Longitudinal grooves
• Smaller internal diameter
• Advantages:
o Continuous cooling
o Surge resistance
H. OTHER TIPS (1-LINERS)
• Cobra tip – wider distal end, heats more
• Diaphragm tip – internal constriction → ↓ surge
• Turbosonics tip – hydrodynamically balanced
II. IRRIGATION–ASPIRATION HANDPIECES
A. COAXIAL I/A
• Single handpiece
• Aspiration port: 0.2–0.7 mm (0.3 mm common)
• Angulated (45°–90°) → subincisional cortex
B. BIMANUAL I/A
• Separate:
o Aspiration cannula
o Infusion cannula
• Advantages:
o Better access
o Microincision surgery
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
92 | P a g e
drprabhatdevkota@gmail.com
2. FOOT PEDAL
PEDAL POSITIONS
Position Function
P0 No function
P1 Irrigation
P2 Irrigation + Aspiration
P3 Irrigation + Aspiration + Phaco
FOOT GRADIENT (FG)
• Defines sensitivity of phaco power
• Lower max preset power → coarser control
SIDE KICK FUNCTIONS
• Reflux
• Continuous Infusion Mode (CIM)
• Bottle height control
• Pulse on/off
• Dual linear control (pitch + yaw)
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
93 | P a g e
drprabhatdevkota@gmail.com
PHACODYNAMICS
Study of interaction between:
• Fluidics
• Phaco power
• Surge
FLUIDICS
COMPONENTS
1. Irrigation
2. Aspiration
IRRIGATION SYSTEM
Conventional Phaco
• Coaxial sleeve
• Flow: 80–85 cc/min
• Bottle height: ~3 ft
• Maintains safe IOP (~16 mmHg clinically)
Micro-Phaco
• Separate irrigation (chopper)
• Flow: 40–45 cc/min
• Needs augmentation
METHODS TO INCREASE IRRIGATION (EXAM FAVORITE)
1. Increase bottle height
2. Air pump (fish pond pump)
3. AC Maintainer
4. Pressurized bottle
5. Mechanized infusion (Accurus, Millennium)
6. BP cuff pressurization
ASPIRATION SYSTEM
FUNCTIONS
• Flow (lavage)
• Vacuum (holding)
KEY TERMINOLOGY
• AFR – ml/min
• Vacuum – mmHg
• Rise time
• Occlusion
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
94 | P a g e
drprabhatdevkota@gmail.com
ZONES OF ASPIRATION
• Central Safe Zone (CSZ) – inside CCC
• Peripheral Unsafe Zone (PUSZ) – capsular fornices, angle
FLOWABILITY
• Depends on:
o Bottle height (+ pressure)
o Vacuum (− pressure)
• Better in:
o Venturi pumps
o Smaller nuclear fragments
TYPES OF ASPIRATION PUMPS
A. FLOW PUMPS
1. Peristaltic pump
o Controlled AFR
o Vacuum builds on occlusion
o Safer, beginner-friendly
o Disadvantage: surge (compliance)
2. Scroll pump
o Less compliance
o Less surge
o Better volumetric efficiency
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
95 | P a g e
drprabhatdevkota@gmail.com
B. VACUUM PUMPS
1. Venturi pump (MOST COMMON)
2. Diaphragmatic pump
3. Rotary vane pump
Venturi Pump – Key Points
• Instant vacuum
• Excellent flowability
• Higher PCR risk for beginners
• Less surge practically (pre-collapse tubing)
C. Hybrid & Specialized Pumps
• Dual-Pump System
o Combines Peristaltic + Venturi pumps in one console.
o Allows on-the-fly switching according to surgical step.
o Example: Johnson & Johnson WHITESTAR Signature Pro.
• SPEEP Pump
o Speed-controlled peristaltic pump (e.g., Oertli OS 4).
o Independent control of flow + vacuum limits.
o Combines:
▪ High hold-force → Venturi-like behavior
▪ Chamber stability & precision → Peristaltic-like behavior
o Key advantage: Enhanced control of flow, vacuum, and chamber stability.
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
96 | P a g e
drprabhatdevkota@gmail.com
Feature Peristaltic Pump Venturi Pump
Principle Flow-based Vacuum-based
Vacuum
generation
By occlusion/compression of tubing
Instantaneous vacuum generated
by the pump
Flow
Relatively constant until tubing
occlusion changes
Varies with vacuum level
Collection Soft bag Rigid cassette
Followability Less More
Best suited for Beginners / slow surgeons Experienced / fast surgeons
Portability More portable Less portable
PHACO POWER
Phaco Power= Frequency X Stroke Length
PARAMETERS
• Stroke length (2-6µ)
• Frequency (20-80 KHz)
MECHANISMS
1. Jackhammer effect
2. Cavitation
3. Acoustic wave
MODES OF PHACO POWER DELIVERY-- imp
Mode Key Feature Best Use
Continuous Constant power Sculpting
Pulse 50% duty cycle ↓ chatter
Burst Power fixed, interval variable Hard cataract
HyperPulse / Whitestar Duty <50%, up to 100 PPS Cold phaco
Power setting(Trenching) = Grade of nucleus X 15 +25
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
97 | P a g e
drprabhatdevkota@gmail.com
SURGE: Sudden chamber collapse due to occlusion break
CAUSES
• High vacuum
• High AFR
• Tubing compliance
SURGE CONTROL
MACHINE-BASED
• Rigid cassettes
• Software algorithms
• Venting (fluid > air)
• ABS tips
• Flared tips
• Cruise control
• Differential vacuum/AFR
SURGEON-BASED
• Proper wound (2.8–3 mm)
• Bottle height adjustment
• Reduce AFR / vacuum
• Foot pedal control
• Viscoelastic use
• Partial re-occlusion maneuver
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
98 | P a g e
drprabhatdevkota@gmail.com
PHACO– SURGICAL STEPS
PREOPERATIVE PREPARATION
Cleaning, Draping & Exposure
• Lid skin: 10% povidone iodine
• Conjunctival sac: 5% povidone iodine (≥2–3 min contact time)
• Draping: Sterile disposable drape
• Exposure: Universal eye speculum
#Exam pearl: Povidone iodine is the single most effective measure to prevent
endophthalmitis. (mcq)
SIDE PORT (PARACENTESIS) INCISION
Purposes
• Injection of OVD
• Capsulorhexis (cystitome/forceps)
• Globe stabilization
• Introduction of chopper / Sinskey hook
• Protection of posterior capsule
• Cortical I/A
Location
(Right-handed surgeon)
• Divide & conquer / central chop: → 3 clock hours from main incision
• Peripheral chop: → 2 clock hours from main incision
• Two side ports: → Second port 180° opposite first
Advantages of Two Side Ports
• Better AC stability
• Safer cortical aspiration
• Easier capsular polishing
• Less iris trauma
• Crushing of epinuclear fragments possible
Size
• 1–1.5 mm square tunnel
• Smaller for bimanual I/A
Technique
• Instrument: 15° blade / MVR
• Entry: Clear cornea, parallel to iris plane
• Counter-pressure: fixation ring / forceps
PG Notes: Lens & Cataract Dr. Prabhat Devkota, MD
99 | P a g e
drprabhatdevkota@gmail.com
Errors
Tunnel issue Problem
Too tight Corneal whitening, difficult entry
Too large Iris prolapse, unstable AC
MAIN PHACO INCISION (WOUND CONSTRUCTION)
CLEAR CORNEAL INCISION (m/c)
Types
• Triplanar (gold standard)
• Biplanar
• Uniplanar (expert only)
• Modified triplanar (very popular)
Triplanar Clear Corneal Incision
Components
1. External groove
o Depth: ~500 µm
o Length: 3–3.5 mm
2. Corneal tunnel
o Width: ~1.75 mm
3. Internal corneal entry
o 2.8–3.2 mm keratome
Advantages
• Excellent self-sealing valve
Disadvantages
• Slightly time-consuming
• Needs extra instruments
Modified Triplanar (Single Keratome)
1. Vertical stab
2. Horizontal tunnel
3. Internal entry parallel to iris plane
Most commonly practiced today