Skip to main content
Recommended
PPTX
DOCX
PPTX
An approach to diagnosis and management of Heart failure
DOCX
PPTX
Seminar presentation ON Heart Failure.pptx
PPTX
Acute_Heart_Failure_DR_RANJITH.pptx.....
PPT
HEART FAILURE-converted.ppt
PPT
PPT
Acute left ventricular failure
PPTX
Comprehensive Overview of Acute Heart Failure: Diagnosis and Management
PDF
5-HF PTh basics of 1st semestwr diploma.pdf
PPTX
CONGESTIVE HEART FAILURE recent guidelines.pptx
PPTX
Comprehensive Overview of Heart Failure: Causes, Symptoms, and Treatments
PPTX
heart failure PART-1.pptx
PDF
4- Heart failure medical dextboook .pdf
PPTX
N366 Module 1 PowerPoint 1 of 3 (1).pptx
PPTX
Comprehensive Overview of Heart Failure: Pathophysiology, Types, and Clinical...
PPTX
Congestive heart Failure by dr solome.pptx
PPTX
7. Cardiac Failure.pptxkkkkkkkkkkkkkkkkk
PPTX
PPTX
Examination of a patient with heart failure
PDF
Internal medicine Heart failure presentation .pdf
PPT
CONGESTIVE HEART FAILURE NOTES ....PPT.
PPTX
hf.pptx heart filure for nursing students
PPTX
PPTX
hypertensive hearth disease.....................................................
PPTX
hearth failure...........................................
PPTX
hearthb failure published nigerian nigerian nbjdbsu
PPTX
NURSING SKILLS AND FIRST AID.pptx..2025/
PPTX
Endocrine pharmacology- oral hypoglycaemics (1).pptx
More Related Content
PPTX
DOCX
PPTX
An approach to diagnosis and management of Heart failure
DOCX
PPTX
Seminar presentation ON Heart Failure.pptx
PPTX
Acute_Heart_Failure_DR_RANJITH.pptx.....
PPT
HEART FAILURE-converted.ppt
PPT
Similar to LEFT-SIDED HEART FAILURE-1.pptx...Myocardiac infarction
PPT
Acute left ventricular failure
PPTX
Comprehensive Overview of Acute Heart Failure: Diagnosis and Management
PDF
5-HF PTh basics of 1st semestwr diploma.pdf
PPTX
CONGESTIVE HEART FAILURE recent guidelines.pptx
PPTX
Comprehensive Overview of Heart Failure: Causes, Symptoms, and Treatments
PPTX
heart failure PART-1.pptx
PDF
4- Heart failure medical dextboook .pdf
PPTX
N366 Module 1 PowerPoint 1 of 3 (1).pptx
PPTX
Comprehensive Overview of Heart Failure: Pathophysiology, Types, and Clinical...
PPTX
Congestive heart Failure by dr solome.pptx
PPTX
7. Cardiac Failure.pptxkkkkkkkkkkkkkkkkk
PPTX
PPTX
Examination of a patient with heart failure
PDF
Internal medicine Heart failure presentation .pdf
PPT
CONGESTIVE HEART FAILURE NOTES ....PPT.
PPTX
hf.pptx heart filure for nursing students
PPTX
PPTX
hypertensive hearth disease.....................................................
PPTX
hearth failure...........................................
PPTX
hearthb failure published nigerian nigerian nbjdbsu
More from kamaubrian136
PPTX
NURSING SKILLS AND FIRST AID.pptx..2025/
PPTX
Endocrine pharmacology- oral hypoglycaemics (1).pptx
PPTX
ANTI-EPILEPTICS DRUGS- LECTURE 5 KANS.pptx
PPTX
ENDOCRINE PHARMACOLOGY- antiDiabetes.pptx
PPTX
C.N.S Pharmacology.pptx 2025 PRESENTATIONS
PPTX
DISORDERS OF THE CNS kiptoo-1.pptx 2025 MED
PPTX
NARSOGASTRIC FEEDING.pptx NURSING PROCESS
PPTX
LECTURE 3 IDENTIFYING & MEETING PATIENTS NEEDS (1).pptx
PPTX
End_of_Life_Care_Presentation_FINAL.pptx
PPTX
HISTORY OF THE NURSING PROFESSION 2024.pptx
PPTX
nursing position 2025.PPTX NURSING SKILLS
PPTX
Chemical Senses, EYE,EAR,TONGUE ANATS.PPT
PPT
cell-injury-and-adaptations-Ippt general
Recently uploaded
PPTX
Comprehensive Guide to Microsoft PowerPoint Features and Usage for nurses
PPTX
Agni nivara PPT template for smart agriculture.pptx
PPT
Object Oriented Programming in C++ with Classes and Objects
PDF
Introduction to Databases,E-R model and Relational Model U1
PPTX
Making First Impression by Sandeep K Sharma
PDF
The Atmosphere: An Introduction to Meteorology, 14th Edition pdf
PDF
Comprehensive Overview of Artificial Intelligence Fundamentals and Applications
PDF
TTP, TN, FP, FN are the foundation for understanding accuracy, precision, rec...
PDF
Informed Search Strategies in Artificial Intelligence: Heuristics, Algorithms...
PDF
Comprehensive Guide to DepEd's ILAW Framework for Effective Lesson Planning
PPTX
Comprehensive Overview of UNESCO World Heritage Convention and India's Role i...
PPTX
Shemushi Halloween Quiz Night 2025(PPTX)
PPTX
EFFECTIVE COMMUNICATION- NON VERBAL STRATEGIES.pptx
PPTX
Religious_Secular_Architecture of Ancient India
PDF
Syllabus of Object Oriented Programming with C++
PDF
Comprehensive Lesson Exemplar on Louis Pasteur's Contributions in General Sci...
PDF
Comprehensive material on Protected cultivation and post-harvest technologies
PDF
Game-Based Learning (RPGBL), Task-Based Language Teaching (TBLT), and generat...
PPTX
Design Principles, Elements, and Tools for Effective Manipulative-Based Prese...
PPTX
Comprehensive Guide to UNESCO World Heritage Sites and Criteria for Selection
LEFT-SIDED HEART FAILURE-1.pptx...Myocardiac infarction 1. 2. 3. Definition:
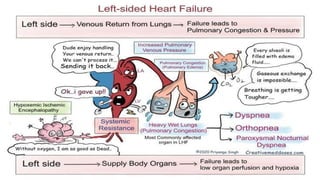
LSHF occurs when the left ventricle of the heart fails to pump
blood effectively into systemic circulation.
As a result, blood backs up inti the lungs, causing pulmonary
congestion and reduced oxygenation of blood.
3
4. Etiology:
1. Ischemic Heart Diseases [IHD] (e.g. myocardial infarction.)
2. Hypertension – increases afterload, straining the left ventricle.
3. Aortic Valve Diseases [AVD] (e.g. aortic stenosis or
regurgitation.)
4. Mitral Valve Diseases [MVD] (e.g. mitral regurgitation.)
5. Cardiomyopathies (e.g. dilated cardiomyopathy.)
4
5. Pathophysiology:
When the left ventricle fails:
• It cannot eject blood efficiently leading to reduced cardiac
output.
• Blood accumulates in the left atrium and then in the pulmonary
veins causing increased pulmonary venous pressure.
• This leads to pulmonary congestion and edema.
The Kidney responds to the low cardiac output by activating the
RAAS leading to fluid retention, worsening the congestion.
5
6. 7. Clinical Manifestation:
Symptoms:
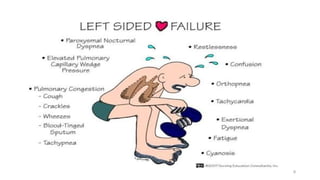
• Dyspnea initially on exertion, later at rest.
• Orthopnea.
• Paroxysmal Nocturnal Dyspnea [PND].
• Fatigue and exercise intolerance (due to tissue hypoperfusion.)
• Cough (often productive of frothy sputum – sometimes blood
tinged)
7
8. Clinical Manifestation:
Signs:
• Tachypnea.
• Fine crackles(crepitations) heard at lung bases (due to
pulmonary edema.)
• S3 gallop rhythm (from increased ventricular filling pressure.)
• Cool extremities and weak pulse (poor peripheral perfusion.)
• Cyanosis (in severe cases)
8
9. 10. Complications:
1. Pulmonary edema.
2. Right-Sided Heart Failure (if prolonged) due to increased
pulmonary pressure.
3. Renal impairment (from poor perfusion.)
4. Arrhythmias (due to myocardial strain or ischemia.)
10
11. 12. Management:
Pharmacological:
1. Diuretics (e.g. furosemide) – reduce pulmonary congestion.
2. ACE inhibitors/ ARBs – reduce afterload and prevent
remodeling.
3. Beta-blockers – reduce myocardial oxygen demand improving
survival.
4. Aldosterone antagonist (e.g. spironolactone.)
5. Vasodilators – for afterload reduction.
12
13. 14. Difference from Right-Sided Heart Failure.
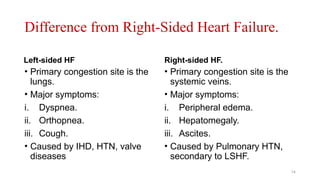
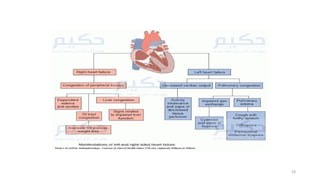
Left-sided HF
• Primary congestion site is the
lungs.
• Major symptoms:
i. Dyspnea.
ii. Orthopnea.
iii. Cough.
• Caused by IHD, HTN, valve
diseases
Right-sided HF.
• Primary congestion site is the
systemic veins.
• Major symptoms:
i. Peripheral edema.
ii. Hepatomegaly.
iii. Ascites.
• Caused by Pulmonary HTN,
secondary to LSHF.
14
15. 16. 17. 18.