OBJECTIVES
By theend of the study the student
will be able to:
Define nursing process
Describe the steps of nursing
process
Describe the utilization of the
nursing process in identifying and
meeting patients needs
3.
Nursing Process:
Foundation forPractice
What is the “Nursing Process”?
It is a systematic method that directs the
nurse and patient in planning and
delivering nursing care
It is patient centered and outcome
oriented
The steps are interrelated and
dependent on the accuracy of each of
the preceding steps
4.
It isused to identify, diagnose, and treat
human responses to health and illness
It is a dynamic continuous process
Using the nursing process promote
individualized nursing care
It is an approach that allows nurses to
differentiate their practice from that of
physicians and other health professionals
5.
Together the nurseand the
patient accomplish the following:
Assess the patient to determine need
for nursing care
Determine nursing diagnoses for actual
and potential health problems
Identify expected out comes and plan
care
Implement care
Evaluate the results
6.
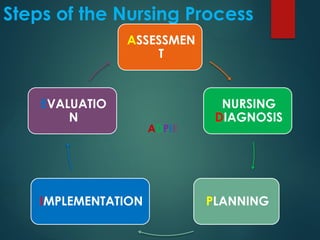
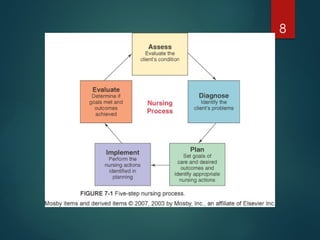
Steps of theNursing
Process
Assessment – collection of patient data
Diagnosis – identifies patients strengths and
potential problems
Planning – develop the specific holistic
desired goals and nursing interventions to
assist the patient
Implementation – carry out the plan of care
Evaluation – determine the effectiveness of
the plan of care
7.
Steps of theNursing Process
ASSESSMEN
T
NURSING
DIAGNOSIS
PLANNING
IMPLEMENTATION
EVALUATIO
N
ADPIE
Assessment: Phase Oneof
the Nursing Process
Purpose:
Establish a baseline of information on the
client and develop a data base
Determine client’s normal function
Determine client’s risk for dysfunction
Determine presence or absence of
dysfunction
Determine client’s strengths
Provide data for diagnostic phase
10.
Unique Focus ofNursing
Assessment
Nursing assessments do not
duplicate medical assessments
Medical assessments target data
pointing to pathologic conditions
Nursing assessments focus on the
patient’s responses to health
problems or potential health
problems
11.
Assessment
The purposeis to establish a database by:
Collecting data
Subjective versus objective
Interviewing and taking a health history
Subjective and organized
Performing a physical examination
Vital signs, patient’s behavior, diagnostic
and laboratory data, medical records
12.
As youdevelop your skills and gain
more expertise in the care and
understanding of disease processes
the planning of care and interview
process will become easier
You will learn what is abnormal
after much practice with the
normal
13.
Approaches for Data
Collection
Gordon’s 11 Functional Health Patterns
Uses a series of questions which assist in formulating
a nursing diagnosis
Problem focused assessment
Focuses on the patient’s problem and develop your
plan of care around the problem
Either of these methods allow for clustering of cues
and inferences which give rise to patterns or potential
problems
Cues – information obtained through the use of senses
Inference – judgment or interpretation of cues
Assessment
• The nurse;collects, organizes, validates
and records data on the client’s health
status.
The nurse also Identifies current and
potential problems as well as the client’s
potential for achieving optimal well-being.
A vital step because all other steps
depend on assessment.
16.
Assessment
Collect data– using signs and symptoms, physical exam
and diagnostic tests from the client or others.
Organize data – using nursing models (Orem’s self-care
theory) and non-nursing models (Maslow’s hierarchy of
needs)
Validate data – check for accuracy of data
Document data – record client’s data in an organized
factual manner.
17.
17
Types of Data
Subjective Data
Information perceived only by
the affected person
Cannot be perceived or verified
by another person
Examples: feeling nervous,
nauseated, chilly, complains of
headaches
18.
18
Types of Data
Objective Data
Observable and measurable data
Data that can be seen, heard or
felt by someone other than the
person experiencing it
Examples: elevated temperature of
38o
c, moist skin, refusal to eat,
tachycardia, sweating, vomiting,
emaciation
20
Sources of Data
Primary
patient
Secondary
Family members
Significant other
Other healthcare professionals
Health records
21.
21
Components of Data
Collection
Nursing History
Biographical information (demographical
history)
Reasons for seeking healthcare
Present illness or health concern
Past Health history
Environmental history
Psychosocial and cultural history
Review of systems or functional health
patterns
23
Diagnosis: Phase 2of the
Nursing Process
Looking at the data, we can see
both problems treated by nursing
(nursing diagnosis) and treated by
other disciplines (collaborative
problems).
Nursing diagnosis are not medical
diagnosis
24.
24
Purpose of aNursing
Diagnosis
1. Identify how an individual, group or community
responds to an actual or potential health and life
processes
2. Identify factors that contribute to or cause health
problems (etiology).
3. Identify resources or strengths the individual, group
or community can utilize to prevent or resolve
problems
25.
25
Health Problem
Acondition that necessitates intervention to
prevent or resolve the disease or illness or to
promote coping and wellness
After the data is collected and recorded, the
nurse interprets and analyzes the data to identify
strengths and health problems
26.
26
Health Problems forNursing
Focus
Monitoring for changes in health status
Promoting safety and preventing harm
Identifying and meeting learning needs
Tailoring treatment and medication regimens for
each individual
Nurses should focus on certain types of health
problems to better understand their responsibilities
in diagnosis and management of health problems
27.
27
Health Problems forNursing
Focus
Promoting comfort and managing pain
Promoting health and a sense of well being
Recognizing and addressing barriers to an
independent, healthy lifestyles
Determining human responses
28.
28
Nursing Diagnosis
Aclinical judgment about individual, family, or
community responses to actual and potential
health problems or life processes
The goal of a nursing diagnosis is to identify actual
and potential responses
29.
29
Nursing Diagnosis
Actualor potential health problems that can be
prevented or resolved by independent nursing
interventions
30.
30
Nursing Diagnosis
Nursingdiagnoses provide the basis for selecting
nursing interventions that will achieve valued
patient outcomes for which the nurse is
responsible
31.
31
NANDA
NANDA: NorthAmerican Nursing
Diagnosis Association
Established in 1973 to identify standards
and classify health problems treated by
nurses
NANDA conferences are held every two
years to continue progress in defining,
classifying and describing diagnoses
32.
32
Nursing Diagnosis
Clinicaljudgment about individual,
family or community Response to
actual or potential health or life
process
Provides basis for nursing
interventions
Label and action of describing
functional problems
Identify and synthesize information
gathered during assessment
33.
33
Nursing Diagnosis vs.
MedicalDiagnosis
Medical diagnosis
Identify disease
Nursing diagnosis
Focus on unhealthy response to health or
illness
Medical diagnosis
Physician directs treatment
Nursing diagnosis
Nurse treats problem within scope of
independent nursing practice
34.
34
Nursing Diagnosis vs.Medical
Diagnosis
Medical Diagnosis
Remains the same as long as the
disease is present
Nursing Diagnosis
May change from day to day as
the patient’s responses change
36
Development of Nursing
Diagnosis
Assess the patient
Review data and find actual and potential
problems
Use diagnostic reasoning to identify patient
needs
Arrange data in clusters or defining
characteristics
Use all data available
Reach conclusions for patient needs
Determine Nursing Diagnosis according to
NANDA approved diagnoses
37.
37
Development of Nursing
Diagnosis
Assess the patient
Review data and find actual and potential
problems
Use diagnostic reasoning to identify patient
needs
Arrange data in clusters or defining
characteristics
Use all data available
Reach conclusions for patient needs
Determine Nursing Diagnosis according to
NANDA approved diagnoses
38.
Components of NursingDiagnosis
The Problem ( defining characteristics)
Name of the nursing diagnosis as listed in the
North American Nursing Diagnosis
Association (NANDA) taxonomy
The Etiology - Describes factors causing or
contributing to the problem
The term ‘Related to’ - Connects the two
parts of the statement
39.
We willwrite the ND in one, two or
three parts:
diagnosis
related to - etiology
as evidenced by – data
collected
40.
Types of NursingDiagnosis
Actual: Occurring “here & now”. A
problem currently present; manifested by
signs and symptoms.
Risk: Altered state which may occur unless
specific nursing actions are implemented.
Validated by risk factors.
Possible: A problem which may exist, but
additional data is needed to confirm its
presence
41.
Statements
Nursing diagnostic statementscan be;
• One part statements - these only describe the
health status diagnosed. E.G. “Potential for
airway obstruction”
• Two part statements – these describe the health
status diagnosed and the related factors. E.G.
“Risk for impaired skin integrity related to
immobility”
• Three part statements – these describe the
health status diagnosed, the related factors and
the signs/ symptoms present.”
42.
• E.G. “Ineffectivebreathing pattern
related to pulmonary infection as
manifested by dyspnoea”.
• “Impaired tissue oxygenation
related to airway obstruction as
evidenced by cyanosis
43.
Actual nursing diagnosis:represents a
problem that has been validated by the
presence of major defining characteristics
Has three parts
Risk nursing diagnosis
clinical judgments that an individual,
family or community is more vulnerable to
develop the problem than others in the
same or similar situations
Has two parts
44.
44
What a NursingDiagnosis
is Not
A nursing diagnosis is NOT a
medical diagnosis
A nursing diagnosis is NOT a
statement of patient need
EXAMPLE: needs assistance with
bathing
INSTEAD: self care deficit: bathing
and hygiene related to immobility
45.
45
Legal Ramifications of
NursingDiagnosis
A nurse
Can only identify problems
within the scope of practice
Cannot diagnose or treat
medical disease
Must identify problems within
his/her scope of practice,
abilities and education
46.
Planning
Based onnursing assessment and diagnosis.
Prescribes nursing interventions to attain
expected outcomes.
Outcomes/goals / objectives must be SMART
Includes;
Setting priorities
Establishing expected outcomes and goals
Planning nursing actions and rationale
Documentation of these as the Nursing Care
Plan.
47.
Implementation
Intervention phase
This stage is independent as well as collaborative
Skills required – cognitive, interpersonal and
psychomotor
Continue to assess, validate concerns, modify the
plan and identify priorities as needed
Document time every intervention done, patient’s
response & any other pertinent information
48.
Evaluation
Evaluate patientsprogress towards attainment of
expected outcome/feedback
Compare set goals with patient’s response
Record findings in terms of how well goals were
met
49.
Benefits of theNursing Process
Gives framework to use in patient care
Promotes efficiency & effectiveness
Facilitates standardization of nursing
practice
Promotes continuity, accountability and
prevents duplication of care
Ensures quality, individualized care and
encourages client participation
50.
Benefits of theNursing Process
Promotes job satisfaction and enhances
professional growth
Defines scope of nursing practice and
contributes to profession’s autonomy
Defines the nursing role in provision of
comprehensive patient care
Editor's Notes
#25 After the data is collected and recorded, the nurse interprets an analyzes the data to identify strengths and health problems
#33 Initially, nursing diagnosis was confused with medical diagnosis sparking controversy