Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 1
LABOUR ROOM & MATERNITY
EXCELLENCE MANUAL
Global Standards for Safe Childbirth, Respectful Maternity Care, and Quality Healthcare
A Comprehensive Reference for
THE MULTIDISCIPLINARY LABOUR ROOM & MATERNITY TEAM
Obstetricians • Midwives & Labour Room Nurses • Neonatal Resuscitation Teams • Anesthesiologists & Allied
Maternity Care Professionals
“Two Lives Enter the Labour Room and Two Lives Must Leave It Safely — Every Contraction
Watched, Every Complication Anticipated, Every Mother and Newborn Protected.”
Dr J L Meena
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 2
DEDICATION
This book is dedicated to all those who are committed to advancing healthcare through vigilance, tenderness,
technical mastery, and the profound responsibility of caring for two lives at once.
To Every Mother
For whom every partograph plotted on time, every early sign of haemorrhage caught before it became a crisis,
and every moment of dignity preserved during the most vulnerable hours of her life represents a promise that
childbirth, however uncertain nature makes it, will be met with unwavering readiness.
To Every Newborn
For whom the first breath, the first cry, and the first moment of skin-to-skin contact depend entirely on a team
trained to act within seconds when those things do not happen on their own.
To My Family
For their unwavering love, patience, and encouragement, which have been the foundation of this journey.
To My Mentors & Teachers
For inspiring my passion, guiding my path, and instilling in me the value of vigilance, technical precision, and
genuine compassion for the mother facing labour's uncertainty.
To My Colleagues & Friends
For their support, collaboration, and shared dedication to a labour room where two lives are always protected,
never merely one at the expense of the other.
To Every Member of the Labour Room and Maternity Team
Obstetricians, midwives, labour room nurses, neonatal resuscitation teams, and every professional who
answers the call of a mother in labour, day or night — the guardians of the single moment where life itself
begins, and where readiness must never, even once, be found wanting.
Your vigilance, your technical mastery, and your tenderness toward mother and newborn alike are the
silent pillars of a healthcare system that keeps its oldest and most sacred promise: that new life will be
brought into the world safely. This book is for you, and because of you. Thank you to everyone who has
been a part of this journey.
Dr J L Meena
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 3
FOREWORD
There is no other clinical encounter in medicine where two lives depend, simultaneously and inseparably, on
the vigilance of a single team. A labouring mother's blood pressure rising silently toward eclampsia. A foetal
heart rate pattern shifting in a way that, unaddressed for even twenty minutes, could mean the difference
between a healthy newborn and a lifetime of disability. A third stage of labour that turns, in the span of
minutes, from routine to a haemorrhage that can claim a mother's life before the blood bank can even be
reached. Childbirth is, for the overwhelming majority of mothers, one of the safest and most joyful moments
of their lives — and it remains so only because a trained team stands ready, continuously, to recognize the rare
moment when it is not.
The “Labour Room & Maternity Excellence Manual: Global Standards for Safe Childbirth, Respectful Maternity
Care, and Quality Healthcare” has been developed to provide a comprehensive professional framework for the
multidisciplinary Labour Room and Maternity team — obstetricians, midwives and labour room nurses,
neonatal resuscitation teams, anesthesiologists, and allied maternity care professionals — working together to
protect two lives at once, from the first contraction through the critical hours following birth.
This manual brings together internationally recognized principles of partograph-based labour monitoring, the
WHO Safe Childbirth Checklist, active management of the third stage of labour, obstetric emergency response
(postpartum haemorrhage, eclampsia, shoulder dystocia, cord prolapse), maternal early warning systems,
essential and resuscitative newborn care, respectful maternity care, and continuous quality improvement
specific to labour and delivery. It is built around globally accepted accreditation frameworks — WHO Standards
for Improving Quality of Maternal and Newborn Care, NABH, JCI, FOGSI/RCOG/ACOG guidelines, and national
initiatives such as India's LaQshya and MusQan programmes — to provide a rigorous, regulation-compliant
framework for labour room and maternity excellence.
The chapters of this manual guide the Labour Room and Maternity team through every dimension of the role
— from admission assessment and partograph-based monitoring, through the active management of labour
and delivery, to obstetric emergency response, newborn resuscitation, and the professional conduct that
defines excellence across every category of childbirth: normal, high-risk, operative, and emergency.
The Labour Room is not simply a delivery suite — it is the place where healthcare's most fundamental promise
is kept or broken: that a mother who enters in labour, and the child she carries, will both leave safely. Their
work is defined by a discipline unlike any other in medicine — the continuous, simultaneous vigilance over two
patients whose wellbeing cannot be separated, where warning signs must be caught not eventually, but within
minutes, and where readiness for the rare catastrophic complication must never lapse, even during the most
routine, uneventful shift.
It is hoped that this manual will serve as an indispensable resource for Obstetricians, Midwives, Labour Room
Nurses, Neonatal Resuscitation Teams, hospital administrators, quality heads, and all those committed to
building a healthcare system where childbirth is attended with the vigilance, technical precision, dignity, and
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 4
compassion that the safe arrival of every new life, and the safety of every mother who brings it into the world,
demands.
“Two Lives Enter the Labour Room and Two Lives Must Leave It Safely — Every Contraction Watched,
Every Complication Anticipated, Every Mother and Newborn Protected.”
With Best Wishes, Dr J L Meena
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 5
TABLE OF CONTENTS
FOREWORD............................................................................................................................................3
LIST OF ABBREVIATIONS........................................................................................................................7
MANUAL MOTTO...................................................................................................................................9
CHAPTER 1: Introduction.....................................................................................................................10
Purpose...........................................................................................................................................................10
Objectives .......................................................................................................................................................11
Vision & Mission .............................................................................................................................................13
CHAPTER 2: Role of the Labour Room & Maternity Team in Quality Healthcare..............................14
Admission Assessment & Risk Stratification...................................................................................................14
Partograph-Based Labour Monitoring............................................................................................................14
Active Management of the Third Stage of Labour..........................................................................................15
Obstetric Emergency Recognition & Response ..............................................................................................15
Essential & Resuscitative Newborn Care ........................................................................................................16
Maternal Early Warning Systems....................................................................................................................16
Respectful Maternity Care & Birth Companion Support ................................................................................17
Postnatal Care, Breastfeeding & Referral Coordination.................................................................................17
CHAPTER 3: Professional Standards for the Labour Room & Maternity Team..................................18
Professional Appearance & Behaviour ...........................................................................................................18
Communication Standards .............................................................................................................................19
Confidentiality & Information Security...........................................................................................................20
Ethical Standards ............................................................................................................................................20
Time Management, Teamwork & Continuous Learning.................................................................................21
CHAPTER 4: Patient- and Family-Centered Communication in the Labour Room.............................22
The A-T-C-R-C Communication Model............................................................................................................22
Communicating Complications & Respectful Maternity Care ........................................................................23
CHAPTER 5: Patient Safety and Maternal-Newborn Care Standards.................................................25
The R-T-A-C-A Framework ..............................................................................................................................25
Daily Quality Standards Checklist ...................................................................................................................27
CHAPTER 6: Confidentiality, Privacy, and Information Security ........................................................29
Privacy and Dignity in the Labour Room.........................................................................................................29
Cybersecurity of Maternal-Newborn Information Systems............................................................................30
CHAPTER 7: Standard Operating Procedures (SOPs)..........................................................................32
SOP 1: Labour Admission Assessment and Risk Stratification ........................................................................32
SOP 2: Partograph Monitoring and Labour Progress Assessment..................................................................32
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 6
SOP 3: WHO Safe Childbirth Checklist Application .........................................................................................33
SOP 4: Active Management of the Third Stage of Labour (AMTSL)................................................................33
SOP 5: Postpartum Haemorrhage Recognition and Management .................................................................34
SOP 6: Hypertensive Disorders and Eclampsia Management.........................................................................34
SOP 7: Shoulder Dystocia and Cord Prolapse Response.................................................................................35
SOP 8: Newborn Resuscitation .......................................................................................................................35
SOP 9: Maternal Referral and Interfacility Transfer........................................................................................36
SOP 10: Maternal and Perinatal Death Review ..............................................................................................36
CHAPTER 8: Communication with Special Groups..............................................................................37
CHAPTER 9: Handling Difficult Situations ...........................................................................................40
CHAPTER 10: Emergency Response — Critical Obstetric and Newborn Presentations.....................44
CHAPTER 11: Digital Competency for the Labour Room & Maternity Team .....................................48
CHAPTER 12: Daily Labour Room & Maternity Checklist....................................................................50
CHAPTER 13: Key Performance Indicators (KPIs)................................................................................52
CHAPTER 14: Top 20 Do's & Top 20 Don'ts.........................................................................................55
CHAPTER 15: Labour Room & Maternity Professional Pledge ...........................................................58
CONCLUSION........................................................................................................................................62
REFERENCES.........................................................................................................................................65
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 7
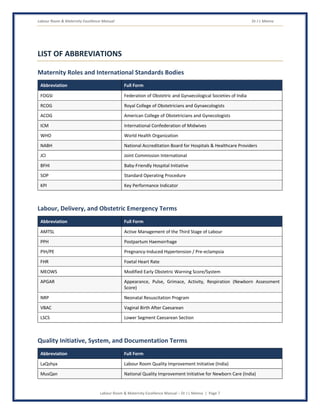
LIST OF ABBREVIATIONS
Maternity Roles and International Standards Bodies
Abbreviation Full Form
FOGSI Federation of Obstetric and Gynaecological Societies of India
RCOG Royal College of Obstetricians and Gynaecologists
ACOG American College of Obstetricians and Gynecologists
ICM International Confederation of Midwives
WHO World Health Organization
NABH National Accreditation Board for Hospitals & Healthcare Providers
JCI Joint Commission International
BFHI Baby-Friendly Hospital Initiative
SOP Standard Operating Procedure
KPI Key Performance Indicator
Labour, Delivery, and Obstetric Emergency Terms
Abbreviation Full Form
AMTSL Active Management of the Third Stage of Labour
PPH Postpartum Haemorrhage
PIH/PE Pregnancy-Induced Hypertension / Pre-eclampsia
FHR Foetal Heart Rate
MEOWS Modified Early Obstetric Warning Score/System
APGAR Appearance, Pulse, Grimace, Activity, Respiration (Newborn Assessment
Score)
NRP Neonatal Resuscitation Program
VBAC Vaginal Birth After Caesarean
LSCS Lower Segment Caesarean Section
Quality Initiative, System, and Documentation Terms
Abbreviation Full Form
LaQshya Labour Room Quality Improvement Initiative (India)
MusQan National Quality Improvement Initiative for Newborn Care (India)
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 8
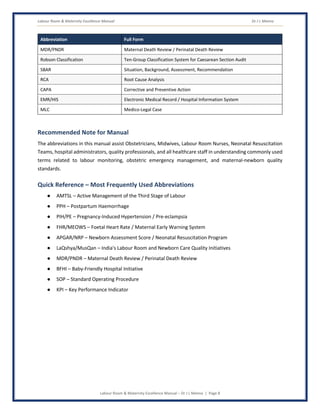
Abbreviation Full Form
MDR/PNDR Maternal Death Review / Perinatal Death Review
Robson Classification Ten-Group Classification System for Caesarean Section Audit
SBAR Situation, Background, Assessment, Recommendation
RCA Root Cause Analysis
CAPA Corrective and Preventive Action
EMR/HIS Electronic Medical Record / Hospital Information System
MLC Medico-Legal Case
Recommended Note for Manual
The abbreviations in this manual assist Obstetricians, Midwives, Labour Room Nurses, Neonatal Resuscitation
Teams, hospital administrators, quality professionals, and all healthcare staff in understanding commonly used
terms related to labour monitoring, obstetric emergency management, and maternal-newborn quality
standards.
Quick Reference – Most Frequently Used Abbreviations
● AMTSL – Active Management of the Third Stage of Labour
● PPH – Postpartum Haemorrhage
● PIH/PE – Pregnancy-Induced Hypertension / Pre-eclampsia
● FHR/MEOWS – Foetal Heart Rate / Maternal Early Warning System
● APGAR/NRP – Newborn Assessment Score / Neonatal Resuscitation Program
● LaQshya/MusQan – India's Labour Room and Newborn Care Quality Initiatives
● MDR/PNDR – Maternal Death Review / Perinatal Death Review
● BFHI – Baby-Friendly Hospital Initiative
● SOP – Standard Operating Procedure
● KPI – Key Performance Indicator
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 9
MANUAL MOTTO
“Two Lives Enter the Labour Room”
“And Two Lives Must Leave It Safely —”
“Every Contraction Watched, Every Complication Anticipated.”
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 10
CHAPTER 1: INTRODUCTION
1. Purpose
No other clinical encounter in medicine asks a team to hold two lives in continuous, simultaneous vigilance the
way the Labour Room does. The mother whose blood pressure is climbing silently toward a seizure. The foetal
heart rate pattern shifting in a way that, left unaddressed, will cause the very brain injury a caesarean section
performed twenty minutes sooner would have prevented. The third stage of labour that turns, without
warning, from a routine delivery into haemorrhagic shock. For the overwhelming majority of mothers,
childbirth is safe, natural, and joyful — and it remains so specifically because a trained team stands ready,
continuously, to recognize the rare moment when it is not, and to act within the minutes that recognition
allows.
The World Health Organization and the Federation of Obstetric and Gynaecological Societies (FOGSI), alongside
RCOG and ACOG globally, recognize that partograph-based labour monitoring, active management of the third
stage of labour, and disciplined obstetric emergency response protocols are directly and measurably linked to
reductions in maternal and perinatal mortality — among the most powerful, evidence-based interventions
available in all of healthcare. Research consistently demonstrates that facilities applying the WHO Safe
Childbirth Checklist, structured partograph monitoring, and rehearsed emergency response to postpartum
haemorrhage and eclampsia achieve dramatically and measurably lower maternal and newborn mortality than
facilities relying on unstructured, ad hoc labour management. In institutions where the Labour Room and
Maternity team applies rigorous, systematic monitoring and rehearsed emergency response, maternal and
newborn survival are demonstrably and measurably better. The investment in Labour Room excellence is,
without qualification, one of the highest-yield investments any healthcare system can make — protecting not
one life, but two, at the very moment life begins.
Why the Labour Room & Maternity Team Is Critical to Healthcare Quality
● Provides continuous, simultaneous monitoring of two patients — mother and foetus/newborn —
whose safety cannot be separated.
● Applies systematic partograph-based monitoring that identifies prolonged or obstructed labour before
it becomes catastrophic.
● Delivers active management of the third stage of labour, the single most effective intervention in
preventing postpartum haemorrhage.
● Maintains rehearsed readiness for obstetric emergencies (haemorrhage, eclampsia, shoulder dystocia,
cord prolapse) where minutes determine survival.
● Provides immediate, skilled newborn resuscitation for the newborn who does not breathe
spontaneously at birth.
● Applies maternal early warning systems that catch physiological deterioration before it becomes a
crisis.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 11
● Delivers respectful maternity care that preserves the dignity, autonomy, and emotional wellbeing of
every labouring woman.
● Maintains regulatory compliance with national maternal-newborn care standards and international
accreditation guidelines.
● Contributes to accreditation compliance (NABH, JCI, LaQshya, MusQan) for labour room and maternity
care standards.
Key Responsibilities of the Labour Room & Maternity Team
● Conducting systematic admission assessment and risk stratification for every labouring woman.
● Maintaining partograph-based monitoring throughout the active phase of labour.
● Applying the WHO Safe Childbirth Checklist at every critical pause point during labour and delivery.
● Performing active management of the third stage of labour for every delivery.
● Recognizing and responding immediately to obstetric emergencies (PPH, eclampsia, shoulder dystocia,
cord prolapse).
● Providing immediate essential newborn care and, where needed, skilled neonatal resuscitation.
● Applying maternal early warning score systems to detect deterioration proactively.
● Coordinating safe, timely referral and interfacility transfer for high-risk or complicated cases.
● Supporting breastfeeding initiation and Baby-Friendly Hospital Initiative practices.
● Engaging in continuous professional development to maintain competence in evolving obstetric and
newborn care evidence.
2. Objectives
1. Ensure Systematic, Continuous Monitoring of Every Labouring Woman
Every mother in labour must be monitored systematically, using validated tools, so that deviation from normal
progress or physiology is caught early. This is the Labour Room's primary patient safety obligation.
How to Achieve:
● Apply partograph monitoring consistently from the active phase of labour onward.
● Apply maternal early warning score systems at defined intervals throughout labour and the
postpartum period.
● Apply continuous or intermittent foetal heart rate monitoring appropriate to risk classification.
2. Prevent and Manage Postpartum Haemorrhage Proactively
● Apply active management of the third stage of labour for every delivery, without exception.
● Maintain immediate readiness (medication, blood products, skilled personnel) for postpartum
haemorrhage response.
● Apply structured, stepwise escalation protocols for haemorrhage that does not respond to first-line
measures.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 12
3. Recognize and Respond to Obstetric Emergencies Immediately
● Maintain rehearsed, drilled response protocols for eclampsia, shoulder dystocia, and cord prolapse.
● Apply the WHO Safe Childbirth Checklist to ensure critical safety steps are never omitted.
● Escalate immediately any deviation from normal maternal or foetal physiology.
4. Provide Immediate, Skilled Newborn Care
● Ensure a team member trained in newborn resuscitation is present at every delivery.
● Apply essential newborn care practices (thermal care, early breastfeeding, cord care) for every birth.
● Apply Neonatal Resuscitation Program (NRP) protocols immediately for the newborn who does not
breathe spontaneously.
5. Deliver Respectful, Dignified Maternity Care
● Support birth companion presence and informed choice throughout labour.
● Communicate honestly and compassionately with every mother and family.
● Protect privacy and dignity throughout labour, delivery, and the postpartum period.
6. Maintain Regulatory and Accreditation Compliance
● Comply with national maternal-newborn care standards and international accreditation guidelines.
● Maintain NABH/JCI and, where applicable, LaQshya/MusQan documentation standards.
● Participate in accreditation surveys with complete, auditable labour room and maternity records.
3. Vision
Vision Statement
“To build and maintain a Labour Room and Maternity service where every mother is monitored systematically,
every complication is anticipated and rehearsed for, every newborn receives immediate skilled care, and no
mother or newborn is ever harmed by a preventable delay, missed warning sign, or lapse in readiness.”
4. Mission
Mission Statement
“To deliver safe, respectful, evidence-based, and continuously vigilant maternity care that protects both
mother and newborn from harm through systematic monitoring, active management of labour, and rehearsed
obstetric emergency response, while maintaining regulatory compliance and enabling the healthcare
organization to provide quality maternity care with confidence in its readiness for two lives, at the moment life
begins.”
Expected Outcomes of an Excellent Labour Room & Maternity Practice
● 100% of labouring women monitored using partograph from the active phase of labour.
● Active management of the third stage of labour applied for 100% of deliveries.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 13
● WHO Safe Childbirth Checklist applied and documented at every critical pause point.
● Postpartum haemorrhage and eclampsia response protocols tested and drilled per regular schedule.
● A skilled newborn resuscitation provider present at 100% of deliveries.
● Complete, accurate, and NABH/JCI/LaQshya-compliant maternal-newborn documentation.
● All maternal deaths and significant perinatal complications reviewed through maternal/perinatal
death review with documented CAPA.
● Full compliance with national maternal-newborn care standards and international accreditation
guidelines.
The Labour Room and Maternity team holds a responsibility unlike any other in medicine — continuous,
simultaneous vigilance over two lives whose safety cannot be separated. Their partograph monitoring is a
deterioration-detection system, their active management of the third stage of labour is the single most
powerful haemorrhage-prevention tool available, and their rehearsed emergency readiness is what stands
between childbirth's overwhelming safety and the rare catastrophic complication that demands action
within minutes.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 14
CHAPTER 2: ROLE OF THE LABOUR ROOM & MATERNITY TEAM IN
QUALITY HEALTHCARE
1. Admission Assessment and Risk Stratification
Overview
Accurate admission assessment and risk stratification determine the entire trajectory of care a labouring
woman will receive — identifying high-risk pregnancies requiring heightened vigilance from the moment of
arrival.
Responsibilities
● Conduct systematic history, examination, and risk factor assessment for every woman admitted in
labour.
● Apply validated risk stratification criteria to identify high-risk pregnancies requiring escalated
monitoring.
● Confirm gestational age, foetal presentation, and estimated foetal weight on admission.
● Document baseline maternal and foetal parameters accurately at admission.
2. Partograph-Based Labour Monitoring
Overview
The partograph is the single most validated tool for detecting abnormal labour progress before it becomes
obstructed labour, a leading cause of preventable maternal and perinatal morbidity worldwide.
Responsibilities
● Plot cervical dilatation, descent, and maternal/foetal vital signs on the partograph systematically from
the active phase of labour.
● Recognize and act immediately when labour progress crosses the alert or action line.
● Apply intermittent or continuous foetal heart rate monitoring appropriate to risk classification.
3. Active Management of the Third Stage of Labour
Overview
Active management of the third stage of labour — prophylactic uterotonic administration, controlled cord
traction, and uterine massage — is the single most effective, evidence-based intervention in preventing
postpartum haemorrhage.
Responsibilities
● Administer prophylactic uterotonic medication immediately following delivery of the baby, for every
birth.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 15
● Apply controlled cord traction and uterine massage per standardized protocol.
● Monitor for and respond immediately to signs of excessive postpartum bleeding.
4. Obstetric Emergency Recognition and Response
Overview
Postpartum haemorrhage, eclampsia, shoulder dystocia, and cord prolapse represent the classic “never
events” of obstetric care where rehearsed, rapid, protocol-driven response most directly determines survival.
Responsibilities
● Maintain immediate readiness (medication, equipment, blood products, trained personnel) for every
major obstetric emergency.
● Apply standardized, drilled response protocols for postpartum haemorrhage, eclampsia, shoulder
dystocia, and cord prolapse.
● Escalate and mobilize the full emergency response team immediately upon recognition.
5. Essential and Resuscitative Newborn Care
Overview
The transition from foetal to newborn life is the most physiologically dramatic transition any human being
undergoes, and a proportion of newborns will not achieve it without skilled intervention within the first minute
of life.
Responsibilities
● Ensure a team member trained in Neonatal Resuscitation Program (NRP) protocols is present at every
delivery.
● Apply essential newborn care practices (immediate drying, thermal protection, early skin-to-skin
contact, delayed cord clamping where appropriate) for every birth.
● Apply systematic newborn resuscitation immediately for any newborn not breathing spontaneously.
6. Maternal Early Warning Systems
Overview
Maternal early warning score systems apply the same evidence-based deterioration-detection principle used
in general critical care specifically to the unique physiological parameters of pregnancy and the postpartum
period.
Responsibilities
● Apply maternal early warning scoring systematically throughout labour, delivery, and the immediate
postpartum period.
● Escalate immediately per defined protocol when warning score thresholds are met.
● Apply particular vigilance during the immediate postpartum period, when haemorrhage risk is highest.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 16
7. Respectful Maternity Care and Birth Companion Support
Overview
Respectful maternity care — dignity, autonomy, informed choice, and freedom from mistreatment — is now
recognized internationally as a fundamental component of quality maternal care, not merely a courtesy.
Responsibilities
● Support the presence of a birth companion of the woman's choice throughout labour, per institutional
policy and WHO recommendation.
● Provide informed choice and genuine consent for every intervention during labour and delivery.
● Maintain privacy, dignity, and freedom from any form of disrespect or abuse throughout care.
8. Postnatal Care, Breastfeeding, and Referral Coordination
Overview
The hours and days following birth carry continued risk for both mother and newborn, requiring structured
monitoring, breastfeeding support, and appropriate escalation when higher-level care is needed.
Responsibilities
● Apply structured postnatal monitoring for both mother and newborn per defined schedule.
● Support early, exclusive breastfeeding initiation per Baby-Friendly Hospital Initiative (BFHI) principles.
● Coordinate safe, timely referral or interfacility transfer for mothers or newborns requiring a higher
level of care.
How the Labour Room & Maternity Team Contributes to Quality Healthcare
● By applying systematic partograph monitoring, the team detects abnormal labour progress before it
becomes obstructed labour.
● By applying active management of the third stage of labour, the team prevents the majority of
postpartum haemorrhage before it begins.
● By maintaining rehearsed emergency readiness, the team ensures rapid, effective response to the rare
but catastrophic obstetric emergency.
● By providing skilled newborn resuscitation, the team ensures every newborn who needs help receives
it within the critical first minute of life.
● By applying maternal early warning systems, the team catches physiological deterioration before it
becomes a crisis.
● By delivering respectful maternity care, the team protects the dignity and autonomy of every labouring
woman alongside her physical safety.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 17
The Labour Room and Maternity team carries a responsibility no other clinical team in medicine shares in
quite the same way — continuous, simultaneous vigilance over two lives. Their partograph is a
deterioration-detection system, their active management of the third stage of labour is haemorrhage
prevention practiced proactively rather than reactively, and their rehearsed emergency response is what
an entire community trusts will be there in the rare moment childbirth turns from routine to catastrophic.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 18
CHAPTER 3: PROFESSIONAL STANDARDS FOR THE LABOUR ROOM &
MATERNITY TEAM
Labour room and maternity practice requires an uncommon combination of continuous, simultaneous clinical
vigilance over two patients, technical mastery of both normal delivery and obstetric emergency response,
genuine respect for a labouring woman's dignity and autonomy, and unwavering readiness for the rare
complication that can turn catastrophic within minutes. The standards that govern Labour Room practice
derive from obstetric and neonatal patient safety science, respectful maternity care principles, and the unique
responsibility of protecting two lives that cannot be separated.
1. Professional Appearance
Standards
Attire and Identification
● Wear appropriate clinical attire, PPE, and ID badge as per hospital infection control and identification
policy.
● Follow strict aseptic and infection control dress code given the significant blood and body fluid
exposure risk of delivery care.
Professional Presence
● Maintain a calm, reassuring, and confident demeanor, particularly during obstetric emergencies.
● Model composed, decisive leadership during emergency response, while maintaining genuine warmth
toward the labouring woman.
2. Professional Behaviour
Expected Behaviours
Monitoring Discipline
● Never allow partograph plotting or maternal early warning scoring to lapse or fall behind schedule.
● Never dismiss an abnormal foetal heart rate pattern or maternal vital sign as insignificant without
proper assessment.
Emergency Readiness Discipline
● Never allow obstetric emergency equipment, medication, or blood product readiness to lapse
between deliveries.
● Respond to every obstetric emergency call with immediate, full-team mobilization, without exception.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 19
Accountability
● Own every monitoring decision, every emergency response action, and every disposition made for
mother and newborn.
● Report and disclose critical incidents and adverse events honestly and promptly.
Collaborative Respect
● Treat every member of the multidisciplinary team — obstetrician, midwife, nurse, anesthesiologist,
neonatal team — as an essential, equal safety partner.
● Coordinate genuinely with the birth companion and family as partners in the woman's care.
Patient-Centered Focus
● Every monitoring decision and intervention is ultimately about the safety and dignity of the mother
and the safe arrival of her newborn — not merely completing a delivery.
3. Communication Standards
Communication with Mothers and Families
● Communicate labour progress, findings, and any concern clearly and honestly throughout labour.
● Obtain genuine informed consent for every intervention, explaining risks, benefits, and alternatives.
● Deliver difficult news (complication, stillbirth, neonatal death) with structure and profound
compassion.
Communication Within the Team
● Communicate rapidly and clearly during obstetric emergencies using closed-loop communication.
● Use structured handover tools (SBAR or equivalent) for every shift change and transfer of care.
● Escalate any deterioration or safety concern immediately and directly.
Written Communication Standards
● Partograph and labour documentation must be accurate, contemporaneous, and complete.
● Maternal and perinatal death review documentation must be factual, complete, and support honest
institutional learning.
● Newborn resuscitation documentation must accurately reflect the complete timeline and
interventions performed.
4. Confidentiality and Information Security
Overview
Maternity care involves inherently sensitive reproductive health information, requiring particular
confidentiality discipline throughout labour, delivery, and postnatal care.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 20
Responsibilities
● Discuss patient information only in appropriate clinical settings and only with those who have a
legitimate need to know.
● Protect access credentials for EMR/HIS and maternal-newborn information systems.
● Apply particular discretion for sensitive circumstances (adolescent pregnancy, stillbirth, adoption,
unmarried motherhood).
5. Ethical Standards
Core Ethical Principles for Labour Room Practice
Non-Maleficence
● Never allow a known monitoring gap or emergency readiness lapse to persist unaddressed.
● Never proceed with an intervention without genuine informed consent, except in genuine life-
threatening emergency.
Respect for Autonomy
● Honour the labouring woman's informed choices regarding her care, including her right to a birth
companion and to decline intervention.
Honesty and Transparency
● Communicate complications, risks, and outcomes honestly, including honest disclosure of adverse
events.
● Never falsify partograph or delivery documentation.
Non-Discrimination
● Provide the same rigorous, respectful care to every woman, regardless of marital status, background,
or circumstances of pregnancy.
6. Time Management and Prioritization
Clinical Priority Framework
● Immediate/Emergency: Cord prolapse, eclamptic seizure, massive haemorrhage, non-reassuring
foetal status, shoulder dystocia — immediate response, no delay.
● Urgent: Abnormal partograph trend, rising maternal early warning score — prompt assessment and
escalation.
● Routine: Scheduled monitoring intervals, routine postnatal checks — managed per defined schedule.
7. Teamwork and Collaboration
Work Effectively With
● Anesthesiology — for labour analgesia, operative delivery, and obstetric emergency anesthesia
support.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 21
● Neonatology/paediatrics — for newborn resuscitation and ongoing neonatal care.
● Blood bank — for rapid blood product availability during obstetric haemorrhage.
● Operating theatre teams — for emergency and elective caesarean section coordination.
● ICU/critical care — for coordinated management of critically ill obstetric patients.
● Quality department — for maternal/perinatal death review, incident reporting, and accreditation
support.
8. Professional Competence and Continuous Learning
Areas of Competence
● Partograph interpretation and labour progress assessment.
● Active management of the third stage of labour and postpartum haemorrhage management.
● Hypertensive disorders of pregnancy and eclampsia management.
● Shoulder dystocia and cord prolapse emergency response.
● Neonatal Resuscitation Program (NRP) protocols.
● Maternal early warning system interpretation and escalation.
● FMEA, RCA, and maternal/perinatal death review methodologies.
Continuous Learning
● Maintain current certification in obstetric emergency and neonatal resuscitation training (NRP and
equivalent).
● Maintain current knowledge of evolving obstetric and newborn care evidence and guidelines (FOGSI,
RCOG, ACOG, WHO).
● Engage with national and international obstetric and midwifery professional bodies.
● Participate regularly in obstetric emergency simulation and drill training.
● Participate in NABH, JCI, LaQshya, and MusQan accreditation training.
Professional Standards Checklist
● Have I applied systematic partograph monitoring to every labouring woman today?
● Have I applied active management of the third stage of labour for every delivery?
● Have I maintained obstetric emergency and newborn resuscitation readiness throughout my shift?
● Have I applied maternal early warning scoring consistently?
● Have I communicated honestly and compassionately with every mother and family?
● Have I reported any incident or safety concern through the appropriate system?
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 22
Labour Room and Maternity professionalism is continuous vigilance over two lives held to an unwavering
safety standard — the team that never lets partograph monitoring lapse, never skips active management
of the third stage, and never delays emergency response is the team every mother and newborn depends
upon at the very moment life begins.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 23
CHAPTER 4: PATIENT- AND FAMILY-CENTERED COMMUNICATION IN
THE LABOUR ROOM
Communication in the Labour Room occurs during one of the most physically and emotionally intense
experiences a woman will ever have — pain, fear, uncertainty, and profound vulnerability, often compounded
by the presence of a partner or family member experiencing their own version of that same fear. Respectful
maternity care, now recognized as a global standard rather than an optional courtesy, requires that this
communication preserve the woman's dignity, autonomy, and genuine participation in decisions about her
own body and her child's birth, even amid clinical urgency.
Why Communication Quality Matters in the Labour Room
● A woman who does not understand why an intervention is being performed may experience it as a
violation rather than care, regardless of clinical necessity.
● Poorly communicated labour progress can leave a woman and her family in unnecessary fear or false
reassurance.
● Disrespectful communication during labour is now recognized internationally as a form of maternal
mistreatment with lasting psychological consequences.
● Clear, honest communication following a complication or loss shapes a family's entire experience of
grief and their trust in the healthcare system.
The A-T-C-R-C Communication Model for the Labour Room
A — Acknowledge
Definition
Acknowledge the woman's pain, fear, and vulnerability genuinely, treating her as an active participant in her
own birth, not a passive recipient of care.
Examples
● “I know this is intense and frightening — you're doing this, and I'm here with you every step.”
T — Listen (Respect Her Voice and Choices)
Definition
Listen genuinely to the woman's questions, concerns, and preferences, honouring her autonomy even amid
clinical urgency.
Techniques
● “What matters most to you right now, and what questions do you have about what's happening?”
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 24
C — Clarify (Explain Findings and Plan Clearly)
Definition
Explain labour progress, any concern, and the recommended plan in clear, non-technical language, before
proceeding with intervention.
Examples
● “Your labour has slowed down more than we'd expect, so here's what we're thinking and why.”
R — Respond (Obtain Genuine Informed Consent)
Definition
Respond to her questions honestly and obtain genuine informed consent for every intervention, explaining
risks, benefits, and alternatives.
Examples
● “Here's what this procedure involves, why we're recommending it, and what would happen if we didn't
do it — it's your decision.”
C — Confirm (Verify Understanding and Ongoing Consent)
Definition
Confirm she genuinely understands and remains in agreement with the plan, recognizing that consent in labour
is an ongoing process, not a single moment.
Examples
● “Does this still feel right to you, or do you have any concerns before we go ahead?”
Communicating Complications and Respectful Maternity Care
Principles of Respectful Maternity Care Communication
● Support the presence of a birth companion of the woman's choosing throughout labour, per WHO
recommendation.
● Never perform an intervention without genuine informed consent, except in a genuine, immediate
life-threatening emergency.
● Communicate with warmth and respect regardless of the woman's background, marital status, or the
circumstances of her pregnancy.
● Never use language, tone, or physical handling that could be experienced as disrespectful, dismissive,
or abusive.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 25
Delivering Difficult News: Complication, Stillbirth, or Neonatal Loss
Structured Approach
● Deliver news of stillbirth or neonatal death directly, honestly, and with profound compassion, in as
private a setting as possible.
● Allow genuine space for the family's grief before continuing with further information or next steps.
● Involve chaplaincy, social work, and bereavement support resources promptly.
● Offer culturally appropriate options for the family to see, hold, or spend time with their newborn, per
institutional policy and family wishes.
Communicating During Obstetric Emergencies
Team and Family Communication Principles
● Use closed-loop communication during emergency response, confirming that instructions were heard
and completed.
● Provide honest, brief updates to the woman and her companion even during active emergency
management, wherever feasible.
● Debrief the woman and family honestly following any emergency, once the immediate crisis has
resolved.
Common Labour Room Communication Mistakes to Avoid
● Proceeding with an intervention without adequately explaining it or obtaining genuine consent.
● Dismissing a woman's pain, fear, or concern without genuine engagement.
● Excluding a birth companion without genuine clinical justification.
● Delivering news of stillbirth or complication without adequate structure or compassion.
● Using disrespectful language or tone during the intensity of labour or delivery.
Communication in the Labour Room must honour both clinical urgency and the profound dignity of the
woman experiencing one of the most vulnerable moments of her life — the team that explains honestly,
obtains genuine consent, and delivers difficult news with structure and compassion protects mothers and
families through respect as surely as through any clinical intervention performed.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 26
CHAPTER 5: PATIENT SAFETY AND MATERNAL-NEWBORN CARE
STANDARDS
Patient safety in the Labour Room is uniquely defined by the simultaneous vigilance two lives require — a
labour room that monitors systematically, manages the third stage actively, and responds to emergencies with
rehearsed precision produces measurably better maternal and newborn survival than one relying on
unstructured, reactive care. The R-T-A-C-A framework applies with particular intensity to the dual-patient,
rapidly-evolving nature of obstetric practice.
1. RESPECT
Definition
Treating every labouring woman's dignity, autonomy, and voice as inseparable from her physical safety — and
treating the birth companion as a genuine partner in her care.
How the Labour Room Demonstrates Respect
● Respect for Autonomy: Obtain genuine informed consent for every intervention, honouring the
woman's right to accept or decline care.
● Respect for Dignity: Maintain privacy and dignity throughout labour, delivery, and the postpartum
period.
● Respect for the Birth Companion: Support the presence of a companion of the woman's choosing per
WHO recommendation.
● Equal Service Standards: Provide the same rigorous, respectful care to every woman, regardless of
background or circumstance.
2. TIMELINESS
Definition
Monitoring labour progress, recognizing deviation, and responding to obstetric emergencies within timeframes
that protect two lives simultaneously.
Why Timeliness Is a Patient Safety Issue
A foetal heart rate abnormality unaddressed for even twenty minutes can cause permanent neurological injury.
Postpartum haemorrhage can progress from manageable to life-threatening within minutes. Eclampsia can
occur without adequate warning if maternal vital signs are not monitored systematically. Time in the Labour
Room is not a service quality metric — for both mother and newborn, it is frequently the entire determinant
of a healthy outcome versus permanent harm or death.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 27
Labour Room Timeliness Standards
● Partograph monitoring: plotted at defined intervals throughout the active phase of labour, without
exception.
● Obstetric emergency response: full team mobilization immediate upon recognition, no delay.
● Newborn resuscitation: initiated within the first minute of life (the “golden minute”) for any newborn
not breathing spontaneously.
● Maternal early warning escalation: acted upon immediately per defined threshold protocol.
3. ACCURACY
Definition
Applying partograph plotting, risk assessment, and obstetric emergency protocol criteria correctly and
consistently, despite the physical and emotional intensity of labour and delivery.
Why Accuracy Is Non-Negotiable in the Labour Room
An inaccurately plotted partograph can miss the alert line that would have prompted earlier intervention for
obstructed labour. An inaccurate foetal heart rate interpretation can miss the pattern indicating genuine foetal
compromise. An inaccurate blood loss estimation can delay recognition of postpartum haemorrhage until it
becomes life-threatening. Accuracy in the Labour Room, achieved under time pressure and physical intensity,
is what separates systematic obstetric care from dangerous improvisation.
Areas Requiring Labour Room Accuracy
● Partograph Plotting: Every labouring woman's progress must be plotted accurately and consistently.
● Foetal Heart Rate Interpretation: Every monitoring strip or auscultation finding must be interpreted
using validated, systematic criteria.
● Blood Loss Estimation: Every delivery's blood loss must be estimated accurately, using objective
measurement wherever possible.
● Documentation: Every labour and delivery record must accurately and completely reflect the evolving
clinical picture.
4. COMPASSION
Definition
Recognizing that every woman in the Labour Room is experiencing profound physical and emotional intensity,
and that genuine compassion, sustained throughout labour and delivery, is itself a core component of excellent
maternity care.
How the Labour Room Demonstrates Compassion
● Provide Continuous Emotional Support: Genuine reassurance and presence throughout the physical
and emotional intensity of labour.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 28
● Support Pain Management with Genuine Care: Offer and respect the woman's choices regarding
labour analgesia.
● Deliver Difficult News with Structure and Profound Care: Stillbirth and neonatal loss disclosure deserve
the deepest compassion healthcare can offer.
● Extend Compassion to Every Family Circumstance: Adolescent mothers, single mothers, and mothers
facing difficult circumstances deserve the same warmth as every other woman.
5. ACCOUNTABILITY
Definition
Taking full professional responsibility for every monitoring decision, every emergency response action, and
every disposition made for mother and newborn under Labour Room care.
Labour Room Accountability Standards
● Every partograph, monitoring assessment, and clinical decision is documented with the responsible
team member's identification.
● Never allow a known monitoring gap or emergency readiness lapse to go unaddressed.
● Report every critical incident and adverse maternal or newborn event honestly through the quality
reporting system.
● Participate in maternal and perinatal death review for every applicable case with complete clinical
honesty.
● Participate in quality audits and accreditation surveys with accurate, complete maternal-newborn
records.
The R-T-A-C-A Framework in the Labour Room
Standard Core Focus in the Labour Room
Respect Genuine informed consent; birth companion support; dignity throughout labour
Timeliness Immediate emergency response; golden-minute newborn resuscitation; scheduled
monitoring intervals
Accuracy Precise partograph plotting, FHR interpretation, blood loss estimation, complete
documentation
Compassion Continuous emotional support; structured, profound compassion for loss
Accountability Every decision owned and documented; every maternal/perinatal death honestly reviewed
Daily Quality Standards Checklist for the Labour Room
● Apply systematic partograph monitoring to every labouring woman.
● Apply active management of the third stage of labour for every delivery.
● Maintain obstetric emergency and newborn resuscitation readiness continuously.
● Apply maternal early warning scoring consistently throughout labour and postpartum.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 29
● Communicate honestly, respectfully, and compassionately with every mother and family.
● Document every clinical assessment and intervention completely.
● Report any incident or safety concern through the quality reporting system.
In the Labour Room, patient safety is measured across two lives simultaneously — a family experiences it
as a mother who survived a haemorrhage caught in time, a newborn who breathed because a trained hand
was ready in the golden minute, and a birth remembered not for fear but for the dignity with which it was
attended. That is patient safety delivered at the moment life itself begins.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 30
CHAPTER 6: CONFIDENTIALITY, PRIVACY, AND INFORMATION
SECURITY
Maternity care involves inherently sensitive reproductive health information — pregnancy circumstances,
marital status, prior obstetric history, and sometimes deeply personal or stigmatized situations — requiring
particular confidentiality discipline throughout labour, delivery, and postnatal care, within an environment that
is often physically shared among multiple labouring women.
1. Privacy and Dignity in the Labour Room
Responsibilities
● Use curtains, screens, or private rooms wherever available, particularly during examination and
delivery.
● Limit exposure of the woman's body to what is clinically necessary, maintaining dignity throughout.
● Never discuss one woman's case within earshot of another labouring woman or visiting family.
● Limit the presence of trainees or observers to those with genuine educational need and, wherever
required, the woman's consent.
2. Confidentiality of Sensitive Reproductive Health Circumstances
Overview
Adolescent pregnancy, pregnancy outside marriage, stillbirth, and adoption decisions carry particular social
sensitivity requiring heightened discretion.
Responsibilities
● Handle sensitive reproductive health circumstances with heightened confidentiality and non-
judgmental discretion.
● Communicate only the clinically necessary information to the wider care team, not personal
circumstances beyond clinical relevance.
● Apply appropriate legal and safeguarding reporting obligations while maintaining maximum discretion
consistent with legal requirement.
3. Clinical Data and EMR/HIS Confidentiality
Responsibilities
● Access only the patient records necessary for current labour room or maternity care responsibilities.
● Never discuss a patient's clinical information with anyone outside the legitimate care team.
● Follow hospital IT and cybersecurity policy for all EMR/HIS and maternal-newborn information system
access.
● Never leave labour room or documentation workstations unlocked or logged in when unattended.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 31
4. Confidentiality of Maternal and Perinatal Death Review
Overview
Maternal and perinatal death reviews carry significant emotional and legal sensitivity requiring rigorous
confidentiality protection to sustain honest institutional learning.
Responsibilities
● Maintain strict confidentiality of maternal and perinatal death review proceedings per institutional
peer review protection policy.
● Share review findings only with those who have a legitimate governance or improvement need to
know.
● Coordinate with legal counsel for any case with medico-legal implications.
5. Cybersecurity of Maternal-Newborn Information Systems
Why Cybersecurity Is a Patient Safety Issue
Maternal-newborn information systems store the real-time monitoring data — partograph trends, foetal heart
rate patterns, maternal early warning scores — upon which safe labour management depends. A compromised
system risks both sensitive data breach and, if monitoring data is corrupted, direct patient safety harm through
delayed recognition of deterioration.
Responsibilities
● Use only authorized, unique login credentials for all EMR/HIS and maternal-newborn monitoring
system access.
● Never share login credentials with colleagues, regardless of workload pressure.
● Never connect personal devices to hospital clinical networks without IT authorization.
● Report any suspected unauthorized access or cybersecurity anomaly to IT security immediately.
6. Confidentiality for Vulnerable and High-Profile Circumstances
Responsibilities
● Maintain the same confidentiality standard for high-profile or notorious patients as for every other
patient.
● Never disclose patient identity, pregnancy circumstances, or delivery outcome to media or
unauthorized persons.
● Apply heightened discretion for cases involving suspected abuse, trafficking, or other safeguarding
concerns.
Confidentiality Checklist for the Labour Room & Maternity Team
● Maintain privacy and dignity during examination and delivery.
● Handle sensitive reproductive health circumstances with heightened discretion.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 32
● Use only authorized credentials for EMR/HIS and monitoring systems.
● Maintain strict confidentiality of maternal/perinatal death review proceedings.
● Never connect personal devices to hospital clinical networks without IT authorization.
● Apply appropriate safeguarding reporting obligations with maximum discretion consistent with legal
requirement.
In the Labour Room, confidentiality must be actively maintained within an environment that is often
physically shared among multiple labouring women, for information that touches some of the most
personal and sensitive circumstances a woman may ever share with a healthcare team.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 33
CHAPTER 7: STANDARD OPERATING PROCEDURES (SOPs) FOR THE
LABOUR ROOM & MATERNITY TEAM
Objectives of Labour Room SOPs
● Ensure consistent, safe, and respectful labour and delivery care for every mother and newborn.
● Minimize maternal and perinatal harm through systematic, documented monitoring and emergency
protocols.
● Support NABH/JCI/LaQshya/MusQan accreditation compliance for maternal-newborn care standards.
● Provide a defensible clinical and legal framework for maternal/perinatal incident investigation.
SOP 1: Labour Admission Assessment and Risk Stratification
Purpose
To ensure systematic assessment and appropriate risk classification for every woman admitted in labour.
Procedure
● Step 1: Conduct History and Examination — conduct systematic history, general and obstetric
examination.
● Step 2: Confirm Gestational Parameters — confirm gestational age, presentation, and estimated foetal
weight.
● Step 3: Apply Risk Stratification — apply validated criteria to classify pregnancy risk level.
● Step 4: Document Baseline Parameters — document baseline maternal and foetal vital parameters.
● Step 5: Communicate Plan — communicate the admission assessment and care plan to the woman.
Quality Standards
● 100% of admissions include documented risk stratification within the institutionally defined
timeframe.
SOP 2: Partograph Monitoring and Labour Progress Assessment
Purpose
To ensure systematic, continuous monitoring of labour progress from the active phase onward.
Procedure
● Step 1: Initiate Partograph — initiate partograph plotting at the onset of the active phase of labour.
● Step 2: Plot at Defined Intervals — plot cervical dilatation, descent, and vital parameters at defined
intervals.
● Step 3: Monitor Foetal Heart Rate — apply intermittent or continuous FHR monitoring per risk
classification.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 34
● Step 4: Recognize Alert/Action Lines — recognize and act immediately when progress crosses the alert
or action line.
● Step 5: Document — maintain complete, accurate partograph documentation.
Quality Standards
● 100% of labouring women monitored using partograph from the active phase of labour.
SOP 3: WHO Safe Childbirth Checklist Application
Purpose
To ensure critical safety steps are never omitted at key pause points during labour and delivery.
Procedure
● Step 1: Apply at Admission — apply the checklist pause point at admission.
● Step 2: Apply Before Delivery — apply the checklist pause point before pushing/delivery.
● Step 3: Apply Soon After Birth — apply the checklist pause point within one hour after birth.
● Step 4: Apply Before Discharge — apply the checklist pause point before discharge.
● Step 5: Document — document checklist completion at every pause point.
Quality Standards
● 100% of deliveries include documented checklist completion at all four pause points.
SOP 4: Active Management of the Third Stage of Labour (AMTSL)
Purpose
To prevent postpartum haemorrhage through evidence-based active management of the third stage.
Procedure
● Step 1: Administer Uterotonic — administer prophylactic uterotonic medication immediately after
delivery of the baby.
● Step 2: Apply Controlled Cord Traction — apply controlled cord traction with counter-traction per
protocol.
● Step 3: Perform Uterine Massage — perform uterine massage after placental delivery.
● Step 4: Monitor Blood Loss — monitor and estimate blood loss objectively.
● Step 5: Document — document the complete AMTSL process and blood loss estimation.
Quality Standards
● AMTSL applied for 100% of vaginal deliveries.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 35
SOP 5: Postpartum Haemorrhage Recognition and Management
Purpose
To ensure rapid, structured, stepwise response to postpartum haemorrhage.
Procedure
● Step 1: Recognize Excessive Bleeding — recognize and quantify blood loss exceeding defined
thresholds.
● Step 2: Call for Help — activate the obstetric emergency team immediately.
● Step 3: Apply First-Line Measures — apply uterine massage, additional uterotonics, and bimanual
compression as indicated.
● Step 4: Escalate Per Protocol — escalate to balloon tamponade, surgical intervention, or massive
transfusion as required.
● Step 5: Coordinate Blood Bank — coordinate rapid blood product availability throughout.
● Step 6: Document — document the complete haemorrhage response timeline.
Quality Standards
● 100% of PPH events include documented stepwise response per protocol.
SOP 6: Hypertensive Disorders and Eclampsia Management
Purpose
To ensure early recognition and structured management of hypertensive disorders of pregnancy.
Procedure
● Step 1: Screen Systematically — screen blood pressure and proteinuria at every antenatal and labour
assessment.
● Step 2: Recognize Severe Features — recognize severe pre-eclampsia and impending eclampsia signs
promptly.
● Step 3: Administer Magnesium Sulphate — administer magnesium sulphate per protocol for severe
pre-eclampsia/eclampsia.
● Step 4: Control Blood Pressure — administer antihypertensive therapy per protocol for severe
hypertension.
● Step 5: Plan Delivery — coordinate timely delivery planning based on maternal and foetal status.
● Step 6: Document — document the complete assessment and management.
Quality Standards
● 100% of eclampsia/severe pre-eclampsia cases include documented magnesium sulphate
administration per protocol.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 36
SOP 7: Shoulder Dystocia and Cord Prolapse Response
Purpose
To ensure immediate, structured response to these obstetric emergencies.
Procedure (Shoulder Dystocia)
● Step 1: Recognize and Call for Help — recognize shoulder dystocia and call for additional assistance
immediately.
● Step 2: Apply Systematic Manoeuvres — apply standardized manoeuvres (McRoberts, suprapubic
pressure, and further escalation) systematically.
● Step 3: Document — document the timeline and manoeuvres applied.
Procedure (Cord Prolapse)
● Step 1: Recognize and Call for Help — recognize cord prolapse and activate emergency caesarean
pathway immediately.
● Step 2: Relieve Cord Compression — apply manual elevation or positioning to relieve cord
compression.
● Step 3: Expedite Delivery — expedite delivery via the most rapid safe route.
● Step 4: Document — document the complete response timeline.
Quality Standards
● 100% of shoulder dystocia and cord prolapse events include documented structured response.
SOP 8: Newborn Resuscitation
Purpose
To ensure immediate, skilled resuscitation for any newborn not breathing spontaneously.
Procedure
● Step 1: Assess Immediately — assess breathing, tone, and heart rate immediately after birth.
● Step 2: Provide Initial Steps — provide warmth, positioning, and stimulation per NRP algorithm.
● Step 3: Escalate Per Algorithm — escalate to positive pressure ventilation, chest compressions, or
medication per NRP algorithm as indicated.
● Step 4: Reassess Continuously — reassess heart rate and breathing continuously throughout
resuscitation.
● Step 5: Document — document the complete resuscitation timeline and interventions.
Quality Standards
● A trained NRP provider present at 100% of deliveries.
● Positive pressure ventilation initiated within the golden minute for 100% of eligible newborns.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 37
SOP 9: Maternal Referral and Interfacility Transfer
Purpose
To ensure safe, timely transfer of mothers or newborns requiring a higher level of care.
Procedure
● Step 1: Recognize Transfer Need — recognize conditions exceeding local facility capability promptly.
● Step 2: Stabilize for Transfer — stabilize mother and/or newborn to the extent possible before transfer.
● Step 3: Coordinate Receiving Facility — coordinate with the receiving facility and confirm acceptance.
● Step 4: Provide Structured Handover — provide complete clinical handover using a standardized tool.
● Step 5: Document — document the complete transfer coordination and handover.
Quality Standards
● 100% of transfers include documented structured handover.
SOP 10: Maternal and Perinatal Death Review
Purpose
To ensure systematic, honest review of every maternal death and significant perinatal loss.
Procedure
● Step 1: Identify Cases — identify all maternal deaths and significant perinatal losses for review.
● Step 2: Conduct Multidisciplinary Review — conduct systematic, honest, multidisciplinary case review.
● Step 3: Identify Contributing Factors — identify systemic and clinical contributing factors without
defensive minimization.
● Step 4: Develop Corrective Action — develop specific, actionable corrective action recommendations.
● Step 5: Track Implementation — track corrective action to verified completion.
● Step 6: Document — document the complete review process and outcomes, per applicable
maternal/perinatal death review reporting requirements.
Quality Standards
● 100% of maternal deaths and applicable perinatal losses reviewed within the defined timeframe.
Labour Room SOP Daily Compliance Checklist
● Partograph monitoring current and complete for every labouring woman today.
● AMTSL applied and documented for every vaginal delivery.
● WHO Safe Childbirth Checklist completed at all four pause points for every delivery.
● Obstetric emergency and newborn resuscitation equipment verified ready.
● Any incident or safety concern reported through the appropriate system.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 38
SOPs in the Labour Room are the operating instructions for protecting two lives simultaneously. When
followed consistently, they are the systematic foundation of safe labour monitoring, haemorrhage
prevention, and rehearsed emergency response for every mother and newborn.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 39
CHAPTER 8: COMMUNICATION WITH SPECIAL GROUPS
The Labour Room team communicates across an unusually intimate and high-stakes range of circumstances —
from a first-time mother terrified by the unfamiliarity of labour, to a high-risk pregnancy requiring careful,
honest risk communication, to a family suddenly facing the devastation of stillbirth, to a neonatal team
receiving a newborn requiring immediate resuscitation. Excellent maternity care requires adapted
communication for each of these very different, often emotionally intense, circumstances.
1. First-Time Mothers (Primigravidae)
Overview
First-time mothers often face labour with limited prior experience and heightened anxiety about the unknown.
Communication Guidelines
● Provide clear, reassuring explanation of what to expect at each stage of labour.
● Check understanding frequently, avoiding assumptions about prior knowledge.
● Offer genuine encouragement and emotional support throughout.
2. High-Risk Pregnancy Patients
Overview
Women with high-risk pregnancies require honest risk communication balanced with genuine reassurance and
support.
Communication Guidelines
● Communicate risk factors and the heightened monitoring plan honestly, without unnecessary alarm.
● Explain the rationale for any additional intervention or monitoring clearly.
● Provide continuous reassurance of the team's vigilance and readiness.
3. Adolescent and Vulnerable Mothers
Overview
Adolescent mothers and those in vulnerable social circumstances require particular sensitivity, non-judgmental
communication, and appropriate safeguarding awareness.
Communication Guidelines
● Communicate without judgment, with genuine warmth and support.
● Apply appropriate safeguarding assessment and support coordination where indicated.
● Respect privacy and confidentiality with particular care given social stigma risk.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 40
4. Families Facing Stillbirth or Neonatal Loss
Overview
Families experiencing stillbirth or neonatal death face one of the most profound losses possible, requiring the
deepest compassion healthcare can offer.
Communication Guidelines
● Deliver news directly, honestly, and with profound compassion, in as private a setting as possible.
● Offer culturally appropriate options for the family to see, hold, or spend time with their newborn.
● Involve bereavement support, chaplaincy, and social work promptly and continuously.
5. Neonatal Resuscitation and Paediatric Teams
Overview
Rapid, clear communication with the neonatal team is essential for coordinated newborn resuscitation and
ongoing care.
Communication Guidelines
● Communicate anticipated high-risk delivery circumstances to the neonatal team in advance wherever
possible.
● Use closed-loop communication during active newborn resuscitation.
● Provide complete handover of maternal history relevant to newborn care.
6. Birth Companions and Family Members
Overview
Birth companions play a genuine support role and require respectful inclusion and clear communication
throughout labour.
Communication Guidelines
● Communicate labour progress and any concern to the birth companion as an active support partner,
with the woman's consent.
● Provide clear guidance on how the companion can best support the labouring woman.
● Prepare the companion honestly if an emergency response becomes necessary.
7. Anesthesiology and Operating Theatre Teams
Communication Guidelines
● Communicate urgency clearly and accurately when requesting operative delivery or anesthesia
support.
● Coordinate clearly regarding haemodynamic status during obstetric haemorrhage or other emergency.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 41
8. Hospital Administration and Quality/Accreditation Bodies
Communication Guidelines
● Present partograph compliance, AMTSL rates, and maternal/perinatal outcome data in management-
accessible formats.
● Advocate for necessary resources (staffing, equipment, blood bank capacity) with clear patient safety
justification.
● Respond to accreditation inquiries (NABH, JCI, LaQshya, MusQan) with complete and accurate
documentation.
Universal Labour Room Communication Principles
● Communicate with warmth and respect, recognizing the profound vulnerability of labour and delivery.
● Respond to every deterioration and every mother's or family's genuine concern with appropriate
urgency.
● Always obtain genuine informed consent before intervention, except in immediate life-threatening
emergency.
● Document every significant clinical communication completely.
The Labour Room team that communicates with equal skill toward a frightened first-time mother, a high-
risk pregnancy requiring honest risk communication, and a family facing devastating loss serves every
stakeholder at maximum impact — rigorous clinical excellence delivered alongside the profound
compassion that childbirth, at its most vulnerable, demands.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 42
CHAPTER 9: HANDLING DIFFICULT SITUATIONS
Common Difficult Situations for the Labour Room & Maternity Team
● Two or more simultaneous obstetric emergencies exceed immediate team capacity.
● A labouring woman declines a recommended intervention that the team believes is clinically
necessary.
● A postpartum haemorrhage does not respond to first-line management measures.
● A newborn requires resuscitation beyond initial steps, escalating through the NRP algorithm.
● A family disputes a caesarean section recommendation, delaying a time-sensitive decision.
● A stillbirth or neonatal death occurs, requiring immediate compassionate disclosure.
● Blood bank stock is inadequate during an active obstetric haemorrhage.
● A maternal death raises genuine concern about a preventable systemic failure.
● A birth companion's presence creates a genuine safety or clinical concern.
● A colleague's clinical judgment or fitness for duty raises concern during a high-pressure delivery.
Core Principles for Handling Difficult Situations
1. Two Lives Are Paramount
In every difficult situation, the safety of both mother and newborn drives every decision — systematic
monitoring and emergency protocols must never be bypassed for administrative or interpersonal convenience.
2. Respect Autonomy While Ensuring Genuine Understanding
A woman's right to decline intervention must be respected, but only after genuine effort to ensure she
understands the clinical implications — informed refusal is different from uninformed refusal.
3. Apply Standardized Protocols Under Pressure
Obstetric emergencies are precisely when standardized protocols matter most — resist the temptation to
improvise when a proven, drilled protocol exists.
4. Document Everything
Every difficult clinical situation must be contemporaneously documented — what was found, what was
communicated, what decisions were made, and by whom.
Handling Simultaneous Obstetric Emergencies
Steps
● Apply triage-based prioritization based on genuine severity and immediacy of life threat.
● Mobilize additional team members and resources per institutional surge protocol.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 43
● Coordinate with anesthesiology, blood bank, and operating theatre for capacity support.
● Document the resource decision-making and rationale thoroughly.
Handling a Woman Declining Recommended Intervention
Steps
● Explain the clinical rationale and risk of declining clearly and without coercion.
● Ensure genuine understanding through teach-back or equivalent confirmation.
● Respect her informed decision while continuing to offer support and monitoring.
● Document the discussion, her decision, and the informed consent/refusal process thoroughly.
Handling Postpartum Haemorrhage Unresponsive to First-Line Measures
Steps
● Escalate immediately to the full obstetric emergency protocol, including surgical and blood bank
teams.
● Apply balloon tamponade, surgical intervention, or further escalation per protocol without delay.
● Maintain continuous, clear communication among every team member involved.
● Conduct thorough review following stabilization, regardless of outcome.
Handling Newborn Resuscitation Requiring Extended Escalation
Steps
● Continue systematic NRP algorithm escalation without deviation.
● Call for additional neonatal support immediately if resuscitation extends beyond initial steps.
● Communicate honestly with the family throughout, once immediate resuscitation allows.
● Document the complete resuscitation timeline and outcome thoroughly.
Handling a Family Disputing a Time-Sensitive Caesarean Recommendation
Steps
● Explain the clinical urgency and risk of delay clearly and directly.
● Involve senior obstetric leadership immediately for a second, reinforcing explanation if time allows.
● Document the discussion and decision-making process thoroughly.
● Escalate to institutional ethics or legal consultation if genuine emergency and refusal create
irreconcilable conflict.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 44
Handling Compassionate Disclosure of Stillbirth or Neonatal Death
Steps
● Deliver the news directly, honestly, and with profound compassion in as private a setting as possible.
● Allow genuine space for grief before continuing with further information.
● Involve bereavement support, chaplaincy, and social work immediately.
● Offer appropriate options for the family regarding their newborn, per institutional policy and family
wishes.
Handling Inadequate Blood Bank Stock During Obstetric Haemorrhage
Steps
● Escalate immediately to blood bank leadership and hospital administration.
● Activate emergency blood supply protocols, including regional coordination where available.
● Apply all available haemorrhage control measures to minimize ongoing blood loss while supply is
secured.
● Conduct thorough review following the event to strengthen blood bank readiness for obstetric
emergencies.
Handling Concern About a Preventable Maternal Death
Steps
● Initiate immediate, honest maternal death review.
● Ensure the review is conducted with genuine investigative rigour, not defensive minimization.
● Communicate findings honestly to institutional leadership and, where required, statutory maternal
death review bodies.
● Implement corrective action arising from the review with genuine institutional priority.
Handling a Birth Companion Creating a Safety or Clinical Concern
Steps
● Address the specific concern directly and respectfully with the companion.
● Explain any necessary boundary clearly, without unnecessarily excluding genuine support.
● Involve security only if genuine safety risk emerges beyond clinical management.
Handling Concern About a Colleague's Fitness for Duty
Steps
● Address any immediate patient safety concern directly and without delay.
● Escalate to department leadership immediately if the concern involves impairment or an immediate
safety risk.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 45
● Document the concern and actions taken through appropriate professional channels.
The CALM Model for the Labour Room & Maternity Team
● C – Control the immediate risk to mother and/or newborn.
● A – Acknowledge the clinical and emotional reality accurately.
● L – Lead with evidence — partograph criteria, obstetric emergency protocols, and NRP algorithms.
● M – Manage through documented escalation channels when needed.
Difficult situations in the Labour Room are always, ultimately, tests of whether systematic protocol and
genuine compassion hold firm together under the pressure of two lives at risk simultaneously. The team
that never bypasses monitoring, never delays emergency response, and never abandons compassion even
in crisis is fulfilling the highest professional obligation of maternity care.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 46
CHAPTER 10: EMERGENCY RESPONSE — CRITICAL OBSTETRIC AND
NEWBORN PRESENTATION
Overview
While systematic monitoring underlies the entirety of Labour Room practice, certain presentations demand
the team's most immediate, standardized, and rehearsed response — scenarios where the difference between
a coordinated, protocol-driven response and an improvised one is measured directly in the survival of mother,
newborn, or both.
Critical Presentations Requiring Immediate Response
● Postpartum haemorrhage.
● Eclamptic seizure.
● Shoulder dystocia.
● Cord prolapse.
● Non-reassuring foetal status requiring emergency delivery.
● Uterine rupture.
● Amniotic fluid embolism.
● Newborn not breathing at birth.
● Maternal cardiac arrest.
● Massive obstetric haemorrhage requiring emergency hysterectomy.
1. Postpartum Haemorrhage
Immediate Response
● Call for help and activate the obstetric emergency team immediately.
● Apply uterine massage and additional uterotonic medication.
● Escalate to bimanual compression, balloon tamponade, or surgical intervention per stepwise protocol.
● Coordinate immediate blood product availability.
2. Eclamptic Seizure
Steps
● Protect the airway and ensure maternal and foetal safety during the seizure.
● Administer magnesium sulphate immediately per protocol.
● Control blood pressure per protocol.
● Plan urgent delivery once maternal condition is stabilized.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 47
3. Shoulder Dystocia
Steps
● Call for immediate additional assistance.
● Apply systematic manoeuvres (McRoberts, suprapubic pressure, and further escalation) in sequence.
● Avoid excessive traction throughout the manoeuvre sequence.
● Document the timeline and manoeuvres applied.
4. Cord Prolapse
Steps
● Relieve cord compression immediately through manual elevation or maternal positioning.
● Activate the emergency caesarean pathway without delay.
● Continue foetal heart rate monitoring throughout preparation for delivery.
5. Non-Reassuring Foetal Status
Steps
● Apply immediate intrauterine resuscitation measures (maternal repositioning, oxygen, fluid,
discontinuation of oxytocin).
● Reassess foetal status promptly following intrauterine resuscitation measures.
● Expedite delivery via the most rapid safe route if status does not improve.
6. Uterine Rupture
Steps
● Recognize signs (severe pain, foetal heart rate abnormality, maternal instability) promptly.
● Activate emergency laparotomy pathway immediately.
● Coordinate massive transfusion protocol concurrently.
7. Amniotic Fluid Embolism
Steps
● Recognize sudden cardiorespiratory collapse and coagulopathy promptly.
● Initiate immediate resuscitation per maternal cardiac arrest protocol.
● Coordinate immediate multidisciplinary critical care and blood product support.
8. Newborn Not Breathing at Birth
Steps
● Provide warmth, positioning, and stimulation immediately.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 48
● Initiate positive pressure ventilation within the golden minute if breathing does not improve.
● Escalate through the NRP algorithm (chest compressions, medication) as indicated.
9. Maternal Cardiac Arrest
Steps
● Initiate immediate high-quality CPR with left uterine displacement for the pregnant patient.
● Activate the obstetric and resuscitation emergency teams simultaneously.
● Consider perimortem caesarean delivery per protocol and timeframe if resuscitation is not
immediately successful.
10. Massive Obstetric Haemorrhage Requiring Emergency Hysterectomy
Steps
● Escalate through the full stepwise haemorrhage protocol before proceeding to hysterectomy.
● Coordinate immediate surgical, anesthesia, and blood bank teams for definitive surgical management.
● Maintain massive transfusion protocol support throughout.
Emergency Response: Key Performance Targets
Emergency Scenario Maximum Response Time Key Action
Postpartum Haemorrhage Immediate Uterine massage; uterotonics;
escalate per stepwise protocol
Eclamptic Seizure Immediate Protect airway; administer
magnesium sulphate
Cord Prolapse Immediate Relieve compression; activate
emergency caesarean pathway
Newborn Not Breathing Within the golden minute Positive pressure ventilation;
escalate per NRP
Maternal Cardiac Arrest Immediate High-quality CPR with uterine
displacement; consider perimortem
delivery
Emergency Preparedness Checklist for the Labour Room & Maternity Team
● Obstetric emergency trolley (haemorrhage, eclampsia medications) verified and accessible at all times.
● Newborn resuscitation equipment verified and functional at every delivery station.
● Massive transfusion and blood bank coordination pathway tested and functional.
● Regular participation in obstetric emergency and neonatal resuscitation simulation drills.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 49
Emergency preparedness in the Labour Room is not a policy statement — it is the immediate, standardized,
rehearsed response that determines survival for mother and newborn alike in the minutes before definitive
treatment can begin. The team that has practiced these critical presentations until the response is
automatic protects two lives in the moments when there is no time to think, only to act correctly.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 50
CHAPTER 11: DIGITAL COMPETENCY FOR THE LABOUR ROOM &
MATERNITY TEAM
Objectives
● Enable the Labour Room team to use electronic partograph, monitoring, and clinical information
systems accurately, securely, and efficiently.
● Leverage technology to improve monitoring accuracy, early warning detection, and coordinated
emergency response.
● Manage the cybersecurity of maternal-newborn information systems as a core patient safety function.
Core Digital Competencies for the Labour Room & Maternity Team
1. Electronic Partograph and Labour Monitoring Systems
Essential Skills
● Enter and interpret partograph data accurately in real time within the electronic system.
● Generate alerts and escalation triggers based on partograph alert/action line criteria.
2. Electronic Foetal Monitoring (Cardiotocography) Systems
Essential Skills
● Interpret continuous foetal heart rate monitoring using standardized classification criteria.
● Recognize and respond to system-generated alerts for non-reassuring patterns.
3. Maternal Early Warning Score Systems
Essential Skills
● Enter vital signs and generate maternal early warning scores systematically.
● Act promptly on system-generated escalation alerts.
4. Electronic Medical Record (EMR) / Hospital Information System (HIS)
Essential Skills
● Document labour, delivery, and newborn care accurately and in real time.
● Access relevant antenatal history and prior obstetric records efficiently.
5. AI-Assisted Foetal Monitoring and Risk Prediction
Awareness
● AI and computerized cardiotocography interpretation tools are increasingly applied to foetal
monitoring and risk prediction.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 51
● Understand and appropriately leverage these tools while maintaining independent clinical judgment
— AI tools are decision-support, not a substitute for systematic clinical assessment.
6. Telemedicine for Remote Obstetric Consultation
Essential Skills
● Use telemedicine platforms for remote obstetric or maternal-foetal medicine consultation where
applicable, particularly for referring facilities.
7. Cybersecurity and Information Security
Personal Digital Security Responsibilities
● Use unique, strong credentials for all EMR/HIS and monitoring system logins.
● Lock or log out of workstations whenever stepping away, even briefly.
● Never connect personal devices to hospital clinical networks.
● Report all cybersecurity anomalies to IT security immediately.
Digital Competency Checklist
● Navigate electronic partograph, foetal monitoring, and EMR/HIS systems for all core functions without
assistance.
● Interpret cardiotocography and maternal early warning score outputs accurately.
● Apply basic cybersecurity practices to all clinical system access.
● Know the downtime procedure for partograph/monitoring system failure, including manual paper
partograph backup.
Digital competency for the Labour Room and Maternity team is the ability to integrate systematic clinical
judgment with the electronic partograph, foetal monitoring, and early warning systems that modern
maternity care increasingly depends upon — using technology to extend, never replace, the disciplined,
continuous vigilance that defines safe care for two lives at once.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 52
CHAPTER 12: DAILY LABOUR ROOM & MATERNITY CHECKLIST
Objectives
● Provide a structured daily framework for safe, consistent, and respectful labour and delivery care.
● Ensure every monitoring, emergency readiness, and newborn care obligation is addressed every shift.
● Support accurate clinical documentation and departmental performance data quality.
PART A: START-OF-SHIFT CHECKLIST
Personal and Professional Readiness
● Appropriate clinical attire, PPE, and ID badge displayed.
● EMR/HIS, partograph, and foetal monitoring systems functional and accessible.
Handover and Readiness Review
● Reviewed structured handover from previous shift, including any high-risk or ongoing labour cases.
● Verified obstetric emergency trolley and newborn resuscitation equipment are stocked and functional.
● Verified blood bank readiness and current stock status for obstetric haemorrhage.
PART B: ADMISSION AND MONITORING CHECKLIST
● Risk stratification completed for every new admission.
● Partograph monitoring current for every labouring woman.
● Foetal heart rate monitoring applied per risk classification.
PART C: DELIVERY AND AMTSL CHECKLIST
● WHO Safe Childbirth Checklist applied at every pause point for every delivery.
● Active management of the third stage of labour applied for every vaginal delivery.
● Blood loss estimated and documented objectively for every delivery.
PART D: NEWBORN CARE CHECKLIST
● A trained NRP provider present at every delivery.
● Essential newborn care practices applied for every birth.
● Early breastfeeding initiation supported per BFHI principles.
PART E: MATERNAL EARLY WARNING CHECKLIST
● Maternal early warning scoring applied per defined schedule throughout labour and postpartum.
● Any escalation threshold met acted upon immediately.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 53
PART F: RESPECTFUL CARE CHECKLIST
● Genuine informed consent obtained for every intervention.
● Birth companion presence supported per policy and the woman's choice.
PART G: SAFETY AND INCIDENT CHECKLIST
● Any obstetric or newborn incident reported through the appropriate system.
● Any maternal death or applicable perinatal loss flagged for review.
PART H: DOCUMENTATION CHECKLIST
● All partograph, delivery, and newborn documentation completed accurately.
● All documentation audit-ready before end of shift.
PART I: END-OF-SHIFT CHECKLIST
● All clinical records updated and complete for the shift.
● Structured handover prepared for the incoming shift.
● Clinical systems securely logged out.
Daily Self-Assessment for the Labour Room & Maternity Team
● Did we verify obstetric emergency and newborn resuscitation readiness at the start of the shift?
● Did we apply systematic partograph monitoring to every labouring woman?
● Did we apply AMTSL for every delivery?
● Did we recognize and respond to any obstetric emergency promptly?
● Did we communicate honestly, respectfully, and compassionately with every mother and family?
● Have we identified any case requiring maternal/perinatal death review?
A consistent, structured daily routine — from start-of-shift equipment verification to end-of-shift handover
— transforms individual clinical skill into a systemic maternal-newborn safety programme that operates
reliably across every shift, every delivery, and every mother and newborn whose survival depends on
genuine, continuous vigilance.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 54
CHAPTER 13: KEY PERFORMANCE INDICATORS (KPIs) FOR THE LABOUR
ROOM & MATERNITY TEAM
Objectives
● Measure labour monitoring compliance, emergency response performance, and maternal-newborn
safety objectively.
● Enable data-driven continuous improvement in labour room and maternity practice.
● Support NABH/JCI/LaQshya/MusQan accreditation standards for maternal-newborn care.
● Demonstrate the value and patient safety impact of the Labour Room team to institutional leadership.
Categories of Labour Room & Maternity KPIs
1. Monitoring and Process Compliance KPIs
KPI Definition Target
Partograph Compliance Rate % of labouring women monitored using partograph from
active phase
100%
AMTSL Compliance Rate % of vaginal deliveries with documented active
management of third stage
100%
WHO Safe Childbirth Checklist
Compliance
% of deliveries with checklist completed at all pause points 100%
2. Obstetric Emergency and Outcome KPIs
KPI Definition Target
Postpartum Haemorrhage Rate % of deliveries with PPH exceeding defined blood loss
threshold
At or below
institutional/national
benchmark
Eclampsia Rate Rate of eclamptic seizures among hypertensive
disorder cases
Minimize; track and
trend
Caesarean Section Rate (Robson
Classification)
C-section rate analysed by Robson ten-group
classification
Track against WHO-
recommended
benchmark by group
3. Newborn Outcome KPIs
KPI Definition Target
Fresh Stillbirth Rate Rate of fresh stillbirths per total births Minimize toward
zero for
intrapartum-
preventable cases
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 55
KPI Definition Target
Birth Asphyxia Rate % of newborns with low APGAR score requiring
resuscitation
Track and trend
against benchmark
NRP Provider Presence Rate % of deliveries with a trained NRP provider present 100%
4. Maternal Safety and Mortality KPIs
KPI Definition Target
Maternal Near-Miss Rate Rate of severe maternal complications meeting near-
miss criteria
Track and trend;
minimize
Maternal Death Review Completion
Rate
% of maternal deaths reviewed within defined
timeframe
100%
Perinatal Death Review Completion
Rate
% of applicable perinatal deaths reviewed within
defined timeframe
100%
5. Respectful Care and Patient Experience KPIs
KPI Definition Target
Birth Companion Presence Rate % of deliveries with a birth companion present per
woman's choice
≥ 90% (or
institutional target)
Informed Consent Documentation
Rate
% of interventions with documented genuine informed
consent
100%
Maternal Satisfaction Score % positive patient feedback on respectful care and
communication
≥ 85%
6. Governance and Certification KPIs
KPI Definition Target
Obstetric Emergency Drill Compliance % of scheduled emergency drills completed 100%
Staff NRP/Emergency Certification
Compliance
% of staff with current required certification 100%
CAPA Completion Rate % of maternal/perinatal death review corrective
actions completed on schedule
≥ 90%
Using KPIs for Continuous Improvement
● Review all Labour Room and Maternity KPIs regularly at maternal-newborn quality governance
meetings.
● Analyse PPH, eclampsia, and newborn outcome trends to identify targeted process improvements.
● Use Robson classification data to guide evidence-based caesarean section rate optimization.
● Present KPI data to hospital management to demonstrate the patient safety impact of maternity care
excellence.
● Use maternal/perinatal death review findings to strengthen protocols and system readiness
continuously.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 56
Labour Room and Maternity KPIs translate continuous, dual-patient vigilance into institutional
accountability — demonstrating that the investment in systematic partograph monitoring, active
management of labour, and rehearsed obstetric emergency response is a measurable, trackable, life-
saving patient safety programme for two lives, at the very moment life begins.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 57
CHAPTER 14: TOP 20 DO'S & TOP 20 DON'TS FOR THE LABOUR ROOM
& MATERNITY TEAM
Introduction
The Labour Room and Maternity team carries a responsibility unlike any other in medicine — continuous,
simultaneous vigilance over two lives whose safety cannot be separated. Their daily professional decisions —
about monitoring discipline, emergency readiness, and genuine respect for the labouring woman — determine
whether childbirth's overwhelming natural safety holds firm, and whether the rare catastrophic complication
is met with rehearsed precision rather than improvisation. These Do's and Don'ts provide the practical daily
architecture of Labour Room excellence.
TOP 20 DO'S FOR THE LABOUR ROOM & MATERNITY TEAM
● 1. Apply Partograph Monitoring to Every Labouring Woman — From the active phase onward, without
exception.
● 2. Apply AMTSL for Every Delivery — The single most effective haemorrhage prevention measure
available.
● 3. Complete the WHO Safe Childbirth Checklist at Every Pause Point — Admission, before delivery,
after birth, before discharge.
● 4. Recognize and Escalate Abnormal Partograph Trends Immediately — The alert line exists to be acted
upon, not merely observed.
● 5. Ensure a Trained NRP Provider at Every Delivery — The golden minute cannot wait for someone to
be called.
● 6. Apply Maternal Early Warning Scoring Consistently — Throughout labour and the postpartum
period, without lapse.
● 7. Obtain Genuine Informed Consent Before Every Intervention — Except in immediate life-
threatening emergency.
● 8. Support Birth Companion Presence — Per WHO recommendation and the woman's choice.
● 9. Verify Obstetric Emergency Equipment Every Shift — Readiness must be proven, not assumed.
● 10. Escalate Postpartum Haemorrhage Immediately — Minutes of delay cost blood volume that cannot
be recovered.
● 11. Administer Magnesium Sulphate Promptly for Severe Pre-eclampsia/Eclampsia — Per protocol,
without hesitation.
● 12. Estimate Blood Loss Objectively — Visual estimation alone underestimates true haemorrhage
volume.
● 13. Debrief After Every Significant Obstetric Emergency — Consolidate learning while it is fresh.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 58
● 14. Deliver Difficult News with Structure and Profound Compassion — Stillbirth and loss deserve
nothing less.
● 15. Test Obstetric Emergency Drills Regularly — A plan tested only in theory is not genuinely ready.
● 16. Coordinate Genuinely with Anesthesiology, Blood Bank, and Neonatal Teams — No single specialty
manages an obstetric emergency alone.
● 17. Provide Structured Handover for Every Transfer of Care — SBAR or equivalent, every time.
● 18. Support Early Breastfeeding Initiation — Per Baby-Friendly Hospital Initiative principles.
● 19. Report Every Incident Honestly — Including your own errors and near-misses.
● 20. Continue Learning — Obstetric and newborn care evidence evolves. The team that does not learn
continuously attends today's births with yesterday's protocols.
TOP 20 DON'TS FOR THE LABOUR ROOM & MATERNITY TEAM
● 1. Don't Skip or Delay Partograph Plotting — Every interval matters for catching abnormal progress in
time.
● 2. Don't Omit AMTSL for Any Vaginal Delivery — This is a non-negotiable, evidence-based standard.
● 3. Don't Skip Safe Childbirth Checklist Pause Points — Even during a busy, routine-feeling shift.
● 4. Don't Dismiss an Abnormal Partograph Trend — The alert line is a call to action, not a note to file.
● 5. Don't Leave a Delivery Without a Trained Resuscitation Provider Present — The golden minute has
no room for delay.
● 6. Don't Let Maternal Early Warning Scoring Lapse — Particularly during the highest-risk postpartum
hours.
● 7. Don't Proceed with Intervention Without Genuine Consent — Except in genuine, immediate life-
threatening emergency.
● 8. Don't Exclude a Birth Companion Without Genuine Clinical Justification — Respectful care includes
her choice of support.
● 9. Don't Allow Emergency Equipment Readiness to Lapse — Verify every shift, without exception.
● 10. Don't Delay Haemorrhage Escalation — Ad hoc, sequential response costs lives during active
bleeding.
● 11. Don't Delay Magnesium Sulphate for Severe Pre-eclampsia/Eclampsia — Seizure prevention
cannot wait.
● 12. Don't Rely on Visual Blood Loss Estimation Alone — It systematically underestimates true
haemorrhage.
● 13. Don't Skip Team Debriefing After a Critical Event — Unprocessed events repeat their gaps.
● 14. Don't Deliver Difficult News Without Structure or Privacy — Even amid the intensity of an active
shift.
● 15. Don't Skip Scheduled Obstetric Emergency Drills — An untested plan is an unreliable plan.
● 16. Don't Manage Obstetric Emergencies in Isolation — Coordinate across every specialty involved.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 59
● 17. Don't Hand Over Complex Cases Informally — Structure protects against critical omissions.
● 18. Don't Delay or Discourage Early Breastfeeding Without Genuine Clinical Reason — The first hour
matters.
● 19. Don't Hide or Minimize an Incident — Suppressed incidents cannot drive the improvement that
prevents recurrence.
● 20. Don't Practice Outside Current Obstetric and Newborn Care Evidence — Personal habit or outdated
method must never override current best practice.
Labour Room & Maternity Golden Rules
● Plot the partograph, every interval — abnormal progress caught early prevents obstructed labour.
● Apply AMTSL, every delivery — the most effective haemorrhage prevention available.
● Complete the safe childbirth checklist — at every pause point, every time.
● Have a resuscitation provider ready — the golden minute cannot wait.
● Score maternal early warning consistently — especially in the highest-risk postpartum hours.
● Obtain genuine consent — respect and safety are not in tension.
● Escalate haemorrhage immediately — minutes of blood loss cannot be recovered.
● Verify readiness every shift — assumed readiness is unreliable readiness.
● Coordinate across every specialty — no single discipline manages an obstetric emergency alone.
● Never stop learning — today's obstetric evidence is not yesterday's.
Daily Commitment Statement
“Today, I will apply systematic partograph monitoring, perform active management of the third stage for every
delivery, ensure a resuscitation provider is present at every birth, obtain genuine informed consent, escalate
every warning sign immediately, and uphold every safety standard without exception — because every mother
and every newborn depends on the vigilance I hold for both of them, together.”
The Top 20 Do's and Top 20 Don'ts are the daily professional architecture of Labour Room excellence —
each shaped by the understanding that maternity care is patient safety management practiced across two
lives simultaneously, and that there are no minor lapses when the moment life begins is the moment being
protected.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 60
CHAPTER 15: LABOUR ROOM & MATERNITY PROFESSIONAL PLEDGE
Introduction
A Labour Room and Maternity Professional Pledge is a formal, collective commitment to uphold the highest
standards of continuous monitoring, active management of labour, rehearsed emergency readiness, and
respectful maternity care. It serves as a daily affirmation that every partograph plotted, every uterotonic
administered, and every newborn received into skilled hands is an act of professional purpose in service of two
lives whose safety cannot be separated.
Purpose of the Pledge
● Reinforce the Labour Room team's collective identity as the guardians of the moment life begins.
● Promote a culture of systematic monitoring, active labour management, and honest incident review.
● Strengthen the commitment to rehearsed obstetric emergency response and skilled newborn
resuscitation.
● Support continuous professional development and maternal-newborn care excellence.
● Build institutional and community recognition of the Labour Room as the place where healthcare
keeps its oldest and most sacred promise.
Official Labour Room & Maternity Professional Pledge
“We solemnly pledge that as the Labour Room and Maternity team, we will fulfil our collective and individual
responsibilities with the highest standards of clinical vigilance, technical precision, and unwavering
commitment to every mother and every newborn whose safety we hold, simultaneously, in our hands.
We will apply systematic partograph monitoring to every labouring woman, plotting progress at defined
intervals without exception, and we will act immediately when that progress crosses the alert line that exists
specifically to give us time to intervene.
We will perform active management of the third stage of labour for every delivery, knowing that this single
evidence-based intervention prevents the majority of postpartum haemorrhage before it ever begins, and we
will escalate any sign of excessive bleeding immediately and without hesitation.
We will ensure a provider trained in newborn resuscitation is present at every birth, ready within the golden
minute for the newborn who does not breathe spontaneously, and we will apply maternal early warning
scoring consistently throughout labour and the vulnerable hours that follow.
We will obtain genuine informed consent before every intervention, support the presence of a birth companion
of the woman's choosing, and treat every mother with the dignity and respect that childbirth, at its most
vulnerable, demands — recognizing that respectful care and clinical safety are never in tension.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 61
We will maintain continuous readiness for the rare obstetric emergency — haemorrhage, eclampsia, shoulder
dystocia, cord prolapse — rehearsing our response until it is automatic, because two lives cannot wait for a
team to be assembled after the crisis has already begun.
We will communicate honestly and with profound compassion with every family, especially in the hardest
moments of complication or loss, and we will review every maternal death and significant perinatal loss
honestly, using every finding to protect the next mother and newborn who will never know their case drove
that improvement.
We will continuously expand our knowledge and skill — knowing that obstetric and newborn care evidence
evolves, and that the team that does not learn continuously attends today's births with yesterday's protocols.
With continuous vigilance, technical mastery, and genuine compassion for every mother and every newborn,
we pledge to be the Labour Room and Maternity team that keeps healthcare's oldest promise: that new life
will be brought into the world safely, and that the mother who brings it will be protected, respected, and never
left to face that moment alone.”
Daily Commitment Statement
“Today, we commit to applying systematic partograph monitoring, performing active management of labour
for every delivery, ensuring skilled newborn resuscitation readiness, obtaining genuine informed consent,
escalating every warning sign immediately, and upholding every safety standard — because every mother and
newborn depends on our vigilance for both of them, together.”
Core Values Reflected in the Pledge
1. Continuous Dual-Patient Vigilance
Systematic monitoring of mother and foetus/newborn as inseparable, simultaneous responsibilities.
2. Proactive Haemorrhage Prevention
Active management of the third stage applied for every delivery, without exception.
3. Golden-Minute Newborn Readiness
A trained resuscitation provider present and ready at every birth.
4. Respectful Maternity Care
Genuine informed consent, birth companion support, and dignity throughout labour.
5. Rehearsed Emergency Response
Drilled, protocol-driven readiness for the rare but catastrophic obstetric emergency.
6. Honest Communication
Compassionate, structured communication, especially in the hardest moments of complication or loss.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 62
7. Accountability
Every maternal death and significant perinatal loss reviewed honestly, without exception.
8. Continuous Learning
Obstetric and newborn care evidence evolves. Professional competence requires perpetual learning.
When the Pledge Should Be Recited
● At the beginning of every new Labour Room team member's appointment.
● At the start of a new departmental leadership role or shift responsibility.
● At maternal/perinatal death review and quality governance meetings.
● At NABH/JCI/LaQshya/MusQan accreditation preparation events.
● As a periodic collective affirmation, particularly following a significant maternal or perinatal event.
Benefits of the Pledge
For Mothers and Newborns
● Confidence that labour is monitored systematically, catching complications before they become crises.
● Assurance that a skilled resuscitation provider stands ready for the newborn's first moments.
● Trust that their dignity, choices, and voice are respected throughout labour and delivery.
For Families
● Confidence in a team genuinely ready for the rare emergency, not merely hoping it will not occur.
● Honest, compassionate communication throughout labour, delivery, and any complication.
● A birth experience remembered for dignity and safety, whatever its outcome.
For Healthcare Organizations
● Measurable improvement in maternal and newborn survival outcomes.
● Stronger NABH/JCI/LaQshya/MusQan accreditation performance in maternal-newborn care
standards.
● Reduced preventable maternal and perinatal mortality and their profound clinical, legal, and
reputational consequences.
Labour Room & Maternity Oath of Dual Vigilance
“We pledge to hold two lives in continuous vigilance — ensuring that every mother is monitored, protected,
and respected, and that every newborn is received into hands trained and ready for the single most important
minute of their life.”
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 63
Labour Room & Maternity Signature Commitment
This pledge is recited collectively by the multidisciplinary Labour Room and Maternity team and may be
individually signed by:
Name: ___________________________
Role: Obstetrician / Midwife / Labour Room Nurse / Neonatal Resuscitation Provider / Allied Maternity Care
Professional
Department: Labour Room & Maternity
Registration/Employee ID: _______________
Signature: ________________________
Date: ____________________________
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 64
CONCLUSION
No other clinical encounter asks a team to protect two lives in continuous, inseparable vigilance quite the way
childbirth does. For the overwhelming majority of mothers, this vigilance is invisible — experienced only as a
partograph quietly plotted, a uterotonic administered as a matter of routine, a resuscitation provider present
but never needed. Yet it is precisely this invisible, continuous readiness that allows childbirth to remain one of
the safest and most joyful moments in human life, and that stands ready, without warning, for the rare moment
it is not.
Throughout this manual, we have explored the full scope of Labour Room and Maternity professional practice
— from admission assessment and partograph-based monitoring, through active management of the third
stage of labour, obstetric emergency response, and newborn resuscitation, to respectful maternity care,
postnatal support, and the professional conduct that defines excellence across every category of childbirth.
These responsibilities collectively define a discipline that is simultaneously the most technically demanding and
the most profoundly human area of medicine — because no clinical skill matters if it is not delivered with
genuine respect for the woman experiencing one of the most vulnerable moments of her life.
The Importance of the Labour Room & Maternity Team in Healthcare Quality
● The dual-life guardian — holding continuous, simultaneous vigilance over mother and newborn.
● The deterioration detector — catching abnormal labour progress and maternal physiological warning
signs before they become crises.
● The haemorrhage preventer — applying active management of the third stage as the single most
effective intervention against the leading cause of maternal death.
● The golden-minute responder — ensuring every newborn who needs help receives it within the critical
first sixty seconds of life.
● The rehearsed emergency team — standing ready, drilled and coordinated, for the rare catastrophic
obstetric complication.
● The dignity protector — delivering respectful maternity care that honours every woman's autonomy
alongside her physical safety.
● The honest reviewer — examining every maternal death and significant perinatal loss to protect the
next mother and newborn.
Key Lessons from This Manual
Two Lives Cannot Be Protected Separately
Every monitoring decision, every intervention, and every emergency response in the Labour Room
simultaneously affects mother and newborn — excellence in this discipline means never treating one life's
safety as separable from the other's.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 65
Systematic Monitoring Prevents What Vigilance Alone Cannot Catch
The partograph, foetal heart rate monitoring, and maternal early warning scores exist because human
vigilance, however genuine, benefits from structured tools that catch gradual deterioration before it becomes
a crisis — systematic monitoring is not bureaucracy, it is the mechanism through which early warning becomes
early action.
Prevention Is More Powerful Than Response
Active management of the third stage of labour, applied proactively to every delivery, prevents far more
postpartum haemorrhage than even the most skilled emergency response could ever treat — the most
powerful patient safety intervention in the Labour Room happens before any emergency occurs.
Respectful Care and Clinical Safety Are Never in Tension
Genuine informed consent, birth companion support, and dignity throughout labour are not obstacles to safe
care — they are integral to it, recognized internationally as fundamental components of quality maternal care
rather than optional courtesies.
Rehearsal Transforms Rare Emergencies into Manageable Ones
Postpartum haemorrhage, eclampsia, shoulder dystocia, and cord prolapse are rare, but their rarity is precisely
why rehearsed, drilled response protocols matter most — a team that has practiced these scenarios responds
with the speed and precision that untested readiness cannot provide.
The Impact of Excellent Labour Room & Maternity Practice
● Every labouring woman monitored systematically, catching abnormal progress before it becomes
obstructed labour.
● Postpartum haemorrhage prevented proactively through active management of the third stage of
labour for every delivery.
● Every newborn who needs resuscitation receiving it within the golden minute from a trained, ready
provider.
● Obstetric emergencies met with rehearsed, coordinated, protocol-driven response rather than
improvisation.
● Every mother treated with the dignity, autonomy, and respect that quality maternity care demands.
● NABH/JCI/LaQshya/MusQan accreditation reflecting genuine, not merely documented, maternal-
newborn care excellence.
Final Commitment
“As the Labour Room and Maternity team, we commit to applying systematic partograph monitoring,
performing active management of labour for every delivery, maintaining continuous readiness for obstetric
emergency and newborn resuscitation, delivering respectful and honest communication, and upholding every
regulatory and ethical standard without exception — because every mother and every newborn depends on
the vigilance we hold for both of them, together, at the very moment life begins.”
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 66
Final Motto
“Two Lives Enter the Labour Room and Two Lives Must Leave It Safely — Every Contraction Watched, Every
Complication Anticipated, Every Mother and Newborn Protected.”
Together, We Are the Guardians of the Moment Life Begins — Ensuring Every Mother Is Protected, Every
Newborn Is Received Safely, and No One Faces That Moment Alone.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 67
REFERENCES
Global Accreditation and Regulatory Standards
● World Health Organization (WHO) – Standards for Improving Quality of Maternal and Newborn Care
in Health Facilities.
● Joint Commission International (JCI) – JCI Accreditation Standards for Hospitals: Care of Patients (COP)
Chapter, including Maternal and Newborn Care Requirements.
● National Accreditation Board for Hospitals & Healthcare Providers (NABH, India) – Standards for
Obstetric and Newborn Care Services (5th Edition).
● International Society for Quality in Health Care (ISQua) – Guidelines and Principles for Health and Social
Care Standards, applied to Maternal-Newborn Services.
National Maternal-Newborn Quality Improvement Initiatives (India)
● Ministry of Health and Family Welfare, Government of India – LaQshya (Labour Room Quality
Improvement Initiative) Guidelines.
● Ministry of Health and Family Welfare, Government of India – MusQan (National Quality Improvement
Initiative for Newborn Care) Guidelines.
● Ministry of Health and Family Welfare, Government of India – Janani Suraksha Yojana and Janani
Shishu Suraksha Karyakram Guidelines.
Obstetric Society and Professional Body Guidelines
● Federation of Obstetric and Gynaecological Societies of India (FOGSI) – Good Clinical Practice
Recommendations.
● Royal College of Obstetricians and Gynaecologists (RCOG) – Green-top Guidelines on Obstetric
Emergencies.
● American College of Obstetricians and Gynecologists (ACOG) – Practice Bulletins on Obstetric Care.
● International Confederation of Midwives (ICM) – Global Standards for Midwifery Practice.
Labour Monitoring and Delivery Standards
● World Health Organization – WHO Labour Care Guide and Partograph Implementation Guidance.
● World Health Organization – WHO Safe Childbirth Checklist Implementation Guide.
● World Health Organization – WHO Recommendations on Postpartum Haemorrhage Prevention and
Treatment.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 68
Newborn Resuscitation and Essential Newborn Care Standards
● American Academy of Pediatrics / American Heart Association – Neonatal Resuscitation Program (NRP)
Guidelines.
● World Health Organization – Guidelines on Basic Newborn Resuscitation and Essential Newborn Care.
● World Health Organization / UNICEF – Baby-Friendly Hospital Initiative (BFHI) Implementation
Guidance.
Hypertensive Disorders and Obstetric Emergency Standards
● International Society for the Study of Hypertension in Pregnancy (ISSHP) – Classification and
Management Guidelines.
● Royal College of Obstetricians and Gynaecologists (RCOG) – Shoulder Dystocia and Cord Prolapse
Green-top Guidelines.
Maternal and Perinatal Death Review Standards
● World Health Organization – Maternal Death Surveillance and Response (MDSR) Technical Guidance.
● World Health Organization – Making Every Baby Count: Perinatal Death Review and Audit Guidance.
● Ministry of Health and Family Welfare, Government of India – Maternal Death Review and Confidential
Review Guidelines.
Indian Regulatory and Statutory Framework
● National Medical Commission (NMC) – Code of Medical Ethics Regulations Applicable to Obstetric
Care.
● Clinical Establishments (Registration and Regulation) Act, India – Applicable Maternal-Newborn Care
Regulatory Requirements.
● Pre-Conception and Pre-Natal Diagnostic Techniques (PCPNDT) Act, India – Applicable Statutory
Requirements.
● Medical Termination of Pregnancy (MTP) Act and Rules, India – Applicable Statutory Requirements.
Quality Improvement and Patient Safety Frameworks
● Institute for Healthcare Improvement (IHI) – Framework for Patient Safety and Quality Improvement
in Maternal-Newborn Care.
● World Health Organization – Global Patient Safety Action Plan 2021–2030, including Maternal and
Newborn Safety Priorities.
● Robson Classification System – WHO-Endorsed Ten-Group Classification for Caesarean Section Audit.
Cybersecurity and Digital Health Records
● NIST Cybersecurity Framework – Applied to Healthcare Maternal-Newborn Information Systems.
● HL7 International – Health Level Seven Data Interchange Standards.
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 69
This manual has been developed using internationally recognized principles and best practices from WHO
Standards for Improving Quality of Maternal and Newborn Care, WHO Labour Care Guide and Safe Childbirth
Checklist, JCI Care of Patients Standards, NABH Obstetric and Newborn Care Standards, India's LaQshya and
MusQan National Quality Improvement Initiatives, FOGSI/RCOG/ACOG obstetric guidelines, Neonatal
Resuscitation Program (NRP) protocols, WHO Maternal Death Surveillance and Response guidance, applicable
Indian statutory requirements including the PCPNDT Act and MTP Act, and international maternal-newborn
patient safety frameworks. Institutions should verify current versions of all cited guidelines and regulatory
requirements, as clinical protocols and accreditation standards are subject to periodic revision.
ॐ जय माता द( ॐ
Labour Room & Maternity Excellence Manual Dr J L Meena
Labour Room & Maternity Excellence Manual – Dr J L Meena | Page 70

END OF MANUAL
Thank You
This manual has been prepared with the vision to empower the multidisciplinary Labour Room and Maternity
team with global standards, best practices, and professional guidance to ensure safe, respectful, and vigilant
care for mother and newborn alike.
Our Commitment Continues
The journey of learning never ends. As obstetric and newborn care evidence evolves and maternal-newborn
safety science advances, our commitment to patient safety, respectful care, quality, and continuous vigilance
must remain unwavering.
Together, We Build Trust
Every partograph plotted, every uterotonic administered on time, every newborn received into ready hands,
and every mother treated with genuine dignity contributes to one greater purpose — a healthcare system that
keeps its oldest promise, that new life will always be brought into the world safely.
“Two Lives Enter the Labour Room and Two Lives Must Leave It Safely — Every Contraction
Watched, Every Complication Anticipated, Every Mother and Newborn Protected.”
REMEMBER: Safety is our priority • Vigilance is our discipline • Dignity is our standard • Two lives are our
purpose • Learning is our journey
Thank you for being a part of this vital mission. Your dedication makes a difference every day.
Dr J L Meena