










Part 6
Chapter 35
Agents Used in Dyslipidemia
• Atherosclerosis is the leading cause of death for both men and women in the Western world.
• Drugs discussed in this chapter:
o Prevent the sequelae of atherosclerosis (heart attacks, angina, PAD, ischemic stroke)
o Decrease mortality in patients with a history of cardiovascular disease and hyperlipidemia.
o Generally safe and effective
o Can cause problems, including:
▪ Drug-drug interactions
▪ Toxic reactions in skeletal muscle and the liver
HYPERLIPOPROTEINEMIA
Pathogenesis
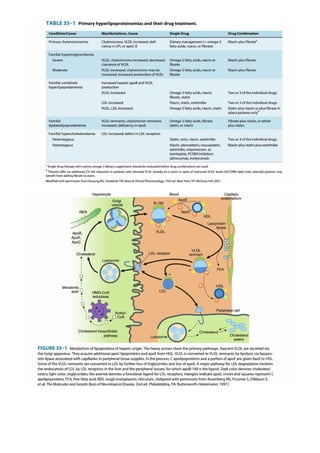
Atherosclerosis and Lipid Profile
• Premature or accelerated development of atherosclerosis is strongly associated with:
o Elevated LDL levels (that participate in cholesterol transport)
• Also associated with increased risk of atherosclerosis:
o Depressed HDL levels
o Hypertriglyceridemia (in some families)
Chylomicronemia
• The occurrence of chylomicrons in the serum while fasting
• A recessive trait
• Correlated with a high incidence of acute pancreatitis
• Managed by restriction of total fat intake
Regulation of plasma lipoprotein levels involves a complex interplay of:
• Dietary fat intake
• Hepatic processing
• Utilization in peripheral tissues
Causes of Dysregulation
Primary (Genetic) disturbances
• Mutations in apolipoproteins, their receptors, transport mechanisms, & lipid-metabolizing enzymes
Secondary disturbances
• Western diet
• Many endocrine conditions
• Diseases of the liver or kidneys
Treatment Strategies
Diet
• Cholesterol and saturated fats
o The primary dietary factors that contribute to elevated levels of plasma lipoproteins.
• Dietary measures (restrictions)
o The first method of management
o Designed to reduce the total intake of cholesterol and saturated fats.
o May be sufficient to reduce lipoprotein levels to a safe range.
• Alcohol
o Raises TG and VLDL levels.
o Thys, should be avoided by patients with hypertriglyceridemia.
Drugs
• The choice of drug treatment is based on the lipid abnormality.
Most effective at lowering LDL-C
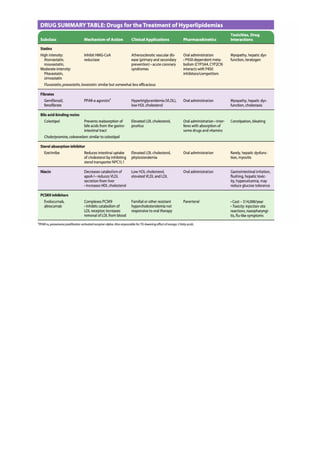
• Statins (HMG-CoA reductase inhibitors)
• Bile acid sequestrants (resins)
• Ezetimibe
• PCSK9 inhibitors
Most effective at lowering TG and VLDL levels and raising HDL-C
• Fibrates
• Niacin (B3)
• Marine omega-3 fatty acids
STATINS (HMG-COA REDUCTASE INHIBITORS)
Mechanism and Effects
HMG-CoA reductase
• Catalysis the conversion of HMG-CoA to mevalonate
(which is the rate-limiting step in hepatic cholesterol synthesis)
Statins Mechanism of Action
1. Statins are structural analogs of HMG-CoA
2. Statins competitively inhibit HMG-CoA reductase
Statins Drug Form
o Prodrugs: Lovastatin and simvastatin
o Active drugs: Other statins (atorvastatin, fluvastatin, pravastatin, pitavastatin, and rosuvastatin)
The cause of the serum cholesterol-lowering effect
Direct inhibition (minor contribution)
• Statins directly inhibit hepatic cholesterol synthesis
Indirect LDLR upregulation (major contribution)
• In response to a reduction in hepatic pool of cholesterol, the liver compensates by increasing the number of
high-affinity LDLRs, resulting in increased clearance of circulating LDL and VLDL remnants.
• Functional LDLRs are required to achieve a therapeutic LDL-lowering effect with statins.
Other Clinically Beneficial Effects of Statins
• Direct antiatherosclerotic and anti-inflammatory effects
• Prevention of bone loss
Clinical Use
Lipid Effect
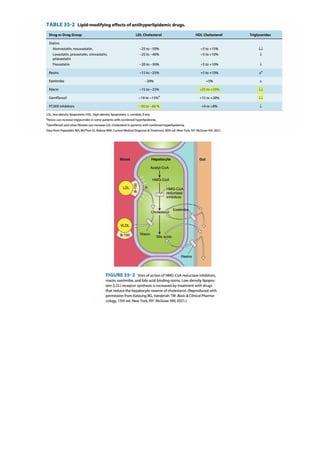
• LDL-C levels reduction (dramatically)
(especially when used in combination with other cholesterol-lowering drugs)
Advantages
• Commonly used because they are effective and well tolerated.
Clinical benefits
• Reduced risk of coronary events
• Reduced mortality in patients with IHD
• Reduced risk of ischemic stroke
Classification by LDL-C Reduction
High-intensity statins
• Reduce LDL-C by 50%
• Include: Rosuvastatin and atorvastatin
• Also reduce TG and increase HDL-C in patients with TG levels > 250 mg/dL and reduced HDL-C levels
Moderate-intensity statins
• Reduce LDL-C by 30-50%
• Include: Pitavastatin and simvastatin
Low-intensity statins
• Reduce LDL-C by <30%
• Include: Other statins
Toxicity
Liver
• Mild elevations of serum aminotransferases (common)
• Not often associated with hepatic damage.
• Patients with preexisting liver disease may have more severe reactions.
Skeletal muscle
• Elevated serum CK, released from skeletal muscle (in ≈10% of patients)
• Severe muscle pain and even rhabdomyolysis may occur rarely.
Drug and Food Interactions
• Most statins are metabolized by the cytochrome P450 system.
• Drugs or foods that inhibit cytochrome P450 activity increase the risk of hepatotoxicity and myopathy.
o Such as grapefruit juice
Pregnancy
• Statins are teratogenic; Thus, should be avoided in pregnancy.
RESINS (BILE ACID SEQUESTRANTS)
Mechanism and Effects
Bile Acids Characteristics
• Bile acids are metabolites of cholesterol.
• Normally, over 90% of bile acids are reabsorbed in the GI tract and returned to the liver for reuse.
Resins Characteristics
• Include: Cholestyramine, colestipol, colesevelam
• Large nonabsorbable polymers
Mechanism
1. Resins bind bile acids and similar steroids in the intestine and prevent their absorption and recycling.
2. Hepatic cholesterol is diverted toward synthesis of new bile acids
3. The tightly regulated hepatic cholesterol pool decreases.
4. As a compensatory response, high-affinity LDLRs in the liver are upregulated.
5. Removal of circulating LDL increases.
Lipid Effects
• Modest reduction in LDL-C levels
• Little effect on HDL-C or TG (VLDL) levels
• In patients with a genetic condition that predisposes them to hypertriglyceridemia and hypercholesterolemia
(FCH), resins increase TG and VLDL levels.
Clinical Use
• Hypercholesterolemia
• Reduction of pruritus in patients with cholestasis and bile salt accumulation.
Toxicity
• Bloating, constipation, an unpleasant gritty taste
Impairment of absorption of:
• Vitamins (eg, vitamin K, dietary folates)
• Drugs (eg, thiazide diuretics, warfarin, pravastatin, fluvastatin)
EZETIMIBE
Mechanism and Effects
Activation
• Ezetimibe is a prodrug that is converted in the liver to the active glucuronide form.
Mechanism
1. Its active metabolite inhibits a transporter that mediates GI uptake of cholesterol and phytosterols.
2. Absorption of dietary and biliary-excreted cholesterol are prevented.
3. The tightly regulated hepatic cholesterol pool decreases.
4. As a compensatory response, high-affinity LDLRs in the liver are upregulated.
5. Removal of circulating LDL increases.
Lipid Effect
• As monotherapy, reduces LDL-C by ≈20%.
• When combined with a statin, it is even more effective.
Clinical Use
• Hypercholesterolemia
• Phytosterolemia (a rare genetic disorder that results from impaired export of phytosterols)
Toxicity
• Ezetimibe is well tolerated.
• When combined with statins, it may increase the risk of hepatic toxicity.
• Serum concentrations of the glucuronide form are:
o Increased by fibrates
o Reduced by cholestyramine
NIACIN (NICOTINIC ACID) – B3
Mechanism and Effects
Lipid Effect
• Reduces LDL-C, TG, and VLDL
• Increases HDL-C
• These effects are not seen with nicotinamide.
Mechanism
In liver:
• Niacin reduces hepatic VLDL synthesis, which in turn reduces LDL and VLDL-TG levels.
In adipose tissue:
1. Niacin reduces HSL activity in adipose tissues and thus decreases plasma FFA.
2. With reduced FFA delivery to the liver, VLDL and subsequently LDL formation are reduced.
3. Thus, plasma LDL-C and VLDL-TG levels decrease.
↓ HSL activity → ↓ FFA release → ↓ hepatic TG synthesis → ↓ VLDL formation → ↓ TG & LDL levels
Other mechanisms:
• Niacin increases VLDL clearance by the LPL on capillary ECs, resulting in reduced TG levels.
• Niacin reduces the catabolic rate for HDL.
• Niacin decreases circulating fibrinogen and increases t-PA.
Clinical Use
• Hypercholesterolemia
• Hypertriglyceridemia
• Low levels of HDL-C
• Wide clinical usefulness
Toxicity
• Cutaneous flushing
o Common
o Pretreatment with aspirin or other NSAIDs reduces the intensity of this flushing
o Improvement of flushing with aspirin indicates that this reaction is mediated by prostaglandins.
o Tolerance to the flushing reaction usually develops within a few days.
• Dose-dependent nausea and abdominal discomfort often occur.
• Pruritus and other skin conditions are reported.
• Moderate elevations of liver enzymes and even severe hepatotoxicity may occur.
• Severe liver dysfunction
(associated with an extended-release preparation which is not the same as the sustained-release formulation)
• Hyperuricemia (in ≈20% of patients)
• Carbohydrate tolerance (may be moderately impaired)
FIBRIC ACID DERIVATIVES (FIBRATES)
Mechanism and Effects
• e.g., gemfibrozil, fenofibrate
Mechanism
LPL Enhancement
1. Fibrates are ligands for the PPAR-α
(PPAR is a receptor that regulates transcription of genes involved in lipid metabolism)
2. Via PPAR activation, LPL synthesis increases.
(LPL is synthesized in adipose, skeletal, and cardiac muscle cells and then transported to and anchored on the
luminal surface of capillary ECs, where it functions to hydrolyze TGs in circulating chylomicrons and VLDL.)
3. Clearance of TG-rich lipoproteins is enhanced.
VLDL Synthesis
1. Fibrates stimulate fatty acid oxidation in the liver.
2. This limits TG supply, resulting in decreased VLDL synthesis.
Other Mechanism
• Fibrates also decrease expression of apoC-III, which impedes the clearance of VLDL
• Fibrates increase the expression of apoA-I and apoA-II, which in turn increases HDL levels.
LDL Levels
• In most patients, fibrates have little or no effect on LDL levels.
• However, fibrates can increase LDL-C in patients with a genetic condition called FCH.
In FCH, LPL enhancement by fibrates accelerates the conversion of VLDL and VLDL remnants to LDL, which
may cause a transient increase in LDL-C despite reductions in VLDL-TG levels.
Clinical Use
• Hypertriglyceridemia
• Because these drugs have only a modest ability to reduce LDL-C and can increase LDL-C in some patients, they
might be combined with other cholesterol-lowering drugs for treatment of patients with elevated levels of
both LDL and VLDL.
(enhanced LPL-mediated metabolism of VLDL can increase the formation of LDL, leading to a rise in LDL-C)
• Adding a fibrate to a high-intensity statin
o Does not confer further cardiovascular risk reduction
o Increases risk of toxicity
o No longer recommended as initial approach in patients with elevated LDL-C and TG (VLDL).
Toxicity
• Nausea is the most common adverse effect with all fibrates.
• Skin rashes are common with gemfibrozil.
• A few patients show decreases in WBC count or hematocrit
• These drugs can potentiate the action of anticoagulants.
• There is an increased risk of cholesterol gallstones
(Fibrates increase cholesterol excretion into bile)
Thus, fibrates should be used with caution in patients with a history of cholelithiasis.
• When used in combination with statins, the risk of myopathy increases.
COMBINATION THERAPY
• Dietary modification
o The first step in the treatment of all patients with hyperlipidemia
o Often insufficient and drugs must be added.
• Drug combinations
o Often required to achieve the:
▪ Maximum lowering possible with minimum toxicity
▪ Desired effect on the various lipoproteins (LDL, VLDL, and HDL)
• Certain drug combinations provide advantages, whereas others present specific challenges.
• Resins interfere with the absorption of certain statins (pravastatin, atorvastatin, and fluvastatin)
Therefore, these must be given at least 1 h before or 4 h after the resins
• The combination of statins with either fibrates or niacin increases the risk of myopathy.
DRUGS RESTRICTED TO PATIENTS WITH HOFH & TREATMENT-RESISTANT
HYPERCHOLESTEROLEMIA
Lomitapide
• Mechanism
1. Lomitapide is a MTP inhibitor
2. MTP inhibition decreases VLDL secretion and consequently plasma LDL levels.
(MTP is required for the accretion of TGs to nascent VLDL in liver and to chylomicrons in the intestine)
• The only indication:
o HoFH
• Adverse effect
o Can cause accumulation of TGs in the liver and elevations in transaminases.
Mipomersen
• Mechanism
o An antisense oligonucleotide that targets apoB-100, mainly in the liver.
• Side effects
o Mild to moderate injection site reactions and flu-like symptoms can occur.
PCSK9 Inhibitors
• Include: Evolocumab and alirocumab
• Mechanism
o Both are humanized antibodies to the enzyme PCSK9.
(PCSK9 transports the LDLR to the lysosome for degradation)
• Lipid effect
o LDL reductions of up to 70%
• Adverse effects
o Local reactions at the injection site, upper respiratory and flu- like symptoms.
• These drugs should be approached with caution because of its established role in normal cell biology.
• Expensive
SKILL KEEPER
ANGINA
• The antihyperlipidemic drugs, especially the statins, are commonly used to treat patients with IHD.
• Angina is one of the most common manifestations of IHD and coronary atherosclerosis.
Questions
• What are the 3 major forms of angina?
• Name the 3 major drug groups used to treat angina and specify which form of angina each is useful for.
Answers
The 3 major forms of angina:
• Angina of effort
o Associated with a fixed plaque that partially occludes one or more coronary arteries
• Vasospastic angina
o Involves unpredictably timed, reversible coronary spasm
• Unstable angina
o Often immediately precedes a MI and requires emergency treatment.
The 3 major drug groups used in angina
• Nitrates
o Used for treatment of all 3 types of angina
• CCBs
o Useful for treatment of angina of effort and vasospastic angina
o Can be added to β blockers and nitroglycerin in patients with refractory unstable angina
• β blockers
o Not useful in vasospastic angina or for an acute attack of angina of effort
o Primarily used for prophylaxis of angina of effort
o Also used in emergency treatment of ACSs.
KEY POINTS FROM “QUESTIONS” SECTION
• HoFH
o Etiology: Most commonly caused by mutations leading to dysfunctional LDLRs
o Lomitapide and mipomersen are specifically indicated for HoFH.
o Statins will not work in patient with HoFH
(Because statins rely on functional LDLRs to achieve a LDL-lowering effect)
• A dramatic increase in HDL-C (e.g., doubling of HDL) strongly suggests niacin therapy.
• In patients with FCH and elevated VLDL (TG):
o Resins are not recommended (because they increase VLDL and TG levels while lowering LDL-C)
• Statins
o Contraindicated in pregnancy because of the risk of teratogenic effects.
o The 2 primary adverse effects:
▪ Hepatotoxicity
• LFTs should be performed before starting therapy, and at regular intervals as needed
during therapy.
• Markers of hepatocellular toxicity: Serum ALT and AST levels
▪ Myopathy
• Fibrates
o mechanism of action:
▪ Increase activity of the LPL associated with capillary ECs
▪ Decrease VLDL secretion, presumably by stimulating hepatic fatty acid oxidation.
o A major toxicity
▪ Increased risk of gallstone formation (due to enhanced biliary excretion of cholesterol)
• Chronic ethanol ingestion
o Increases serum VLDL and TG levels (thereby placing patients with alcoholism at risk of pancreatitis)
o Also raises serum HDL levels.
• Niacin can exacerbate:
o Hyperuricemia
o Glucose intolerance
Abbreviations:
ACS = acute coronary syndrome
CK = creatine kinase
ECs = endothelial cells
FCH = familial combined hyperlipidemia
FCH = familial combined hyperlipoproteinemia
GI = gastrointestinal
HDL = high-density lipoprotein
HMG-CoA = hydroxymethylglutaryl coenzyme A
HoFH = Homozygous familial hypercholesterolemia
HSL = hormone-sensitive lipase
IHD = ischemic heart disease
LDL = low-density lipoprotein
LDL receptor = LDLR
LPL = lipoprotein lipase
MI = myocardial infarction
MTP = microsomal triglyceride transfer protein
NSAIDs = nonsteroidal anti-inflammatory drugs
PAD = peripheral arterial disease
PPAR-α = peroxisome proliferator-activated receptor-alpha
TG = triglyceride
T-PA = tissue plasminogen activator
VLDL = very-low-density lipoprotein
Meanings:
Marine = originating from the sea or ocean.
Explanations:
Phytosterols = plant sterols that normally enter GI epithelial cells but then are immediately transported back into the intestinal lumen.
FCH is associated with a combined increase in VLDL-TG and LDL-C.
Editor: Erfan Hosseinmardi
Reference: Katzung & Trevor's pharmacology examination & board review, 13th Edition
Contact Me: erfanhosseinmardi24@gmail.com or erfan.hosseinmardi@iran.ir
Katzung, Part 6, Chapter 35, Agents Used in Dyslipidemia