INTRODUCTION
• Juvenile IdiopathicArthritis (JIA) –
• most common paediatric rheumatological disease
• Heterogenous group of disorders.
• significant long term morbidity.
• Juvenile Rheumatoid Arthritis ( by ACR –American College of Rheumatology)
or Juvenile Chronic Arthritis ( by ELAR – European League Against
Rheumatology).
3.
DEFINITION
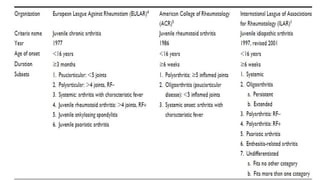
• International Leagueof Association for Rheumatology ( ILAR ) proposed
uniform definition And classification criteria for JIA.
• Arthritis in > 1 joints
• (Swelling OR effusion OR the presence of 2 or more of the following
signs :limitation of range of motion , pain or tenderness on motion , increased
heat)
• Age of onset – before 16 years
• Duration > 6 weeks
• Exclusion of other forms of juvenile arthritis .
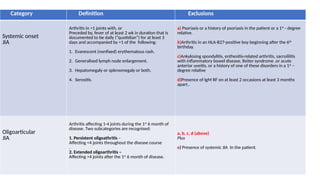
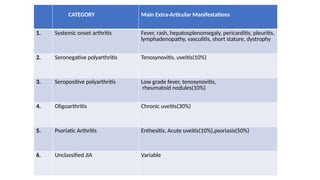
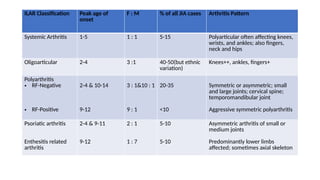
Category Definition Exclusions
Systemiconset
JIA
Arthritis in >1 joints with, or
Preceded by, fever of at least 2 wk in duration that is
documented to be daily (“quotidian”) for at least 3
days and accompanied by >1 of the following:
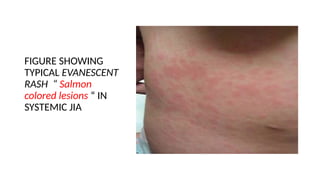
1. Evanescent (nonfixed) erythematous rash.
2. Generalised lymph node enlargement.
3. Hepatomegaly or splenomegaly or both.
4. Serositis.
a) Psoriasis or a history of psoriasis in the patient or a 1st
- degree
relative.
b)Arthritis in an HLA-B27-positive boy beginning after the 6th
birthday.
c)Ankylosing spondylitis, enthesitis-related arthritis, sacroiliitis
with inflammatory bowel disease, Reiter syndrome ,or acute
anterior uveitis, or a history of one of these disorders in a 1st
–
degree relative
d)Presence of IgM RF on at least 2 occasions at least 3 months
apart..
Oligoarticular
JIA
Arthritis affecting 1-4 joints during the 1st
6 month of
disease. Two subcategories are recognised:
1. Persistent oligoathritis –
Affecting <4 joints throughout the disease course
.
2. Extended oligoarthritis –
Affecting >4 joints after the 1st
6 month of disease.
a, b, c, d (above)
Plus
e) Presence of systemic JIA In the patient.
7.
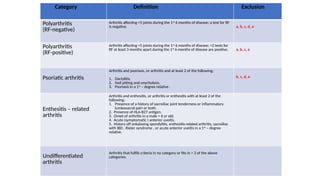
Category Definition Exclusion
Polyarthritis
(RF-negative)
Arthritisaffecting >5 joints during the 1st
6 months of disease; a test for RF
is negative. a, b, c, d, e
Polyarthritis
(RF-positive)
Arthritis affecting >5 joints during the 1st
6 months of disease; >2 tests for
RF at least 3 months apart during the 1st
6 months of disease are positive. a, b, c, e
Psoriatic arthritis
Arthritis and psoriasis, or arthritis and at least 2 of the following;
1. Dactylitis.
2. Nail pitting and onycholysis.
3. Psoriasis in a 1st
– degree relative .
b, c, d, e
Enthesitis – related
arthritis
Arthritis and enthesitis, or arthritis or enthesitis with at least 2 of the
following:
1. Presence of a history of sacroiliac joint tenderness or inflammatory
lumbosacral pain or both.
2. Presence of HLA-B27 antigen.
3. Onset of arthritis in a male > 6 yr old.
4. Acute (symptomatic ) anterior uveitis.
5. History off ankylosing spondylitis, enthesitis-related arthritis, sacroiliac
with IBD , Rieter syndrome , or acute anterior uveitis in a 1st
– degree
relative.
Undifferentiated
arthritis
Arthritis that fulfils criteria in no category or fits in > 2 of the above
categories.
8.
ETIOLOGY AND PATHOGENESIS
1.The aetiology and pathogenesis of JIA are not completely
understood. Genetic susceptibility plays a major role, but there is
significant overlap between loci associated with JIA and those
associated with other autoimmune diseases.
2. JIA is genetically complex disorder in which multiple genes are
important for disease onset and manifestations.
9.
PATHOGENESIS
1. JIA hasbeen suggested to be a Th1 cell mediated disorder, driven by
a population of T cells producing inflammatory cytokines and
chemokines.
Most important cytokines involved in pathogenesis of JIA are:
TNF-alpha, IL-1 , IL-6.These cytokines play roles in specific
immunological processes that promote autoimmunity, chronic
inflammation, and tissue destruction .
10.
• 2.Heat shockproteins(HSP60)- autoantigen on the synovial
membrane in patients with JIA.
• CHEMOKINES:CCR5, RANTES and CXCR3.
• Calcium Binding Proteins: S100A8, S100A9, S100A12, produced from
activated neutrophils and monocytes, are increased in oligoarticular &
polyarticular JIA & correlate with severity of joint inflammation.
11.
GENETICS of JIA
Associationsbetween HLA and JIA have been reported.
• E.g HLA-A2 – Early disease onset
HLA-B27- Enthesitis related arthritis
HLA-DRB1*08,11 and 13 ,HLA-DBP1*02- Caucasian
children with JIA.
HLA-DRB1*0405- Asian children with JIA.
• Another non HLA genes associated are e.g. MIF, NRAMP1, PTPN22, TNFA, and WISP3
• Strong association between
TNFAIP3 variant - Oligoarticular JIA
STAT4 variant – Polyarticular JIA
12.
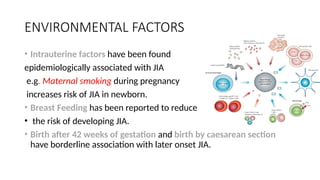
ENVIRONMENTAL FACTORS
• Intrauterinefactors have been found
epidemiologically associated with JIA
e.g. Maternal smoking during pregnancy
increases risk of JIA in newborn.
• Breast Feeding has been reported to reduce
• the risk of developing JIA.
• Birth after 42 weeks of gestation and birth by caesarean section
have borderline association with later onset JIA.
13.
• INFECTIOUS AGENTS:
VIRUSES like parvovirus B19 and Ebstein Barr virus in primis.
BACTERIAL AGENTS like Salmonella spp, Shigella spp, Campylobacter
spp, Mycoplasma pneumoniae, Bartonella henselae, and Streptococcus
pyogenes.
• OTHER FACTORS :
a)Heat shock proteins
b)Abnormal reproductive hormone levels
c) Joint trauma
14.
CLINICAL MENIFESTATIONS:JIA
• Jointswelling
• Stiffness that typically is worse in the morning or after a nap
• Pain may limit/loss movement of the affected joint.
• Commonly affects the knees and joints in the hands and feet
• One of the earliest signs of JIA may be limping in the morning
because of an affected knee.
Besides joint symptoms, children with systemic JIA have
• A high fever and a light skin rash. The rash and fever may
appear and disappear very quickly.
• Swelling in the lymph nodes located in the neck and other
parts of the body
• In some cases (<50%) , internal organs ( heart and, very rarely ,
the lungs) may be involved.
MACROPHAGE ACTIVATION SYNDROME(MAS)
•MAS is a rare but potentially fatal complication of a sJIA that can
occur at any time ( onset, medication change, active or remission)
during the disease course.
• Also referred as “secondary hemophagocytic syndrome or
hemophagocytic lymphohistiocytosis(HLH)”
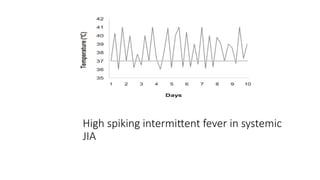
• CLINICAL MANIFESTATIONS: High spiking fever, Profound anaemia,
lymphadenopathy, hepatosplenomegaly, Purpura, mucosal bleeding
and encephalopathy.
21.
• LAB INVESTIGATIONS:1)CBC-Thrombocytopenia(<1.8 Lac/L) and
leukopenia.
2)elevated liver enzymes(AST>48 U/L), lactate dehydrogenase,
ferritin(>684ng/ml) and triglycerides(>156mg/Dl).
3) ↓Fibrinogen(≤360mg/dL)elevated fibrin split products, prolonged
PT and aPTT.
4) falling ESR- A feature useful in distinguishing MAS from flare of
systemic disease.
5) Elevated sCD25 and sCD163.
22.
• DIAGNOSIS :Based on clinical criteria discussed before and confirmed
by bone marrow biopsy demonstrating hemophagocytosis AND
increased CD163 staining of bone marrow.
• TREATMENT :1)I/V Glucocorticoid Therapy-a)mPSL Therapy
b)dexamethasone
2)I/V cyclosporine therapy
3)Anticoagulant therapy
4)Apheresis therapy
23.
APPROACH Considerations
• Thediagnosis of JIA is based on the history and physical examination
findings.
• No laboratory studies are diagnostic for JIA, and indeed, all laboratory
study findings may be normal in children with this disorder.
However, laboratory studies help to exclude other underlying
disorders, classify the type, and evaluate for extra-articular
manifestations of JIA.
24.
Laboratory Investigations
• CBC(Completeblood count)
• ANA(Antinuclear Antibody)-
- 70% oligoarticular JIA – Positive ANA
- Raise suspicion of SLE
-increased risk of Anterior uveitis
• Fibrinogen, ferritin and D-dimer- elevated in systemic
onset JIA
• Antistreptolysin O(ASO) and anti-DNAse B- elevated in
acute rheumatic fever or post streptococcal arthrirtis.
• Urinalysis- to r/o SLE( Proteinurea >0.5 g/d or 3+ positive
on dipstick test or cellular cast)
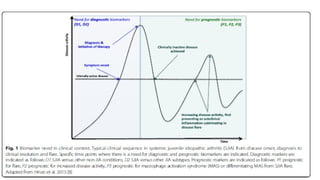
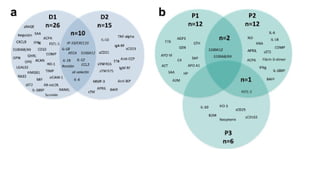
BIOMARKERS in JIA
•Diagnostic and Prognostic
• DIAGNOSTIC :
2 types – those identifying SJIA VERSUS
1)non-SJIA or healthy controls
2)other non-SJIA subtypes
• PROGNOSTIC :
3 types – those for prediction of
1)Disease flare
2)increased ds activity +/_ discrimination of active versus inactive ds
3)MAS
• MECHANISTIC Markers – Specific
• PROXY Markers – non specific e.g. CRP
• CANDIDATE Markers
Goals of Treatment
1.Eliminate active Ds
2. Normalise joint function
3. Preserve normal growth
4. Prevent long term outcome
5. Prevent patient disability
36.
ACR(American College of
Rheumatology)criteriafor complete Remission
• No inflammatory joint pain
• No morning stiffness
• No fatigue
• No synovitis
• No progression of damage, as determined in sequential radiographic
examinations
• No elevation of ESR and CRP levels
BIOLOGICAL AGENTS
1)TNF alphainhibitors-
DRUG Mechanism of Action
Etanercept Soluble TNF p75 receptor fusion protein that binds to and inactivates TNF alpha
Adalimumab A Humanised IgG1 monoclonal antibody that binds to TNF alpha
Infliximab Chimeric human/mouse monoclonal antibody that binds to soluble TNF alpha &
its membrane bound precursor, neutralising its action
39.
2)MODULATOR OF Tcell Activation-
ABATACEPT-
• Selective inhibitor of T cell costimulation
3)B cell Depletion-
RITUXIMAB-
• Chimeric monoclonal antibody to antigen CD20,A Transmembrane protein on
the surface of B cell precursors and mature B lymphocytes
• RF+ve pJIA(Failed 2 TNF-alpha inhibitors)-ACR
4)IL-1 Antagonists-
ANAKINRA-
• Human IL-1 receptor antagonist inhibiting both IL-1alpha & IL-1beta
CANAKINUMAB-
• IL-1beta antagonist
40.
5)IL-6 Receptor inhibitor-
TOCILIZUMAB-Bindto both soluble and membrane associated receptors
• i/v infusion
• Dose->30kg – 8mg/kg
<10kg – 10mg/kg
• RF –VE pJIA(failed 2 TNF- alpha inhibitors)
ADVERSE EFFECTS OF BIOLOGICAL AGENTS-
1)Pain at injection site
2)Serious systemic infections e.g. sepsis, flare up of TB, invasive fungal
infections
3) Increased risk of malignancy
4) Allergic reactions
41.
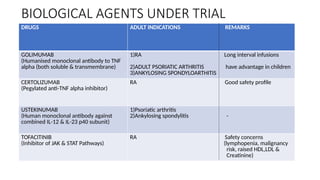
BIOLOGICAL AGENTS UNDERTRIAL
DRUGS ADULT INDICATIONS REMARKS
GOLIMUMAB
(Humanised monoclonal antibody to TNF
alpha (both soluble & transmembrane)
1)RA Long interval infusions
2)ADULT PSORIATIC ARTHRITIS have advantage in children
3)ANKYLOSING SPONDYLOARTHITIS
CERTOLIZUMAB
(Pegylated anti-TNF alpha inhibitor)
RA Good safety profile
USTEKINUMAB
(Human monoclonal antibody against
combined IL-12 & IL-23 p40 subunit)
1)Psoriatic arthritis
2)Ankylosing spondylitis -
TOFACITINIB
(Inhibitor of JAK & STAT Pathways)
RA Safety concerns
(lymphopenia, malignancy
risk, raised HDL,LDL &
Creatinine)
42.
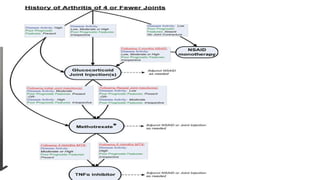
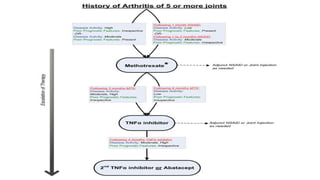
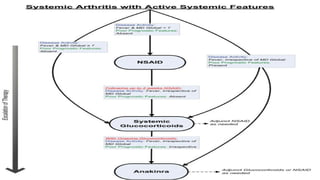
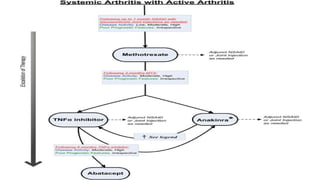
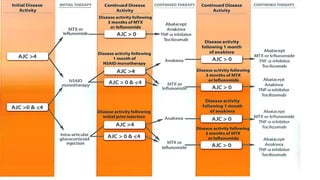
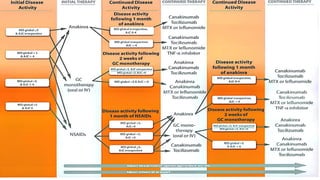
TREATMENT GROUPS(ACR)
• Historyof Arthritis in 4 or fewer joints
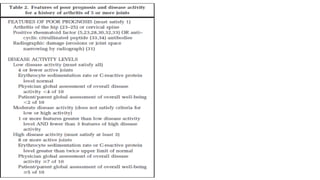
• History of arthritis in 5 or more joints
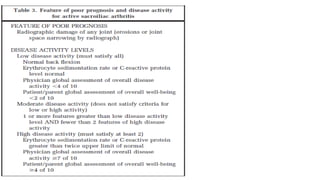
• Active sacroiliac arthritis
• Systemic arthritis without active arthritis
• Systemic arthritis with active arthritis
43.
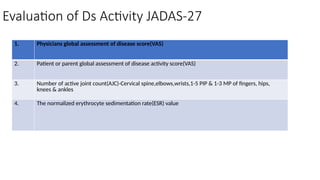
Evaluation of DsActivity JADAS-27
1. Physicians global assessment of disease score(VAS)
2. Patient or parent global assessment of disease activity score(VAS)
3. Number of active joint count(AJC)-Cervical spine,elbows,wrists,1-5 PIP & 1-3 MP of fingers, hips,
knees & ankles
4. The normalized erythrocyte sedimentation rate(ESR) value
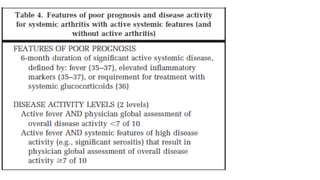
POOR PROGNOSTIC FEATURES
•Arthritis of Hip or Cervical spine, wrist or ankle joints.
• Prolonged raised inflammatory markers
• Radiographic damage of joints(erosions or joint space reduction)
• Systemic features->6m
• Requirement for treatment with systemic corticosteroids.
48.
Active Sacroiliac Arthritis
•TNF alpha inhibitor – only medication class for this treatment group.
INDICATIONS :
• High disease activity+features of poor prognosis – no improvement after adequate trial
of NSAIDS.
• High disease activity+irrespective of poor prognosis ,moderate ds activity+features of
poor prognosis – no improvement after 3 m of Mtx
• Moderate ds activity without features of poor prognosis – no improvement after 6 m of
Mtx
• Moderate or high ds activity ,irrespective of prognostic features – no response after 3 m
of sulfasalazine therapy or
• Low ds activity with features of poor prognosis – no response after 6 m of sulfasalazine
therapy.
REFERENCES
• Nelson Textbookof Paediatrics 20th
edition
• Clinical practice guidance for juvenile idiopathic arthritis 2018,Modern
Rheumatology 10.1080/14397595.2018.1514724.
• 2013Update of 2011 American college of Rheumatology
Recommendations for Treatment of Juvenile idiopathic
Arthritis ,Journal of American College of Rheumatology vol.65,pp
2499-2512.
• 2011 American College of Rheumatology Recommendations for the
treatment of juvenile idiopathic arthritis ,Journal of American College
of Rheumatology vol. 63, pp 465-482.