














Pharmacology Department,
           Faculty Of Pharmacy,
            Helwan University.


Designed By,
       Ahmed Kamal Abdel Aziz
Content:
 Trade Names.
 Drug Description.
 Dosage Forms.
 Pharmacodynamic (Pharmacological Mechanisms).
 Pharmacokinetics.
 Indications And Usage.
 Drug-drug Interactions .
 Drug-food Interactions.
 Side Effects.
 Overdose.
 Contraindications.
 Storage.
Trade Names:

Avalide®
 Avapro®
 Aprovel ®
 Karvea ®
Dosage Forms:

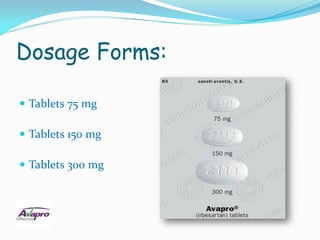
 Tablets 75 mg

 Tablets 150 mg

 Tablets 300 mg
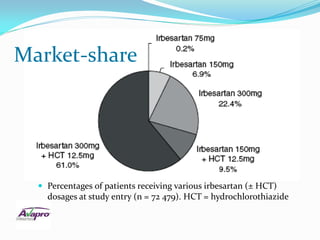
Market-share


   Percentages of patients receiving various irbesartan (± HCT)
    dosages at study entry (n = 72 479). HCT = hydrochlorothiazide
Pharmacological Mechanisms
(Pharmacodynamic):

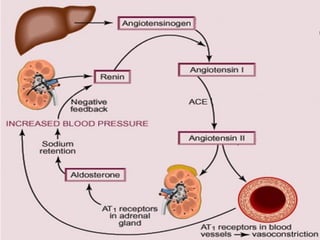
   Antagonizes the effect of angiotensin II
            (vasoconstriction and aldosterone secretion)


 by blocking the angiotensin II (AT1 receptor) in vascular smooth
 muscle and the adrenal gland, producing decreased BP
Combination with diuretic
 Irbesartan is also available in a combination
  formulation with a low dose thiazide diuretic,
  invariably hydrochlorothiazide, to achieve an
  additive antihypertensive effect.


                                                       Hydrochlorothiazide


               Irbesartan/hydrochlorothiazide combination preparations are
               marketed under similar trade names to irbesartan preparations,
               including
               Irda, CoIrda, CoAprovel, Karvezide, Avalide and
               Avapro HCT.
Pharmacokinetics:
  Absorption:
The mean absolute bioavailability is:
60% to 80%.

The T max is 1.5 to 2 h.


           Food does not affect the bioavailability of irbesartan.
Pharmacokinetics,
(continue)

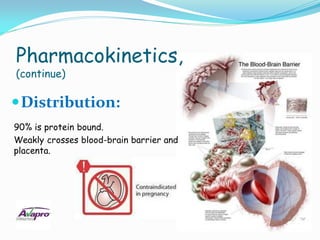
 Distribution:
90% is protein bound.
Weakly crosses blood-brain barrier and
placenta.
Pharmacokinetics,
(continue)

 Metabolism:
Less than 20% converted to metabolites, primarily via CYP2C9.

 Elimination:
Renal clearances is 3 to 3.5 mL/min.
The mean t ½ is 11 to 15 h.
Approximately, 20% is eliminated in the
urine and 80% in the feces.
Indications and Usage
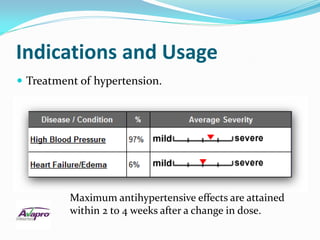
 Treatment of hypertension.


          Maximum antihypertensive effects are attained
          within 2 to 4 weeks after a change in dose.
Drug-Drug interactions :
 No      significant drug-drug pharmacokinetic (or
    pharmacodynamic) interactions have been found in
    interaction studies with :
   Hydrochlorothiazide, a diuretic and antihypertensive drug.
   Digoxin, cardiotonic steroid .
   Warfarin, anticoagulant.
   Nifedipine, a calcium channel blocker .

 Lithium :
                      However,
    Plasma concentrations my be increased by irbesartan,
    resulting in an increase in the pharmacologic and adverse
    effects of lithium
Drug-Food interactions:
 The chances of an interaction with Avapro are low.
Avalide may be administered with or without food.
Side Effects:
 Several   potential    side
 effects may develop with the
 use of Avapro.

 Side effects that were most
 commonly reported include :

 diarrhea,
 heartburn,
 dizziness,
 and fatigue.
OVERDOSE
 No data are available in regard to
 over dosage in humans.
 However, daily doses of 900 mg for
  8 weeks were well-tolerated.

 The most likely manifestations of
 over dosage are expected to be :
  hypotension and tachycardia;
bradycardia might also occur from overdose.

 Irbesartan is not removed by hemodialysis.
Contraindications:
   Avapro® (irbesartan) is contraindicated in
    patients who are hypersensitive to any component
    of this product.


           However,
Because of the hydrochlorothiazide component,
this product is contraindicated in patients with :
 Anuria ,
 Hypersensitivity to other sulfonamide-derived
  drugs.
WARNING:
                 USE IN PREGNANCY
When pregnancy is detected, discontinue AVALIDE as soon as
possible.
When used in pregnancy during the second and third trimesters,
drugs that act directly on the renin-angiotensin system can
cause injury and even death to the developing fetus.
Storage
 Store at 25°C (77°F);
 excursions permitted to 15°C - 30°C (59°F - 86°F)
http://www.medicineonline.com/drugs/A/2137/AV
References                    APRO-irbesartan-Tablets.html


^ Lewis EJ, Hunsicker LG, Clarke WR, Berl T, Pohl MA, Lewis JB, Ritz E,
   Atkins RC, Rohde R, Raz I; Collaborative Study Group. (2001).

"Renoprotective effect of the angiotensin-receptor antagonist irbesartan in
  patients with nephropathy due to type 2 diabetes". N Engl J Med 345 (12):
  851–60. doi:10.1056/NEJMoa011303. PMID 11565517.

^ Rossi S, editor. Australian Medicines Handbook 2006. Adelaide:
   Australian Medicines Handbook; 2006. ISBN 0-9757919-2-3

^ Massie BM, Carson PE, McMurray JJ, Komajda M, McKelvie R, Zile MR,
  Anderson S, Donovan M, Iverson E, Staiger C, Ptaszynska A (December
  2008). "Irbesartan in patients with heart failure and preserved ejection
  fraction". N. Engl. J. Med. 359 (23): 2456–67. doi:10.1056/NEJMoa0805450.
  PMID 19001508.
Team,
      Students from No. 3011-3020
   Ahmed Salah Mohamed             2011
   Ahmed Adel Ibrahim              2012
   Ahmed Abdel Aziz El-beltagi     2013
   Ahmed Abdel Mohsen              2014
   Ahmed Alaa El-dien Ahmed        2015
   Ahmed Fathi Abdel Samee’a       2016
   Ahmed Fawzy Selim               2017
   Ahmed Karim El-dien Zaki        2018
   Ahmed Kamal Abdel Aziz          2019
   Ahmed Maher Ismael              2020
Irbesartan