Introduction to pharmacology,
Routs of drug administration,
Principles of drug action
Dr. S. Parasuraman, M.Pharm., Ph.D.,
Senior Associate Professor, Faculty of Pharmacy,
AIMST University, Malaysia.
Introduction to Pharmacology - for allied health sciences
Introduction
• Pharmacology is the science of drugs (Greek:
Pharmacon—drug; logos—discourse in)
• Pharmacology deals with interaction of exogenously
administered chemical molecules with living systems,
or any single chemical substance which can produce a
biological response is a ‘drug’.
• The two main divisions of pharmacology are
pharmacodynamics and pharmacokinetics.
• Pharmacology as an experimental science was
ushered by Rudolf Buchheim who founded the first
institute of pharmacology in 1847 in Germany.
Glossary
• Pharmacodynamics: (Greek: dynamis-power) - What
the drug does to the body. Pharmacodynamics is the
study of the relationship between the concentration
of drug at the site of action and the biochemical and
physiological effect.
• Pharmacokinetics: (Greek: Kinesis-movement) - What
the body does to the drug. Pharmacokinetics is the
study of drug absorption, distribution, metabolism,
and excretion
• Drug (French: Drogue—a dry herb): It is the single
active chemical entity present in a medicine that is
used for diagnosis, prevention, treatment/cure of a
disease.
Glossary
• Pharmacotherapeutics: Is also known as
pharmacological therapy or drug therapy. It is the
application of pharmacological information together
with knowledge of the disease for its prevention,
mitigation or cure.
• Clinical pharmacology: It is the scientific study of
drugs (both old and new) in man. It includes
pharmacodynamic and pharmacokinetic investigation
in healthy volunteers as well as in patients.
• Chemotherapy: It is the treatment of systemic
infection/malignancy with specific drugs.
Glossary
• Pharmacy: It is the art and science of compounding
and dispensing drugs or preparing suitable dosage
forms for administration of drugs to man or animals.
• Toxicology: It is the study of poisonous effect of drugs
and other chemicals (household, environmental
pollutant, industrial, agricultural, homicidal) with
emphasis on detection, prevention and treatment of
poisonings.
• Receptor: Is a macromolecule in the membrane or
inside the cell that specifically (chemically) bind a
ligand (drug).
Introduction
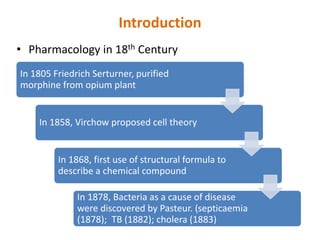
• Pharmacology in 18th Century
In 1805 Friedrich Serturner, purified
morphine from opium plant
In 1858, Virchow proposed cell theory
In 1868, first use of structural formula to
describe a chemical compound
In 1878, Bacteria as a cause of disease
were discovered by Pasteur. (septicaemia
(1878); TB (1882); cholera (1883)
Introduction
• In 19th century, Oswald Schmiedeberg, regarded as the
‘father of pharmacology’.
• Professor of pharmacology at the
University of Strasbourg, France
• In 1869 he demonstrated
that muscarine had a similar
effect on the heart as electrical
stimulation of the vagus nerve.
• He also demonstrated the
hypnotic properties of urethane.
• He published over 200 scientific
books and articles.
Introduction
• Pharmacology-become a
science in 19th century
• Long before that-herbal
medicine was used - written
pharmacopoeias
• MATERIA MEDICA the
science of drug preparation
and the medical uses of
drugs—began to develop as
the precursor to
pharmacology Page from the 6th century Vienna
Dioscurides, an illuminated version of
the 1st century De Materia Medica
Introduction
• Robert Boyle, regarded as the ‘first modern chemist’,
and one of the founders of modern chemistry.
Robert Boyle – ‘The Sceptical
Chymist’ – ‘The alchemist’
• He is best known for Boyle's law.
• As a founder of the Royal
Society, he was elected a Fellow
of the Royal Society (FRS) in 1663
Sources of drugs
Sources of drugs
• Primitive Medicine: Folklore, witchcraft, dreams,
trances etc. Also from observing the reaction of some
animals to particular herbs. E.g.: quinine, vitamin C
was discovered.
Cinchona calisaya Phyllanthus emblica
Cinchona bark
The barks of cinchona yield
quinine used for the
treatment of malaria
Sources of drugs
• Plants: Plant parts such as leaves, bark, roots,
flowers, seeds were used as sources for drugs. E.g.:
reserpine, digitalis, morphine.
Roots of Rauwolfia serpentina
Reserpine is an indole
alkaloid, antipsychotic,
and antihypertensive
drug
Digitalis purpurea
Digoxin used as
cardiotonic agent
Papaver somniferum
capsule exuding latex
Morphine used as
analgesic
Sources of drugs
• Animal sources: Obtained from animals' sources such
as hormones (replacement in times of deficiencies).
E.g.: Insulin from the pancreases of pigs and cattle.
• Human sources:
Drugs Source
HCG
Menotrophin
Insulin
Urokinase
Pregnant woman
Post menopausal women urine
Human
Human kidney cell
Sources of drugs
• Microbial sources: Obtained from microbial sources
such antimicrobials (AMBs).
Drug Microorganisms
Penicillin
Chloramphenicol
Griseofluvin
Streptomycin
Neomycin
Penicilium notatum
Streptomyces venezuelace
Pencillin grisofullivum
Streptomyces griseus
Streptomyces fradiae
Sources of drugs
• Minerals: E.g.: Acids, bases and salts like potassium
chloride.
• Synthesis of Substances: from natural products in the
laboratory.
• Synthetic drugs: These are chemical compounds
produced in a laboratory. They can be produced
commercially by drug manufacturers for valid medical
purposes and are diverted from legal channels or
produced illegally in clandestine laboratories for illicit
markets worldwide. E.g.: Sulfonamide
Drug
• The WHO (1966) has given a more comprehensive
definition—
“Drug is any substance or product that is used or is
intended to be used to modify or explore physiological
systems or pathological states for the benefit of the
recipient.”
Routs of drug administration
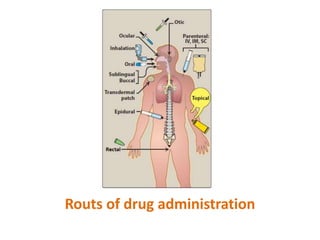
• Most drugs can be administered by a variety of
routes.
• The choice of appropriate route in a given situation
depends both on drug (for example, water or lipid
solubility, ionization), therapeutic objectives (for
example, the desirability of a rapid onset, the need
for long-term treatment, or restriction of delivery to a
local site) as well as patient related factors.
• Major routes of drug administration include enteral,
parenteral, and topical, among others.
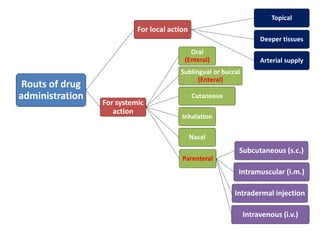
Routs of drug
administration
For local action
Topical
Deeper tissues
Arterial supply
For systemic
action
Oral
(Enteral)
Sublingual or buccal
(Enteral)
Cutaneous
Inhalation
Nasal
Parenteral
Subcutaneous (s.c.)
Intramuscular (i.m.)
Intravenous (i.v.)
Intradermal injection
Routs of drug administration - Oral
• Oral ingestion is the oldest and commonest mode of
drug administration.
• Oral drugs are easily self-administered, and toxicities
and/or overdose of oral drugs may be overcome with
antidotes, such as activated charcoal.
• Limitations of oral route of administration
– Action of drugs is slower and thus not suitable for
emergencies.
– Unpalatable drugs are difficult to administer.
– May cause nausea and vomiting.
– Cannot be used for uncooperative/unconscious patient.
– Absorption of drugs may be variable.
Routs of drug administration - Inhalation
• Volatile liquids and gases are given by inhalation for
systemic action, e.g. general anaesthetics.
• Absorption takes place from the vast surface of
alveoli - action is very rapid.
Routs of drug administration - Parenteral
• The parenteral route introduces drugs directly into
the systemic circulation.
• Parenteral administration is used for drugs that are
poorly absorbed from the GI tract (for example,
heparin) or unstable in the GI tract (for example,
insulin).
• parenteral routes have the highest bioavailability and
are not subject to first-pass metabolism.
Routs of drug administration - Parenteral
• Parenteral
– Subcutaneous (s.c.): Only small volumes can be injected
s.c. Self-injection is possible because deep penetration is
not needed. This route should be avoided in shock patients.
– Intramuscular (i.m.): The drug is injected in one of the
large skeletal muscles—deltoid, triceps, gluteus maximus,
rectus femoris, etc.
– Intravenous (i.v.): The drug is injected as a bolus or infused
slowly over hours in one of the superficial veins. The drug
reaches directly into the blood stream and effects are
produced immediately (great value in emergency)
(bioavailability is 100%).
– Intradermal injection: The drug is injected into the skin
raising a bleb (e.g. BCG vaccine, sensitivity testing). This
route is employed for specific purposes only.
Principles of drug action
• Drugs (except those gene based) do not impart new
functions to any system, organ or cell and only alter
the pace of ongoing activity.
• The basic types of drug action is broadly classed as:
– Stimulation
– Depression
– Irritation
– Replacement
– Cytotoxic action
Principles of drug action
• Majority of drugs produce their effects by interacting
with a discrete target biomolecule, which usually is a
protein.
• Such mechanism confers selectivity of action to the
drug. Functional proteins that are targets of drug
action can be grouped into four major categories,
viz. enzymes, ion channels, transporters and
receptors
Principles of drug action
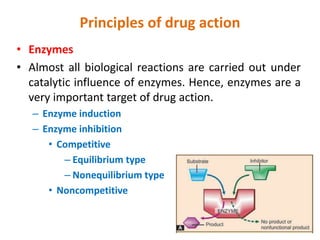
• Enzymes
• Almost all biological reactions are carried out under
catalytic influence of enzymes. Hence, enzymes are a
very important target of drug action.
– Enzyme induction
– Enzyme inhibition
• Competitive
– Equilibrium type
– Nonequilibrium type
• Noncompetitive
Principles of drug action
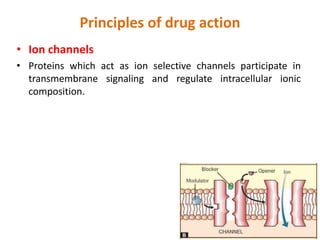
• Ion channels
• Proteins which act as ion selective channels participate in
transmembrane signaling and regulate intracellular ionic
composition.
Principles of drug action
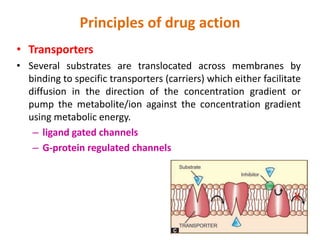
• Transporters
• Several substrates are translocated across membranes by
binding to specific transporters (carriers) which either facilitate
diffusion in the direction of the concentration gradient or
pump the metabolite/ion against the concentration gradient
using metabolic energy.
– ligand gated channels
– G-protein regulated channels
Principles of drug action
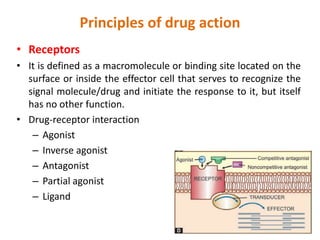
• Receptors
• It is defined as a macromolecule or binding site located on the
surface or inside the effector cell that serves to recognize the
signal molecule/drug and initiate the response to it, but itself
has no other function.
• Drug-receptor interaction
– Agonist
– Inverse agonist
– Antagonist
– Partial agonist
– Ligand
Principles of drug action
• Receptors
• Drug-receptor interaction
– Agonist: An agent which activates a receptor to produce an
effect similar to that of the physiological signal molecule.
– Inverse agonist: An agent which activates a receptor to
produce an effect in the opposite direction to that of the
agonist.
– Antagonist: An agent which prevents the action of an
agonist on a receptor or the subsequent response, but does
not have any effect of its own.
– Partial agonist: An agent which activates a receptor to
produce submaximal effect but antagonizes the action of a
full agonist.
– Ligand: Any molecule which attaches selectively to
particular receptors or sites.
Introduction to pharmacology (For Allied health students)