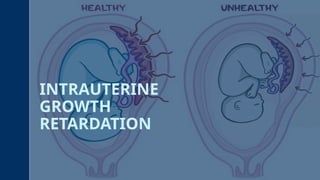
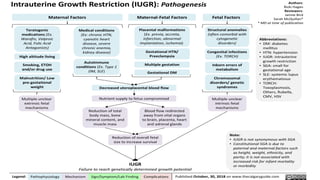
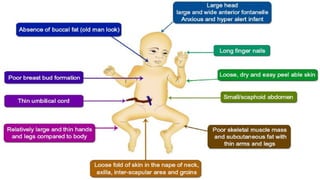
• FGR isa syndrome where fetus fails to reach its growth potential due to
several underlying disorders related to maternal, fetal or placental.
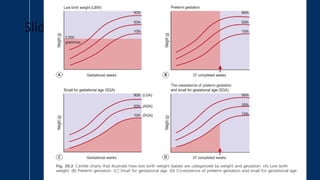
• Small for Gestational Age (SGA) is defined as an estimated fetal weight
below the 10th percentile for the gestational age.
• Fetal Growth Restriction (FGR) is defined on a combination of
measures of fetal size percentile and Doppler abnormalities.
• FGR may be with early onset (<32 weeks) or late onset (>=32 weeks).
• Growth restriction can occur in preterm, term or post term babies.
DEFINITION
4.
DEFINITION
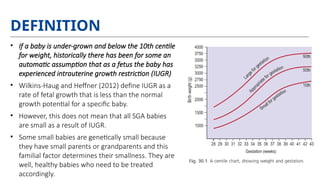
• If ababy is under-grown and below the 10th centile
for weight, historically there has been for some an
automatic assumption that as a fetus the baby has
experienced intrauterine growth restriction (IUGR)
• Wilkins-Haug and Heffner (2012) define IUGR as a
rate of fetal growth that is less than the normal
growth potential for a specific baby.
• However, this does not mean that all SGA babies
are small as a result of IUGR.
• Some small babies are genetically small because
they have small parents or grandparents and this
familial factor determines their smallness. They are
well, healthy babies who need to be treated
accordingly.
INCIDENCE
FGR comprises aboutone-third of low birth weight babies.
In high income group countries, its overall incidence is about 2-8%.
The incidence among the term babies is about 5% and that among the post-term
babies is about 15%.
8.
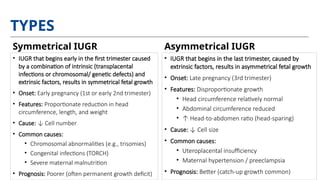
TYPES
• IUGR thatbegins early in the first trimester caused
by a combination of intrinsic (transplacental
infections or chromosomal/ genetic defects) and
extrinsic factors, results in symmetrical fetal growth
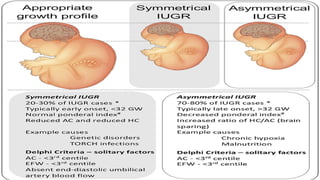
• Onset: Early pregnancy (1st or early 2nd trimester)
• Features: Proportionate reduction in head
circumference, length, and weight
• Cause: ↓ Cell number
• Common causes:
• Chromosomal abnormalities (e.g., trisomies)
• Congenital infections (TORCH)
• Severe maternal malnutrition
• Prognosis: Poorer (often permanent growth deficit)
• IUGR that begins in the last trimester, caused by
extrinsic factors, results in asymmetrical fetal growth
• Onset: Late pregnancy (3rd trimester)
• Features: Disproportionate growth
• Head circumference relatively normal
• Abdominal circumference reduced
• ↑ Head-to-abdomen ratio (head-sparing)
• Cause: ↓ Cell size
• Common causes:
• Uteroplacental insufficiency
• Maternal hypertension / preeclampsia
• Prognosis: Better (catch-up growth common)
Symmetrical IUGR Asymmetrical IUGR
10.
RISK FACTORS
• Maternalage more than 35 years;
• IVF singleton pregnancy;
• Nulliparity;
• BMI <20 or >35;
• Previous pre-eclampsia;
• Pregnancy interval <6 or >60 months. :
• Maternal age >40 years;
• Previous SGA baby;
• Previous stillbirth;
• Maternal SGA;
• Chronic hypertension;
• Diabetes with vascular disease;
• Renal impairment;
• Antiphospholipid syndrome;
• Heavy bleeding similar to menses and
Minor risk factors: Major risk factors:
PREDICTION AND DIAGNOSIS
•CLINICAL :
• Clinical palpation of the uterus for the fundal height, liquor volume and fetal mass may be used for screening.
It is simple, safe and inexpensive. But it is less sensitive.
• Symphysis Fundal Height (SFH): A lag of 3 cm or more suggests growth restriction.
• Maternal weight gain remains stationary or, at times, falling during the second-half of pregnancy.
• Measurement of the abdominal girth showing stationary or falling values.
• BIOPHYSICAL:
• Head Circumference (HC) and Abdominal Circumference (AC) ratios: If the fetus is affected by asymmetric FGR,
the HC remains larger. The HC/ AC is then elevated. In symmetric FGR, both the HC and AC are reduced. The
HC/ AC ratio remains normal.
• AC is the single most sensitive parameter to detect FGR
• Femur Length (FL) : not affected in asymmetric FGR. The FL/AC ratio is 22 at all gestational ages from 21 weeks
to term. FL/AC ratio greater than 23.5 suggests FGR.
• Amniotic fluid volume: Vertical pocket of amniotic fluid <1cm suggests iugr
• Anatomical survey: To exclude fetal anomalies by sonography (aneuploidy, structural defects).
22.
ULTRASOUND DOPPLER PARAMETERS
•Doppler velocimetry: Elevated Systolic/Diastolic (SID) ratio, the Resistance Index (RI) and the Pulsatility Index (PI)
indicate increased blood flow resistance and decrease in end diastolic velocity. These are associated with FGR and
intrauterine fetal hypoxia.
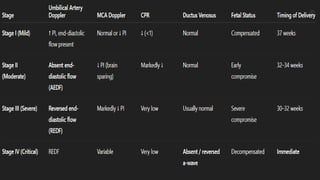
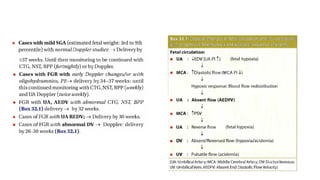
• Umbilical Artery (UA) Doppler study : should be the primary surveillance tool in the FGR fetus (RCOG). Reduced
or Absent or Reversed End-Diastolic Velocity (AREDV) in the umbilical artery indicates fetal jeopardy and poor
perinatal outcome.
• Uterine Artery (UtA): The presence of diastolic notch suggests the possible development of pre-eclampsia IUGR
and fetal demise.
• Middle Cerebral Artery (MCA) Doppler: Reflects fetal adaptation (brain-sparing effect); ↓ MCA PI; ↑ Diastolic
flow due to cerebral vasodilatation and Indicates chronic hypoxia
• Cerebroplacental Ratio (CPR) = MCA PI / UA PI; Normal: > 1.0–1.1; Abnormal: < 1 → early marker of fetal
compromise and is the Best single predictor of adverse outcome
• Ductus venosus Doppler study can predict fetal acidemia and adverse perinatal outcome (still birth). It is used
when UA Doppler study is abnormal
• Ponderal index (PI): The degree of fetal wasting is judged by fetal Pl. PI below 10th centiles is taken as FGR.
23.
ULTRASOUND DOPPLER PARAMETERS
•Biochemical markers:
• Maternal serum markers :
• ↑MSAFP(Maternal Serum Alpha-Fetoprotein) and
• ↑ hCG in the second trimester are the markers for IUGR by 5-10 fold.
• Placental dysfunction markers:
• ↓ PAPP-A (Pregnancy-Associated Plasma Protein-A) :Low in 1st trimester, Strongly associated with IUGR
& preeclampsia
• ↓ PlGF (Placental Growth Factor): Reflects impaired placental angiogenesis, Low levels → placental
insufficiency
25.
MANAGEMENT
Fetuses that areconstitutionally small (70%) require no intervention.
• General
• Rest, especially in left lateral position;
• Improve nutritional status by balanced diet: 300 extra calories per day are to be taken;
• To institute appropriate therapy for the associated complicating factors likely to produce growth restriction;
• Avoidance of smoking, tobacco and alcohol;
• Maternal hyperoxygenation at the rate of 2.5 L/min by nasal prong, for short-term prolongation of pregnancy;
• Low-dose aspirin (75-150 mg daily) since 12 weeks may be helpful in very selected cases with history of
thrombotic disease, hypertension, pre-eclampsia, or recurrent FGR;
• Maternal hyperalimentation by amino acids can improve fetal growth if it was due to maternal malnutrition.
Maternal hyperalimentation is only helpful when IUGR is due maternal malnutrition. It is not helpful when
placental function is deficient;
• Maternal circulatory volume expansion may be helpful in improving placental perfusion.
26.
MANAGEMENT
Antepartum evaluation: Serialevaluations of fetal growth and assessment of wellbeing should be done
once the diagnosis is made
• Ultrasound examination should be done at an interval of 1-2 weeks for the assessment of BPD, HC/
AC, fetal weight and AFI for high risk fetus (based on history, biochemistry, UtA Doppler or single
SFH measurement <10th centile or serial measurements indicative of FGR).
• Fetal wellbeing is assessed by • Kick count, • NST, • Biophysical profile, • Amniotic fluid volume •
Monitoring • CTG • Monitoring frequency: CTG/ NST twice weekly.
• Doppler ultrasound parameters are to be studied.
• At present, there is no effective treatment to improve FGR. There is no proven treatment for FGR
• Timing of delivery is a critical issue. This is to balance the risk of prematurity against the risk of
continued pregnancy. Unless carefully judged, continued pregnancy may end in IUFD or organ
damage due to hypoxia.
• TIMING OF DELIVERY:
• The factors to be considered are: (1) Presence of fetal abnormality; (2) Duration of pregnancy; (3)
Onset ofFGR; (4) Associated complicating factor; (5) Underlying pathology (if known); (6) Results of
antenatal fetal surveillance; and (7) Availability of neonatal intensive care unit (NICU).
27.
DELIVERY
• Delivery timingbeyond 37 weeks is recommended
• Before 37 weeks,
• for uncomplicated mild IUGR:
• General treatment applied
• Placental function may improve
• Pregnancy can continue until at least 37 weeks
• Severe iugr:
• If lung maturation is achieved : presence of phosphatidyl glycerol and L:S ratio ≥ 2 in amniotic fluid →
consider delivery
• If lung maturation is not achieved:
• Risks include prematurity and growth restriction and Preterm IUGR infants need highest level NICU
care
• Betamethasone therapy recommended before 34 weeks gestation: Corticosteroids reduce risk of
neonatal hyaline membrane disease (HMD) and intraventricular hemorrhage (IVH)
• When delivery is to be done before 32 weeks, magnesium sulfate should be given ( additional) to the mother for fetal
and neonatal neuroprotection.
• Absolute indications for delivery: Irrespective of gestational age are: CTG/NST abnormalities: Reduced variability,
repetitive late deceleration, severe PE with end-organ damage.
28.
DELIVERY
• Delivery methodand timing depend on:
• Severity of Intrauterine Growth Restriction (IUGR)
• Maternal health status
• Presence of other obstetric complications
• Labor induction options:
• Low rupture of membranes followed by oxytocin if beyond 34 weeks, cervix is favorable, and
fetal head is low in pelvis
• Prostaglandin E2 (PGE2) gel if cervix is unfavorable
• Intrapartum monitoring includes:
• Clinical assessment
• Continuous electronic fetal monitoring
• Scalp blood sampling
• High risk of intrapartum asphyxia necessitates close monitoring
• Opt for Caesarean section without trial of labour if vaginal delivery risks are high, such as fetal
acidemia, absent or reversed diastolic flow in the umbilical artery, or an unfavourable cervix
30.
NURSING DIAGNOSIS
1. Ineffectiveplacental tissue perfusion related to vasospasm secondary to preeclampsia, hypercoagulable state due to
APLA positivity as evidenced by stage 2 intrauterine growth restriction (IUGR), maternal hypertension, abnormal fetal
growth parameter
2. Excess fluid volume related to: endothelial damage and capillary leakage secondary to preeclampsia as evidenced by
edema, elevated blood pressure, proteinuria
3. Anxiety related to: high-risk pregnancy, fear of fetal loss or preterm delivery ,complex medical conditions and frequent
monitoring as evidenced by: verbalization of concern, restlessness, difficulty concentrating
4. Deficient knowledge related to: complex pregnancy management, anticoagulation therapy, blood glucose monitoring,
warning signs of preeclampsia
5. Disturbed sleep pattern related to: anxiety, hospital environment, physical discomfort (edema, headache)
6. Risk for fetal injury related to: reduced uteroplacental blood flow, maternal hypertension, hypercoagulability (APLA
positive), poor glycemic control (prediabetes)
7. Risk for maternal injury related to: severe preeclampsia (risk of eclampsia), thromboembolic complications associated
with APLA
8. Risk for unstable blood glucose level related to: insulin resistance during pregnancy, prediabetic state, stress response
associated with high-risk pregnancy
9. Risk for impaired maternal–fetal attachment related to: prolonged hospitalization, fear of poor pregnancy outcome,
emotional stress related to IUGR diagnosis
31.
NURSING MANAGEMENT
• Antenatalnursing management
• Identify high-risk mother
• PIH, anemia, diabetes, malnutrition, smoking
• Monitor fetal well-being
• Daily fetal movement count
• Assist with USG & Doppler follow-up
• Non-stress test (NST) / BPP
• Maternal care
• Encourage adequate nutrition & rest
• Left lateral position → improves uteroplacental
flow
• Administer prescribed iron, folic acid,
antihypertensives
• Prepare for preterm delivery
• Assist with antenatal corticosteroids
• Counseling regarding NICU care
• Intrapartum nursing management
• Continuous fetal monitoring (CTG)
• Observe for fetal distress & meconium
• Maintain maternal oxygenation & hydration
• Prepare for:
• Operative delivery if fetal compromise
• Neonatal resuscitation at birth
• Postnatal nursing management
• Thermoregulation
• Prevent hypothermia
• Warm chain, radiant warmer, skin-to-
skin (KMC)
• Glucose monitoring
• Frequent blood sugar checks
• Early feeding / IV glucose if needed
• Prevent hypoglycemia
• Feeding
• Early, frequent feeds
• Expressed breast milk preferred
• Gavage feeding if weak suck
32.
COMPLICATION
• After birth:Immediate: Asphyxia, bronchopulmonary
dysplasia and RDS;
• Hypoglycemia due to shortage of glycogen reserve in the
liver;
• Meconium aspiration syndrome;
• Microcoagulation leading to DIC;
• Hypothermia;
• Pulmonary hemorrhage;
• Polycythemia, anemia, thrombocytopenia;
• Hyperviscosity-thrombosis;
• necrotizing enterocolitis;
• Intraventricular hemorrhage (IVH);
• Electrolyte abnormalities: hypocalcemia (due to
hypoparathyroidism), hyponatremia, hyperphosphatemia
(due to tissue break down), hypokalemia due to impaired
renal function;
• Multiorgan failure;
• Increased perinatal morbidity and mortality.
• Late: Asymmetrical FGR babies tend to catch up
normal growth in early infancy
• retarded neurological and cognitive function,
delayed intellectual development in infancy
• Other long-term complications are:
• Increased risk of metabolic syndrome in adult life:
obesity, hypertension, diabetes and Coronary
Heart Disease (CHD).
• LBW infants have an altered orexigenic mechanism
that causes increased appetite and reduced satiety.
• Reduced number of nephrons-causes renal
vascular hypertension.
Fetal:
(A) Antenatal-
(A) chronic fetal distress,
(B) fetal death,
(C) preterm birth;
(B) Intrapartum-hypoxia and acidosis;