Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 1
INFECTION CONTROL COMMITTEE
EXCELLENCE MANUAL
Global Standards for Infection Prevention and Control Excellence, Surveillance Rigour,
and Quality Healthcare
A Comprehensive Reference for
THE MULTIDISCIPLINARY INFECTION CONTROL TEAM
Infection Control Officers โ€ข Infection Control Nurses โ€ข Hospital Epidemiologists โ€ข Antimicrobial Stewardship &
Allied Professionals
โ€œThe Infection We Prevent Is the One No One Will Ever See โ€” Success Here Looks Like Nothing
Happened at All.โ€
Dr J L Meena
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 2
DEDICATION
This book is dedicated to all those who are committed to advancing healthcare through a discipline unlike any other in a hospital:
its greatest successes are permanently invisible. A surgeon's successful operation is visible. A radiologist's caught tumour is visible.
An infection control programme's success is a patient who never developed the infection they were statistically at risk of โ€” an
outcome that, by definition, leaves no trace, generates no story, and is celebrated by no one except the team that quietly ensured
it never happened.
To Every Patient Who Never Knew How Close They Came
For whom a hand washed at exactly the right of five critical moments, a central line bundle followed without a single step skipped,
and a contaminated surface disinfected before it was ever touched again represent a promise kept: that the place meant to heal
them was never allowed to become the source of new harm.
To Every Healthcare Worker Who Washed Their Hands One More Time, When No One Was Watching
For whom hand hygiene compliance, performed with the same discipline on the hundredth patient of a long shift as on the first,
is the single most powerful and most quietly demanding act of patient protection in all of medicine.
To My Family
For their unwavering love, patience, and encouragement, which have been the foundation of this journey.
To My Mentors & Teachers
For inspiring my passion, guiding my path, and instilling in me the understanding that infection prevention is a discipline whose
triumphs are invisible by definition โ€” every chain of transmission broken before it started leaves no evidence of the outbreak
that never happened, and this genuine difficulty of proving a negative is precisely why sustained, unglamorous vigilance matters
more here than almost anywhere else in medicine.
To My Colleagues & Friends
For their support, collaboration, and shared dedication to a discipline where an outbreak traced rapidly to its source, a device
bundle followed without exception, and a surveillance system that never stopped watching are the only things standing between
a hospital's promise to heal and the invisible chain of transmission that could otherwise undermine it.
To Every Member of the Infection Control Team
Infection Control Officers, Infection Control Nurses, hospital epidemiologists, and every professional who has traced an
outbreak's source, audited a hand hygiene moment, or halted an unsafe practice before it became tomorrow's headline โ€” the
guardians of an invisible chain of vigilance that, when it holds, means nothing dramatic ever needs to happen at all.
Your vigilance, your rigorous surveillance, and your unwavering commitment to a discipline whose greatest successes are
permanently invisible are the silent pillars of a healthcare system where the place meant to heal is never allowed to become
the source of new harm. This book is for you, and because of you. Thank you to everyone who has been a part of this journey.
Dr J L Meena
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 3
FOREWORD
There is a discipline in healthcare whose greatest successes are permanently invisible. A surgeon's successful
operation is visible. A radiologist's caught tumour is visible. An infection control programme's success is a
patient who never developed the infection they were statistically at risk of โ€” an outcome that, by definition,
leaves no trace, generates no story, and is celebrated by no one except the team that quietly ensured it never
happened. This is what makes Infection Prevention and Control unlike almost any other discipline in a hospital:
transmission of pathogens is completely invisible to the naked eye, a hand can appear clean while carrying
organisms capable of causing serious harm, and the entire value of this committee's work is measured not in
what happened, but in what was quietly, invisibly prevented from happening at all.
The โ€œInfection Control Committee Manual: Global Standards for Infection Prevention and Control Excellence,
Surveillance Rigour, and Quality Healthcareโ€ has been developed to provide a comprehensive professional
framework for the multidisciplinary Infection Control team โ€” Infection Control Officers, Infection Control
Nurses, hospital epidemiologists, and allied antimicrobial stewardship professionals โ€” working together to
break every invisible chain of transmission before it ever produces a visible outcome.
This manual brings together internationally recognized principles of hand hygiene compliance and the WHO's
Five Moments framework, rigorous surveillance and outbreak investigation methodology, evidence-based
device-associated infection prevention bundles, correct isolation precaution application, environmental
cleaning and sterilization oversight, antimicrobial stewardship governance, and healthcare worker exposure
management. It is built around globally accepted accreditation frameworks โ€” WHO Guidelines on Hand
Hygiene in Health Care, NABH, JCI's Prevention and Control of Infections (PCI) chapter, and international
surveillance standards from the U.S. CDC's National Healthcare Safety Network (NHSN) and the Association for
Professionals in Infection Control and Epidemiology (APIC) โ€” to provide a rigorous, regulation-compliant
framework for Infection Control Committee excellence.
The chapters of this manual guide the Infection Control team through every dimension of the role โ€” from hand
hygiene compliance and rigorous surveillance, through device-associated infection bundle compliance and
isolation precaution application, to outbreak investigation, antimicrobial stewardship governance, and the
professional conduct that defines excellence across every category of infection prevention practice: the hand
washed at exactly the right moment out of five, whether or not anyone was watching; the central line bundle
followed completely, not because an infection was expected, but because complacency is precisely how an
invisible chain of transmission begins; and the outbreak traced to its source quickly enough that the pattern
never had the chance to become a crisis.
Infection Prevention and Control is not simply a hospital committee that reviews infection statistics โ€” it is a
distinct discipline built on the understanding that its subject matter, microbial transmission, is invisible until a
patient becomes clinically ill, that proving prevention is inherently harder than proving harm because
prevention leaves no evidence, and that this team's sustained, unglamorous vigilance is the only real defence
against a hospital becoming the source of the very harm it exists to treat. Their work is defined by a discipline
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 4
that must never relax, because the chain of transmission it prevents is one that, by its very nature, gives no
visible warning when it is about to break.
It is hoped that this manual will serve as an indispensable resource for Infection Control Officers, Infection
Control Nurses, hospital epidemiologists, hospital administrators, quality heads, and all those committed to
building a healthcare system where the place meant to heal is never allowed to become the source of new
harm.
โ€œThe Infection We Prevent Is the One No One Will Ever See โ€” Success Here Looks Like Nothing Happened
at All.โ€
With Best Wishes, Dr J L Meena
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 5
TABLE OF CONTENTS
FOREWORD............................................................................................................................................3
LIST OF ABBREVIATIONS........................................................................................................................8
MANUAL MOTTO.................................................................................................................................10
CHAPTER 1: Introduction.....................................................................................................................11
Purpose...........................................................................................................................................................11
Objectives .......................................................................................................................................................12
Vision & Mission .............................................................................................................................................13
CHAPTER 2: Role of the Infection Control Committee in Quality Healthcare....................................14
Hand Hygiene Compliance & the WHO Five Moments...................................................................................14
Surveillance and Outbreak Investigation........................................................................................................14
Device-Associated Infection Prevention Bundles ...........................................................................................15
Isolation Precautions & PPE............................................................................................................................15
Environmental Cleaning, Disinfection & Sterilization Oversight.....................................................................16
Antimicrobial Stewardship Governance .........................................................................................................16
Healthcare Worker Exposure Management ...................................................................................................17
Outbreak Response & Public Health Reporting..............................................................................................17
CHAPTER 3: Professional Standards for the Infection Control Team.................................................17
Professional Appearance & Behaviour ...........................................................................................................17
Communication Standards .............................................................................................................................18
Confidentiality & Information Security...........................................................................................................19
Ethical Standards ............................................................................................................................................19
Time Management, Teamwork & Continuous Learning.................................................................................20
CHAPTER 4: Communication for the Infection Control Committee ...................................................21
The A-T-C-R-C Communication Model............................................................................................................21
Communicating Hand Hygiene Feedback & Outbreak Findings .....................................................................22
CHAPTER 5: Patient Safety and Surveillance Standards.....................................................................23
The R-T-A-C-A Framework ..............................................................................................................................23
Daily Quality Standards Checklist ...................................................................................................................25
CHAPTER 6: Confidentiality, Privacy, and Information Security ........................................................26
Privacy in Infection Control Practice...............................................................................................................26
Cybersecurity of Infection Control Surveillance Systems ...............................................................................27
CHAPTER 7: Standard Operating Procedures (SOPs)..........................................................................28
SOP 1: Hand Hygiene Compliance Monitoring ...............................................................................................28
SOP 2: Healthcare-Associated Infection Surveillance.....................................................................................28
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 6
SOP 3: Outbreak Investigation and Response.................................................................................................29
SOP 4: Central Line-Associated Bloodstream Infection Bundle......................................................................29
SOP 5: Catheter-Associated UTI and Ventilator-Associated Pneumonia Bundles ..........................................30
SOP 6: Surgical Site Infection Prevention Bundle ...........................................................................................30
SOP 7: Isolation Precautions and PPE Compliance .........................................................................................31
SOP 8: Environmental Cleaning and Sterilization Verification........................................................................31
SOP 9: Antimicrobial Stewardship Program Oversight ...................................................................................32
SOP 10: Healthcare Worker Exposure and Post-Exposure Prophylaxis ..........................................................32
CHAPTER 8: Communication with Special Groups..............................................................................33
CHAPTER 9: Handling Difficult Situations ...........................................................................................35
CHAPTER 10: Emergency Response โ€” Critical Infection Control Presentations................................38
CHAPTER 11: Digital Competency for the Infection Control Team.....................................................41
CHAPTER 12: Daily Infection Control Checklist...................................................................................43
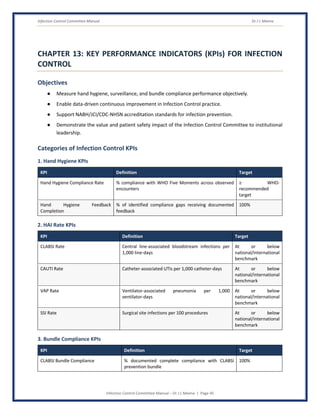
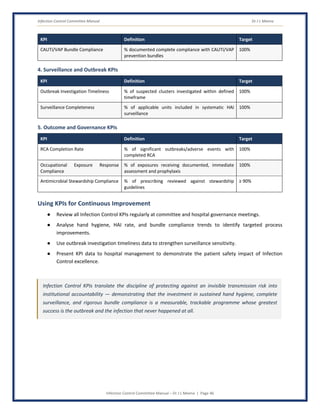
CHAPTER 13: Key Performance Indicators (KPIs)................................................................................45
CHAPTER 14: Top 20 Do's & Top 20 Don'ts.........................................................................................47
CHAPTER 15: Infection Control Professional Pledge...........................................................................50
CONCLUSION........................................................................................................................................53
REFERENCES.........................................................................................................................................54
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 7
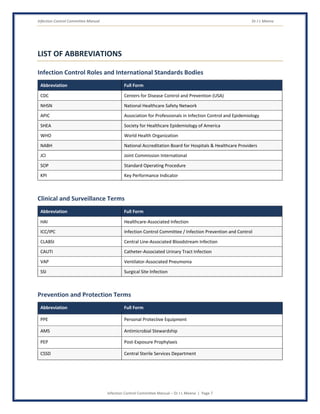
LIST OF ABBREVIATIONS
Infection Control Roles and International Standards Bodies
Abbreviation Full Form
CDC Centers for Disease Control and Prevention (USA)
NHSN National Healthcare Safety Network
APIC Association for Professionals in Infection Control and Epidemiology
SHEA Society for Healthcare Epidemiology of America
WHO World Health Organization
NABH National Accreditation Board for Hospitals & Healthcare Providers
JCI Joint Commission International
SOP Standard Operating Procedure
KPI Key Performance Indicator
Clinical and Surveillance Terms
Abbreviation Full Form
HAI Healthcare-Associated Infection
ICC/IPC Infection Control Committee / Infection Prevention and Control
CLABSI Central Line-Associated Bloodstream Infection
CAUTI Catheter-Associated Urinary Tract Infection
VAP Ventilator-Associated Pneumonia
SSI Surgical Site Infection
Prevention and Protection Terms
Abbreviation Full Form
PPE Personal Protective Equipment
AMS Antimicrobial Stewardship
PEP Post-Exposure Prophylaxis
CSSD Central Sterile Services Department
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 8
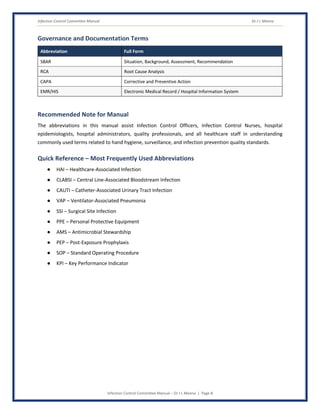
Governance and Documentation Terms
Abbreviation Full Form
SBAR Situation, Background, Assessment, Recommendation
RCA Root Cause Analysis
CAPA Corrective and Preventive Action
EMR/HIS Electronic Medical Record / Hospital Information System
Recommended Note for Manual
The abbreviations in this manual assist Infection Control Officers, Infection Control Nurses, hospital
epidemiologists, hospital administrators, quality professionals, and all healthcare staff in understanding
commonly used terms related to hand hygiene, surveillance, and infection prevention quality standards.
Quick Reference โ€“ Most Frequently Used Abbreviations
โ— HAI โ€“ Healthcare-Associated Infection
โ— CLABSI โ€“ Central Line-Associated Bloodstream Infection
โ— CAUTI โ€“ Catheter-Associated Urinary Tract Infection
โ— VAP โ€“ Ventilator-Associated Pneumonia
โ— SSI โ€“ Surgical Site Infection
โ— PPE โ€“ Personal Protective Equipment
โ— AMS โ€“ Antimicrobial Stewardship
โ— PEP โ€“ Post-Exposure Prophylaxis
โ— SOP โ€“ Standard Operating Procedure
โ— KPI โ€“ Key Performance Indicator
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 9
MANUAL MOTTO
โ€œThe Infection We Preventโ€
โ€œIs the One No One Will Ever See โ€”โ€
โ€œSuccess Here Looks Like Nothing Happened at All.โ€
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 10
CHAPTER 1: INTRODUCTION
1. Purpose
There is a discipline in healthcare whose greatest successes are permanently invisible. A surgeon's successful
operation is visible. An infection control programme's success is a patient who never developed the infection
they were statistically at risk of โ€” an outcome that, by definition, leaves no trace and generates no story. This
manual exists because proving prevention is inherently harder than proving harm, and because this genuine
difficulty is precisely why sustained, unglamorous vigilance โ€” hand hygiene performed correctly at every one
of five critical moments, every device bundle followed without exception, every outbreak traced rapidly to its
source โ€” matters more here than almost anywhere else in medicine.
The World Health Organization and international infection prevention bodies โ€” CDC/NHSN, APIC, SHEA โ€”
recognize that rigorous hand hygiene compliance, systematic surveillance, and evidence-based device bundle
adherence are directly and measurably linked to reduced healthcare-associated infection rates. Research
consistently demonstrates that hospitals applying standardized hand hygiene monitoring, complete
surveillance systems, and disciplined bundle compliance achieve dramatically and measurably lower HAI rates
than institutions where infection prevention is treated as an occasional priority rather than a sustained,
invisible discipline. In institutions where the Infection Control Committee applies systematic surveillance,
honest outbreak investigation, and rigorous bundle compliance, patient outcomes are demonstrably and
measurably better. The investment in Infection Control Committee excellence is, without qualification, one of
the highest-yield investments any healthcare system can make โ€” because the place meant to heal must never
be allowed to become the source of new harm.
Why the Infection Control Committee Is Critical to Healthcare Quality
โ— Provides hospital-wide surveillance and governance preventing healthcare-associated infections
across every department.
โ— Applies rigorous hand hygiene compliance monitoring, the single most powerful and most consistently
under-performed infection prevention intervention.
โ— Applies systematic surveillance and rapid outbreak investigation, breaking invisible chains of
transmission before they become visible crises.
โ— Applies evidence-based device-associated infection prevention bundles, reducing CLABSI, CAUTI, VAP,
and SSI rates measurably.
โ— Ensures correct isolation precaution application, preventing transmission between patients and to
staff.
โ— Oversees environmental cleaning, disinfection, and sterilization, closing gaps invisible to casual
inspection.
โ— Governs antimicrobial stewardship at the institutional policy level, protecting antibiotic effectiveness
hospital-wide.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 11
โ— Contributes to accreditation compliance (NABH, JCI, CDC/NHSN) for infection prevention and control
standards.
Key Responsibilities of the Infection Control Committee
โ— Applying rigorous hand hygiene compliance monitoring and feedback across every department.
โ— Applying systematic, complete surveillance for healthcare-associated infections.
โ— Applying rapid, evidence-based outbreak investigation methodology.
โ— Applying and auditing evidence-based device-associated infection prevention bundles.
โ— Ensuring correct isolation precaution classification and application.
โ— Overseeing environmental cleaning, disinfection, and sterilization verification.
โ— Governing antimicrobial stewardship policy and monitoring institutional compliance.
โ— Engaging in continuous professional development to maintain competence in evolving infection
prevention evidence.
2. Objectives
1. Achieve Genuine, Sustained Hand Hygiene Compliance
Every healthcare worker must perform hand hygiene at every one of the WHO's five critical moments โ€” this is
the Infection Control Committee's foundational, non-negotiable obligation, because this single behaviour,
performed consistently, prevents more transmission than any other single intervention in medicine.
How to Achieve:
โ— Apply systematic, direct observation and electronic monitoring of hand hygiene compliance.
โ— Provide honest, constructive feedback rather than punitive responses to compliance gaps.
2. Maintain Complete, Systematic Surveillance
โ— Apply standardized case definitions and complete surveillance for all major HAI categories.
โ— Never allow surveillance gaps to leave a transmission chain invisible longer than necessary.
3. Apply Evidence-Based Prevention Bundles Without Exception
โ— Apply complete CLABSI, CAUTI, VAP, and SSI prevention bundles for every applicable patient.
โ— Audit bundle compliance regularly, addressing any identified gap immediately.
4. Investigate Outbreaks Rapidly and Rigorously
โ— Apply structured outbreak investigation methodology immediately upon suspected clustering.
โ— Communicate findings honestly and transparently to affected departments and leadership.
5. Apply Correct Isolation Precautions Consistently
โ— Apply correct isolation category classification for every relevant diagnosis.
โ— Verify genuine staff compliance with isolation precautions and PPE use.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 12
6. Govern Antimicrobial Stewardship Effectively
โ— Apply institutional antimicrobial stewardship policy and monitor compliance.
โ— Support microbiology and pharmacy in evidence-based prescribing practice.
7. Maintain Regulatory and Accreditation Compliance
โ— Comply with national infection prevention standards and international accreditation guidelines.
โ— Maintain NABH/JCI/CDC-NHSN documentation standards.
โ— Participate in accreditation surveys with complete, auditable surveillance and compliance records.
3. Vision
Vision Statement
โ€œTo build and maintain an Infection Control Committee where hand hygiene compliance is genuinely sustained,
surveillance never blinks, and the invisible chain of transmission is broken so consistently that the outbreak,
the device infection, and the crisis never have the chance to become visible at all.โ€
4. Mission
Mission Statement
โ€œTo deliver rigorous, evidence-based infection prevention and control governance across the entire institution,
through sustained hand hygiene compliance, complete surveillance, evidence-based bundle adherence, and
rapid outbreak investigation, ensuring the place meant to heal every patient is never allowed to become the
source of new harm.โ€
Expected Outcomes of an Excellent Infection Control Committee Practice
โ— Hand hygiene compliance sustained at or above WHO-recommended targets across every
department.
โ— 100% of applicable patients receive documented, complete device-associated infection prevention
bundles.
โ— 100% of suspected outbreak clusters receive documented, rapid investigation.
โ— HAI rates (CLABSI, CAUTI, VAP, SSI) maintained at or below national/international benchmarks.
โ— Full compliance with national infection prevention standards and international accreditation
guidelines.
The Infection Control Committee protects against a transmission that is completely invisible until a patient
becomes clinically ill โ€” their sustained hand hygiene discipline, complete surveillance, and rigorous bundle
compliance are what ensure the place meant to heal every patient is never allowed to become the source
of new harm.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 13
CHAPTER 2: ROLE OF THE INFECTION CONTROL COMMITTEE IN
QUALITY HEALTHCARE
1. Hand Hygiene Compliance and the WHO Five Moments
Overview
Hand hygiene, performed at each of the WHO's five critical moments, is the single most powerful and most
consistently under-performed infection prevention intervention in all of medicine โ€” sustained compliance
monitoring is this committee's foundational responsibility.
Responsibilities
โ— Apply systematic, direct observation and electronic monitoring of hand hygiene compliance.
โ— Provide honest, constructive feedback supporting genuine, sustained behaviour change.
2. Surveillance and Outbreak Investigation
Overview
Because transmission is invisible until a patient becomes clinically ill, complete, systematic surveillance is the
only mechanism by which an emerging cluster can be detected and investigated before it becomes a visible
crisis.
Responsibilities
โ— Apply standardized case definitions and complete surveillance for all major HAI categories.
โ— Apply rapid, structured outbreak investigation methodology upon any suspected clustering.
3. Device-Associated Infection Prevention Bundles
Overview
Central lines, urinary catheters, and ventilators each carry a well-defined, evidence-based bundle of prevention
steps โ€” completing every element, every time, is what separates genuine prevention from partial compliance.
Responsibilities
โ— Apply complete CLABSI, CAUTI, and VAP prevention bundles for every applicable patient.
โ— Audit bundle compliance regularly, addressing any identified gap immediately.
4. Isolation Precautions and PPE
Overview
Correct isolation category classification, matched to the specific transmission route of the causative organism,
is essential to prevent both under-protection and unnecessary over-restriction.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 14
Responsibilities
โ— Apply correct isolation category classification for every relevant diagnosis.
โ— Verify genuine staff compliance with isolation precautions and appropriate PPE use.
5. Environmental Cleaning, Disinfection, and Sterilization Oversight
Overview
Contaminated surfaces and inadequately sterilized equipment represent invisible transmission risk requiring
systematic oversight beyond casual visual inspection.
Responsibilities
โ— Apply systematic verification of environmental cleaning and disinfection protocols.
โ— Oversee sterilization quality control in the Central Sterile Services Department.
6. Antimicrobial Stewardship Governance
Overview
The committee governs antimicrobial stewardship at the institutional policy level, supporting microbiology and
pharmacy in protecting antibiotic effectiveness hospital-wide.
Responsibilities
โ— Apply institutional antimicrobial stewardship policy and monitor compliance.
โ— Support evidence-based prescribing practice in coordination with microbiology and pharmacy.
7. Healthcare Worker Exposure Management
Overview
Healthcare workers themselves face occupational exposure risk, requiring rigorous post-exposure prophylaxis
protocols and genuine support.
Responsibilities
โ— Apply immediate, rigorous post-exposure prophylaxis protocols following any occupational exposure.
โ— Provide genuine follow-up support and monitoring for exposed healthcare workers.
8. Outbreak Response and Public Health Reporting
Overview
Confirmed outbreaks require coordinated institutional response and honest, timely reporting to public health
authorities as regulatory requirements demand.
Responsibilities
โ— Apply coordinated, institution-wide outbreak response protocols.
โ— Apply honest, timely public health reporting per regulatory requirement.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 15
How the Infection Control Committee Contributes to Quality Healthcare
โ— By sustaining hand hygiene compliance, the committee prevents more transmission than any other
single intervention in medicine.
โ— By maintaining complete surveillance, the committee detects emerging clusters before they become
visible crises.
โ— By applying complete prevention bundles, the committee reduces device-associated infection rates
measurably.
โ— By governing antimicrobial stewardship, the committee protects antibiotic effectiveness for future
patients.
โ— By investigating outbreaks rapidly and honestly, the committee breaks the invisible chain of
transmission before it spreads further.
The Infection Control Committee protects against a transmission that is completely invisible until a patient
becomes clinically ill โ€” their sustained hand hygiene discipline, complete surveillance, and rigorous bundle
compliance are what ensure the place meant to heal every patient is never allowed to become the source
of new harm.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 16
CHAPTER 3: PROFESSIONAL STANDARDS FOR THE INFECTION CONTROL
TEAM
Infection Control practice requires an uncommon combination of sustained vigilance for a transmission risk
that is genuinely invisible until illness appears, the discipline to complete every element of a prevention bundle
even when an infection was never expected in the first place, and the analytical rigour to trace an outbreak to
its true source rather than a convenient assumption. The standards that govern Infection Control practice
derive from a discipline whose greatest successes, by definition, leave no visible trace.
1. Professional Appearance
Standards
Attire and Identification
โ— Wear appropriate professional attire and ID badge as per facility policy.
Professional Presence
โ— Model impeccable hand hygiene and PPE practice in every observed and unobserved interaction.
โ— Maintain rigorous, disciplined attention to surveillance data throughout every shift.
2. Professional Behaviour
Expected Behaviours
Surveillance Discipline
โ— Never allow a surveillance gap or delayed case identification to persist unaddressed.
โ— Apply standardized case definitions consistently, resisting the temptation to under- or over-classify
cases.
Bundle Compliance Discipline
โ— Never accept partial bundle compliance as sufficient; every element matters.
โ— Escalate immediately upon any identified bundle compliance gap or outbreak signal.
Accountability
โ— Own every surveillance finding, every outbreak investigation conclusion, and every policy
recommendation made under this team's responsibility.
โ— Report and disclose critical incidents and adverse events honestly and promptly.
Collaborative Respect
โ— Treat every member of the multidisciplinary Infection Control team โ€” officer, nurse, epidemiologist
โ€” as an essential, equal partner.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 17
Patient-Centered Focus
โ— Every surveillance activity and every bundle audit is ultimately about protecting a patient from an
invisible transmission risk โ€” never about administrative box-checking.
3. Communication Standards
Communication with Departments and Staff
โ— Communicate hand hygiene and bundle compliance feedback honestly and constructively, never
punitively.
โ— Communicate outbreak findings clearly and transparently to affected departments.
Communication Within the Team
โ— Communicate any surveillance concern or outbreak signal rapidly and clearly.
โ— Use structured handover tools (SBAR or equivalent) for every transfer of surveillance responsibility.
โ— Escalate any significant compliance gap or outbreak concern immediately and directly.
Written Communication Standards
โ— Infection control documentation must be accurate, contemporaneous, and complete, reflecting
surveillance and investigation rationale.
โ— Reports must be exact and free of language that could be misinterpreted regarding compliance status.
4. Confidentiality and Information Security
Overview
Infection control involves sensitive patient and staff health information, including outbreak investigation data
and occupational exposure records, requiring heightened confidentiality discipline.
Responsibilities
โ— Discuss patient and staff health information only in appropriate settings and only with those who have
a legitimate need to know.
โ— Protect access credentials for EMR/HIS and infection control surveillance systems.
โ— Apply particular discretion for outbreak investigation and occupational exposure information.
5. Ethical Standards
Core Ethical Principles for Infection Control Practice
Non-Maleficence
โ— Never allow a known surveillance gap or bundle compliance concern to persist unaddressed.
โ— Never suppress or minimize an outbreak finding to avoid institutional discomfort.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 18
Beneficence
โ— Apply rigorous, evidence-based practice consistently, ensuring the most effective prevention
achievable.
Honesty and Transparency
โ— Communicate genuine surveillance findings, outbreak conclusions, and any error honestly.
Justice and Equity
โ— Apply the same rigorous surveillance and compliance standard to every department, regardless of
seniority or convenience.
6. Time Management and Prioritization
Clinical Priority Framework
โ— Immediate/Emergency: Suspected outbreak or cluster requiring immediate investigation โ€”
immediate response, no delay.
โ— Urgent: Significant bundle compliance gap or occupational exposure requiring prompt action โ€”
prompt resolution.
โ— Routine: Standard surveillance and compliance monitoring โ€” managed per defined schedule, with
unwavering thoroughness.
7. Teamwork and Collaboration
Work Effectively With
โ— Microbiology and pharmacy โ€” for antimicrobial stewardship coordination.
โ— Nursing and clinical departments โ€” for bundle compliance and isolation precaution implementation.
โ— Environmental services and CSSD โ€” for cleaning and sterilization oversight.
โ— Quality department โ€” for incident reporting, RCA, and accreditation support.
8. Professional Competence and Continuous Learning
Areas of Competence
โ— Hand hygiene compliance monitoring methodology.
โ— Surveillance case definitions and outbreak investigation methodology.
โ— Device-associated infection prevention bundle protocols.
โ— Antimicrobial stewardship principles and governance.
โ— FMEA, RCA, and CAPA methodologies for infection control-specific quality improvement.
Continuous Learning
โ— Maintain current certification in relevant infection control competencies.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 19
โ— Maintain current knowledge of evolving infection prevention evidence and guidelines (CDC/NHSN,
APIC, WHO).
โ— Engage with national and international infection prevention professional bodies.
โ— Participate regularly in outbreak investigation and surveillance simulation training.
โ— Participate in NABH, JCI, and CDC/NHSN accreditation training for infection prevention standards.
Professional Standards Checklist
โ— Have I applied rigorous hand hygiene compliance monitoring across departments today?
โ— Have I applied complete, systematic surveillance for all major HAI categories?
โ— Have I audited device-associated infection prevention bundle compliance thoroughly?
โ— Have I investigated any suspected outbreak cluster rapidly and rigorously?
โ— Have I communicated compliance feedback honestly and constructively?
โ— Have I reported any incident or safety concern through the appropriate system?
Infection Control professionalism is sustained vigilance for a transmission risk that is genuinely invisible
until illness appears โ€” the team that completes every bundle element and traces every outbreak to its true
source is the team that ensures the place meant to heal never becomes the source of new harm.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 20
CHAPTER 4: COMMUNICATION FOR THE INFECTION CONTROL
COMMITTEE
Communication in Infection Control must accomplish something genuinely distinctive: the committee must
deliver honest, sometimes uncomfortable feedback about hand hygiene and bundle compliance gaps to
colleagues across every department, in a way that builds genuine improvement rather than defensiveness,
while communicating outbreak findings with a transparency that protects patients without inducing
unnecessary institutional panic.
Why Communication Quality Matters in Infection Control
โ— Honest, constructive compliance feedback builds genuine behaviour change rather than resentment
or defensive compliance theatre.
โ— Transparent outbreak communication supports coordinated institutional response rather than denial
or delay.
โ— Clear communication of bundle rationale helps clinical staff understand why every element matters,
not merely that it is required.
โ— Honest public health reporting protects the wider community beyond the institution's own walls.
The A-T-C-R-C Communication Model for Infection Control
A โ€” Acknowledge
Definition
Acknowledge the genuine workload pressure and good intentions of staff facing a compliance gap, before
addressing the concern.
Examples
โ— โ€œI know how busy this shift has been โ€” I want to talk through something I observed with the central
line bundle, because getting every step right protects your patient.โ€
T โ€” Listen (Understand the Genuine Barrier)
Definition
Listen genuinely to any systemic or practical barrier contributing to a compliance gap, rather than assuming
simple negligence.
C โ€” Clarify (Communicate the Genuine Stakes)
Definition
Communicate honestly why the specific compliance element matters, connecting it to genuine patient risk.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 21
Examples
โ— โ€œThis step exists because it's the one most linked to preventing bloodstream infection โ€” skipping it,
even once, genuinely increases risk.โ€
R โ€” Respond (Support Genuine Improvement)
Definition
Respond with genuine support for improvement โ€” additional training, workflow adjustment โ€” rather than
punitive consequence alone.
C โ€” Confirm (Verify Genuine Commitment)
Definition
Confirm genuine understanding and commitment to sustained compliance going forward.
Communicating Hand Hygiene Feedback and Outbreak Findings
Principles for Communicating Compliance Feedback
โ— Communicate feedback constructively and privately, never publicly shaming an individual.
โ— Focus on genuine behaviour change, not blame, while maintaining honest accountability.
Communicating Outbreak Findings
โ— Communicate findings transparently to affected departments and leadership, without minimizing
genuine concern.
โ— Communicate honestly with public health authorities per regulatory reporting requirement.
Communicating with the Wider Institution
โ— Communicate surveillance data and compliance trends regularly to hospital leadership.
โ— Communicate genuine successes as well as genuine gaps, building a culture of honest improvement.
Common Infection Control Communication Mistakes to Avoid
โ— Delivering compliance feedback punitively rather than constructively.
โ— Minimizing or delaying communication of a genuine outbreak signal to avoid institutional discomfort.
โ— Failing to explain the genuine rationale behind a bundle element, reducing it to mere rule-following.
โ— Communicating surveillance data only when problems arise, never celebrating genuine sustained
compliance.
Communication in Infection Control must build genuine improvement rather than defensiveness โ€” the
team that delivers honest, constructive feedback and communicates outbreak findings transparently
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 22
protects patients through a discipline whose successes are otherwise invisible and whose failures can
otherwise be denied.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 23
CHAPTER 5: PATIENT SAFETY AND SURVEILLANCE STANDARDS
Patient safety in Infection Control is uniquely defined by a transmission risk that is completely invisible until
illness appears โ€” a committee that sustains genuine hand hygiene compliance, maintains complete
surveillance, and applies rigorous bundle compliance produces measurably better outcomes than one where
any of these safeguards is treated as an occasional priority. The R-T-A-C-A framework applies with particular
intensity to a discipline whose greatest successes leave no visible trace at all.
1. RESPECT
Definition
Treating every hand hygiene moment and every bundle element as equally deserving of the Infection Control
Committee's full rigour, regardless of department seniority or how routine a procedure appears.
How the Infection Control Committee Demonstrates Respect
โ— Respect for the Invisible Risk: Apply the same surveillance rigour to a routine ward as to a high-acuity
intensive care unit.
โ— Respect for Genuine Compliance: Never accept partial bundle compliance as sufficient.
โ— Respect for Every Team Member's Judgment: Value the infection control nurse's ward observation as
highly as the epidemiologist's data analysis.
โ— Equal Service Standards: Apply the same rigorous surveillance and compliance standard to every
department.
2. TIMELINESS
Definition
Recognizing and responding to suspected outbreak clusters and significant compliance gaps within timeframes
that protect patient safety, while never rushing the systematic surveillance process that requires its own,
uncompressed rigour.
Why Timeliness Is a Patient Safety Issue โ€” and Why It Cuts Both Ways
A delayed outbreak investigation can allow a transmission chain to spread further before it is broken. Yet the
opposite lesson applies equally: rushing surveillance case classification to close an investigation quickly is
precisely the shortcut that can mean a genuine outbreak signal is missed or an unrelated cluster is wrongly
declared โ€” both errors with serious consequences. Timeliness in Infection Control means responding to
genuine outbreak signals immediately while refusing to compress the surveillance rigour that requires its full,
uncompressed thoroughness.
Infection Control Timeliness Standards
โ— Suspected outbreak investigation: immediate, without avoidable delay.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 24
โ— Surveillance case classification: complete, uncompressed, every case, regardless of workload pressure.
โ— Public health reporting: prompt, per regulatory timeline, never delayed to avoid discomfort.
3. ACCURACY
Definition
Applying every surveillance case definition exactly, auditing every bundle element precisely, and investigating
every outbreak signal rigorously, sustained without deviation across every department.
Why Accuracy Is Non-Negotiable in Infection Control
An inaccurate surveillance case definition can mean a genuine outbreak signal is missed entirely, invisible until
it becomes a visible crisis. An inaccurate bundle audit can mean a genuine compliance gap persists undetected.
Accuracy in Infection Control, sustained across surveillance, bundle auditing, and outbreak investigation alike,
is what separates a discipline that genuinely protects patients from an invisible risk from one whose gaps
surface only when an outbreak has already occurred.
Areas Requiring Infection Control Accuracy
โ— Surveillance: Every case must be classified against standardized definitions exactly.
โ— Bundle Auditing: Every prevention bundle element must be verified completely, not sampled.
โ— Outbreak Investigation: Every suspected cluster must be investigated to its genuine source.
โ— Documentation: Every infection control record must accurately and completely reflect surveillance
and investigation rationale.
4. COMPASSION
Definition
Recognizing that compliance feedback affects colleagues doing genuinely difficult work under real pressure,
and that genuine compassion in this feedback is as important as surveillance accuracy.
How the Infection Control Committee Demonstrates Compassion
โ— Deliver Feedback Constructively: Building genuine improvement, not defensiveness.
โ— Support Colleagues Through Genuine Barriers: Workflow or resource constraints deserve genuine
problem-solving, not blame alone.
โ— Support Exposed Healthcare Workers Genuinely: Occupational exposure carries real anxiety deserving
genuine care.
โ— Respect the Weight of an Outbreak on Affected Staff: A department facing an outbreak deserves
support, not shame.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 25
5. ACCOUNTABILITY
Definition
Taking full professional responsibility for every surveillance finding, every outbreak investigation conclusion,
and every policy recommendation made under Infection Control Committee responsibility.
Infection Control Accountability Standards
โ— Every surveillance, audit, and investigation decision is documented with the responsible team
member's identification.
โ— Never allow a known surveillance gap or compliance concern to go unaddressed.
โ— Report every confirmed outbreak and significant adverse event honestly through the quality reporting
system.
โ— Participate in RCA for significant outbreaks, with complete clinical and administrative honesty.
โ— Participate in quality audits and accreditation surveys with accurate, complete surveillance records.
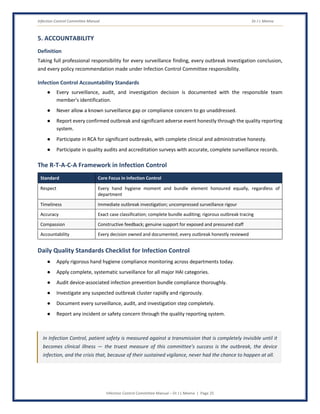
The R-T-A-C-A Framework in Infection Control
Standard Core Focus in Infection Control
Respect Every hand hygiene moment and bundle element honoured equally, regardless of
department
Timeliness Immediate outbreak investigation; uncompressed surveillance rigour
Accuracy Exact case classification; complete bundle auditing; rigorous outbreak tracing
Compassion Constructive feedback; genuine support for exposed and pressured staff
Accountability Every decision owned and documented; every outbreak honestly reviewed
Daily Quality Standards Checklist for Infection Control
โ— Apply rigorous hand hygiene compliance monitoring across departments today.
โ— Apply complete, systematic surveillance for all major HAI categories.
โ— Audit device-associated infection prevention bundle compliance thoroughly.
โ— Investigate any suspected outbreak cluster rapidly and rigorously.
โ— Document every surveillance, audit, and investigation step completely.
โ— Report any incident or safety concern through the quality reporting system.
In Infection Control, patient safety is measured against a transmission that is completely invisible until it
becomes clinical illness โ€” the truest measure of this committee's success is the outbreak, the device
infection, and the crisis that, because of their sustained vigilance, never had the chance to happen at all.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 26
CHAPTER 6: CONFIDENTIALITY, PRIVACY, AND INFORMATION
SECURITY
Infection control involves particularly sensitive information, including patient outbreak investigation data and
staff occupational exposure records, requiring heightened confidentiality discipline.
1. Privacy in Infection Control Practice
Responsibilities
โ— Conduct outbreak investigation interviews in as private a setting as available.
โ— Never discuss one patient's or staff member's information within earshot of unauthorized persons.
โ— Apply particular discretion when discussing outbreak investigation and exposure findings.
2. Confidentiality of Sensitive Findings
Overview
Outbreak investigation data and occupational exposure records carry particular sensitivity, potentially affecting
both patient and staff wellbeing and institutional reputation.
Responsibilities
โ— Handle outbreak and exposure information with heightened confidentiality until appropriate
communication occurs.
โ— Communicate only the clinically and administratively necessary information to relevant parties.
3. Clinical Data and EMR/HIS Confidentiality
Responsibilities
โ— Access only the surveillance and patient records necessary for current responsibilities.
โ— Never discuss surveillance or investigation information with anyone outside the legitimate committee
and care team.
โ— Follow hospital IT and cybersecurity policy for all EMR/HIS and infection control surveillance system
access.
โ— Never leave workstations unlocked or logged in when unattended.
4. Cybersecurity of Infection Control Surveillance Systems
Why Cybersecurity Is a Patient Safety Issue
Infection control surveillance systems store data upon which outbreak detection and patient safety directly
depend. A compromised system risks both sensitive data breach and, if surveillance data is corrupted, a
genuine outbreak signal going undetected.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 27
Responsibilities
โ— Use only authorized, unique login credentials for all EMR/HIS and surveillance system access.
โ— Never share login credentials with colleagues, regardless of workload pressure.
โ— Never connect personal devices to hospital clinical networks without IT authorization.
โ— Report any suspected unauthorized access or cybersecurity anomaly to IT security immediately.
5. Confidentiality for High-Profile and Vulnerable Patients
Responsibilities
โ— Maintain the same confidentiality standard for high-profile or notorious patients as for every other
patient.
โ— Never disclose patient identity, diagnosis, or condition to media or unauthorized persons.
Confidentiality Checklist for the Infection Control Team
โ— Conduct investigation interviews with maximum available privacy.
โ— Handle outbreak and exposure information with heightened discretion.
โ— Use only authorized credentials for EMR/HIS and surveillance information systems.
โ— Never connect personal devices to hospital clinical networks without IT authorization.
In Infection Control, confidentiality must be actively maintained for outbreak and exposure information
carrying particular sensitivity, demanding a discretion this team applies without exception.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 28
CHAPTER 7: STANDARD OPERATING PROCEDURES (SOPs) FOR
INFECTION CONTROL
Objectives of Infection Control SOPs
โ— Ensure consistent, rigorous surveillance and compliance monitoring across every department.
โ— Minimize harm through systematic, documented prevention protocols.
โ— Support NABH/JCI/CDC-NHSN accreditation compliance for infection prevention standards.
โ— Provide a defensible clinical framework for outbreak investigation and quality improvement.
SOP 1: Hand Hygiene Compliance Monitoring
Purpose
To sustain genuine, high hand hygiene compliance across every department.
Procedure
โ— Step 1: Apply Systematic Direct Observation โ€” apply standardized WHO Five Moments observation
methodology.
โ— Step 2: Apply Electronic Monitoring Where Available โ€” supplement observation with electronic
compliance data.
โ— Step 3: Provide Constructive Feedback โ€” provide honest, constructive feedback to departments and
individuals.
โ— Step 4: Document โ€” document the complete compliance monitoring and feedback record.
Quality Standards
โ— Hand hygiene compliance sustained at or above WHO-recommended targets.
SOP 2: Healthcare-Associated Infection Surveillance
Purpose
To detect HAI trends and emerging clusters systematically.
Procedure
โ— Step 1: Apply Standardized Case Definitions โ€” apply CDC/NHSN or equivalent standardized definitions.
โ— Step 2: Apply Complete Case Ascertainment โ€” apply systematic case-finding across all applicable
units.
โ— Step 3: Analyse Trends Regularly โ€” analyse surveillance data for emerging patterns.
โ— Step 4: Document โ€” document the complete surveillance record.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 29
Quality Standards
โ— 100% of applicable units included in systematic HAI surveillance.
SOP 3: Outbreak Investigation and Response
Purpose
To rapidly identify and control the source of any suspected outbreak.
Procedure
โ— Step 1: Confirm the Outbreak โ€” apply case definition and line listing to confirm genuine clustering.
โ— Step 2: Investigate the Source โ€” apply epidemiological investigation to identify the genuine source.
โ— Step 3: Apply Control Measures โ€” apply immediate control measures to break the transmission chain.
โ— Step 4: Document and Report โ€” document the complete investigation and report per regulatory
requirement.
Quality Standards
โ— 100% of suspected outbreak clusters receive documented, rapid investigation.
SOP 4: Central Line-Associated Bloodstream Infection Bundle
Purpose
To prevent CLABSI through complete, evidence-based bundle compliance.
Procedure
โ— Step 1: Apply Insertion Bundle โ€” apply hand hygiene, maximal barrier precautions, and chlorhexidine
skin antisepsis.
โ— Step 2: Apply Maintenance Bundle โ€” apply daily review of line necessity and dressing care.
โ— Step 3: Audit Compliance Regularly โ€” audit complete bundle compliance, not sampled elements.
โ— Step 4: Document โ€” document the complete bundle compliance record.
Quality Standards
โ— 100% documented compliance with complete CLABSI prevention bundle.
SOP 5: Catheter-Associated UTI and Ventilator-Associated Pneumonia Bundles
Purpose
To prevent CAUTI and VAP through complete, evidence-based bundle compliance.
Procedure
โ— Step 1: Apply CAUTI Bundle โ€” apply catheter necessity review, aseptic insertion, and closed drainage
system maintenance.
โ— Step 2: Apply VAP Bundle โ€” apply head-of-bed elevation, sedation vacation, and oral care protocols.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 30
โ— Step 3: Audit Compliance Regularly โ€” audit complete bundle compliance for both categories.
โ— Step 4: Document โ€” document the complete bundle compliance record.
Quality Standards
โ— 100% documented compliance with complete CAUTI and VAP prevention bundles.
SOP 6: Surgical Site Infection Prevention Bundle
Purpose
To prevent SSI through complete, evidence-based perioperative bundle compliance.
Procedure
โ— Step 1: Apply Preoperative Bundle โ€” apply appropriate skin preparation and antibiotic prophylaxis
timing.
โ— Step 2: Apply Intraoperative Bundle โ€” apply normothermia maintenance and glycemic control.
โ— Step 3: Apply Postoperative Surveillance โ€” apply systematic SSI surveillance through appropriate
follow-up period.
โ— Step 4: Document โ€” document the complete bundle compliance and surveillance record.
Quality Standards
โ— 100% documented compliance with complete SSI prevention bundle.
SOP 7: Isolation Precautions and PPE Compliance
Purpose
To prevent transmission through correct isolation category application.
Procedure
โ— Step 1: Apply Correct Isolation Classification โ€” classify per transmission route (contact, droplet,
airborne).
โ— Step 2: Verify PPE Availability and Use โ€” verify appropriate PPE is available and genuinely used.
โ— Step 3: Audit Compliance Regularly โ€” audit isolation and PPE compliance through direct observation.
โ— Step 4: Document โ€” document the complete isolation and PPE compliance record.
Quality Standards
โ— 100% of applicable patients receive correct isolation classification.
SOP 8: Environmental Cleaning and Sterilization Verification
Purpose
To ensure environmental and equipment cleanliness beyond visual inspection.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 31
Procedure
โ— Step 1: Apply Systematic Cleaning Verification โ€” apply ATP testing or fluorescent marker verification.
โ— Step 2: Apply CSSD Sterilization Quality Control โ€” apply biological and chemical indicator monitoring.
โ— Step 3: Address Any Identified Gap Immediately โ€” apply immediate corrective action for any
deviation.
โ— Step 4: Document โ€” document the complete verification record.
Quality Standards
โ— 100% compliance with scheduled environmental and sterilization verification.
SOP 9: Antimicrobial Stewardship Program Oversight
Purpose
To govern institutional antimicrobial stewardship policy and monitor compliance.
Procedure
โ— Step 1: Apply Institutional Stewardship Policy โ€” apply evidence-based prescribing guidelines.
โ— Step 2: Monitor Prescribing Compliance โ€” monitor compliance in coordination with pharmacy and
microbiology.
โ— Step 3: Provide Prescriber Feedback โ€” provide constructive, evidence-based feedback to prescribers.
โ— Step 4: Document โ€” document the complete stewardship oversight record.
Quality Standards
โ— Regular, documented antimicrobial stewardship compliance monitoring.
SOP 10: Healthcare Worker Exposure and Post-Exposure Prophylaxis
Purpose
To manage occupational exposure rigorously and support affected healthcare workers.
Procedure
โ— Step 1: Apply Immediate Exposure Assessment โ€” assess the exposure type and risk immediately.
โ— Step 2: Apply Post-Exposure Prophylaxis โ€” apply appropriate prophylaxis per current guidelines
without delay.
โ— Step 3: Provide Follow-Up Support โ€” provide genuine follow-up monitoring and support.
โ— Step 4: Document โ€” document the complete exposure and prophylaxis record.
Quality Standards
โ— 100% of occupational exposures receive documented, immediate assessment and appropriate
prophylaxis.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 32
Infection Control SOP Daily Compliance Checklist
โ— Hand hygiene compliance monitored across departments today.
โ— Complete surveillance maintained for all major HAI categories.
โ— Any incident, outbreak signal, or safety concern reported through the appropriate system.
SOPs in Infection Control are the operating instructions for breaking an invisible chain of transmission
before it ever becomes visible. When followed consistently, they are the systematic foundation of sustained
hand hygiene, complete surveillance, and rigorous bundle compliance for every patient this committee
protects.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 33
CHAPTER 8: COMMUNICATION WITH SPECIAL GROUPS
The Infection Control Committee communicates across a distinctive range of circumstances โ€” from frontline
nursing staff receiving compliance feedback, to a department facing a confirmed outbreak, to hospital
leadership requiring surveillance data for strategic decisions, to public health authorities requiring honest,
timely reporting. Excellent infection control practice requires adapted communication for each of these
circumstances.
1. Frontline Nursing and Clinical Staff
Communication Guidelines
โ— Communicate hand hygiene and bundle compliance feedback constructively and privately.
โ— Explain the genuine rationale behind each prevention measure, not merely the requirement.
2. Departments Facing a Confirmed Outbreak
Communication Guidelines
โ— Communicate findings transparently, without minimizing genuine concern or inducing unnecessary
panic.
โ— Provide clear, actionable guidance on control measures and ongoing monitoring.
3. Hospital Leadership and Governance
Communication Guidelines
โ— Present surveillance data, compliance trends, and outbreak findings in accessible, actionable formats.
โ— Advocate for necessary resources with clear patient safety justification.
4. Public Health Authorities
Communication Guidelines
โ— Communicate honestly and promptly per regulatory reporting requirement.
โ— Coordinate transparently on any broader public health investigation.
5. Patients and Families Affected by a Healthcare-Associated Infection
Overview
A patient or family affected by a healthcare-associated infection deserves honest, compassionate
communication about what occurred and what is being done.
Communication Guidelines
โ— Communicate honestly and compassionately about the infection and its management.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 34
โ— Communicate genuine institutional actions taken to prevent recurrence.
6. Exposed Healthcare Workers
Communication Guidelines
โ— Communicate exposure risk and prophylaxis information honestly and supportively.
โ— Provide genuine reassurance alongside honest risk information.
7. Environmental Services and CSSD Staff
Communication Guidelines
โ— Communicate cleaning and sterilization verification findings clearly and constructively.
โ— Support genuine process improvement rather than blame alone.
8. Hospital Administration and Quality/Accreditation Bodies
Communication Guidelines
โ— Present compliance, surveillance, and outbreak data in management-accessible formats.
โ— Advocate for necessary resources (staffing, surveillance systems, training) with clear patient safety
justification.
Universal Infection Control Communication Principles
โ— Communicate honestly, even when findings are genuinely uncomfortable for the institution.
โ— Respond to every genuine outbreak signal with appropriate urgency, without inducing unnecessary
panic.
โ— Always confirm genuine understanding, particularly for compliance feedback and control measures.
โ— Document every significant communication completely.
The Infection Control Committee that communicates with equal honesty toward a colleague's compliance
gap and a hospital leader's strategic question serves every stakeholder at maximum impact โ€” transparent,
constructive communication delivered alongside the genuine urgency an invisible transmission risk
deserves.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 35
CHAPTER 9: HANDLING DIFFICULT SITUATIONS
Common Difficult Situations for the Infection Control Committee
โ— A department resists hand hygiene or bundle compliance feedback defensively.
โ— A suspected outbreak cluster is genuinely ambiguous, requiring careful investigation.
โ— Hospital leadership is reluctant to allocate resources for a needed intervention.
โ— A colleague appears to have falsified or minimized compliance data.
โ— A confirmed outbreak requires difficult, transparent communication with affected patients.
โ— An antimicrobial stewardship recommendation meets prescriber resistance.
โ— A healthcare worker exposure occurs with genuine uncertainty about the exposure source.
โ— A department requests an isolation precaution exception for convenience.
โ— A public health authority requests information the institution is reluctant to share.
โ— A significant compliance gap is discovered only after a patient has already developed an infection.
Core Principles for Handling Difficult Situations
1. Surveillance and Compliance Integrity Are Never Compromised
In every difficult situation, genuine surveillance accuracy and rigorous compliance monitoring drive every
decision โ€” no institutional discomfort or convenience, however genuine, justifies a shortcut in either.
2. Apply Standardized Protocols Under Pressure
Institutional resistance and ambiguous findings are precisely when standardized protocols matter most โ€”
resist the temptation to improvise when a proven protocol exists.
3. Escalate Immediately and Persistently
A genuine safety concern is not resolved until it reaches someone who can act on it โ€” escalate through
alternative channels if the first attempt does not produce a response.
4. Document Everything
Every difficult situation must be contemporaneously documented โ€” what was found, what was
communicated, what decisions were made, and by whom.
Handling Defensive Resistance to Compliance Feedback
Steps
โ— Communicate the genuine patient safety rationale calmly and constructively.
โ— Escalate to department leadership if resistance genuinely persists.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 36
Handling an Ambiguous Suspected Outbreak Cluster
Steps
โ— Apply rigorous epidemiological investigation to resolve genuine ambiguity.
โ— Apply the more cautious interpretation when uncertainty genuinely remains.
Handling Leadership Reluctance on Resource Allocation
Steps
โ— Present clear, data-driven patient safety and financial impact justification.
โ— Escalate through governance channels if a genuine safety risk persists unaddressed.
Handling Suspected Falsified Compliance Data
Steps
โ— Apply immediate, confidential investigation of the concern.
โ— Escalate to appropriate leadership and human resources per institutional protocol.
Handling Transparent Communication with Affected Patients
Steps
โ— Communicate honestly and compassionately about the infection and its management.
โ— Coordinate with the clinical and quality teams on genuine institutional response.
Handling Prescriber Resistance to Stewardship Recommendations
Steps
โ— Communicate the genuine evidence base clearly and respectfully.
โ— Escalate to medical leadership if resistance genuinely compromises patient safety.
Handling Uncertain Exposure Source
Steps
โ— Apply the more cautious, protective assessment when genuine uncertainty remains.
โ— Apply appropriate post-exposure prophylaxis pending further clarification.
Handling a Request for an Isolation Precaution Exception
Steps
โ— Decline the exception professionally, explaining the genuine transmission risk.
โ— Explore genuine alternative solutions addressing the underlying convenience concern.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 37
Handling a Public Health Information Request
Steps
โ— Provide honest, complete information per legal and regulatory obligation.
โ— Coordinate with institutional leadership and legal counsel as genuinely needed.
Handling a Compliance Gap Discovered After Patient Harm
Steps
โ— Apply immediate, honest disclosure and RCA.
โ— Apply immediate corrective action preventing recurrence.
The CALM Model for Infection Control
โ— C โ€“ Control the immediate transmission or safety risk.
โ— A โ€“ Acknowledge the situation accurately, including genuine uncertainty.
โ— L โ€“ Lead with evidence โ€” surveillance data, bundle protocols, and epidemiological findings.
โ— M โ€“ Manage through documented escalation channels when needed.
Difficult situations in Infection Control are always, ultimately, tests of whether surveillance and compliance
integrity hold firm under institutional or professional pressure. The team that never compromises either,
escalates persistently, and communicates honestly even when it is uncomfortable is fulfilling the highest
professional obligation of infection control practice.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 38
CHAPTER 10: EMERGENCY RESPONSE โ€” CRITICAL INFECTION CONTROL
PRESENTATIONS
Overview
Certain presentations demand the Infection Control Committee's most immediate, standardized, and
rehearsed response โ€” scenarios where the difference between a coordinated, protocol-driven response and
an improvised one is measured directly in whether an invisible transmission chain is broken before it spreads
further.
Critical Presentations Requiring Immediate Response
โ— A confirmed cluster of healthcare-associated infections in a single unit.
โ— A multidrug-resistant organism (MDRO) outbreak.
โ— A significant occupational exposure (needlestick, mucocutaneous, airborne) in a healthcare worker.
โ— A suspected or confirmed highly transmissible pathogen requiring immediate isolation.
โ— A sterilization failure identified in CSSD affecting multiple patients.
โ— A water system or environmental source contamination event (e.g., Legionella).
โ— A significant hand hygiene or bundle compliance failure identified during an active outbreak.
โ— A community or regional outbreak requiring coordinated institutional preparedness.
โ— A breach in isolation precautions for a highly transmissible pathogen.
โ— A public health authority alert requiring immediate institutional response.
1. Confirmed HAI Cluster in a Single Unit
Immediate Response
โ— Apply immediate case confirmation and line listing.
โ— Apply immediate control measures while investigation proceeds.
2. Multidrug-Resistant Organism Outbreak
Steps
โ— Apply immediate contact precautions and cohorting as indicated.
โ— Apply immediate enhanced surveillance and environmental assessment.
3. Significant Occupational Exposure
Steps
โ— Apply immediate exposure assessment and post-exposure prophylaxis without delay.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 39
โ— Provide immediate, genuine support and follow-up planning.
4. Suspected Highly Transmissible Pathogen
Steps
โ— Apply immediate, appropriate isolation precautions pending confirmation.
โ— Notify appropriate leadership and public health authorities as indicated.
5. Sterilization Failure Affecting Multiple Patients
Steps
โ— Apply immediate quarantine of affected instrument sets.
โ— Apply immediate patient notification and follow-up per institutional protocol.
6. Environmental Source Contamination Event
Steps
โ— Apply immediate environmental sampling and remediation.
โ— Apply enhanced surveillance for related cases.
7. Bundle Compliance Failure During Active Outbreak
Steps
โ— Apply immediate corrective retraining and enhanced monitoring.
โ— Escalate to department and hospital leadership immediately.
8. Community or Regional Outbreak Preparedness
Steps
โ— Apply immediate institutional preparedness review and resource assessment.
โ— Coordinate with public health authorities on surveillance and response planning.
9. Isolation Precaution Breach
Steps
โ— Apply immediate assessment of exposure risk to affected patients and staff.
โ— Apply immediate corrective action and enhanced monitoring.
10. Public Health Authority Alert
Steps
โ— Apply immediate institutional response per the alert's guidance.
โ— Coordinate transparently with public health authorities throughout the response.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 40
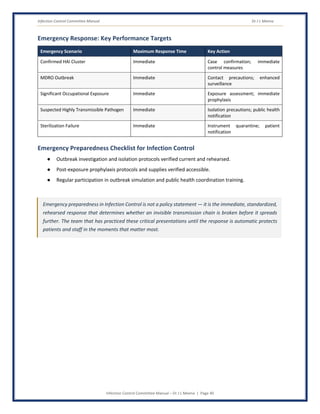
Emergency Response: Key Performance Targets
Emergency Scenario Maximum Response Time Key Action
Confirmed HAI Cluster Immediate Case confirmation; immediate
control measures
MDRO Outbreak Immediate Contact precautions; enhanced
surveillance
Significant Occupational Exposure Immediate Exposure assessment; immediate
prophylaxis
Suspected Highly Transmissible Pathogen Immediate Isolation precautions; public health
notification
Sterilization Failure Immediate Instrument quarantine; patient
notification
Emergency Preparedness Checklist for Infection Control
โ— Outbreak investigation and isolation protocols verified current and rehearsed.
โ— Post-exposure prophylaxis protocols and supplies verified accessible.
โ— Regular participation in outbreak simulation and public health coordination training.
Emergency preparedness in Infection Control is not a policy statement โ€” it is the immediate, standardized,
rehearsed response that determines whether an invisible transmission chain is broken before it spreads
further. The team that has practiced these critical presentations until the response is automatic protects
patients and staff in the moments that matter most.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 41
CHAPTER 11: DIGITAL COMPETENCY FOR THE INFECTION CONTROL
TEAM
Objectives
โ— Enable the Infection Control team to use surveillance, compliance monitoring, and outbreak
investigation systems accurately, securely, and efficiently.
โ— Leverage technology to improve surveillance sensitivity and compliance documentation.
โ— Manage the cybersecurity of infection control information systems as a core patient safety function.
Core Digital Competencies for the Infection Control Team
1. Electronic Surveillance Systems
Essential Skills
โ— Use electronic HAI surveillance systems accurately for case ascertainment and trend analysis.
2. Electronic Hand Hygiene Monitoring Systems
Essential Skills
โ— Use electronic hand hygiene monitoring systems accurately, supplementing direct observation.
3. Outbreak Investigation and Epidemiological Software
Essential Skills
โ— Use epidemiological analysis software accurately for line listing and epidemic curve construction.
4. Electronic Medical Record (EMR) / Hospital Information System (HIS)
Essential Skills
โ— Document surveillance, compliance, and investigation findings accurately and in real time.
5. AI-Assisted Surveillance and Outbreak Detection Tools
Awareness
โ— AI-assisted tools are increasingly applied to support early outbreak signal detection.
โ— Understand and appropriately leverage these tools while maintaining independent epidemiological
judgment โ€” AI tools are decision-support, not a substitute for genuine surveillance and investigation.
6. Antimicrobial Stewardship Tracking Systems
Essential Skills
โ— Use antimicrobial stewardship tracking systems accurately to monitor prescribing compliance.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 42
7. Cybersecurity and Information Security
Personal Digital Security Responsibilities
โ— Use unique, strong credentials for all EMR/HIS and surveillance system logins.
โ— Lock or log out of workstations whenever stepping away, even briefly.
โ— Never connect personal devices to hospital clinical networks.
โ— Report all cybersecurity anomalies to IT security immediately.
Digital Competency Checklist
โ— Navigate surveillance, hand hygiene monitoring, and outbreak investigation systems for all core
functions without assistance.
โ— Apply accurate, complete surveillance and compliance documentation.
โ— Apply basic cybersecurity practices to all clinical system access.
โ— Know the downtime procedure for surveillance system failure.
Digital competency for the Infection Control team is the ability to integrate rigorous epidemiological
judgment with the surveillance, monitoring, and investigation systems that modern infection prevention
increasingly depends upon โ€” using technology to extend, never replace, the sustained vigilance that
defines safe infection control practice.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 43
CHAPTER 12: DAILY INFECTION CONTROL CHECKLIST
Objectives
โ— Provide a structured daily framework for sustained hand hygiene and surveillance discipline.
โ— Ensure every surveillance, compliance, and safety obligation is addressed every shift.
โ— Support accurate documentation and departmental performance data quality.
PART A: START-OF-SHIFT CHECKLIST
Personal and Professional Readiness
โ— Appropriate professional attire and ID badge displayed.
โ— EMR/HIS and surveillance systems functional and accessible.
Equipment and Readiness Review
โ— Verified hand hygiene monitoring equipment/access functional.
โ— Verified PPE availability across relevant departments.
PART B: SURVEILLANCE CHECKLIST
โ— Systematic HAI surveillance maintained across all applicable units today.
โ— Any suspected cluster or outbreak signal investigated immediately.
PART C: HAND HYGIENE AND BUNDLE CHECKLIST
โ— Hand hygiene compliance monitored across departments today.
โ— Device-associated infection prevention bundle compliance audited thoroughly.
PART D: ISOLATION AND ENVIRONMENTAL CHECKLIST
โ— Isolation precaution classification and compliance verified for applicable patients.
โ— Environmental cleaning and sterilization verification conducted per schedule.
PART E: STEWARDSHIP AND EXPOSURE CHECKLIST
โ— Antimicrobial stewardship compliance monitored in coordination with pharmacy.
โ— Any occupational exposure assessed and managed immediately.
PART F: SAFETY AND INCIDENT CHECKLIST
โ— Any incident, outbreak signal, or compliance concern reported through the appropriate system.
โ— CAPA actions from previous incidents reviewed for completion.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 44
PART G: END-OF-SHIFT CHECKLIST
โ— All surveillance and compliance records updated and complete for the shift.
โ— Structured handover prepared for the incoming shift.
โ— Clinical systems securely logged out.
Daily Self-Assessment for the Infection Control Team
โ— Did we apply rigorous hand hygiene compliance monitoring across departments today?
โ— Did we apply complete, systematic surveillance for all major HAI categories?
โ— Did we audit device-associated infection prevention bundle compliance thoroughly?
โ— Did we investigate any suspected outbreak cluster rapidly and rigorously?
โ— Did we communicate compliance feedback honestly and constructively?
A consistent, structured daily routine โ€” from start-of-shift equipment verification to end-of-shift handover
โ€” transforms individual vigilance into a systemic infection prevention programme whose greatest success
is measured by what never happened at all.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 45
CHAPTER 13: KEY PERFORMANCE INDICATORS (KPIs) FOR INFECTION
CONTROL
Objectives
โ— Measure hand hygiene, surveillance, and bundle compliance performance objectively.
โ— Enable data-driven continuous improvement in Infection Control practice.
โ— Support NABH/JCI/CDC-NHSN accreditation standards for infection prevention.
โ— Demonstrate the value and patient safety impact of the Infection Control Committee to institutional
leadership.
Categories of Infection Control KPIs
1. Hand Hygiene KPIs
KPI Definition Target
Hand Hygiene Compliance Rate % compliance with WHO Five Moments across observed
encounters
โ‰ฅ WHO-
recommended
target
Hand Hygiene Feedback
Completion
% of identified compliance gaps receiving documented
feedback
100%
2. HAI Rate KPIs
KPI Definition Target
CLABSI Rate Central line-associated bloodstream infections per
1,000 line-days
At or below
national/international
benchmark
CAUTI Rate Catheter-associated UTIs per 1,000 catheter-days At or below
national/international
benchmark
VAP Rate Ventilator-associated pneumonia per 1,000
ventilator-days
At or below
national/international
benchmark
SSI Rate Surgical site infections per 100 procedures At or below
national/international
benchmark
3. Bundle Compliance KPIs
KPI Definition Target
CLABSI Bundle Compliance % documented complete compliance with CLABSI
prevention bundle
100%
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 46
KPI Definition Target
CAUTI/VAP Bundle Compliance % documented complete compliance with CAUTI/VAP
prevention bundles
100%
4. Surveillance and Outbreak KPIs
KPI Definition Target
Outbreak Investigation Timeliness % of suspected clusters investigated within defined
timeframe
100%
Surveillance Completeness % of applicable units included in systematic HAI
surveillance
100%
5. Outcome and Governance KPIs
KPI Definition Target
RCA Completion Rate % of significant outbreaks/adverse events with
completed RCA
100%
Occupational Exposure Response
Compliance
% of exposures receiving documented, immediate
assessment and prophylaxis
100%
Antimicrobial Stewardship Compliance % of prescribing reviewed against stewardship
guidelines
โ‰ฅ 90%
Using KPIs for Continuous Improvement
โ— Review all Infection Control KPIs regularly at committee and hospital governance meetings.
โ— Analyse hand hygiene, HAI rate, and bundle compliance trends to identify targeted process
improvements.
โ— Use outbreak investigation timeliness data to strengthen surveillance sensitivity.
โ— Present KPI data to hospital management to demonstrate the patient safety impact of Infection
Control excellence.
Infection Control KPIs translate the discipline of protecting against an invisible transmission risk into
institutional accountability โ€” demonstrating that the investment in sustained hand hygiene, complete
surveillance, and rigorous bundle compliance is a measurable, trackable programme whose greatest
success is the outbreak and the infection that never happened at all.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 47
CHAPTER 14: TOP 20 DO'S & TOP 20 DON'TS FOR INFECTION CONTROL
Introduction
The Infection Control Committee protects against a transmission risk that is completely invisible until a patient
becomes clinically ill. Their daily professional decisions โ€” about hand hygiene monitoring, surveillance
completeness, and bundle compliance โ€” determine whether the place meant to heal ever becomes the source
of new harm. These Do's and Don'ts provide the practical daily architecture of Infection Control excellence.
TOP 20 DO'S FOR INFECTION CONTROL
โ— 1. Monitor Hand Hygiene at Every WHO Five Moment โ€” Systematically, every department.
โ— 2. Provide Constructive, Not Punitive, Compliance Feedback โ€” Building genuine improvement.
โ— 3. Maintain Complete, Systematic HAI Surveillance โ€” Every applicable unit, every day.
โ— 4. Apply Standardized Case Definitions Exactly โ€” Never under- or over-classify.
โ— 5. Investigate Every Suspected Outbreak Immediately โ€” No delay, ever.
โ— 6. Audit Complete Bundle Compliance โ€” Never sample only some elements.
โ— 7. Apply Correct Isolation Classification โ€” Matched to genuine transmission route.
โ— 8. Apply Immediate Post-Exposure Prophylaxis โ€” Every occupational exposure, without delay.
โ— 9. Communicate Outbreak Findings Transparently โ€” Never minimize genuine concern.
โ— 10. Report Public Health Findings Honestly and Promptly โ€” Per regulatory requirement.
โ— 11. Debrief After Every Significant Event โ€” Consolidate learning while it is fresh.
โ— 12. Provide Structured Handover for Every Transfer โ€” SBAR or equivalent, every time.
โ— 13. Communicate with Exact, Constructive Language โ€” Compliance depends on genuine trust.
โ— 14. Report Every Near-Miss Honestly โ€” Including your own, especially in surveillance.
โ— 15. Verify Sterilization and Environmental Cleaning Beyond Visual Inspection โ€” Every time.
โ— 16. Support Antimicrobial Stewardship with Genuine Evidence โ€” Never mere directive.
โ— 17. Apply the Same Rigour to Every Department โ€” Regardless of seniority or convenience.
โ— 18. Coordinate Proactively with Microbiology and Pharmacy โ€” For stewardship success.
โ— 19. Celebrate Genuine Sustained Compliance โ€” Not only crisis response.
โ— 20. Continue Learning โ€” Infection prevention evidence evolves. The team that does not learn
continuously treats today's patients with yesterday's protocols.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 48
TOP 20 DON'TS FOR INFECTION CONTROL
โ— 1. Don't Skip Hand Hygiene Monitoring โ€” Regardless of workload pressure.
โ— 2. Don't Deliver Compliance Feedback Punitively โ€” Build improvement, not resentment.
โ— 3. Don't Leave Any Unit Outside Systematic Surveillance โ€” Complete coverage, always.
โ— 4. Don't Deviate from Standardized Case Definitions โ€” Consistency protects accuracy.
โ— 5. Don't Delay Outbreak Investigation โ€” Ever, for any reason.
โ— 6. Don't Accept Partial Bundle Compliance โ€” Every element matters.
โ— 7. Don't Misclassify Isolation Precautions โ€” Match the genuine transmission route.
โ— 8. Don't Delay Post-Exposure Prophylaxis โ€” Time-critical, every time.
โ— 9. Don't Minimize an Outbreak to Avoid Institutional Discomfort โ€” Ever.
โ— 10. Don't Skip Team Debriefing After a Critical Event โ€” Unprocessed events repeat their gaps.
โ— 11. Don't Hand Over Complex Cases Informally โ€” Structure protects against critical omissions.
โ— 12. Don't Use Ambiguous Language in Any Report โ€” Every word carries safety weight.
โ— 13. Don't Hide or Minimize a Near-Miss โ€” Suppressed incidents cannot drive the improvement that
prevents recurrence.
โ— 14. Don't Rely on Visual Inspection Alone for Cleaning Verification โ€” Apply genuine testing.
โ— 15. Don't Issue Stewardship Directives Without Evidence โ€” Support with genuine data.
โ— 16. Don't Let Department Seniority Affect Compliance Standards โ€” Every department, equally.
โ— 17. Don't Work in Isolation from Microbiology and Pharmacy โ€” Coordinate proactively.
โ— 18. Don't Focus Only on Crisis Response โ€” Recognize genuine sustained compliance too.
โ— 19. Don't Delay Public Health Reporting โ€” Per regulatory timeline, always.
โ— 20. Don't Practice Outside Current Infection Prevention Evidence โ€” Personal habit or outdated
method must never override current best practice.
Infection Control Golden Rules
โ— Monitor hand hygiene at every moment โ€” systematically, every department.
โ— Give constructive feedback โ€” building improvement, not resentment.
โ— Maintain complete surveillance โ€” every applicable unit, every day.
โ— Investigate every suspected outbreak immediately โ€” no delay, ever.
โ— Audit complete bundle compliance โ€” never sample only some elements.
โ— Apply correct isolation classification โ€” matched to genuine transmission route.
โ— Apply immediate post-exposure prophylaxis โ€” every exposure, without delay.
โ— Communicate outbreak findings transparently โ€” never minimize genuine concern.
โ— Report every near-miss โ€” honestly, including your own.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 49
โ— Never stop learning โ€” today's infection prevention evidence is not yesterday's.
Daily Commitment Statement
โ€œToday, I will monitor hand hygiene at every critical moment, maintain complete surveillance, audit every
bundle element thoroughly, and investigate any outbreak signal immediately โ€” because the infection I prevent
is the one no one will ever see, and success here looks like nothing happened at all.โ€
The Top 20 Do's and Top 20 Don'ts are the daily professional architecture of Infection Control excellence
โ€” each shaped by the understanding that this discipline's greatest triumphs are permanently invisible, and
that there are no minor lapses when a skipped hand hygiene moment or an incomplete bundle is the exact
instant an invisible chain of transmission begins.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 50
CHAPTER 15: INFECTION CONTROL PROFESSIONAL PLEDGE
Introduction
An Infection Control Professional Pledge is a formal, collective commitment to uphold the highest standards of
hand hygiene compliance, systematic surveillance, and evidence-based bundle adherence. It serves as a daily
affirmation that the place meant to heal is never allowed to become the source of new harm.
Official Infection Control Professional Pledge
โ€œWe solemnly pledge that as the Infection Control Committee, we will fulfil our collective and individual
responsibilities with the highest standards of sustained vigilance, surveillance rigour, and unwavering
commitment to a discipline whose greatest successes are permanently invisible.
We will monitor hand hygiene compliance systematically at every one of the WHO's five critical moments,
providing honest, constructive feedback that builds genuine improvement rather than resentment, and we will
maintain complete, systematic surveillance for every major category of healthcare-associated infection, never
leaving a unit outside our watch.
We will audit every element of every evidence-based prevention bundle completely, never accepting partial
compliance as sufficient, and we will investigate every suspected outbreak signal immediately and rigorously,
tracing every cluster to its true source rather than a convenient assumption.
We will apply correct isolation precautions matched to genuine transmission route, provide immediate post-
exposure prophylaxis to every affected healthcare worker, and govern antimicrobial stewardship with genuine
evidence, supporting rather than merely directing our prescribing colleagues.
We will report every incident and near-miss honestly, resist any pressure to minimize an outbreak finding for
institutional comfort, and continuously expand our knowledge and skill, knowing that infection prevention
evidence evolves and that the team that does not learn continuously treats today's patients with yesterday's
protocols.
With unwavering vigilance, genuine surveillance rigour, and profound respect for a transmission risk that is
invisible until it becomes illness, we pledge to be the Infection Control Committee whose success is measured
by the outbreak, the device infection, and the crisis that never happened at all.โ€
Daily Commitment Statement
โ€œToday, we commit to monitoring hand hygiene at every critical moment, maintaining complete surveillance,
auditing every bundle element thoroughly, and investigating any outbreak signal immediately โ€” because the
infection we prevent is the one no one will ever see, and success here looks like nothing happened at all.โ€
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 51
Core Values Reflected in the Pledge
1. Sustained Hand Hygiene Vigilance
Compliance monitored systematically at every critical moment, regardless of workload or department.
2. Complete Surveillance
Every applicable unit included in systematic HAI surveillance, without exception.
3. Rigorous Bundle Compliance
Every element of every prevention bundle audited completely, never sampled.
4. Rapid, Honest Outbreak Investigation
Every suspected cluster investigated immediately, with transparent, honest communication.
5. Evidence-Based Stewardship
Antimicrobial stewardship governed through genuine evidence and collaborative support.
6. Accountability
Every decision owned and documented; every outbreak honestly reviewed.
7. Continuous Learning
Infection prevention evidence evolves. Professional competence requires perpetual learning.
When the Pledge Should Be Recited
โ— At the beginning of every new Infection Control team member's appointment.
โ— At quality governance and outbreak review meetings.
โ— At NABH/JCI/CDC-NHSN accreditation preparation events.
โ— As a periodic collective affirmation, particularly following a significant adverse event.
Infection Control Oath of the Invisible Chain
โ€œWe pledge to break every invisible chain of transmission before it ever becomes visible โ€” because our
greatest success will always be the outbreak that never happened.โ€
Infection Control Signature Commitment
This pledge is recited collectively by the multidisciplinary Infection Control team and may be individually signed
by:
Name: ___________________________
Role: Infection Control Officer / Infection Control Nurse / Hospital Epidemiologist
Department: Infection Prevention and Control
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 52
Registration/Employee ID: _______________
Signature: ________________________
Date: ____________________________
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 53
CONCLUSION
There is a discipline in healthcare whose greatest successes are permanently invisible. This manual has
returned, again and again, to why this reality demands a discipline that never relaxes โ€” sustained hand hygiene
compliance because it is the single most powerful and most consistently under-performed intervention in
medicine, complete surveillance because transmission is invisible until illness appears, and rigorous bundle
compliance because partial adherence is not genuine prevention at all.
Throughout this manual, we have explored the full scope of Infection Control Committee professional practice
โ€” from hand hygiene compliance and systematic surveillance, through device-associated infection prevention
bundles and isolation precautions, to outbreak investigation, antimicrobial stewardship, and the professional
conduct that defines excellence across every category of infection prevention practice. These responsibilities
collectively define a discipline that demands both sustained, unglamorous vigilance and the analytical rigour
to trace every outbreak to its true source.
The Importance of the Infection Control Committee in Healthcare Quality
โ— The sustained hand hygiene monitor โ€” protecting patients through the single most powerful
intervention in medicine.
โ— The complete surveillance system โ€” detecting emerging clusters before they become visible crises.
โ— The rigorous bundle auditor โ€” ensuring every prevention element is genuinely followed, not merely
sampled.
โ— The rapid outbreak investigator โ€” tracing every cluster to its true source before it spreads further.
โ— The evidence-based steward โ€” protecting antibiotic effectiveness for every future patient.
โ— The honest reviewer โ€” examining every incident and near-miss to protect the next patient whose
safety depends on an invisible chain of vigilance holding firm.
Final Commitment
โ€œAs the Infection Control Committee, we commit to monitoring hand hygiene at every critical moment,
maintaining complete surveillance, auditing every bundle element thoroughly, and investigating any outbreak
signal immediately โ€” because the infection we prevent is the one no one will ever see, and success here looks
like nothing happened at all.โ€
Final Motto
โ€œThe Infection We Prevent Is the One No One Will Ever See โ€” Success Here Looks Like Nothing Happened at
All.โ€
Together, We Prove That the Absence of a Crisis Is Itself the Greatest Evidence of Our Vigilance.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 54
REFERENCES
Global Accreditation and Regulatory Standards
โ— World Health Organization (WHO) โ€“ WHO Guidelines on Hand Hygiene in Health Care.
โ— Joint Commission International (JCI) โ€“ Prevention and Control of Infections (PCI) Chapter, JCI
Accreditation Standards for Hospitals.
โ— National Accreditation Board for Hospitals & Healthcare Providers (NABH, India) โ€“ Standards for
Hospital Infection Control.
Surveillance and Epidemiology Standards
โ— U.S. Centers for Disease Control and Prevention (CDC) / National Healthcare Safety Network (NHSN) โ€“
Surveillance Definitions for Healthcare-Associated Infections.
โ— Association for Professionals in Infection Control and Epidemiology (APIC) โ€“ Infection Prevention and
Control Practice Guidance.
โ— Society for Healthcare Epidemiology of America (SHEA) โ€“ Compendium of Strategies to Prevent
Healthcare-Associated Infections.
Device-Associated Infection Prevention Standards
โ— CDC/NHSN โ€“ Evidence-Based Bundles for CLABSI, CAUTI, VAP, and SSI Prevention.
โ— Institute for Healthcare Improvement (IHI) โ€“ How-to Guides for Preventing Central Line and Catheter-
Associated Infections.
Isolation Precautions and PPE Standards
โ— CDC โ€“ Guideline for Isolation Precautions: Preventing Transmission of Infectious Agents in Healthcare
Settings.
Antimicrobial Stewardship Standards
โ— CDC โ€“ Core Elements of Hospital Antibiotic Stewardship Programs.
โ— Indian Council of Medical Research (ICMR) โ€“ Antimicrobial Resistance Surveillance and Stewardship
Guidelines.
Indian Regulatory and National Framework
โ— National Centre for Disease Control (NCDC), India โ€“ Guidelines for Hospital Infection Control and
Outbreak Reporting.
โ— Hospital Infection Society, India โ€“ Clinical Practice Guidelines.
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 55
โ— National Medical Commission (NMC) โ€“ Code of Medical Ethics Regulations Applicable to Infection
Control Practice.
Quality Improvement and Patient Safety Frameworks
โ— Institute for Healthcare Improvement (IHI) โ€“ Framework for Patient Safety and Quality Improvement
in Infection Prevention.
โ— World Health Organization โ€“ Global Patient Safety Action Plan 2021โ€“2030.
Cybersecurity and Digital Health Records
โ— NIST Cybersecurity Framework โ€“ Applied to Healthcare Surveillance Information Systems.
โ— HL7 International โ€“ Health Level Seven Data Interchange Standards.
This manual has been developed using internationally recognized principles and best practices from WHO
Guidelines on Hand Hygiene, JCI Prevention and Control of Infections Standards, NABH Hospital Infection
Control Standards, CDC/NHSN Surveillance Definitions and Bundle Guidance, APIC Practice Guidance, SHEA
Compendium of Strategies, CDC Isolation Precautions Guidelines, CDC Core Elements of Antibiotic Stewardship,
ICMR AMR Surveillance Guidelines, India's NCDC Guidelines, Hospital Infection Society Guidelines, and
applicable Indian statutory and regulatory requirements. Institutions should verify current versions of all cited
guidelines and regulatory requirements, as clinical protocols and accreditation standards are subject to
periodic revision.
เฅ เคœเคฏ เคฎเคพเคคเคพ เคฆ( เฅ
Infection Control Committee Manual Dr J L Meena
Infection Control Committee Manual โ€“ Dr J L Meena | Page 56

END OF MANUAL
Thank You
This manual has been prepared with the vision to empower the multidisciplinary Infection Control team with
global standards, best practices, and professional guidance to ensure the place meant to heal is never allowed
to become the source of new harm.
Our Commitment Continues
The journey of learning never ends. As infection prevention evidence and technology evolve, our commitment
to sustained hand hygiene, complete surveillance, and rigorous bundle compliance must remain unwavering
โ€” because a chain of transmission gives no visible warning when it is about to break.
Together, We Build Trust
Every hand washed at the right moment, every surveillance case classified accurately, every bundle element
completed without exception, and every outbreak traced to its true source contributes to one greater purpose
โ€” a hospital where the crisis, the outbreak, and the infection simply never had the chance to happen at all.
โ€œThe Infection We Prevent Is the One No One Will Ever See โ€” Success Here Looks Like Nothing
Happened at All.โ€
REMEMBER: Hand hygiene is our foundation โ€ข Surveillance is our vigilance โ€ข Bundles are our discipline โ€ข
Outbreaks are traced, not assumed โ€ข Learning is our journey
Thank you for being a part of this vital mission. Your dedication makes a difference every day.
Dr J L Meena