Imaging of Cystic
Renal Lesions
Presented by: Dr. Anish Dhakal
Resident, MD Radiodiagnosis
Kathmandu University School of Medical Sciences (KUSMS)
7th
August, 2026
Cystic renal lesions
The definition of “cystic mass” is a lesion with the solid portion
occupying not more than one-fourth (<25%) of the volume
Cystic renal masses constitute about 15% of all renal masses
Bosniak classification system introduced in 1986 by Mortan
Bosniak is a CT based classification system which helps robustly
categorize cystic renal lesions and guide further management.
Renal cysts
1. Serous renal cysts:
Most common cystic kidney disease and become more frequent with age.
Single or multiple and vary in size.
On ultrasound, they appear as round, anechoic cysts with a well-defined
wall, posterior acoustic enhancement, and no doppler blood flow.
On CT, they are well-defined, homogeneous, water-density lesions (0–20
HU) without calcification or contrast enhancement.
On MRI, they show low signal on T1, high signal on T2, and no contrast
enhancement.
2. Atypical cysts:
Serous cysts complicated by hemorrhage, infection, or ischemia, making
them difficult to distinguish from cystic tumors, infections, or other cystic
kidney diseases.
Renal Cysts- Introduction
Renal cysts usually represent notably dilated nephrons or
collecting ducts.
The term renal cystic disease refers to any disorder that
results from the presence of multiple renal cysts.
Imaging Modalities for Renal Cysts:
1. X-ray:
Plain radiography and excretory urography are indirect
imaging modalities and are relatively insensitive in
detecting and characterizing renal cysts.
Excretory urography may show the following imaging
findings when renal cysts are present:
Abnormality of the renal contour or adjacent fascial
planes, displacement of bowel loops or splayed ribs
Curvilinear or rim calcification in the cyst wall
Filling defects in the opacified cortex during the
nephrographic phase of urography
Splaying and distortion of the opacified collecting system
2. USG:
The modality where most renal cysts are detected incidentally.
A simple cyst detected in USG needs no further imaging. Complex cystic lesions
are imaged further.
Gray-scale, real-time sonography is a noninvasive, multiplanar direct imaging
modality, which requires no patient preparation, and unlike EU it shows the
mass lesion itself, along with changes in the renal parenchyma and renal sinus.
However, obesity and excessive bowel gas can obscure the kidneys.
Gray-scale US is useful in characterizing simple cysts but is limited in evaluation
of complex cysts
Color Doppler can aid in assessing blood flow in renal cystic lesions, however
with poor sensitivity.
As Bosniak classification relies on enhancement, various studies have shown
promising results using contrast-enhanced US in the evaluation of renal cystic
lesions based on the Bosniak classification system.
3. CT
Computed tomography is the main modality for imaging and characterizing cystic renal
lesions.
Multiphasic renal CT is obtained including unenhanced CT, corticomedullary phase,
nephrographic phase, and excretory phase. The nephrographic phase is the most valuable
for detecting mass lesions less than 3 cm which include clinically insignificant renal cysts and
RCCs.
A change of less than 10 HU from pre- to postcontrast images is considered typical of a
benign cyst. Pseudoenhancement that is defined as an artefactual increase in HU values of
>10 HU on contrast-enhanced CT can result from beam hardening artifact.
Very rarely, cystic tumors may enhance less than 10 HU. Majority of pathologic lesions
enhance more than 15 HU. An enhancement between 10 HU and 15 HU is considered
suspicious but not diagnostic of a tumor.
Also, if the lesion is smaller than twice the slice thickness used, then partial volume
averaging may result in misinterpretation. Virtual monochromatic imaging on dual-energy
computed tomography may completely eliminate pseudoenhancement in renal cysts larger
than 1.5 cm.
4. MRI:
Used for smaller cysts that may not be detectable or characterized with CT. Also used when radiation of CT
is to be avoided.
Multiplanar imaging capability and angiographic capabilities with excellent soft-tissue contrast resolution
have made MRI a useful method for evaluating the kidneys
High-field strengths, breathhold imaging, fat suppression techniques, and use of MR-contrast agents help
in differentiating tumor from cysts. The multiplanar imaging capability of MRI makes it easier to assess
polar lesions and coronal images make it simple for the urologist to visualize the relative position of a small
lesion if wedge resection or partial nephrectomy is to be planned.
Although the Bosniak classification has been described on CT, various researchers have proven that MR
may be equivalent to CT in Bosniak classification of cystic lesions.
Calcification is however better picked up on CT than on MR. Owing to increased contrast resolution, there
is increased sensitivity of MR for picking up septations and wall thickening on T2-weighted images. This can
result in false upgradation of the Bosniak category of the lesion. Other pitfalls include evaluation of
enhancement in hemorrhagic and calcified lesions. In these situations, subtraction imaging may be used.
Subtraction imaging technique can suffer from misregistration and additional noise.
In few equivocal cases, MR can be problem solving. Postcontrast free breathing 3D fat-suppressed T1

gradient echo (T1 vibe fat sat) sequence allows better evaluation of enhancement which forms the main
basis for Bosniak categorization of lesions. Diffusion-weighted imaging can also be of utility in
differentiating cystic renal masses from simple cysts.
5. Angiography
Prior to the advent of newer imaging modalities such as US, CT, and MRI,
angiography was commonly used for evaluation of renal mass lesions.
However, in the present era it is mainly indicated for interventional
procedures of vascular mass lesions of the kidney.
Actively bleeding tumors such as angiomyolipomas (AMLs) can be treated
with selective angiography by embolization of the intrarenal supply of the
tumor.
6. Biopsy
Biopsy may not give a high yield from cystic lesions owing to paucity of cells
within. It is however useful to biopsy or drain cystic lesions which are
suspected to be abscesses and may be attempted in patients with suspected
malignancy if they are poor surgical candidates.
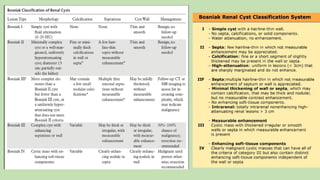
Bosniak classification
The Bosniak classification was described
in 1986. This classification helps the
radiologist to categorize each cystic renal
mass as "nonsurgical" (ie, benign in
category 1 and 2) or as "surgical" (ie,
requiring surgery in category 3 and 4).
After the original description, it became
obvious that there were some category II
cysts that were slightly more complicated
than most category II lesions, but not
complicated enough to place them in
category III. For that reason, a category IIF
(F for follow-up) was introduced in 1993.
Changes to this classification were made in 1990s and in
2005 and now five basic categories are recognized.
Reporting renal cysts in USG report: Major
language recommendations
On plain, non-contrast ultrasound, a radiologist should describe the cyst's size, location, wall
thickness, septations, calcifications, and color Doppler vascularity, then categorize the lesion as
either a simple cyst, a complicated cyst, or a complex/indeterminate mass.
If the cyst fulfills all benign criteria, it should be labeled a simple cyst requiring no further action.
If it exhibits mild deviations like a single thin septum, it can be reported as a likely benign
complicated cyst suitable for routine follow-up.
However, because a formal Bosniak classification cannot be assigned without contrast media to
evaluate tissue perfusion, any lesion with high-risk features such as thick walls, multiple
septations, nodular calcifications, or solid components must be reported as an indeterminate
complex renal mass with an explicit recommendation for a contrast-enhanced CT or MRI to
definitively establish the Bosniak score
While the official Bosniak Version 2019 update formally incorporates only CT and MRI, major
international organizations—such as the European Federation of Societies for Ultrasound in
Medicine and Biology (EFSUMB)—have established a validated CEUS-Bosniak classification system
Simple Cysts – Bosniak I Lesion
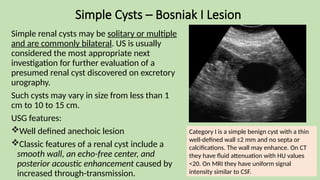
Simple renal cysts may be solitary or multiple
and are commonly bilateral. US is usually
considered the most appropriate next
investigation for further evaluation of a
presumed renal cyst discovered on excretory
urography.
Such cysts may vary in size from less than 1
cm to 10 to 15 cm.
USG features:
Well defined anechoic lesion
Classic features of a renal cyst include a
smooth wall, an echo-free center, and
posterior acoustic enhancement caused by
increased through-transmission.
Category I is a simple benign cyst with a thin
well-defined wall ≤2 mm and no septa or
calcifications. The wall may enhance. On CT
they have fluid attenuation with HU values
<20. On MRI they have uniform signal
intensity similar to CSF.
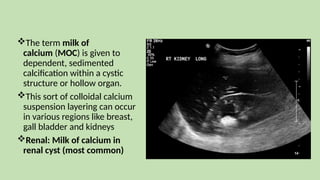
The term milk of
calcium (MOC) is given to
dependent, sedimented
calcification within a cystic
structure or hollow organ.
This sort of colloidal calcium
suspension layering can occur
in various regions like breast,
gall bladder and kidneys
Renal: Milk of calcium in
renal cyst (most common)
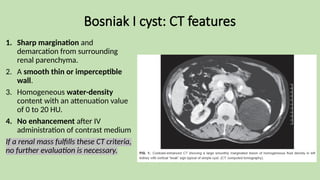
Bosniak I cyst: CT features
1. Sharp margination and
demarcation from surrounding
renal parenchyma.
2. A smooth thin or imperceptible
wall.
3. Homogeneous water-density
content with an attenuation value
of 0 to 20 HU.
4. No enhancement after IV
administration of contrast medium
If a renal mass fulfills these CT criteria,
no further evaluation is necessary.
Simple Cysts – Bosniak I Lesion
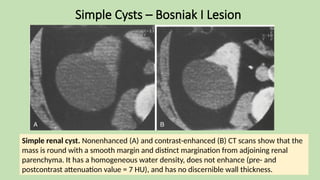
Simple renal cyst. Nonenhanced (A) and contrast-enhanced (B) CT scans show that the
mass is round with a smooth margin and distinct margination from adjoining renal
parenchyma. It has a homogeneous water density, does not enhance (pre- and
postcontrast attenuation value = 7 HU), and has no discernible wall thickness.
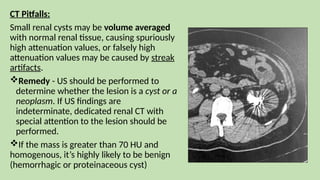
CT Pitfalls:
Small renal cysts may be volume averaged
with normal renal tissue, causing spuriously
high attenuation values, or falsely high
attenuation values may be caused by streak
artifacts.
Remedy - US should be performed to
determine whether the lesion is a cyst or a
neoplasm. If US findings are
indeterminate, dedicated renal CT with
special attention to the lesion should be
performed.
If the mass is greater than 70 HU and
homogenous, it’s highly likely to be benign
(hemorrhagic or proteinaceous cyst)
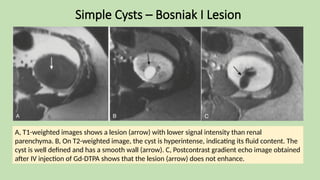
MRI Features:
Even a small simple renal cyst can be diagnosed on contrast-enhanced MRI if it
fulfills the following criteria –
1. Sharp margination and demarcation from surrounding renal parenchyma.
2. A smooth thin wall.
3. Homogeneous contents with signal characteristics of water (such lesions have
low signal intensity on T1-weighted spin echo images and high signal intensity
on T2-weighted spin echo images).
4. No enhancement after IV injection of Gd-DTPA
The use of Gd-enhanced MRI, particularly with gradient echo imaging techniques
applied during breath hold, is helpful in evaluating renal cystic lesions in patients
with contraindications to iodinated IV contrast medium (e.g., chronic renal
failure, previous reactions to contrast media)
Simple Cysts – Bosniak I Lesion
A, T1-weighted images shows a lesion (arrow) with lower signal intensity than renal
parenchyma. B, On T2-weighted image, the cyst is hyperintense, indicating its fluid content. The
cyst is well defined and has a smooth wall (arrow). C, Postcontrast gradient echo image obtained
after IV injection of Gd-DTPA shows that the lesion (arrow) does not enhance.
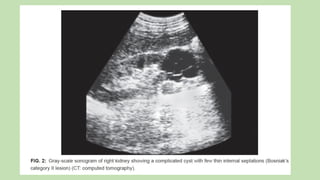
Bosniak II Lesion
Category II lesions are minimally complicated cysts that also usually do not require surgery.
This category includes:
1. Cysts with 1–3 thin septa, that is, septa ≤2 mm in thickness on CT or MRI. The septa or wall
may enhance and have calcification of any type
2. Homogeneous nonenhancing cysts with >20 HU attenuation at renal mass protocol CT; may
have calcification of any type
3. Homogeneous lesions of attenuation 21–30 HU at portal venous phase CT or homogeneous
lesions of attenuation −9 to 20 HU or ≥70 HU on noncontrast CT
4. Homogeneous low-attenuation lesions that are too small to characterize
5. Homogeneously markedly T2 hyperintense (similar to cerebrospinal fluid) cysts or markedly
T1 hyperintense (approximately 2.5 times normal renal parenchymal signal intensity) cysts on
noncontrast MRI
6. Cystic lesions with any number of thin (≤2 mm) nonenhancing septa on MRI
These cysts are benign and do not require treatment or radiological follow-up.
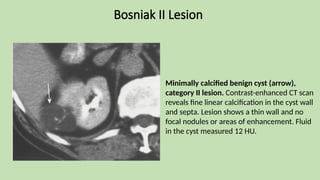
Bosniak II Lesion
Minimally calcified benign cyst (arrow),
category II lesion. Contrast-enhanced CT scan
reveals fine linear calcification in the cyst wall
and septa. Lesion shows a thin wall and no
focal nodules or areas of enhancement. Fluid
in the cyst measured 12 HU.
High Density Cysts
These lesions have attenuation values ranging from 40 to 100 HU on nonenhanced
CT scans and are usually caused by high protein content or previous hemorrhage
Most are benign and can simply be monitored with serial imaging, provided the
following CT criteria are fulfilled –
1. The lesion must be perfectly smooth, round, sharply marginated, and
homogeneous.
2. The lesion should not enhance with IV contrast medium.
3. At least one fourth of the lesion’s circumference should extend outside the
kidney so that the smoothness of some of the wall can be evaluated.
4. The lesion should be less than 3 cm in diameter.
Although most lesions meeting these criteria are benign hemorrhagic cysts,
cystic RCC may rarely show similar characteristics on CT. High- attenuation
renal cysts and RCCs may have a similar appearance on nonenhanced CT
images.
Jonisch and colleagues demonstrated that a homogeneous renal mass with
an attenuation of 70 HU or higher on nonenhanced CT has a greater than
99.9% chance of representing a high-attenuation renal cyst rather than an
RCC.
Hemorrhagic cysts appear on MRI as sharply marginated, smooth, round,
homogeneous lesions. They have high signal intensity on both T1- and T2-
weighted sequences, and they do not enhance after IV administration of Gd-
DTPA.
In addition, hemorrhagic cysts often show fluid-iron levels on MRI, probably
because of dependent settling of methemoglobin-containing sediment.
Bosniak II Lesion
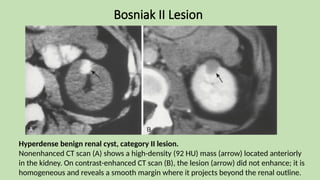
Hyperdense benign renal cyst, category II lesion.
Nonenhanced CT scan (A) shows a high-density (92 HU) mass (arrow) located anteriorly
in the kidney. On contrast-enhanced CT scan (B), the lesion (arrow) did not enhance; it is
homogeneous and reveals a smooth margin where it projects beyond the renal outline.
Bosniak II Lesion
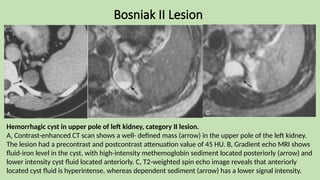
Hemorrhagic cyst in upper pole of left kidney, category II lesion.
A, Contrast-enhanced CT scan shows a well- defined mass (arrow) in the upper pole of the left kidney.
The lesion had a precontrast and postcontrast attenuation value of 45 HU. B, Gradient echo MRI shows
fluid-iron level in the cyst, with high-intensity methemoglobin sediment located posteriorly (arrow) and
lower intensity cyst fluid located anteriorly. C, T2-weighted spin echo image reveals that anteriorly
located cyst fluid is hyperintense, whereas dependent sediment (arrow) has a lower signal intensity.
Bosniak IIF cysts
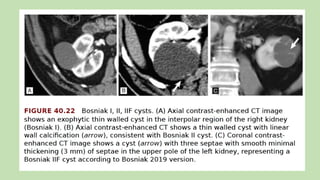
This category (“F” for follow-up) was introduced as a modification of the original
Bosniak classification. It includes lesions that lie intermediately between
categories II and III. They are slightly more complex than category II but do not
fulfill the criteria for category III.
The following cysts are included:
1. Cystic lesions with a smooth minimally thickened (3 mm) enhancing wall, or
smooth minimal thickening (3 mm) of one or more enhancing septa, or many
(≥4) smooth thin enhancing septa.
2. Cystic masses that are heterogeneously hyperintense at unenhanced fat-
saturated T1-weighted imaging are also included.
 Neither the septa nor the wall of these lesions show measurable enhancement.
 These lesions are considered indeterminate and may advance to category III
with time and therefore need follow-up at 6 months.
Bosniak IIF Lesion
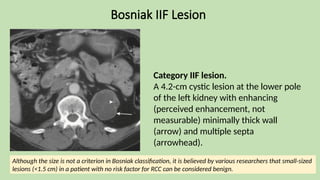
Category IIF lesion.
A 4.2-cm cystic lesion at the lower pole
of the left kidney with enhancing
(perceived enhancement, not
measurable) minimally thick wall
(arrow) and multiple septa
(arrowhead).
Although the size is not a criterion in Bosniak classification, it is believed by various researchers that small-sized
lesions (<1.5 cm) in a patient with no risk factor for RCC can be considered benign.
Bosniak IIF Lesion
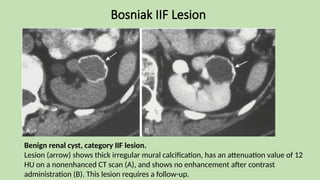
Benign renal cyst, category IIF lesion.
Lesion (arrow) shows thick irregular mural calcification, has an attenuation value of 12
HU on a nonenhanced CT scan (A), and shows no enhancement after contrast
administration (B). This lesion requires a follow-up.
On follow up of IIF cysts
Progression in these cysts is generally a strong indicator of malignancy.
The development of enhancing soft-tissue component(s) should upgrade
the cystic mass and result in surgical treatment.
Malignancy rates for category IIF cysts of up to 5% have been reported
There are no definitive studies determining duration or frequency of
follow-up for Bosniak IIF cysts.
ACR white paper recommends first semiannual and then annual follow-up
for a minimum of 5 years to allow for morphologic change to be identified
Bosniak III Lesion
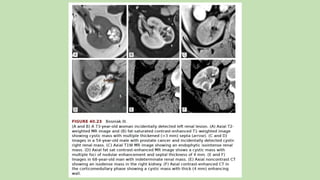
Lesions in category III are indeterminate complicated cystic lesions.
The presence of nodular and thick calcifications in walls or septa, which was considered a
criterion for inclusion in category III according to the original Bosniak classification, is no
longer a criterion.
The modified version of the Bosniak system stresses the presence of abnormal
enhancement of the walls or septa for inclusion in category III. The wall or septa of these
lesions are thick or irregular and most show measurable enhancement.
Category III includes:
Cystic masses that are more complicated and contain enhancing thick irregular walls
and/or septa are included here.
Cystic masses with one or more enhancing thick (≥4 mm width) walls or septa, or
enhancing irregular (displaying ≤3 mm obtusely marginated convex protrusion/s) on the
walls or septa.
Approximately 50% of the Bosniak III masses are malignant (ranging from 25% to 100%)
Definitive treatment of lesions in this category is surgery
Bosniak III Lesion
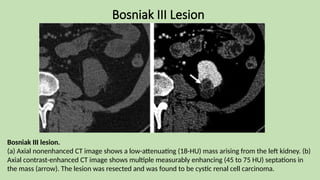
Bosniak III lesion.
(a) Axial nonenhanced CT image shows a low-attenuating (18-HU) mass arising from the left kidney. (b)
Axial contrast-enhanced CT image shows multiple measurably enhancing (45 to 75 HU) septations in
the mass (arrow). The lesion was resected and was found to be cystic renal cell carcinoma.
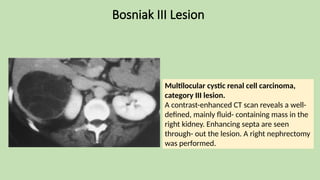
Bosniak III Lesion
Multilocular cystic renal cell carcinoma,
category III lesion.
A contrast-enhanced CT scan reveals a well-
defined, mainly fluid- containing mass in the
right kidney. Enhancing septa are seen
through- out the lesion. A right nephrectomy
was performed.
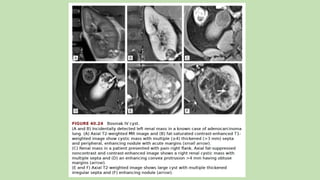
Bosniak IV Lesion
A Bosniak IV cyst contains enhancing nodular soft- tissue components in their septa or
their wall and is considered malignant until proven otherwise.
A small percentage of these lesions have a benign pathology (eg. MEST). Bosniak IV
cystic masses have an enhancing nodule.
The “nodule” is defined as a focal enhancing convex protrusion in the wall or septa that
has acute margins (of any size) or a focal enhancing convex protrusion ≥4 mm that has
obtuse margins with the wall or septa.
An enhancing convex protrusion with obtuse margins that is less than or equal to 3 mm
is not considered as a nodule, and is a feature of a Bosniak III mass.
Malignancy rates in this category are approximately 80% (range 67–100%).
Definitive treatment of these lesions is surgery. Imaging surveillance is considered an
acceptable alternative management approach in patients with a short life expectancy or
comorbidities, especially because these lesions tend to be less aggressive than ccRCCs
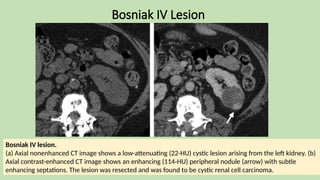
Bosniak IV Lesion
Bosniak IV lesion.
(a) Axial nonenhanced CT image shows a low-attenuating (22-HU) cystic lesion arising from the left kidney. (b)
Axial contrast-enhanced CT image shows an enhancing (114-HU) peripheral nodule (arrow) with subtle
enhancing septations. The lesion was resected and was found to be cystic renal cell carcinoma.
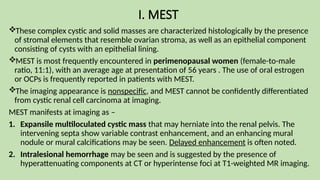
I. MEST
These complex cystic and solid masses are characterized histologically by the presence
of stromal elements that resemble ovarian stroma, as well as an epithelial component
consisting of cysts with an epithelial lining.
MEST is most frequently encountered in perimenopausal women (female-to-male
ratio, 11:1), with an average age at presentation of 56 years . The use of oral estrogen
or OCPs is frequently reported in patients with MEST.
The imaging appearance is nonspecific, and MEST cannot be confidently differentiated
from cystic renal cell carcinoma at imaging.
MEST manifests at imaging as –
1. Expansile multiloculated cystic mass that may herniate into the renal pelvis. The
intervening septa show variable contrast enhancement, and an enhancing mural
nodule or mural calcifications may be seen. Delayed enhancement is often noted.
2. Intralesional hemorrhage may be seen and is suggested by the presence of
hyperattenuating components at CT or hyperintense foci at T1-weighted MR imaging.
MEST
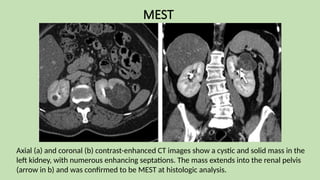
Axial (a) and coronal (b) contrast-enhanced CT images show a cystic and solid mass in the
left kidney, with numerous enhancing septations. The mass extends into the renal pelvis
(arrow in b) and was confirmed to be MEST at histologic analysis.
II. Cystic Nephroma
 Cystic nephroma is a rare benign tumor that typically occurs in boys younger than 4 years or
women aged 40–60 years.
 Children often present with a painless abdominal mass, while adults are more likely to
present with abdominal pain or hematuria but may be asymptomatic.
 On cross-sectional images, cystic nephroma typically appears as
1. A well-circumscribed, encapsulated, multicystic mass with variably enhancing septa.
When compared with simple fluid, the contents of the mass may have similar or slightly
higher attenuation at CT and higher signal intensity at T1-weighted MR imaging.
2. The lesions often herniate into the renal pelvis or proximal ureter.
3. Because of their fibrous composition, the septa and capsule of the lesion are hypointense
on both T1- and T2-weighted MR images.
Nonetheless, cystic nephroma may mimic a variety of benign and malignant renal lesions,
including complex renal cysts and cystic renal cell carcinoma, along with MEST and localized
cystic disease. Because it is challenging to distinguish cystic nephroma from cystic renal cell
carcinoma, many cases are treated surgically.
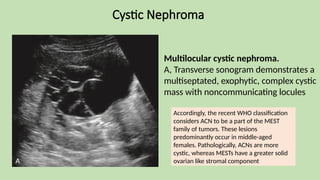
Cystic Nephroma
Multilocular cystic nephroma.
A, Transverse sonogram demonstrates a
multiseptated, exophytic, complex cystic
mass with noncommunicating locules
Accordingly, the recent WHO classification
considers ACN to be a part of the MEST
family of tumors. These lesions
predominantly occur in middle-aged
females. Pathologically, ACNs are more
cystic, whereas MESTs have a greater solid
ovarian like stromal component
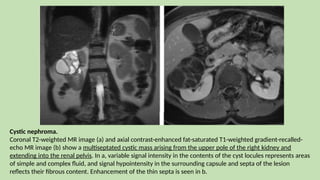
Cystic nephroma.
Coronal T2-weighted MR image (a) and axial contrast-enhanced fat-saturated T1-weighted gradient-recalled-
echo MR image (b) show a multiseptated cystic mass arising from the upper pole of the right kidney and
extending into the renal pelvis. In a, variable signal intensity in the contents of the cyst locules represents areas
of simple and complex fluid, and signal hypointensity in the surrounding capsule and septa of the lesion
reflects their fibrous content. Enhancement of the thin septa is seen in b.
III. AML with epithelial cysts (AMLEC)
This cystic variant of AML is rare and usually seen in women. There are
no specific ultrasonography features. They may present as a Bosniak
category 4 mass, mimicking a cystic RCC. The solid part is usually
hyperattenuating on
CT, homogeneously enhancing, and hypointense on T2WI, which are
diagnostic clues.
A signal drop on CS-MRI may sometimes occur in this type of AML.
Malignant Bosniak IIF, III, IV lesions
I. RCC with cystic changes
RCC can undergo cystic changes, more commonly seen with ccRCC. These
constitute less than 5% of all RCCs. It demonstrates a male predominance
(male-to-female ratio of 2:1), mostly occurring in the sixth to seventh
decades.
ccRCC with cystic changes is a multiloculated cystic mass with an
irregularly thickened wall and areas of enhancing solid nodularity. It is
important to differentiate this from RCC with necrosis which typically has a
poorer prognosis
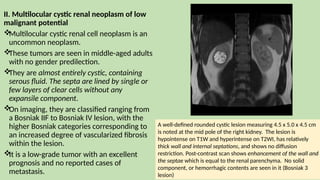
II. Multilocular cystic renal neoplasm of low
malignant potential

Multilocular cystic renal cell neoplasm is an
uncommon neoplasm.

These tumors are seen in middle-aged adults
with no gender predilection.

They are almost entirely cystic, containing
serous fluid. The septa are lined by single or
few layers of clear cells without any
expansile component.

On imaging, they are classified ranging from
a Bosniak IIF to Bosniak IV lesion, with the
higher Bosniak categories corresponding to
an increased degree of vascularized fibrosis
within the lesion.

It is a low-grade tumor with an excellent
prognosis and no reported cases of
metastasis.
A well-defined rounded cystic lesion measuring 4.5 x 5.0 x 4.5 cm
is noted at the mid pole of the right kidney. The lesion is
hypointense on T1W and hyperintense on T2WI, has relatively
thick wall and internal septations, and shows no diffusion
restriction. Post-contrast scan shows enhancement of the wall and
the septae which is equal to the renal parenchyma. No solid
component, or hemorrhagic contents are seen in it (Bosniak 3
lesion)
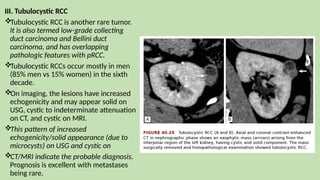
III. Tubulocystic RCC
Tubulocystic RCC is another rare tumor.
It is also termed low-grade collecting
duct carcinoma and Bellini duct
carcinoma, and has overlapping
pathologic features with pRCC.
Tubulocystic RCCs occur mostly in men
(85% men vs 15% women) in the sixth
decade.
On imaging, the lesions have increased
echogenicity and may appear solid on
USG, cystic to indeterminate attenuation
on CT, and cystic on MRI.
This pattern of increased
echogenicity/solid appearance (due to
microcysts) on USG and cystic on
CT/MRI indicate the probable diagnosis.
Prognosis is excellent with metastases
being rare.
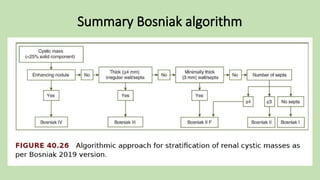
Summary Bosniak algorithm
Renal sinus cysts (Peripelvic Cysts)
Originate within the sinus itself and have a
lymphatic origin
Are asymptomatic cysts that arise from the
lymphatics of the renal hilum. They usually are
multiple, small, and bilateral. Their appearance
is often difficult to distinguish from
hydronephrosis.
However, the distinction is readily apparent on
contrast-enhanced excretory phase CT images,
where the high-attenuation contrast agent–filled
collecting system can easily be distinguished
from fluid-attenuation renal sinus cysts.
Benign extra parenchymal cysts located in renal
sinus. Uni/multilocular and usually bilateral.
These cysts are surrounded by renal sinus fat.
Cysts of Renal Pelvis.
Coronal excretory phase maximum intensity
projection CT image of the abdomen shows the
contrast material– filled collecting system surrounded
by multiple cysts in the renal pelvis.
Cysts of Renal Pelvis
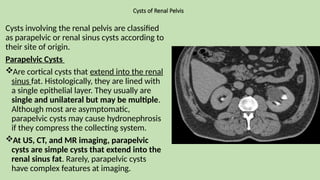
Cysts involving the renal pelvis are classified
as parapelvic or renal sinus cysts according to
their site of origin.
Parapelvic Cysts
Are cortical cysts that extend into the renal
sinus fat. Histologically, they are lined with
a single epithelial layer. They usually are
single and unilateral but may be multiple.
Although most are asymptomatic,
parapelvic cysts may cause hydronephrosis
if they compress the collecting system.
At US, CT, and MR imaging, parapelvic
cysts are simple cysts that extend into the
renal sinus fat. Rarely, parapelvic cysts
have complex features at imaging.
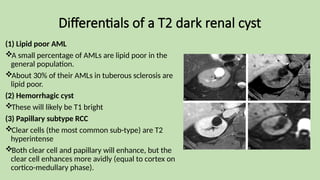
Differentials of a T2 dark renal cyst
(1) Lipid poor AML
A small percentage of AMLs are lipid poor in the
general population.
About 30% of their AMLs in tuberous sclerosis are
lipid poor.
(2) Hemorrhagic cyst
These will likely be T1 bright
(3) Papillary subtype RCC
Clear cells (the most common sub-type) are T2
hyperintense
Both clear cell and papillary will enhance, but the
clear cell enhances more avidly (equal to cortex on
cortico-medullary phase).
Focal Cystic Renal Disease
1. Mixed Epithelial and Stromal Tumor (MEST).
2. Cystic Nephroma.
3. Pyelocalyceal Diverticulum.
Pyelocalyceal Diverticulum
Pyelocalyceal diverticulum is a urine-filled cavity within the renal cortex that
communicates with the renal collecting system.
There are two types of pyelocalyceal diverticulum –
1. Type 1, the more common type, communicates with a minor calyx.
2. Type 2 connects with a major calyx or the renal pelvis.
Pyelocalyceal diverticulum is relatively rare and is identified at 2.1–4.5 per
1000 intravenous urographic evaluations.
The etiology of pyelocalyceal diverticulum is controversial; however, most
cases are thought to be congenital. The most common theory is that
pyelocalyceal diverticulum results from failure of regression of the third- and
fourth-generation ureteric buds. A smaller percentage of cases of pyelocalyceal
diverticulum may be acquired, resulting from obstructing stones or infection.
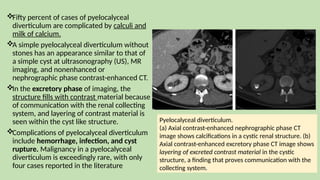
Fifty percent of cases of pyelocalyceal
diverticulum are complicated by calculi and
milk of calcium.
A simple pyelocalyceal diverticulum without
stones has an appearance similar to that of
a simple cyst at ultrasonography (US), MR
imaging, and nonenhanced or
nephrographic phase contrast-enhanced CT.
In the excretory phase of imaging, the
structure fills with contrast material because
of communication with the renal collecting
system, and layering of contrast material is
seen within the cyst like structure.
Complications of pyelocalyceal diverticulum
include hemorrhage, infection, and cyst
rupture. Malignancy in a pyelocalyceal
diverticulum is exceedingly rare, with only
four cases reported in the literature
Pyelocalyceal diverticulum.
(a) Axial contrast-enhanced nephrographic phase CT
image shows calcifications in a cystic renal structure. (b)
Axial contrast-enhanced excretory phase CT image shows
layering of excreted contrast material in the cystic
structure, a finding that proves communication with the
collecting system.
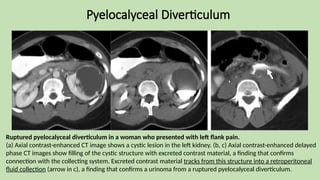
Pyelocalyceal Diverticulum
Ruptured pyelocalyceal diverticulum in a woman who presented with left flank pain.
(a) Axial contrast-enhanced CT image shows a cystic lesion in the left kidney. (b, c) Axial contrast-enhanced delayed
phase CT images show filling of the cystic structure with excreted contrast material, a finding that confirms
connection with the collecting system. Excreted contrast material tracks from this structure into a retroperitoneal
fluid collection (arrow in c), a finding that confirms a urinoma from a ruptured pyelocalyceal diverticulum.
Acquired Multifocal Cystic Renal Disease
1. Glomerulocystic kidney disease.
2. Lithium induced nephrotoxicity.
3. Acquired cystic kidney disease.
Glomerulocystic kidney disease
Glomerulocystic kidney disease (GCKD) is a rare form of cystic renal disease
characterized histologically by uniform cystic dilatation of the Bowman capsule.
These cysts are located predominantly in the subcapsular area of the renal
cortex and spare the tubular portions of the nephron.
The cortical and subcapsular distribution helps distinguish GCKD from other
cystic renal diseases, such as ARPKD, ADPKD, MCDK, and cystic renal dysplasia.
Most often, GCKD occurs in neonates and young children. In many instances,
mild renal failure with accompanying infantile congenital malformations is seen.
Although an autosomal dominant inheritance pattern has been demonstrated
in families with GCKD, several sporadic cases have also been reported.
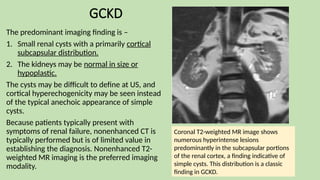
GCKD
The predominant imaging finding is –
1. Small renal cysts with a primarily cortical
subcapsular distribution.
2. The kidneys may be normal in size or
hypoplastic.
The cysts may be difficult to define at US, and
cortical hyperechogenicity may be seen instead
of the typical anechoic appearance of simple
cysts.
Because patients typically present with
symptoms of renal failure, nonenhanced CT is
typically performed but is of limited value in
establishing the diagnosis. Nonenhanced T2-
weighted MR imaging is the preferred imaging
modality.
Coronal T2-weighted MR image shows
numerous hyperintense lesions
predominantly in the subcapsular portions
of the renal cortex, a finding indicative of
simple cysts. This distribution is a classic
finding in GCKD.
Lithium induced nephrotoxicity
Nephrotoxicity due to long-term lithium therapy is a well-described entity and is divided into three main
categories –
1. Acute intoxication.
2. Nephrogenic diabetes insipidus – m/c and reversible with cessation of drug.
3. Chronic renal disease.
CT and MR imaging findings of lithium induced nephrotoxicity typically include-
4. Normal- sized kidneys with abundant and uniformly distributed renal microcysts.
5. Microcysts have been reported in 33%–62% of patients. These cysts are found in the cortex and
medulla and typically are 1–2 mm in diameter.
 At CT, the cysts appear as multiple tiny hypoattenuating lesions. MR imaging best depicts the number
and size of cystic lesions.
 Cysts are best appreciated on T2-weighted MR images, which will depict multiple hyperintense foci.
 The D/Ds includes ADPKD, GCKD, medullary cystic kidney disease, and acquired cystic kidney disease.
These entities can usually be differentiated from lithium-induced nephrotoxicity on the basis of clinical
history as well as the size and distribution of cysts at imaging.
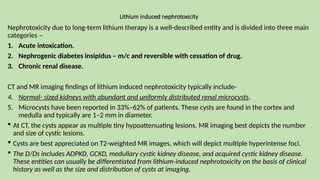
Axial contrast-enhanced CT image shows
multiple hypoattenuating lesions scattered
throughout the cortex and medulla of both
kidneys.
The findings are consistent with microcysts.
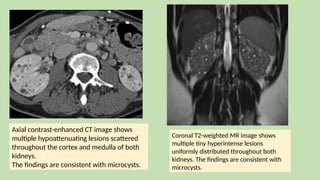
Coronal T2-weighted MR image shows
multiple tiny hyperintense lesions
uniformly distributed throughout both
kidneys. The findings are consistent with
microcysts.
Acquired cystic kidney disease
Acquired cystic kidney disease refers to the development
of renal cysts in patients with end- stage renal disease
who do not already have a heritable cystic renal disease.
Risk factors include male sex and increased duration of
time on dialysis.
The male-to-female ratio is 3:1.
Acquired cystic kidney disease is thought to be
multifactorial in cause. The initiating factor is thought to
be compensatory hypertrophy of functional nephrons in
response to adjacent tissue destruction.
Renal tubular obstruction and expansion caused by
interstitial fibrosis, epithelial hyperplasia, and increased
fluid secretion are thought to lead to cyst development.
There is no correlation with race, cause of renal failure,
or method of dialysis (ie, hemodialysis or peritoneal
dialysis).
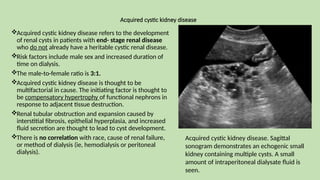
Acquired cystic kidney disease. Sagittal
sonogram demonstrates an echogenic small
kidney containing multiple cysts. A small
amount of intraperitoneal dialysate fluid is
seen.
It is postulated that with progressive destruction of
functioning renal tissue, cystogenic substances
accumulate and cause hypertrophy and hyperplasia of
epithelial cells.
The tubular epithelium proliferate and cystic dilatation
of tubules occurs.
Subsequently, there is a continuum of changes from
single-layered epithelial cysts to multilayered cysts to
RCCs.
Approximately 8%–13% of patients with end-stage
renal disease have acquired cystic kidney disease
before they undergo dialysis. After 10 years of dialysis,
the incidence is believed to approach 100%.
Complications include cyst hemorrhage, ureteral
stones, and the development of renal cell carcinoma.
Renal malignancy will develop in 3%–7% of patients
with acquired cystic kidney disease. Risk factors include
male sex and an increased length of time on dialysis.
The imaging features are small echogenic kidneys with
multiple cysts in kidneys (in USG) and similar in
CT/MRI.
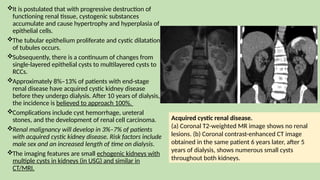
Acquired cystic renal disease.
(a) Coronal T2-weighted MR image shows no renal
lesions. (b) Coronal contrast-enhanced CT image
obtained in the same patient 6 years later, after 5
years of dialysis, shows numerous small cysts
throughout both kidneys.
Multicystic dysplastic kidney
MCDK is a nonheritable developmental disorder in which the kidney is replaced by non-functioning
noncommunicating cysts. It occurs in approximately one of 4300 live births.
Most common form of cystic disease in infants.
The imaging appearance of MCDK varies by age. Often it is diagnosed in utero.
1. In children, it is most commonly assessed with US and appears as a large cluster of
noncommunicating cysts that replaces the renal parenchyma.
2. In some cases, the cysts may replace only a portion of the renal parenchyma.
In children diagnosed with MCDK, it is important to assess the contralateral renal collecting system
because there is vesicoureteral reflux in 5%–43% of cases. Also associated with renal artery hypoplasia.
Two types of MDK may be shown by imaging, pelvoinfundibular atresia and the hydronephrotic type.In the classic type,
pelvoinfundibular atresia, no discernible renal pelvis is demonstrated on imaging. The kidney may be small, normal in
size, or enlarged and contains multiple variably-sized noncommunicating renal cysts . No perfusion of the affected kidney
occurs on renal scintigraphy, and contrast-enhanced CT shows no evidence of contrast excretion by the affected kidney.
The hydronephrotic form of MDK is characterized by dilatation of the renal pelvis and calyces. Differentiation of this type
of MDK from simple hydronephrosis is based on the imaging demonstration of parenchymal cysts that do not
communicate with the collecting system.
The proposed theory of this dysplastic kidney is failure of the ureteric bud
to induce development of metanephric blastema.
The ureteric bud may be absent or may not integrate with metanephric
blastema owing to urinary tract obstruction.
It may also be picked up on antenatal USG
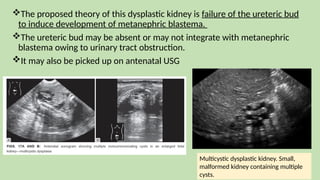
Multicystic dysplastic kidney. Small,
malformed kidney containing multiple
cysts.
In most cases, the dysplastic kidney will completely
regress by adulthood. However, in few of cases, a
small residual mass may be seen in the renal fossa.
Typical imaging features are –
1. A central region of soft tissue; peripheral
noncommunicating cysts.
2. Absence or severe atrophy of the ipsilateral
ureter, renal collecting system, and renal
vasculature.
Occasionally, the cysts may be calcified and
identifiable at radiography. There may be
compensatory hypertrophy of the contralateral
kidney.
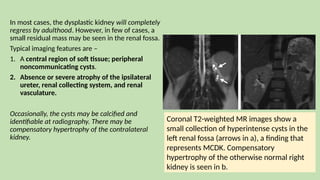
Coronal T2-weighted MR images show a
small collection of hyperintense cysts in the
left renal fossa (arrows in a), a finding that
represents MCDK. Compensatory
hypertrophy of the otherwise normal right
kidney is seen in b.
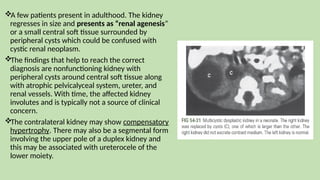
A few patients present in adulthood. The kidney
regresses in size and presents as “renal agenesis”
or a small central soft tissue surrounded by
peripheral cysts which could be confused with
cystic renal neoplasm.
The findings that help to reach the correct
diagnosis are nonfunctioning kidney with
peripheral cysts around central soft tissue along
with atrophic pelvicalyceal system, ureter, and
renal vessels. With time, the affected kidney
involutes and is typically not a source of clinical
concern.
The contralateral kidney may show compensatory
hypertrophy. There may also be a segmental form
involving the upper pole of a duplex kidney and
this may be associated with ureterocele of the
lower moiety.
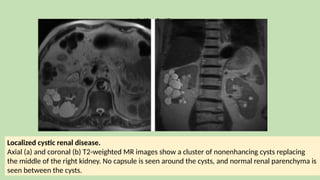
Localized cystic renal disease
Localized cystic renal disease is a rare condition in which a cluster of tightly spaced, variably
sized cysts replaces a portion of or the entire renal parenchyma of one kidney. Normal renal
parenchyma is seen between the cysts. The remaining renal parenchyma in the affected kidney
as well as in the contralateral kidney may contain a few scattered cysts.
Also known as segmental renal cystic disease and unilateral renal cystic disease.
It is a benign, nonprogressive condition. Multiple cysts are seen in one kidney with no cysts in
the contralateral kidney or any other organ. Most patients are asymptomatic.
Some may present with abdominal pain, hematuria, or hypertension but with intact renal
function. At imaging, localized cystic renal disease manifests as –
1. A conglomeration of cysts in one kidney.
2. The presence of intervening normally enhancing renal parenchyma and the absence of a
capsule around the cysts help distinguish from cystic nephroma and multiloculated cystic RCC.
However, the intervening renal parenchyma may be stretched and attenuated, which makes
differentiation of thick septations from intervening parenchyma difficult. Remaining renal
parenchyma and contralateral kidney are generally normal but can show a few scattered cysts.
Localized Cystic Renal Disease
Localized cystic renal disease.
Axial (a) and coronal (b) T2-weighted MR images show a cluster of nonenhancing cysts replacing
the middle of the right kidney. No capsule is seen around the cysts, and normal renal parenchyma is
seen between the cysts.
Renal Infections appearing as cystic lesions
1. Renal Abscess
2. Renal Aspergillosis
3. Renal Echinococcosis
Renal abscess
Renal abscesses are typically seen as a complication of acute pyelonephritis.
They often occur as the result of untreated or incompletely treated pyelonephritis or ascending
urinary tract infections and hematogenous seeding in patients with bacteremia.
Immunocompromised, pregnant, and diabetic patients have an increased risk for abscess
formation.
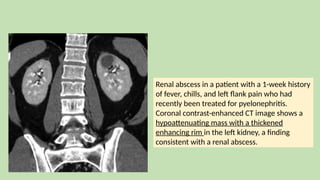
At radiology, a renal abscess may mimic a renal cyst; however, differentiation can typically be
made on the basis of the patient’s clinical scenario.
1. US most commonly demonstrates an anechoic to hypoechoic complex cystic mass with posterior
acoustic enhancement. Internal echoes, septations, and loculations may also be seen at US.
2. CT and MR imaging are more sensitive modalities for detecting a renal abscess. Contrast-
enhanced CT demonstrates a well-defined, hypoattenuating, round mass, often with a thick rim
or halo. Perinephric extension of the abscess may be seen.
3. MR imaging can also be used to evaluate renal abscesses, particularly in cases where it is
important to limit ionizing radiation exposure. MR imaging typically shows a heterogeneous
thick-rimmed lesion that is hypointense on T1-weighted images and hyperintense on T2-weighted
images, with restricted diffusion. The presence of gas will result in blooming artifact on gradient-
recalled-echo MR images.
Renal abscess in a patient with a 1-week history
of fever, chills, and left flank pain who had
recently been treated for pyelonephritis.
Coronal contrast-enhanced CT image shows a
hypoattenuating mass with a thickened
enhancing rim in the left kidney, a finding
consistent with a renal abscess.
Renal aspergillosis
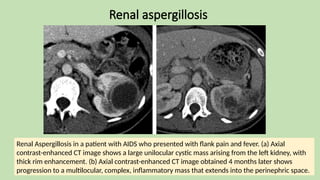
Renal aspergillosis is an uncommon renal infection that manifests as a complex cystic renal
mass. Renal aspergillosis occurs in immunocompromised patients, including patients with
diabetes or human immunodeficiency virus infection and those undergoing corticosteroid
therapy.
Renal aspergillosis is acquired in one of three ways –
1. Hematogenous dissemination – m/c.
2. Ascending infection.
3. Aspergillus casts in the renal pelvis.
The radiologic appearance of renal aspergillosis mimics that of a complex renal cyst or
abscess.
4. CT demonstrates a hypoattenuating mass with a thick enhancing wall and internal
septations. The surrounding renal parenchyma may demonstrate features of focal
pyelonephritis and delayed enhancement.
The diagnosis of renal aspergillosis is typically made after urinalysis or aspiration of the
lesion.
Renal aspergillosis
Renal Aspergillosis in a patient with AIDS who presented with flank pain and fever. (a) Axial
contrast-enhanced CT image shows a large unilocular cystic mass arising from the left kidney, with
thick rim enhancement. (b) Axial contrast-enhanced CT image obtained 4 months later shows
progression to a multilocular, complex, inflammatory mass that extends into the perinephric space.
Renal Echinococcosis
Echinococcosis is a zoonosis caused by the larvae of the Echinococcus tapeworm. Humans
can be an intermediate host when infected through contact with the definitive host or
through contaminated water or food. Liver serves as the first line of defense and is the
m/c involved organ (75%). The lungs are the second m/c site of involvement (15%).
However, hematogenous dissemination can occur to almost any anatomic location and
may rarely involve the kidneys.
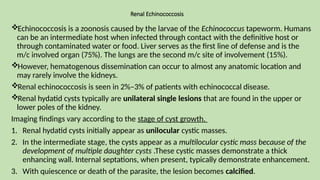
Renal echinococcosis is seen in 2%–3% of patients with echinococcal disease.
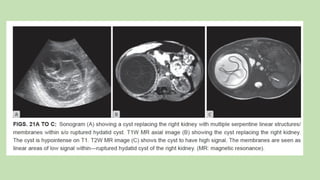
Renal hydatid cysts typically are unilateral single lesions that are found in the upper or
lower poles of the kidney.
Imaging findings vary according to the stage of cyst growth.
1. Renal hydatid cysts initially appear as unilocular cystic masses.
2. In the intermediate stage, the cysts appear as a multilocular cystic mass because of the
development of multiple daughter cysts .These cystic masses demonstrate a thick
enhancing wall. Internal septations, when present, typically demonstrate enhancement.
3. With quiescence or death of the parasite, the lesion becomes calcified.
Renal Echinococcosis
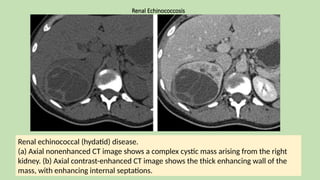
Renal echinococcal (hydatid) disease.
(a) Axial nonenhanced CT image shows a complex cystic mass arising from the right
kidney. (b) Axial contrast-enhanced CT image shows the thick enhancing wall of the
mass, with enhancing internal septations.
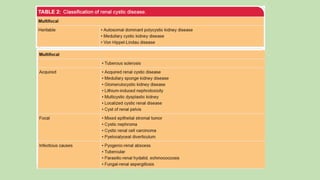
Heritable Multi­
focal Cystic Renal Disease
1. Autosomal Dominant Polycystic Kidney Disease (ADPKD)
2. Von Hippel Lindau Disease (VHL)
3. Tuberous Sclerosis (TS)
ADPKD
ADPKD is a heritable cystic renal disease that causes cysts along the nephron. The disease
occurs in approximately one of 500–1000 live births and is the most common heritable renal
disorder.
There are two types of ADPKD.
Mutation in the PDK1 gene, in the short arm of chromosome 16 – m/c, 85%.
Mutation in the PDK2 gene, in the long arm of chromosome 4. and 3. PKD-3.
The PKD2 mutation results in a milder form of disease than the PKD1 mutation and also has a
later age of onset.
Age of presentation is 44.8 years in PKD-1 and 69.1 years in PKD-2.
Most patients are born with normal kidneys. Only 2% patients present before 15 years of age.
Most affected individuals present in the fourth or fifth decade with flank pain, palpable
masses, hypertension, hematuria, urinary tract infection, proteinuria, or polycythemia.
Progressive azotemia ensues as renal parenchyma is destroyed and renal failure occurs in most
patients by the age of 60 years.
Complications include superimposed infection, cyst hemorrhage, uric acid stones, and
hypertension.
The radiologic appearance of ADPKD includes enlarged
kidneys with multiple cysts in bilateral kidneys.
Extrarenal manifestations may also be seen and most
commonly include hepatic cysts. Cysts are less
commonly seen in the pancreas, spleen, ovaries, and
testes. Patients are at an increased risk for cardiac
valve abnormalities (26%) and intracranial aneurysms
(10%–15%).
Renal complications of ADPKD include cyst
hemorrhage, cyst infection, cyst rupture, and
nephrolithiasis. About 50% of individuals with ADPKD
will develop end-stage renal disease.
Unlike in some other congenital cystic kidney diseases,
there is no increased risk for renal cell carcinoma
unless the patient is undergoing prolonged dialysis.
Genetic testing identifies only 70% of individuals with
ADPKD.
Sunburst or streak nephrogram may be seen in IVU
Imaging plays an important role in
diagnosis, detection of complications, and
follow-up.
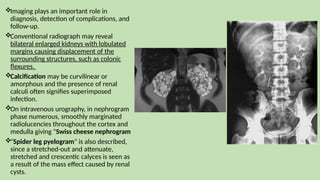
Conventional radiograph may reveal
bilateral enlarged kidneys with lobulated
margins causing displacement of the
surrounding structures, such as colonic
flexures.
Calcification may be curvilinear or
amorphous and the presence of renal
calculi often signifies superimposed
infection.
On intravenous urography, in nephrogram
phase numerous, smoothly marginated
radiolucencies throughout the cortex and
medulla giving "Swiss cheese nephrogram
"Spider leg pyelogram" is also described,
since a stretched-out and attenuate,
stretched and crescentic calyces is seen as
a result of the mass effect caused by renal
cysts.
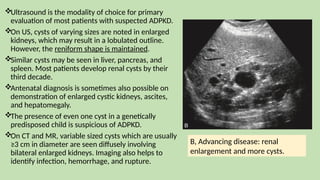
Ultrasound is the modality of choice for primary
evaluation of most patients with suspected ADPKD.
On US, cysts of varying sizes are noted in enlarged
kidneys, which may result in a lobulated outline.
However, the reniform shape is maintained.
Similar cysts may be seen in liver, pancreas, and
spleen. Most patients develop renal cysts by their
third decade.
Antenatal diagnosis is sometimes also possible on
demonstration of enlarged cystic kidneys, ascites,
and hepatomegaly.
The presence of even one cyst in a genetically
predisposed child is suspicious of ADPKD.
On CT and MR, variable sized cysts which are usually
≥3 cm in diameter are seen diffusely involving
bilateral enlarged kidneys. Imaging also helps to
identify infection, hemorrhage, and rupture.
B, Advancing disease: renal
enlargement and more cysts.
On MRI, the renal cysts are hypointense on T1-weighted and hyperintense on T2-
weighted images, with infected and proteinaceous cysts showing intermediate
signal intensities
MRI based renal and cyst volumetry enables assessment of disease progression.
With increasing renal volume, the glomerular filtration rate may decline and the
patient may present with abdominal pain, hypertension, or hematuria. Renal
blood flow may also decrease suggesting progression of the disease.
Imaging is critical in evaluation of patients who have a first-degree relative with
ADPKD.
It is especially so in evaluation of prospective donors who plan to donate a kidney
to their kin with ADPKD.
Severe cases can be diagnosed easily on imaging but a milder form of the disease,
especially with PKD2 mutation, can be difficult to diagnose. Genetic testing helps
in the diagnosis of ADPKD in only 70% cases.
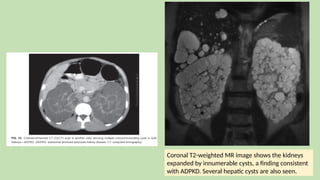
Coronal T2-weighted MR image shows the kidneys
expanded by innumerable cysts, a finding consistent
with ADPKD. Several hepatic cysts are also seen.
ADPKD: Associations
 Cerebral berry aneurysms
 Found in 6% of patients with ADPKD without a family history of aneurysms
 Found in up to 22% of patients with ADPKD with a family history 16
 Intracranial dolichoectasia: 2-3%
 Hypertension: up to 80% of adults
 Ascites: due to rupture liver cyst or portal hypertension
 Colonic diverticulosis
 Small bowel diverticula (perhaps)
 Bicuspid aortic valve
 Mitral valve prolapse: up to 25%
 Aortic dissection
 Multiple biliary hamartomas (Von Meyenberg complexes)
 Cysts in other organs
 Liver: most common, 75% by age 60 years
 Ovaries
 Spleen: ~5 %
 Seminal vesicles: 60% by age 40 years
 Prostate: 11%
 Pancreas: ~10%:
 Pancreatic cysts are more common in Von Hippel-lindau disease (VHL)
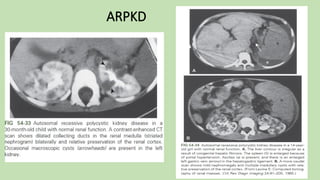
ARPKD
Autosomal recessive polycystic kidney disease is characterized by ectasia of the renal
collecting ducts, interstitial fibrosis, and variable degrees of portal hepatic fibrosis
(congenital hepatic fibrosis), which often causes portal hypertension
10% to 90% of collecting ducts are involved.
Severity of the disease depends on, and is inversely related to, the age at presentation.
Patients with milder renal involvement may present at any age from infancy to early
adulthood.
The severity of renal involvement and extent of liver involvement in these patients are
inversely related.
On noncontrast CT examination, the kidneys are smooth, enlarged, and low in
attenuation, likely a reflection of the large fluid volume in the dilated ducts.
Administration of contrast medium reveals a striated nephrogram, representing
accumulation of contrast in the dilated tubules. Tubular ectasia is confined mainly to the
renal medulla, with only occasional macrocysts. The renal cortex is less severely affected.
CT may also show evidence of congenital hepatic fibrosis and portal hypertension. The liver
contour is often irregular, and dilated intrahepatic bile ducts, ascites, splenomegaly, and
enlarged portosystemic collateral veins may be seen
Associated oligohydramnios may be identified
antenatally (pulmonary hypoplasia with neonatal
mortality)
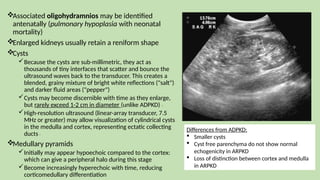
Enlarged kidneys usually retain a reniform shape
Cysts
Because the cysts are sub-millimetric, they act as
thousands of tiny interfaces that scatter and bounce the
ultrasound waves back to the transducer. This creates a
blended, grainy mixture of bright white reflections ("salt")
and darker fluid areas ("pepper")
Cysts may become discernible with time as they enlarge,
but rarely exceed 1-2 cm in diameter (unlike ADPKD) 13
High-resolution ultrasound (linear-array transducer, 7.5
MHz or greater) may allow visualization of cylindrical cysts
in the medulla and cortex, representing ectatic collecting
ducts 8
Medullary pyramids
Initially may appear hypoechoic compared to the cortex:
which can give a peripheral halo during this stage
Become increasingly hyperechoic with time, reducing
corticomedullary differentiation
Differences from ADPKD:
 Smaller cysts
 Cyst free parenchyma do not show normal
echogenicity in ARPKD
 Loss of distinction between cortex and medulla
in ARPKD
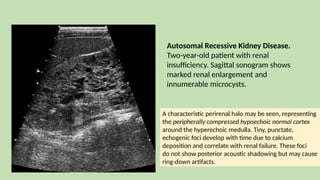
Autosomal Recessive Kidney Disease.
Two-year-old patient with renal
insufficiency. Sagittal sonogram shows
marked renal enlargement and
innumerable microcysts.
A characteristic perirenal halo may be seen, representing
the peripherally compressed hypoechoic normal cortex
around the hyperechoic medulla. Tiny, punctate,
echogenic foci develop with time due to calcium
deposition and correlate with renal failure. These foci
do not show posterior acoustic shadowing but may cause
ring-down artifacts.
ARPKD
ARPKD: Associations
Congenital hepatic fibrosis is present in virtually 100% of the cases
Other associated clinical manifestations are primarily portal
hypertension, splenomegaly, and cholangitis.
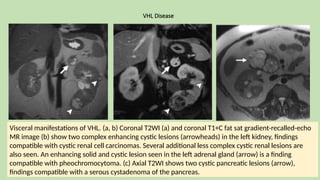
VHL Disease
Is an autosomal dominant disease that is linked to a tumor- suppression
gene on chromosome 3.
The most common visceral manifestations of VHL are renal cysts (59%–63%
of patients), renal cell carcinoma (24%–45%), pheochromocytoma (0%–
60%), pancreatic cysts (50%–91%), and pancreatic neoplasms such as
serous cystadenomas (12%) and neuroendocrine tumors of the pancreas
(5%–17%). Of these, renal cell carcinoma is a significant source of mortality.
Other findings are retinal angiomas, CNS hemangioblastomas
In patients with VHL, cysts that appear simple at imaging often contain
small foci of renal cell carcinoma. As time progresses, these small foci may
grow, forming a solid mass as the original cyst involutes. Therefore, in a
patient with VHL, no cyst can be confidently dismissed at imaging as free of
tumor cells.
VHL Disease
Visceral manifestations of VHL. (a, b) Coronal T2WI (a) and coronal T1+C fat sat gradient-recalled-echo
MR image (b) show two complex enhancing cystic lesions (arrowheads) in the left kidney, findings
compatible with cystic renal cell carcinomas. Several additional less complex cystic renal lesions are
also seen. An enhancing solid and cystic lesion seen in the left adrenal gland (arrow) is a finding
compatible with pheochromocytoma. (c) Axial T2WI shows two cystic pancreatic lesions (arrow),
findings compatible with a serous cystadenoma of the pancreas.
Tuberous Sclerosis (Bourneville disease)
Is an AD neurocutaneous syndrome that causes hamartomas in the kidneys, lungs, liver,
brain, heart, eyes, and skin. It is caused by mutations in the genes TSC1 and TSC2, which
encode for hamartin and tuberin, respectively.
The m/c renal manifestation of tuberous sclerosis is angiomyolipoma, which occurs in
55%–75% of patients followed by simple renal cysts. It is unclear whether patients with
tuberous sclerosis are at increased risk for RCC. However, the average age of patients
with tuberous sclerosis and renal cell carcinoma is 28 years, which is 25 years younger
than the average age of patients with renal cell carcinoma in the general population.
At imaging, differentiation of lipid-poor angiomyolipoma from renal cell carcinoma is
difficult. Rapid growth and the presence of calcification are two imaging findings that
suggest renal cell carcinoma. However, a biopsy may be necessary for differentiation.
As patients with TS age, their risk for end-stage renal disease increases because of the
mass effect of cysts and angiomyolipomas on the renal parenchyma. Angiomyolipomas
also can rupture and cause substantial hemorrhage.
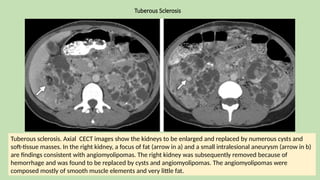
Tuberous Sclerosis
Tuberous sclerosis. Axial CECT images show the kidneys to be enlarged and replaced by numerous cysts and
soft-tissue masses. In the right kidney, a focus of fat (arrow in a) and a small intralesional aneurysm (arrow in b)
are findings consistent with angiomyolipomas. The right kidney was subsequently removed because of
hemorrhage and was found to be replaced by cysts and angiomyolipomas. The angiomyolipomas were
composed mostly of smooth muscle elements and very little fat.
Medullary Cysts
Medullary Sponge Kidney
Medullary sponge kidney (MSK) is defined as dilated, ectatic collecting tubules. It may
be focal or diffuse. The etiology is unknown. Mostly sporadic, a few cases with
autosomal dominant inheritance
The incidence of MSK in the general population is not known, but it is found in up to
12% of patients with renal calculi. Associations with hemi hypertrophy, Ehlers-Danlos
syndrome, congenital HPS, HPT, Caroli’s disease, and ARPKD have been reported.
The onset of symptomatic MSK is usually in the third to fourth decades of life, patients
may present with hematuria, renal colic, or urinary tract infection.
Tubular ectasia may be difficult to impossible to recognize at ultrasound. When
nephrocalcinosis is present, multiple echogenic shadowing foci are seen localized to
the medullary pyramids.
This entity typically involves both the kidneys. Unilateral or segmental involvement
may be seen at times.
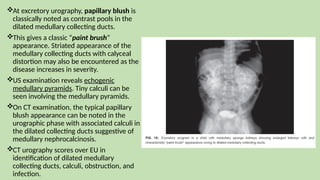
At excretory urography, papillary blush is
classically noted as contrast pools in the
dilated medullary collecting ducts.
This gives a classic “paint brush”
appearance. Striated appearance of the
medullary collecting ducts with calyceal
distortion may also be encountered as the
disease increases in severity.
US examination reveals echogenic
medullary pyramids. Tiny calculi can be
seen involving the medullary pyramids.
On CT examination, the typical papillary
blush appearance can be noted in the
urographic phase with associated calculi in
the dilated collecting ducts suggestive of
medullary nephrocalcinosis.
CT urography scores over EU in
identification of dilated medullary
collecting ducts, calculi, obstruction, and
infection.
Nephronophthisis and Medullary Cystic
Kidney Disease
Medullary cystic disease complex applies to two tubulointerstitial diseases—
nephronophthisis and medullary cystic disease—which are progressive and the most
common heritable cause of renal failure in children and young adults.
It shows autosomal dominant inheritance. Genetic mutations result in protein
derangement which further results in ciliary dysfunction and formation of medullary
cysts.
Nephronophthisis has three forms—infantile, juvenile, and adolescent—based on the
age of onset.
The juvenile form is the most common with presentation at 4–6 years of age. Renal
failure can ensue at an average age of 13 years.
MCKD presents in young adults. Patients with both the forms of the disease present with
polyuria, polydipsia, and salt wasting. They may also develop hyperuricemia and gout.
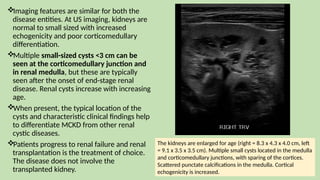
Imaging features are similar for both the
disease entities. At US imaging, kidneys are
normal to small sized with increased
echogenicity and poor corticomedullary
differentiation.
Multiple small-sized cysts <3 cm can be
seen at the corticomedullary junction and
in renal medulla, but these are typically
seen after the onset of end-stage renal
disease. Renal cysts increase with increasing
age.
When present, the typical location of the
cysts and characteristic clinical findings help
to differentiate MCKD from other renal
cystic diseases.
Patients progress to renal failure and renal
transplantation is the treatment of choice.
The disease does not involve the
transplanted kidney.
The kidneys are enlarged for age (right = 8.3 x 4.3 x 4.0 cm, left
= 9.1 x 3.5 x 3.5 cm). Multiple small cysts located in the medulla
and corticomedullary junctions, with sparing of the cortices.
Scattered punctate calcifications in the medulla. Cortical
echogenicity is increased.
References:
•Textbook of Radiology And Imaging, David Sutton, 8th
edition
•Grainger and Allison Diagnostic radiology, 7th
edition
•John R. Haaga et al., CT and MRI of the whole body, 6th
edition
•Carol M Rumack, Diagnostic Ultrasound, 6th
edition