Dr. Kiran G. Piparva.
Assistant professor, All India Institute of Medical
Science, Rajkot
Hypolipidaemic drugs
Fat in diet :Cholesterol:
• Critical substrate for the body:
Essential for
 Building cell membranes,
 the myelin sheath and the brain
 Building block of steroid
hormones
 Core component of bile salts, which helps in
digest dietary fats and fat soluble vitamins
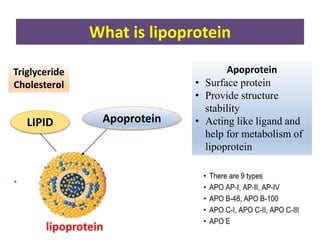
What is lipoprotein
LIPID Apoprotein
Triglyceride
Cholesterol
Apoprotein
• Surface protein
• Provide structure
stability
• Acting like ligand and
help for metabolism of
lipoprotein
lipoprotein
Lipoprotein metabolism
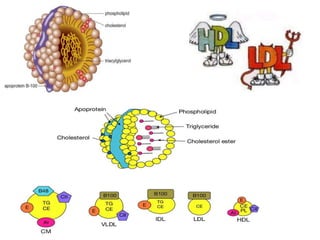
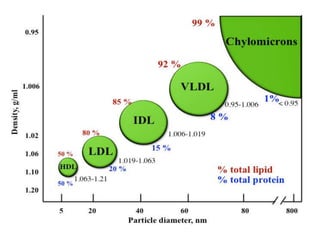
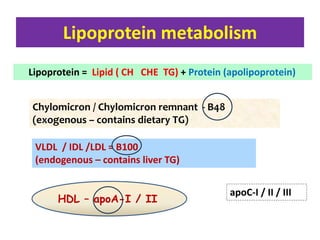
Lipoprotein = Lipid ( CH CHE TG) + Protein (apolipoprotein)
Chylomicron / Chylomicron remnant - B48
(exogenous – contains dietary TG)
VLDL / IDL /LDL = B100
(endogenous – contains liver TG)
HDL – apoA-I / II
apoC-I / II / III
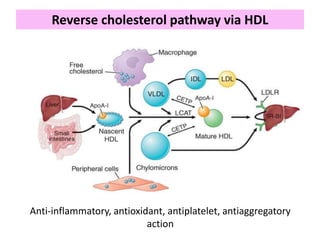
Reverse cholesterol pathway via HDL
Anti-inflammatory, antioxidant, antiplatelet, antiaggregatory
action
Hypolipidaemic drugs
Hyperlipidemia = Major cause of
atherosclerosis and atherosclerosis-induced
conditions, such as coronary heart disease (CHD)
and ischemic cerebrovascular disease
Lower the levels of lipids and lipoproteins
Type of hyperlipoproteinemia….
Primary:
a) Single gene defect- Monogenic/genetic
b) Multiple genetic, dietary and physical activity related causes-
Polygenic/ multifactorial.
• Secondary: Associated with
• Diabetes, Myxoedma, Nephrotic
syndrome, Chronic alcoholism
• Drugs(corticosteroids, oral
contraceptives, beta blockers)
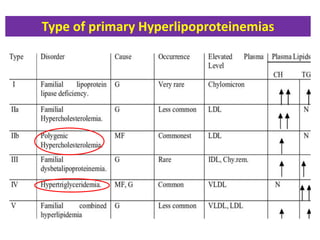
Type of primary Hyperlipoproteinemias
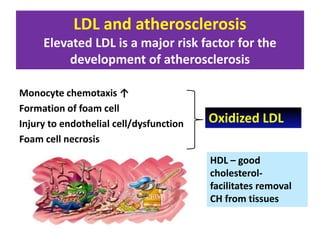
LDL and atherosclerosis
Elevated LDL is a major risk factor for the
development of atherosclerosis
Monocyte chemotaxis ↑
Formation of foam cell
Injury to endothelial cell/dysfunction
Foam cell necrosis
Oxidized LDL
HDL – good
cholesterol-
facilitates removal
CH from tissues
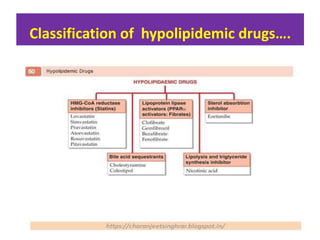
Classification of hypolipidemic drugs….
HMG –CO A reductase inhibitors…….
Lovastatin Atorvastatin
Pravastatin Rosuvastatin
Simvastatin Pitavastatin
HMG CoA reductase inhibitors = STATINS
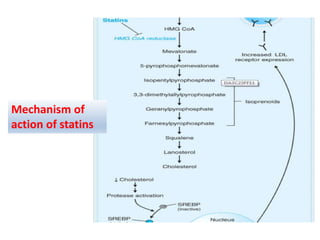
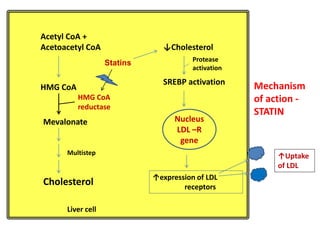
Mechanism of
action of statins
Acetyl CoA +
Acetoacetyl CoA
HMG CoA
Mevalonate
Cholesterol
HMG CoA
reductase
Statins
↓Cholesterol
SREBP activation
Nucleus
LDL –R
gene
↑expression of LDL
receptors
↑Uptake
of LDL
Protease
activation
Liver cell
Multistep
Mechanism
of action -
STATIN
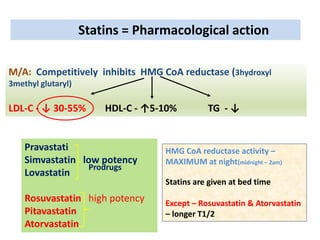
Statins = Pharmacological action
M/A: Competitively inhibits HMG CoA reductase (3hydroxyl
3methyl glutaryl)
LDL-C - ↓ 30-55% HDL-C - ↑5-10% TG - ↓
Pravastati
Simvastatin low potency
Lovastatin
Rosuvastatin high potency
Pitavastatin
Atorvastatin
HMG CoA reductase activity –
MAXIMUM at night(midnight – 2am)
Statins are given at bed time
Except – Rosuvastatin & Atorvastatin
– longer T1/2
Prodrugs
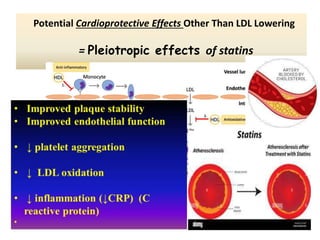
Potential Cardioprotective Effects Other Than LDL Lowering
= Pleiotropic effects of statins
• Well tolerated: Mild GIT/ Headache
ADR of statain
• Myopathy: Commonest- muscle weakness, myalgia
(serious rhabdomyolysis – rare)
when co-prescribed with
– nicotinic acid
- Gemfibrozil
- CYP 3A4 inhibitors (erythromycin,
cyclosporine, HIV protease
inhibitors
Drugs inhibiting
metabolism of statins ↑
risk of myopathy
Erythromycin
Ketoconazole
Uncommon: Hepatotoxicity -↑ alanine transaminase [ALT] and aspartate
transaminase [AST]
To be avoided in pregnancy
Clinical status of Statins:
• 1st choice drugs in reducing raised LDL-CH/
(primary /secondary hyperlipidemias)…
• Secondary prevention:↓ Mortality & morbidity –
Acute coronary Syndrome, Stroke, peripheral artery
disease, particularly after MI
• Primary prevention: Statins: ↓ mortality even in the
absence of cardiovascular disease
• Also used in primary hypercholesterolemia
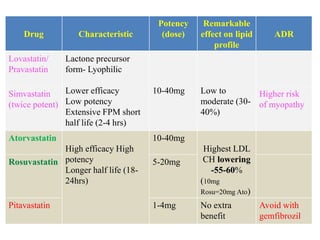
Drug Characteristic
Potency
(dose)
Remarkable
effect on lipid
profile
ADR
Lovastatin/
Pravastatin
Lactone precursor
form- Lyophilic
Lower efficacy
Low potency
Extensive FPM short
half life (2-4 hrs)
10-40mg Low to
moderate (30-
40%)
Simvastatin
(twice potent)
Higher risk
of myopathy
Atorvastatin
High efficacy High
potency
Longer half life (18-
24hrs)
10-40mg
Highest LDL
CH lowering
-55-60%
(10mg
Rosu=20mg Ato)
Rosuvastatin 5-20mg
Pitavastatin 1-4mg No extra
benefit
Avoid with
gemfibrozil
2. Lipoprotein lipase activator (PPAR
activators) /Fibrates:
FIBRATES
• 1st generation: Gemfibrozil
• 2nd generation: Fenofibrate(prodrug ), bezafibrate
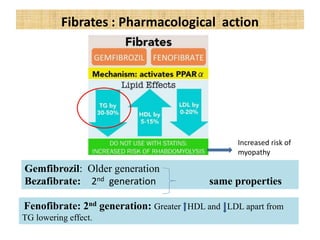
Fibrates : Pharmacological action
Gemfibrozil: Older generation
Bezafibrate: 2nd generation same properties
Fenofibrate: 2nd generation: Greater HDL and LDL apart from
TG lowering effect.
Increased risk of
myopathy
Fibrates - Gemfibrozil Bezafibrate
Fenofibrate ( prodrug )
ADR
• Git – Diarrhea
epigastric distress
• Rash headache
fatigue
• Myalgia
To be avoided in pregnant women
Dose reduction is required in the elderly and renal
insufficiency
• Myalgia
Gemfebrozil + statin -- ↑myopathy risk
(gemfebrozil inhibits hepatic uptake and
glucuronidation of statins)
Clinical status of fibrate
USE - Oral
• Useful in hypertriglyceridemias
• Particularly useful in type 3 & 4 hyperlipoproteinaemias
Don’t use fibrate:
1. If TG level do not lower after 2months of
Primary/secondary prevention of CVD
2. Prophylactic use of CKD
3. Diabetes and CKD
4. Don’t combine with statin
•Saroglitazar ??
PPAR -α PPAR -y
Thiazolidinediones fibrates
Diabetes dyslipidaemia
Only approved in indai
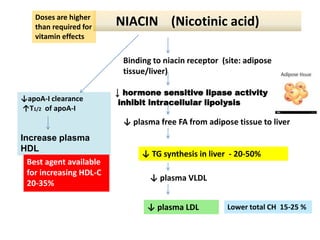
NIACIN (Nicotinic acid)
Binding to niacin receptor (site: adipose
tissue/liver)
↓ hormone sensitive lipase activity
inhibit intracellular lipolysis
↓ plasma free FA from adipose tissue to liver
↓ TG synthesis in liver - 20-50%
↓ plasma VLDL
↓ plasma LDL
↓apoA-I clearance
↑T1/2 of apoA-I
Increase plasma
HDL
Doses are higher
than required for
vitamin effects
Best agent available
for increasing HDL-C
20-35%
Lower total CH 15-25 %
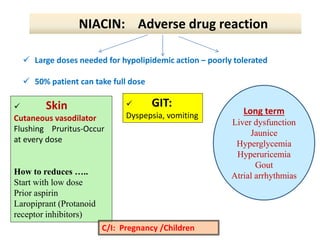
 Skin
Cutaneous vasodilator
Flushing Pruritus-Occur
at every dose
How to reduces …..
Start with low dose
Prior aspirin
Laropiprant (Protanoid
receptor inhibitors)
 GIT:
Dyspepsia, vomiting Long term
Liver dysfunction
Jaunice
Hyperglycemia
Hyperuricemia
Gout
Atrial arrhythmias
C/I: Pregnancy /Children
NIACIN: Adverse drug reaction
 Large doses needed for hypolipidemic action – poorly tolerated
 50% patient can take full dose
 Highly efficacious for type 3,4,5 hyperlipidemia but use is
restricted to high risk group only….
 Not recommended alone or combination with statin for
prevention of CVD (As per NICE guideline- )
 Imp indication is……..
 To control pancreatitis associated with hypertriglyceridemaemias
 Dose : 2gm /day
Clinical use: Current status of niacin…
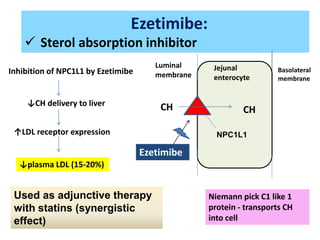
Ezetimibe:
 Sterol absorption inhibitor
CH CH
NPC1L1
Luminal
membrane
Basolateral
membrane
Jejunal
enterocyte
Niemann pick C1 like 1
protein - transports CH
into cell
Inhibition of NPC1L1 by Ezetimibe
↓CH delivery to liver
↑LDL receptor expression
↓plasma LDL (15-20%)
Ezetimibe
Used as adjunctive therapy
with statins (synergistic
effect)
• Ezetimibe inhibit cholesterol absorption by 54%,
precipitating a compensatory increase in cholesterol
synthesis that can be inhibited with a cholesterol
synthesis inhibitor such as a statin.
• Ezetimibe reduces LDL-C levels by 15-20%
Contraindicated in pregnant and nursing women,
women in childbearing years in the absence of
contraception
Ezetimibe: Pharmacological action
• Weak hypocholesterolemia drug
• As adjuvant - Used to supplement statin
• Ezetimibe+Statin (low dose)= High dose of
statin – LDL reduction (reduces upto 60%)
ADR: GI upset, Reversible hepatic dysfunction
Myositis (Rare)
Clinical status of Ezetimibe
Bile acid sequestrants
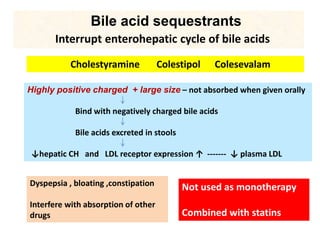
Interrupt enterohepatic cycle of bile acids
Cholestyramine Colestipol Colesevalam
Highly positive charged + large size – not absorbed when given orally
Bind with negatively charged bile acids
Bile acids excreted in stools
↓hepatic CH and LDL receptor expression ↑ ------- ↓ plasma LDL
Dyspepsia , bloating ,constipation
Interfere with absorption of other
drugs
Not used as monotherapy
Combined with statins
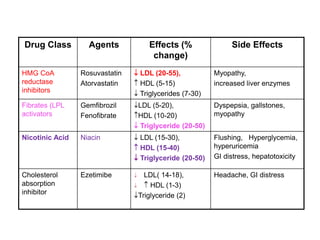
Drug Class Agents Effects (%
change)
Side Effects
HMG CoA
reductase
inhibitors
Rosuvastatin
Atorvastatin
 LDL (20-55),
 HDL (5-15)
 Triglycerides (7-30)
Myopathy,
increased liver enzymes
Fibrates (LPL
activators
Gemfibrozil
Fenofibrate
LDL (5-20),
HDL (10-20)
 Triglyceride (20-50)
Dyspepsia, gallstones,
myopathy
Nicotinic Acid Niacin  LDL (15-30),
 HDL (15-40)
 Triglyceride (20-50)
Flushing, Hyperglycemia,
hyperuricemia
GI distress, hepatotoxicity
Cholesterol
absorption
inhibitor
Ezetimibe  LDL( 14-18),
  HDL (1-3)
Triglyceride (2)
Headache, GI distress
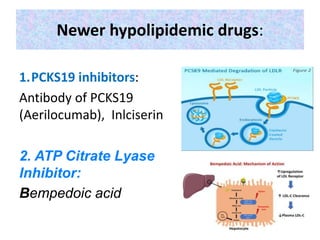
Newer hypolipidemic drugs:
1.PCKS19 inhibitors:
Antibody of PCKS19
(Aerilocumab), Inlciserin
2. ATP Citrate Lyase
Inhibitor:
Bempedoic acid
Guidelines for hypolipidemic drugs use:
1. Who need to start hypolipidemic drug?
2. Treatment of high plasma LDL-CH:
Nonpharmacological measure &
Pharmacological therapy
3. Treatment of low HDL-CH level
4. Treatment of Raised TG level
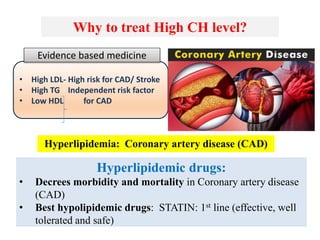
Why to treat High CH level?
• High LDL- High risk for CAD/ Stroke
• High TG Independent risk factor
• Low HDL for CAD
Evidence based medicine
Hyperlipidemia: Coronary artery disease (CAD)
Hyperlipidemic drugs:
• Decrees morbidity and mortality in Coronary artery disease
(CAD)
• Best hypolipidemic drugs: STATIN: 1st line (effective, well
tolerated and safe)
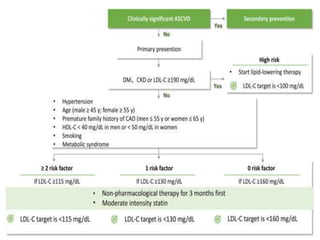
1. Who need to start hypolipidemic drug?:
Risk factor for coronary artery disease
1. Age: Man > years, Women >55 years
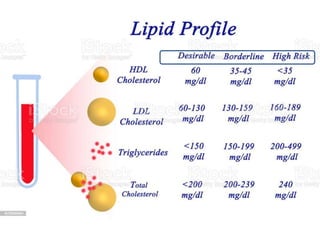
2. Hyperlipidaemia: High LDL- CH (≥160mg/dl)
or total CH: ≥ 240mg/dl)
3. Family history of MI/Sudden cardiac death before 55 years
(men), Women (65 years) in first degree relatives
4. Hypertension: BP>140/90mm of Hg
and antihypertensive Rx
6. Obesity: BMI> 25kg/m2) or Waist >40” (M)/ > 35” (F)
5. Diabetes mellitus
7. Smoking
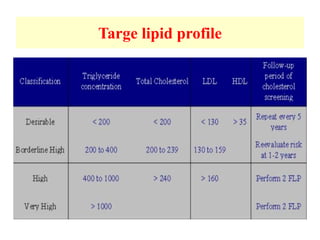
Targe lipid profile
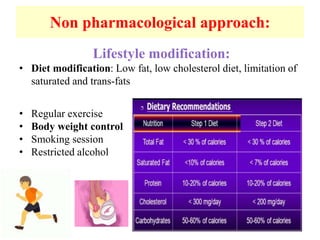
Non pharmacological approach:
Lifestyle modification:
• Diet modification: Low fat, low cholesterol diet, limitation of
saturated and trans-fats
• Regular exercise
• Body weight control
• Smoking session
• Restricted alcohol
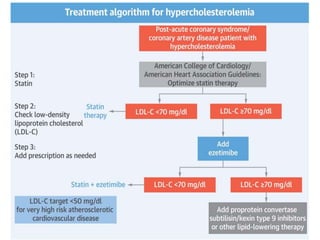
• Indication for statin therapy:
1. Subjects with ASCVD irrespective of plasma CH level
2. All subjects with LDL- CH >190mg/dl
3. All diabetes > 40 years of age
4. Subjects aged 40 years with ASCVD risk > 7.5% irrespective
of plasma CH level.
Statin therapy:
 High intensity (Atorvastatin (80mg)/Rosuvastatin
(10-40ng)
 Moderate intensity ( Rest all statins & others)
 Low intensity
3. Treatment of high plasma LDL-CH
INDICATION: CAD patients+ low HDL +Metabolic syndrome
• Rx of metabolic syndrome - normalize HDL-CH
• Primary approach in subject with low HDL-CH: Reduces LDL
–CH by Intensive statin therapy
• No benefit of adding niacin to statin therapy
Statin therapy:
 High intensity (Atorvastatin (80mg)/Rosuvastatin
(10-40ng)
 Moderate intensity ( Rest all statins & others)
 Low intensity
2. Treatment of low HDL-CH
Drug therapy: Statin + Fenofibrate + Niacin
3. Treatment of raised TG level
Vigilance for myopathy
INDICATION: Hypertriglyceridemia:
• Rx depends upon severity and cause (Obesity, physical
activity, high carbohydrate high calorie diet, saturated
and tans fat, alcohol, smoking, diabetes, kidney disease,
drugs, genetic disorder)
• TG level >500mg/dl: Risk of developing acute
pancreatitis
Hypolipidemic drugs Dr. Kiran Piparva.pptx