DEFINITION
• BGL ofless than 40mg/dL(plasma glucose level less than 45mg/dL)has
been taken as the operational threshold for intervention
• WHO has defined hypoglycemia as BGL of less than
45mg/dL(2.2mmol/L)
• Transitional neonatal hypoglycemia-BGL as low as 30mg/dLwithin 1 to
2 hours of birth in normal newborns.
3.
Symptomatic: Blood sugar<40 mg/dL
Asymptomatic:
• Less than 4 hours of age—25 mg/dL
• 4–24 hours of age—35 mg/dL
• 24–48 hours—45 mg/dL
• More than 48 hours—60 mg/dL
METHODS OF BLOODGLUCOSE ESTIMATION
• Point of care(POC)reagent strips(Glucose oxidase method)-common
screening method,overestimates hypoglycemia.
1st
generation strips based on enzymatic reaction causing color change
2nd
generation strips generate a current on reaction of glucose with
enzymes such as glu oxidase or dehydrogenase
• Continuos glucose monitoring sensors-insertion of probe in
subcutaneous tissue
• Laboratory diagnosis-gold std for measuring –glu oxidase method or glu
electrode method
• Samples to be transported in tubes containing glycolic inhibitors such as
fluoride.
7.
SYMPTOMS OF HYPOGLYCEMIA
•Asymptomatic
• Neurogenic(autonomic)-adrenergic and cholinergic responses-
tachycardia,tachypnea,poor suck,poor feeding,pallor,temperature
instability or sweating
• Neuroglycopenic –due to deficient supply to brain-
stupor,jitteriness,tremors,apathy,episodes of
cyanosis ,convulsions,intermittent apneic spells or
tachypnea,weak/high pitched cry,limpness and lethargy,difficulty in
feeding and eye rolling
8.
DIAGNOSIS
• ASYMPTOMATIC HYPOGLYCEMIA-BGLless than 40mg/dL and no
clinical manifestations
• SYMPTOMATIC HYPOGLYCEMIA-BGL less than 40mg/dl with clinical
symptoms including non specific signs
MANAGEMENT OF SYMPTOMATIC
HYPOGLYCEMIA
•All symptomatic hypoglycemia should be treated with IVF-bolus of
2ml/kg 10% dextrose(200mg/kg) f/b continuos glu infusion at rate of
6-8mg/kg/min
• BGl should be checked after 30 min and then every 6 hrs until
BGL>50mg/dl
• If BGL remain <50mg/dl inspite infusion GIR increased in steps of
2mg/kg/min every 15-30 min until a max of 12mg/kg/min
• After 24 hrs of iv glu therapy ,once 2 or more consecutive BGls are
>50mg/dl the infusion can be tapered 2mg/kg/min every 6 hrs with
BGL monitoring and stopped after GIR of 4mg/kg/min
11.
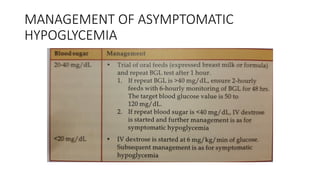
Symptomatic with bloodglucose < 25 mg/dL:
Give bolus IV dextrose 10% 1–2 mL/kg followed by infusion at the rate of 5–8 mg/kg/min.
• Target glucose > 50 mg/dL
• Continue breastfeeding frequently
• Recheck plasma glucose within 30 minutes
12.
Asymptomatic: <40 mg/dLand <4 hours of age:
• Start breastfeeding within half an hour
• Recheck blood glucose before next feeding
• Continue skin-to-skin care
• Intensify breastfeeding
• Evaluate for other underlying illnesses
• If glucose <35 mg/dL start IV glucose therapy
• Target blood glucose > 50 mg/dL
• Recheck until three normal levels
• Check glucose levels once at 24 hours of age in babies like small for
gestational age (SGA)/ low birth weight (LBW)/preterm
13.
PARENTRAL THERAPY
• Rateof start of IV fluids: Use graded approach
• IUGR: 5–7 mg/kg/min
• Mother with infants of diabetic mothers (IDM)/LGA infants:
3–5 mg/kg/min
• Infant with other risk group: 4–6 mg/kg/min
• Glucose infusion >12 mg/kg/min: Consider for further
interventions
• Maximum dextrose concentration through peripheral IV
cannula and central venous catheter is 12.5% and 25%,
respectively
14.
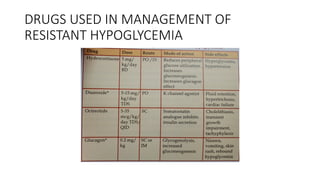
RECURRENT/RESISTANT HYPOGLYCEMIA
• Infantfails to maintain normal BGL despite a GIR of 12mg/kg/min or
when stabilization is not achieved by 7 days of therapy
• MCC is hyperinsulinism-can be congenital or acquired(maternal
diabetes,birth asphyxia,polycythemia,rh incompatibility And severe
IUGR).diagnosis is based on critical sample assay
• Criteria for disgnosis of hyperinsulinism
FOLLOWUP AND OUTCOME
•Determined by factors like duration,severity of hypoglycemia,rate of
cerebral blood flow,cerebral utilization of glucose and co-morbidities
• Special attention to neuro-developmental outcome,overall IQ,reading
ability,arithmetic proficiency and motor performance
• To be assessed at 1 month corrected age for vision
• At3,6,9,12 and 18months corrected age for
growth,neurodevelopment,vision and hearing loss
• MRI at 4-6 weeks provides good estimate of hypoglycemic injury
• Recurrent and persistent hypoglycemia is associated with seizures, poor
visual motor, and executive function at 4–5 years of age,