Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 1
METHODS ADOPTED TO MAINTAIN
QUALITY IN HOSPITAL
EXCELLENCE MANUAL
Global Standards for Hospital Quality Management Excellence, Patient Safety, and
Continuous Improvement
A Comprehensive Reference for
THE HOSPITAL-WIDE QUALITY MANAGEMENT TEAM
Quality Managers • Quality Coordinators • Department Quality Champions • Accreditation & Continuous
Improvement Professionals
“Quality Is Never an Accident — It Is the Sum of Methods Applied Consistently, By Everyone,
Every Single Day.”
Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 2
DEDICATION
This book is dedicated to all those who are committed to advancing healthcare through a discipline that operates
beneath every other discipline in this hospital: the systematic methods, cycles, and structures that turn individual
good intentions into institution-wide, sustained excellence — because a single dedicated clinician cannot make a
hospital safe alone, but a hospital built on rigorous quality methods can make every clinician's good intentions
actually reach every patient, every time.
To Every Patient Who Benefited from a System They Never Saw
For whom a root cause analysis that quietly fixed a recurring error, a corrective action that closed a gap before it
could harm someone else, and a quality indicator tracked patiently over months represent a promise kept: that this
hospital does not merely hope for excellence, but builds it, methodically, one improvement cycle at a time.
To Every Department That Trusted the Quality System to Make Them Better
For whom a fair, honest incident report, a rigorous clinical audit, and a data-driven improvement plan are not
bureaucratic burdens but the very mechanism by which good departments become excellent ones, and excellent
ones stay that way under changing staff, changing volumes, and changing pressures.
To My Family
For their unwavering love, patience, and encouragement, which have been the foundation of this journey.
To My Mentors & Teachers
For inspiring my passion, guiding my path, and instilling in me the understanding that quality in healthcare is never
the product of good intentions alone — it is the product of methods: the PDCA cycle applied honestly, the root cause
found rather than the nearest scapegoat blamed, and the discipline to keep measuring even after the crisis that
prompted the measurement has passed.
To My Colleagues & Friends
For their support, collaboration, and shared dedication to a discipline where the true test of a quality system is not
how it performs during an accreditation survey, but how it performs on an ordinary Tuesday when no one outside
the hospital is watching.
To Every Member of the Hospital Quality Management Team
Quality managers, quality coordinators, department quality champions, and every professional who has turned a
single adverse event into a lesson the entire hospital learned — the architects of the invisible infrastructure that
makes every other department's excellence possible, sustainable, and real.
Your vigilance, your methodological rigour, and your unwavering commitment to building quality into the
system itself, rather than hoping for it individually, are the silent pillars every other department in this hospital
stands upon. This book is for you, and because of you. Thank you to everyone who has been a part of this journey.
Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 3
FOREWORD
There is a discipline in this hospital that operates beneath every other discipline: it does not treat a single
patient directly, yet its methods determine whether every other department's good intentions actually and
reliably reach the patients they serve. A single dedicated clinician cannot make a hospital safe alone —
excellence delivered by individual heroism, however genuine, is fragile, inconsistent, and unsustainable across
shift changes, staff turnover, and the ordinary pressures of a busy day. What makes a hospital reliably excellent
is not the presence of good people, who exist everywhere, but the presence of rigorous, repeatable methods
that turn good intentions into consistent outcomes: the PDCA cycle applied honestly, the root cause analysis
that looks past the nearest scapegoat, the corrective action that is genuinely implemented and verified, and
the quality indicator tracked patiently long after the crisis that prompted its creation has faded from memory.
The “Methods Adopted to Maintain Quality in Hospital Excellence Manual: Global Standards for Hospital
Quality Management Excellence, Patient Safety, and Continuous Improvement” has been developed to provide
a comprehensive professional framework for the hospital-wide Quality Management team — quality
managers, quality coordinators, department quality champions, and accreditation and continuous
improvement professionals — working together to build the systematic infrastructure that makes every
department's excellence possible, sustainable, and verifiable.
This manual brings together internationally recognized quality methodologies — the PDCA/PDSA improvement
cycle, Failure Mode and Effects Analysis (FMEA), Root Cause Analysis (RCA), Corrective and Preventive Action
(CAPA), Lean and Six Sigma process improvement, clinical audit and benchmarking, incident reporting and
patient safety surveillance, and data-driven quality dashboards. It is built around globally accepted
accreditation frameworks — WHO patient safety and quality guidelines, NABH, JCI, and international standards
from the International Society for Quality in Health Care (ISQua) and ISO 9001 quality management systems —
to provide a rigorous, regulation-compliant framework for Hospital Quality Management excellence.
The chapters of this manual guide the Quality Management team through every dimension of the role — from
the foundational improvement cycle that underlies every other method, through rigorous incident
investigation and corrective action, to systematic clinical audit, quality indicator tracking, and the professional
conduct that defines excellence across every category of quality work: the near-miss quietly investigated
before it became a catastrophe, the recurring error traced to its true systemic cause rather than an individual's
blame, and the quality dashboard that turns raw data into decisions that protect the next patient.
Hospital Quality Management is not simply an administrative or compliance function — it is a distinct discipline
built on the understanding that reliable excellence is a designed system, not a hoped-for outcome, that every
adverse event carries a lesson the entire institution can learn from if the investigation is honest enough to find
it, and that the true measure of this team's work is not how the hospital performs when it is being watched,
but how it performs on an ordinary day when no one outside is looking. Their work is defined by a
methodological rigour that must never relax, because the system built loosely today is the preventable harm
discovered tomorrow.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 4
It is hoped that this manual will serve as an indispensable resource for Quality Managers, Quality Coordinators,
Department Quality Champions, hospital administrators, and all those committed to building a healthcare
system where excellence is not an accident of good people trying hard, but the reliable output of methods
applied consistently, by everyone, every single day.
“Quality Is Never an Accident — It Is the Sum of Methods Applied Consistently, By Everyone, Every Single
Day.”
With Best Wishes, Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 5
TABLE OF CONTENTS
FOREWORD............................................................................................................................................3
LIST OF ABBREVIATIONS........................................................................................................................8
MANUAL MOTTO.................................................................................................................................10
CHAPTER 1: Introduction.....................................................................................................................11
Purpose...........................................................................................................................................................11
Objectives .......................................................................................................................................................12
Vision & Mission .............................................................................................................................................13
CHAPTER 2: Methods Adopted to Maintain Quality in Hospital........................................................14
The PDCA/PDSA Improvement Cycle..............................................................................................................14
Failure Mode and Effects Analysis (FMEA) .....................................................................................................14
Root Cause Analysis (RCA) ..............................................................................................................................15
Corrective and Preventive Action (CAPA).......................................................................................................15
Clinical Audit and Benchmarking ....................................................................................................................16
Incident Reporting and Patient Safety Surveillance........................................................................................16
Quality Indicators and Data-Driven Dashboards ............................................................................................17
Lean and Six Sigma Process Improvement......................................................................................................17
CHAPTER 3: Professional Standards for the Quality Management Team..........................................17
Professional Appearance & Behaviour ...........................................................................................................17
Communication Standards .............................................................................................................................18
Confidentiality & Information Security...........................................................................................................19
Ethical Standards ............................................................................................................................................19
Time Management, Teamwork & Continuous Learning.................................................................................20
CHAPTER 4: Communication Across a Hospital-Wide Quality System...............................................21
The A-T-C-R-C Communication Model............................................................................................................21
Communicating Findings Without Blame .......................................................................................................22
CHAPTER 5: Patient Safety and Quality System Standards ................................................................24
The R-T-A-C-A Framework ..............................................................................................................................24
Daily Quality Standards Checklist ...................................................................................................................26
CHAPTER 6: Confidentiality, Privacy, and Information Security ........................................................28
Privacy in Quality Investigation ......................................................................................................................28
Cybersecurity of Quality and Incident Reporting Systems..............................................................................29
CHAPTER 7: Standard Operating Procedures (SOPs)..........................................................................30
SOP 1: PDCA/PDSA Improvement Cycle Application ......................................................................................30
SOP 2: FMEA for Proactive Risk Identification................................................................................................30
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 6
SOP 3: Root Cause Analysis Following a Sentinel Event .................................................................................31
SOP 4: Corrective and Preventive Action Development and Verification.......................................................31
SOP 5: Clinical Audit and Benchmarking.........................................................................................................32
SOP 6: Incident and Near-Miss Reporting.......................................................................................................32
SOP 7: Quality Indicator Definition and Dashboard Reporting.......................................................................33
SOP 8: Accreditation Readiness and Standards Compliance ..........................................................................33
SOP 9: Mortality and Morbidity Review .........................................................................................................34
SOP 10: Patient Feedback and Satisfaction Measurement.............................................................................34
CHAPTER 8: Communication with Special Groups..............................................................................35
CHAPTER 9: Handling Difficult Situations ...........................................................................................37
CHAPTER 10: Emergency Response — Critical Quality and Safety Events.........................................40
CHAPTER 11: Digital Competency for the Quality Management Team .............................................43
CHAPTER 12: Daily Quality Management Checklist............................................................................45
CHAPTER 13: Key Performance Indicators (KPIs)................................................................................47
CHAPTER 14: Top 20 Do's & Top 20 Don'ts.........................................................................................49
CHAPTER 15: Quality Management Professional Pledge ...................................................................52
CONCLUSION........................................................................................................................................55
REFERENCES.........................................................................................................................................57
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 7
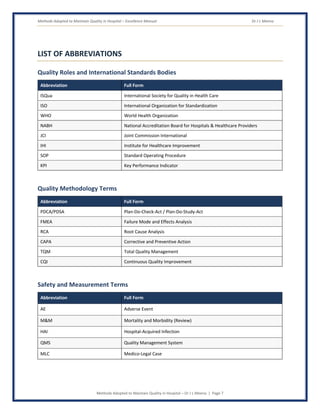
LIST OF ABBREVIATIONS
Quality Roles and International Standards Bodies
Abbreviation Full Form
ISQua International Society for Quality in Health Care
ISO International Organization for Standardization
WHO World Health Organization
NABH National Accreditation Board for Hospitals & Healthcare Providers
JCI Joint Commission International
IHI Institute for Healthcare Improvement
SOP Standard Operating Procedure
KPI Key Performance Indicator
Quality Methodology Terms
Abbreviation Full Form
PDCA/PDSA Plan-Do-Check-Act / Plan-Do-Study-Act
FMEA Failure Mode and Effects Analysis
RCA Root Cause Analysis
CAPA Corrective and Preventive Action
TQM Total Quality Management
CQI Continuous Quality Improvement
Safety and Measurement Terms
Abbreviation Full Form
AE Adverse Event
M&M Mortality and Morbidity (Review)
HAI Hospital-Acquired Infection
QMS Quality Management System
MLC Medico-Legal Case
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 8
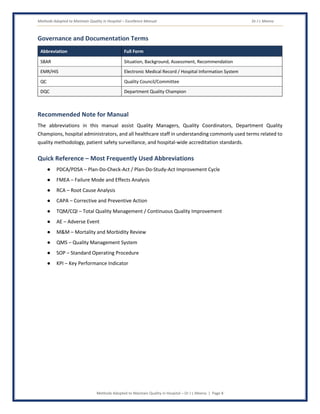
Governance and Documentation Terms
Abbreviation Full Form
SBAR Situation, Background, Assessment, Recommendation
EMR/HIS Electronic Medical Record / Hospital Information System
QC Quality Council/Committee
DQC Department Quality Champion
Recommended Note for Manual
The abbreviations in this manual assist Quality Managers, Quality Coordinators, Department Quality
Champions, hospital administrators, and all healthcare staff in understanding commonly used terms related to
quality methodology, patient safety surveillance, and hospital-wide accreditation standards.
Quick Reference – Most Frequently Used Abbreviations
● PDCA/PDSA – Plan-Do-Check-Act / Plan-Do-Study-Act Improvement Cycle
● FMEA – Failure Mode and Effects Analysis
● RCA – Root Cause Analysis
● CAPA – Corrective and Preventive Action
● TQM/CQI – Total Quality Management / Continuous Quality Improvement
● AE – Adverse Event
● M&M – Mortality and Morbidity Review
● QMS – Quality Management System
● SOP – Standard Operating Procedure
● KPI – Key Performance Indicator
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 9
MANUAL MOTTO
“Quality Is Never an Accident —”
“It Is the Sum of Methods”
“Applied Consistently, By Everyone, Every Single Day.”
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 10
CHAPTER 1: INTRODUCTION
1. Purpose
There is a discipline in this hospital that operates beneath every other discipline: it does not treat a single
patient directly, yet its methods determine whether every other department's good intentions actually and
reliably reach the patients they serve. A single dedicated clinician cannot make a hospital safe alone —
excellence delivered by individual heroism, however genuine, is fragile, inconsistent, and unsustainable across
shift changes, staff turnover, and the ordinary pressures of a busy day. This manual exists because what makes
a hospital reliably excellent is not the presence of good people, who exist everywhere, but the presence of
rigorous, repeatable methods that turn good intentions into consistent outcomes.
The World Health Organization and international quality bodies — ISQua, ISO — recognize that structured
improvement methodologies, rigorous incident investigation, and systematic quality measurement are directly
and measurably linked to reduced preventable harm and improved patient outcomes. Research consistently
demonstrates that hospitals applying disciplined PDCA cycles, honest root cause analysis, and verified
corrective action achieve dramatically and measurably better safety outcomes than institutions relying on
individual vigilance alone, without systematic methods behind it. In institutions where the Quality
Management team applies systematic improvement cycles, rigorous incident investigation, and honest, data-
driven quality tracking, patient outcomes are demonstrably and measurably better. The investment in Hospital
Quality Management excellence is, without qualification, one of the highest-yield investments any healthcare
system can make — turning every other department's good intentions into a system that reliably protects
patients.
Why the Quality Management Team Is Critical to Healthcare Quality
● Provides the systematic methods that turn individual good intentions into institution-wide, sustained
excellence.
● Applies rigorous incident investigation that finds true systemic causes rather than convenient
individual blame.
● Develops and verifies corrective actions that genuinely close the gaps adverse events reveal.
● Maintains quality indicator tracking that turns raw data into decisions protecting the next patient.
● Coordinates accreditation readiness ensuring the hospital meets and sustains global quality standards.
● Applies proactive risk identification (FMEA) that prevents harm before it ever reaches a patient.
● Facilitates clinical audit and benchmarking that reveals genuine performance gaps against best
practice.
● Contributes to sustained NABH, JCI, and ISO compliance across every hospital department.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 11
Key Responsibilities of the Quality Management Team
● Applying the PDCA/PDSA improvement cycle systematically across hospital processes.
● Applying FMEA proactively to identify and mitigate risk before harm occurs.
● Conducting rigorous, honest root cause analysis following significant adverse events.
● Developing and verifying corrective and preventive actions that genuinely resolve identified gaps.
● Facilitating systematic clinical audit and benchmarking against best practice.
● Maintaining a fair, non-punitive incident and near-miss reporting culture.
● Tracking quality indicators and maintaining data-driven dashboards for institutional decision-making.
● Engaging in continuous professional development to maintain competence in evolving quality
methodology.
2. Objectives
1. Apply Systematic Improvement Methodology Institution-Wide
Every significant process must be improved through structured methodology, not ad hoc effort — this is the
Quality Management team's foundational obligation.
How to Achieve:
● Apply the PDCA/PDSA cycle systematically to every improvement initiative.
● Apply FMEA proactively to high-risk processes before harm occurs.
● Never allow improvement to depend on individual heroism rather than systematic method.
2. Investigate Adverse Events Honestly and Find True Causes
● Apply rigorous root cause analysis following every significant adverse event.
● Resist the temptation to stop at convenient individual blame rather than systemic cause.
● Foster a fair, non-punitive culture that encourages honest reporting.
3. Develop and Verify Genuine Corrective Action
● Apply structured CAPA development for every significant finding.
● Verify that corrective actions are genuinely implemented and effective, not merely documented.
4. Track Quality Systematically and Transparently
● Apply systematic quality indicator tracking across every department.
● Maintain transparent, data-driven dashboards supporting institutional decision-making.
5. Maintain Accreditation and Regulatory Compliance
● Comply with national and international quality accreditation standards.
● Maintain NABH/JCI/ISO documentation and readiness continuously, not only before survey.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 12
6. Build a Sustainable Quality Culture
● Foster department quality champions across every clinical and non-clinical area.
● Ensure quality methods are genuinely used, not merely documented for compliance.
3. Vision
Vision Statement
“To build and maintain a hospital where quality is never left to individual heroism alone, where every significant
risk is identified proactively, every adverse event is investigated honestly to its true cause, and every
improvement is verified to genuinely protect the next patient.”
4. Mission
Mission Statement
“To deliver systematic, rigorous, and sustained quality management across every hospital department, through
disciplined improvement methodology, honest incident investigation, and transparent, data-driven quality
tracking, enabling the healthcare organization to provide consistently excellent, accredited care regardless of
who is on duty or who is watching.”
Expected Outcomes of an Excellent Hospital Quality Management Practice
● 100% of significant adverse events receive documented, rigorous root cause analysis.
● 100% of corrective actions verified genuinely implemented and effective.
● Systematic quality indicator tracking maintained across every hospital department.
● Sustained, continuous NABH/JCI/ISO accreditation readiness, not only before survey.
● A fair, non-punitive incident reporting culture with measurably increasing near-miss reporting rates.
The Hospital Quality Management team builds the systematic infrastructure beneath every other
department's excellence — their improvement cycles turn good intentions into consistent outcomes, their
honest root cause analysis finds true systemic causes rather than convenient blame, and their verified
corrective actions ensure that quality is never left to individual heroism alone.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 13
CHAPTER 2: METHODS ADOPTED TO MAINTAIN QUALITY IN HOSPITAL
1. The PDCA/PDSA Improvement Cycle
Overview
The Plan-Do-Check-Act (or Plan-Do-Study-Act) cycle is the foundational method underlying nearly every other
quality technique — a structured, repeatable approach to testing and implementing improvement that
prevents change from being either reckless or perpetually theoretical.
How It Is Applied
● Plan: Identify a specific problem and a testable, measurable improvement hypothesis.
● Do: Implement the change on a small, controlled scale.
● Check/Study: Measure the actual result against the predicted result honestly.
● Act: Standardize the change if successful, or revise the plan and cycle again if not.
2. Failure Mode and Effects Analysis (FMEA)
Overview
FMEA is a proactive risk assessment method that identifies potential failure points in a process before they
cause actual harm, allowing the hospital to fix a dangerous process on paper rather than learning about its
danger through a patient's injury.
How It Is Applied
● Map the process step by step, identifying every point where failure could occur.
● Score each potential failure by severity, likelihood, and detectability.
● Prioritize and redesign the highest-risk failure points before implementation.
3. Root Cause Analysis (RCA)
Overview
RCA is the rigorous, structured investigation applied after a significant adverse event, designed to find the true
systemic cause rather than settling for the nearest convenient individual to blame.
How It Is Applied
● Convene a multidisciplinary team promptly following a qualifying event.
● Apply structured techniques (e.g., the “five whys,” fishbone diagrams) to trace the causal chain to its
systemic root.
● Distinguish genuine systemic causes from individual human error, addressing the system that allowed
the error to cause harm.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 14
4. Corrective and Preventive Action (CAPA)
Overview
CAPA translates an RCA's findings into genuine, verified change — a corrective action fixes what already went
wrong, while a preventive action stops the same failure mode from occurring elsewhere in the system.
How It Is Applied
● Develop specific, assigned, time-bound corrective and preventive actions from every significant RCA
or FMEA finding.
● Verify genuine implementation and measure the corrective action's actual effectiveness, not merely
its documentation.
5. Clinical Audit and Benchmarking
Overview
Clinical audit systematically compares actual practice against defined standards, while benchmarking compares
institutional performance against peer institutions or national/international norms, together revealing genuine
performance gaps.
How It Is Applied
● Apply systematic, periodic clinical audit against defined evidence-based standards.
● Benchmark institutional performance against national/international quality data.
6. Incident Reporting and Patient Safety Surveillance
Overview
A fair, non-punitive incident and near-miss reporting culture is the sensing mechanism for the entire quality
system — without honest reporting, no other method has anything genuine to work with.
How It Is Applied
● Maintain an accessible, fair, non-punitive incident and near-miss reporting system.
● Apply systematic surveillance for patterns across reported incidents.
7. Quality Indicators and Data-Driven Dashboards
Overview
Quality indicators translate abstract goals like “safety” and “excellence” into concrete, trackable measures that
reveal whether genuine improvement is occurring or whether performance is merely assumed.
How It Is Applied
● Define clear, measurable quality indicators across every hospital department.
● Maintain transparent, regularly updated dashboards supporting data-driven institutional decisions.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 15
8. Lean and Six Sigma Process Improvement
Overview
Lean methodology eliminates waste and inefficiency in hospital processes, while Six Sigma reduces variation
and defects, together supporting both efficiency and consistency in care delivery.
How It Is Applied
● Apply Lean process mapping to identify and eliminate non-value-adding steps.
● Apply Six Sigma statistical methods to reduce process variation in high-stakes clinical workflows.
How These Methods Together Maintain Quality in the Hospital
● PDCA provides the universal engine for testing and implementing every improvement, large or small.
● FMEA prevents harm proactively, fixing dangerous processes before a patient is ever exposed to them.
● RCA and CAPA together ensure that when harm does occur, the true cause is found and genuinely
fixed.
● Clinical audit and quality indicators provide the honest, ongoing measurement that tells the hospital
whether it is actually improving.
● Incident reporting provides the sensing mechanism that feeds every other method with genuine,
honest information.
These methods are not a compliance checklist — they are the systematic infrastructure that turns
individual good intentions into institution-wide, sustained excellence, ensuring that quality in this hospital
does not depend on which staff happen to be on duty or who happens to be watching.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 16
CHAPTER 3: PROFESSIONAL STANDARDS FOR THE QUALITY
MANAGEMENT TEAM
Hospital Quality Management practice requires an uncommon combination of methodological rigour applying
structured techniques consistently, the courage to investigate honestly even when the findings are
uncomfortable, and the diplomatic skill to hold every department accountable without becoming an adversary
any department dreads working with. The standards that govern Quality Management practice derive from
the discipline's unique position: operating across every department while directly treating none of them.
1. Professional Appearance
Standards
Attire and Identification
● Wear appropriate professional attire and ID badge as per hospital policy.
Professional Presence
● Maintain a calm, objective, and constructive demeanor throughout every investigation and audit.
● Model methodological rigour that never relaxes, regardless of departmental relationships or pressure.
2. Professional Behaviour
Expected Behaviours
Methodological Discipline
● Never skip a structured methodology step to reach a faster, more convenient conclusion.
● Never allow an RCA to stop at individual blame when a genuine systemic cause remains unexamined.
Accountability
● Own every investigation finding, every corrective action verification, and every quality indicator
reported.
● Report and disclose any conflict of interest in an investigation honestly and promptly.
Collaborative Respect
● Treat every department and every staff member involved in an investigation as a genuine partner in
improvement, not a suspect.
Patient-Centered Focus
● Every audit, every investigation, and every indicator is ultimately about the next patient's safety —
never about assigning blame or protecting institutional reputation over genuine improvement.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 17
3. Communication Standards
Communication with Departments
● Communicate audit and investigation findings honestly, constructively, and without blame.
● Explain the rationale behind quality methods clearly, building genuine departmental buy-in rather than
compliance alone.
Communication Within the Team
● Communicate significant findings rapidly and clearly using closed-loop communication.
● Use structured handover tools (SBAR or equivalent) for every transfer of investigation responsibility.
● Escalate any identified systemic risk immediately and directly to leadership.
Written Communication Standards
● Quality documentation must be accurate, contemporaneous, and complete, reflecting genuine
methodology applied.
● Reports must be exact, evidence-based, and free of language that assigns blame rather than identifies
systemic cause.
4. Confidentiality and Information Security
Overview
Quality Management involves particularly sensitive information, including adverse event details and individual
staff performance data, requiring heightened confidentiality discipline.
Responsibilities
● Discuss investigation and audit findings only in appropriate settings and only with those who have a
legitimate need to know.
● Protect access credentials for incident reporting and quality information systems.
● Apply particular discretion for individual staff performance data within investigations.
5. Ethical Standards
Core Ethical Principles for Quality Management Practice
Non-Maleficence
● Never allow a known systemic risk to persist unaddressed once identified.
● Never let an investigation become a vehicle for punitive blame rather than genuine improvement.
Beneficence
● Apply rigorous, evidence-based methodology consistently, ensuring every improvement genuinely
protects patients.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 18
Honesty and Transparency
● Communicate investigation findings, quality performance, and any institutional gap honestly, including
to leadership.
Justice and Equity
● Apply the same rigorous audit and investigation standard to every department, regardless of seniority
or influence.
6. Time Management and Prioritization
Priority Framework
● Immediate/Emergency: Sentinel event requiring urgent RCA, systemic risk requiring urgent CAPA —
immediate response, no delay.
● Urgent: Significant incident pattern, accreditation gap identified — prompt investigation and
resolution.
● Routine: Scheduled audits, routine quality indicator review — managed per defined schedule, with
unwavering methodological discipline.
7. Teamwork and Collaboration
Work Effectively With
● Every clinical and non-clinical department — as genuine partners in quality, not adversarial auditors.
● Department quality champions — building distributed quality capability across the institution.
● Hospital leadership — for resource support and strategic quality direction.
● Accreditation bodies — for sustained NABH/JCI/ISO compliance.
8. Professional Competence and Continuous Learning
Areas of Competence
● PDCA/PDSA, FMEA, RCA, and CAPA methodologies.
● Clinical audit design and statistical benchmarking.
● Incident reporting system design and non-punitive safety culture building.
● Quality indicator design and data dashboard development.
● Lean and Six Sigma process improvement techniques.
Continuous Learning
● Maintain current certification in relevant quality management competencies.
● Maintain current knowledge of evolving quality methodology and accreditation standards (ISQua,
WHO, ISO).
● Engage with national and international quality management professional bodies.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 19
● Participate regularly in RCA facilitation and FMEA workshop training.
● Participate in NABH and JCI accreditation preparation training continuously, not only before survey.
Professional Standards Checklist
● Have I applied structured methodology rigorously in every investigation and audit today?
● Have I pursued true systemic causes rather than stopping at convenient individual blame?
● Have I verified that corrective actions are genuinely implemented and effective?
● Have I communicated findings honestly and constructively, without blame?
● Have I treated every department as a genuine partner in improvement today?
● Have I escalated any identified systemic risk immediately?
Quality Management professionalism is methodological rigour applied without exception, paired with the
diplomatic skill to make every department a genuine partner rather than an adversary — the team that
finds true systemic causes and verifies genuine corrective action is the team that turns individual good
intentions into institution-wide, sustained excellence.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 20
CHAPTER 4: COMMUNICATION ACROSS A HOSPITAL-WIDE QUALITY
SYSTEM
Communication in Quality Management must accomplish something genuinely difficult: hold every
department accountable for genuine improvement while never becoming an adversary any department dreads
working with. A quality team that inspires defensiveness gets compliance theatre; a quality team that builds
genuine partnership gets real, sustained improvement.
Why Communication Quality Matters in Hospital Quality Management
● Communication that assigns blame rather than identifies systemic cause discourages the honest
reporting every other method depends upon.
● Clear, constructive audit feedback builds genuine departmental ownership of improvement, rather
than resentful compliance.
● Honest communication with leadership about genuine gaps, even uncomfortable ones, is essential to
real institutional improvement.
● Transparent quality dashboard communication builds trust in the data driving institutional decisions.
The A-T-C-R-C Communication Model for Quality Management
A — Acknowledge
Definition
Acknowledge the department's genuine effort and context before delivering audit or investigation findings.
Examples
● “I know this team works incredibly hard under real pressure — let's look together at what the data
and this investigation show, and how we can make the system support you better.”
T — Listen (Elicit Genuine Context)
Definition
Listen genuinely to the department's own perspective on the systemic factors contributing to a finding.
C — Clarify (Communicate Findings Without Blame)
Definition
Communicate the finding's systemic cause and its evidence clearly, framed around the process rather than the
person.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 21
Examples
● “The root cause analysis points to a gap in how this handover step is structured, not to anyone's
individual carelessness — let's redesign the process together.”
R — Respond (Collaborate on Genuine Solutions)
Definition
Respond by collaborating with the department on genuinely workable corrective action, not imposing a
solution unilaterally.
C — Confirm (Verify Shared Understanding and Commitment)
Definition
Confirm genuine shared understanding of the finding and genuine commitment to the corrective action, not
merely compliance.
Communicating Findings Without Blame
Principles for Blame-Free, Genuinely Improvement-Focused Communication
● Frame every finding around the system and process, not the individual, unless genuine misconduct is
involved.
● Communicate that the goal of every investigation is protecting the next patient, never punishing the
last provider.
● Build genuine departmental ownership of corrective action rather than imposing solutions unilaterally.
Communicating with Leadership
● Communicate genuine institutional gaps honestly, even when the finding is uncomfortable for
leadership to hear.
● Advocate for necessary resources with clear, evidence-based patient safety justification.
Communicating Quality Data Transparently
● Communicate quality indicator performance transparently, including genuine underperformance, not
only successes.
● Explain data limitations and genuine uncertainty honestly rather than overstating dashboard precision.
Common Quality Management Communication Mistakes to Avoid
● Framing an RCA finding in language that assigns blame to an individual rather than identifying systemic
cause.
● Imposing corrective action unilaterally without genuine departmental collaboration.
● Softening or hiding genuine institutional gaps to avoid uncomfortable conversations with leadership.
● Presenting quality data with more certainty or precision than the underlying data genuinely supports.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 22
Communication in Quality Management must hold every department accountable while making them
genuine partners, not adversaries — the team that frames findings around systems rather than blame, and
collaborates on genuine solutions rather than imposing them, is the team that builds the honest reporting
culture every other quality method depends upon.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 23
CHAPTER 5: PATIENT SAFETY AND QUALITY SYSTEM STANDARDS
Patient safety through Quality Management is uniquely defined by systems rather than individual encounters
— a hospital that applies rigorous improvement methodology, honest incident investigation, and genuine
corrective action verification produces measurably better outcomes across every department than one relying
on individual staff vigilance alone. The R-T-A-C-A framework applies with particular intensity to a discipline
whose success is measured not in any single patient encounter, but in the reliability of the system protecting
every patient encounter across the institution.
1. RESPECT
Definition
Treating every department's context and every staff member's perspective as genuinely valuable input into
system improvement, rather than treating quality work as external oversight imposed upon them.
How the Quality Management Team Demonstrates Respect
● Respect for Departmental Expertise: Involve frontline staff genuinely in redesigning the processes they
work within.
● Respect for Honest Reporting: Protect and value staff who report incidents and near-misses, rather
than treating reports as confessions.
● Respect for Every Department Equally: Apply the same rigorous audit standard regardless of
departmental seniority or influence.
● Equal Improvement Standards: Ensure every department, not only high-visibility ones, receives
genuine quality attention.
2. TIMELINESS
Definition
Recognizing and responding to significant adverse events and identified systemic risks within timeframes that
protect patients, while never rushing the rigorous methodology that requires its own, uncompressed time.
Why Timeliness Is a Patient Safety Issue — and Why It Cuts Both Ways
A significant systemic risk left unaddressed for months continues to expose every patient who passes through
that process to preventable harm. Yet the opposite lesson applies equally: rushing an RCA to produce a fast
conclusion is precisely the shortcut that can miss the true systemic cause, producing a corrective action that
addresses a symptom rather than the actual failure. Timeliness in Quality Management means responding to
urgent risk promptly while refusing to compress the rigorous investigation that requires its full, uncompressed
time.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 24
Quality Management Timeliness Standards
● Sentinel event RCA initiation: prompt upon recognition, without avoidable delay.
● Investigation rigour: full, uncompressed methodology, never rushed to produce a faster but less
accurate conclusion.
● Corrective action implementation and verification: within defined timeframes, tracked to genuine
completion.
3. ACCURACY
Definition
Applying every quality methodology exactly, tracing every investigation to its genuine systemic cause, and
reporting every quality indicator precisely, sustained without deviation across every audit and investigation.
Why Accuracy Is Non-Negotiable in Quality Management
An inaccurate root cause analysis can produce a corrective action that fixes the wrong problem, leaving the
true systemic risk in place to harm another patient. Accuracy in Quality Management, sustained across
methodology and measurement alike, is what separates a quality system that genuinely protects patients from
one that merely appears to.
Areas Requiring Quality Management Accuracy
● Root Cause Analysis: Every investigation must trace the causal chain to its genuine systemic root, not
stop prematurely.
● Corrective Action Verification: Every corrective action must be verified genuinely implemented and
effective, not merely documented as complete.
● Quality Indicator Data: Every reported metric must accurately reflect genuine institutional
performance.
● Documentation: Every quality record must accurately and completely reflect the methodology applied
and its findings.
4. COMPASSION
Definition
Recognizing that every staff member involved in an adverse event is carrying their own genuine distress, and
that a quality system built on compassion, not punishment, produces more honest reporting and genuinely
better outcomes.
How the Quality Management Team Demonstrates Compassion
● Support Staff Through Investigation: Recognize the “second victim” experience of staff involved in
adverse events.
● Build a Genuinely Non-Punitive Culture: Protect honest reporters from retaliation, in practice as well
as policy.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 25
● Remember the Patient Behind Every Audit: Every quality metric represents real patients whose safety
depends on genuine improvement.
● Extend Compassion to Overburdened Departments: Acknowledge genuine resource constraints while
still holding standards.
5. ACCOUNTABILITY
Definition
Taking full professional responsibility for every investigation finding, every corrective action verification, and
every quality indicator reported by the Quality Management team.
Quality Management Accountability Standards
● Every investigation, audit, and corrective action is documented with the responsible team member's
identification.
● Never allow a known systemic risk or unverified corrective action to go unaddressed.
● Report institutional quality gaps honestly to leadership, even when uncomfortable.
● Participate in meta-review of the quality system's own performance with complete honesty.
● Participate in accreditation surveys with accurate, complete quality management records.
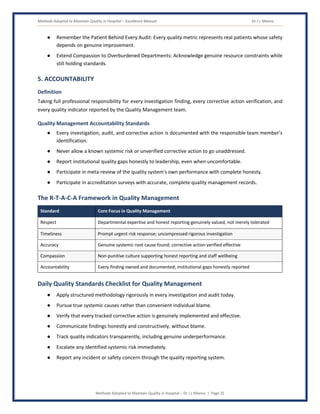
The R-T-A-C-A Framework in Quality Management
Standard Core Focus in Quality Management
Respect Departmental expertise and honest reporting genuinely valued, not merely tolerated
Timeliness Prompt urgent risk response; uncompressed rigorous investigation
Accuracy Genuine systemic root cause found; corrective action verified effective
Compassion Non-punitive culture supporting honest reporting and staff wellbeing
Accountability Every finding owned and documented; institutional gaps honestly reported
Daily Quality Standards Checklist for Quality Management
● Apply structured methodology rigorously in every investigation and audit today.
● Pursue true systemic causes rather than convenient individual blame.
● Verify that every tracked corrective action is genuinely implemented and effective.
● Communicate findings honestly and constructively, without blame.
● Track quality indicators transparently, including genuine underperformance.
● Escalate any identified systemic risk immediately.
● Report any incident or safety concern through the quality reporting system.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 26
In Hospital Quality Management, patient safety is measured across the entire system rather than any
single encounter — a patient experiences it not as any one interaction, but as the reliable, invisible
infrastructure ensuring every department's good intentions actually and consistently reach them,
regardless of which staff are on duty that day.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 27
CHAPTER 6: CONFIDENTIALITY, PRIVACY, AND INFORMATION
SECURITY
Quality Management involves particularly sensitive information — adverse event details, individual staff
performance data, and pre-decisional institutional quality gaps — requiring heightened confidentiality
discipline throughout investigation, audit, and reporting.
1. Privacy in Quality Investigation
Responsibilities
● Conduct RCA interviews and investigation discussions in as private a setting as available.
● Never discuss one department's or individual's investigation findings within earshot of unauthorized
staff.
● Apply particular discretion for individual staff performance information within investigations.
2. Confidentiality of Sensitive Findings
Overview
Adverse event investigation findings and pre-decisional quality gap data carry particular legal and institutional
sensitivity requiring heightened discretion.
Responsibilities
● Handle adverse event investigation information with heightened confidentiality per institutional and
legal peer-review protection requirements.
● Communicate only the necessary information to the wider institution, respecting appropriate
confidentiality protections.
3. Data and Information System Confidentiality
Responsibilities
● Access only the incident and quality records necessary for current responsibilities.
● Never discuss investigation or individual performance information with anyone outside the legitimate
quality review process.
● Follow hospital IT and cybersecurity policy for all quality and incident reporting information system
access.
● Never leave quality management workstations unlocked or logged in when unattended.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 28
4. Cybersecurity of Quality and Incident Reporting Systems
Why Cybersecurity Is a Patient Safety Issue
Quality and incident reporting information systems store sensitive investigation and performance data. A
compromised system risks both sensitive data breach and, if it discourages honest reporting due to perceived
insecurity, the loss of the honest information every quality method depends upon.
Responsibilities
● Use only authorized, unique login credentials for all quality and incident reporting system access.
● Never share login credentials with colleagues, regardless of workload pressure.
● Never connect personal devices to hospital clinical networks without IT authorization.
● Report any suspected unauthorized access or cybersecurity anomaly to IT security immediately.
5. Confidentiality for High-Profile Investigations
Responsibilities
● Maintain the same confidentiality standard for high-profile or media-sensitive investigations as for
every other investigation.
● Never disclose investigation details, findings, or individual identity to media or unauthorized persons.
Confidentiality Checklist for the Quality Management Team
● Conduct investigation interviews with maximum available privacy.
● Handle adverse event and individual performance information with heightened discretion.
● Use only authorized credentials for quality and incident reporting information systems.
● Never connect personal devices to hospital clinical networks without IT authorization.
In Quality Management, confidentiality must be actively maintained for information carrying particular
legal and institutional weight — adverse event findings and individual performance data — protecting both
the individuals involved and the honest reporting culture every quality method depends upon.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 29
CHAPTER 7: STANDARD OPERATING PROCEDURES (SOPs) FOR QUALITY
MANAGEMENT
Objectives of Quality Management SOPs
● Ensure consistent, rigorous application of quality methodology across every department.
● Minimize harm through systematic, documented investigation and improvement protocols.
● Support NABH/JCI/ISO accreditation compliance for hospital-wide quality standards.
● Provide a defensible framework for institutional accountability and continuous improvement.
SOP 1: PDCA/PDSA Improvement Cycle Application
Purpose
To ensure structured, verifiable improvement rather than unstructured or unverified change.
Procedure
● Step 1: Plan — define the specific problem and a testable, measurable improvement hypothesis.
● Step 2: Do — implement the change on a small, controlled scale.
● Step 3: Check/Study — measure the actual result against the predicted result honestly.
● Step 4: Act — standardize the change if successful, or revise and cycle again if not; document the
complete cycle.
Quality Standards
● 100% of significant improvement initiatives apply a documented PDCA/PDSA cycle.
SOP 2: FMEA for Proactive Risk Identification
Purpose
To identify and mitigate risk before it causes actual patient harm.
Procedure
● Step 1: Map the Process — map every step of the high-risk process under review.
● Step 2: Identify Failure Modes — identify every potential point of failure.
● Step 3: Score and Prioritize — score by severity, likelihood, and detectability.
● Step 4: Redesign and Document — redesign the highest-risk points and document the complete
analysis.
Quality Standards
● 100% of newly implemented high-risk processes receive documented FMEA before rollout.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 30
SOP 3: Root Cause Analysis Following a Sentinel Event
Purpose
To find the true systemic cause of a significant adverse event.
Procedure
● Step 1: Convene the Team Promptly — assemble a multidisciplinary team without avoidable delay.
● Step 2: Apply Structured Technique — apply the five whys, fishbone diagram, or equivalent structured
method.
● Step 3: Distinguish Systemic Cause from Individual Error — trace the causal chain to its genuine
systemic root.
● Step 4: Document — document the complete investigation, findings, and rationale.
Quality Standards
● 100% of qualifying sentinel events receive documented, rigorous RCA.
SOP 4: Corrective and Preventive Action Development and Verification
Purpose
To ensure investigation findings translate into genuine, verified change.
Procedure
● Step 1: Develop Specific Actions — develop specific, assigned, time-bound corrective and preventive
actions.
● Step 2: Implement — implement the action per the assigned timeline.
● Step 3: Verify Genuine Effectiveness — verify genuine implementation and measure actual
effectiveness.
● Step 4: Document — document the complete CAPA cycle from development through verification.
Quality Standards
● 100% of CAPAs verified genuinely implemented and effective, not merely documented as complete.
SOP 5: Clinical Audit and Benchmarking
Purpose
To reveal genuine performance gaps against defined standards and peer benchmarks.
Procedure
● Step 1: Define Standards — define clear, evidence-based audit standards.
● Step 2: Apply Systematic Audit — apply the audit consistently and objectively.
● Step 3: Benchmark — compare institutional performance against national/international data.
● Step 4: Document and Act — document findings and initiate improvement action for identified gaps.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 31
Quality Standards
● 100% of scheduled clinical audits completed with documented findings and action.
SOP 6: Incident and Near-Miss Reporting
Purpose
To maintain the honest reporting culture every other quality method depends upon.
Procedure
● Step 1: Maintain Accessible Reporting — maintain an accessible, fair, non-punitive reporting system.
● Step 2: Apply Systematic Review — review every report for pattern and systemic significance.
● Step 3: Provide Feedback — provide feedback to reporters on outcome, sustaining trust in the system.
● Step 4: Document — document the complete review and any resulting action.
Quality Standards
● Near-miss reporting rate tracked and trending toward increase, reflecting genuine reporting culture
health.
SOP 7: Quality Indicator Definition and Dashboard Reporting
Purpose
To translate abstract quality goals into concrete, trackable measures.
Procedure
● Step 1: Define Clear Indicators — define measurable, clinically meaningful indicators per department.
● Step 2: Collect Data Rigorously — apply consistent, accurate data collection methodology.
● Step 3: Maintain Transparent Dashboards — maintain regularly updated, accessible dashboards.
● Step 4: Document — document indicator definitions, data sources, and any methodology change.
Quality Standards
● 100% of departments maintain documented, current quality indicator tracking.
SOP 8: Accreditation Readiness and Standards Compliance
Purpose
To maintain continuous, not merely pre-survey, accreditation compliance.
Procedure
● Step 1: Apply Continuous Self-Assessment — apply ongoing internal assessment against accreditation
standards.
● Step 2: Identify and Close Gaps — identify and remediate any gap promptly, year-round.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 32
● Step 3: Maintain Documentation Readiness — maintain complete, audit-ready documentation
continuously.
● Step 4: Document — document the complete readiness assessment and remediation activity.
Quality Standards
● 100% of accreditation standards maintained in continuous, not only pre-survey, compliance.
SOP 9: Mortality and Morbidity Review
Purpose
To extract genuine learning from mortality and significant morbidity events.
Procedure
● Step 1: Convene Regular Review — convene structured, regular M&M review sessions.
● Step 2: Apply Honest, Non-Punitive Discussion — apply a genuinely open, blame-free discussion
format.
● Step 3: Extract and Disseminate Learning — extract genuine learning and disseminate it appropriately.
● Step 4: Document — document the complete review and any resulting action.
Quality Standards
● 100% of qualifying cases receive documented M&M review with disseminated learning.
SOP 10: Patient Feedback and Satisfaction Measurement
Purpose
To incorporate genuine patient perspective into institutional quality improvement.
Procedure
● Step 1: Apply Systematic Feedback Collection — apply consistent, representative patient feedback
collection.
● Step 2: Analyse for Genuine Patterns — analyse feedback for genuine, actionable patterns.
● Step 3: Close the Loop — translate genuine patterns into improvement action.
● Step 4: Document — document the complete feedback cycle from collection through action.
Quality Standards
● 100% of significant patient feedback themes result in documented improvement consideration.
Quality Management SOP Daily Compliance Checklist
● Structured methodology applied rigorously to every investigation and audit today.
● Any identified systemic risk escalated immediately.
● Every tracked corrective action verified for genuine implementation status.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 33
● Any incident or safety concern reported through the appropriate system.
SOPs for Quality Management are the operating instructions for the systematic infrastructure beneath
every other department's excellence. When followed consistently, they are the foundation ensuring quality
in this hospital never depends on individual heroism alone.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 34
CHAPTER 8: COMMUNICATION WITH SPECIAL GROUPS
The Quality Management team communicates across a distinctive range of circumstances — from a clinical
department receiving difficult audit feedback, to hospital leadership requiring honest institutional gap
disclosure, to an accreditation surveyor assessing compliance, to a staff member navigating the aftermath of
an adverse event. Excellent quality management practice requires adapted communication for each of these
circumstances.
1. Clinical Departments Receiving Audit Feedback
Communication Guidelines
● Frame findings around systemic process, never individual blame, unless genuine misconduct is
involved.
● Collaborate genuinely on corrective action rather than imposing solutions unilaterally.
2. Hospital Leadership
Communication Guidelines
● Communicate genuine institutional gaps honestly, even when uncomfortable.
● Present data with appropriate context and honest acknowledgment of limitations.
3. Accreditation Surveyors
Communication Guidelines
● Present quality systems and documentation honestly and completely.
● Communicate genuine, ongoing improvement work rather than only pre-survey preparation.
4. Staff Members Involved in an Adverse Event
Overview
Staff involved in an adverse event frequently experience genuine distress — the “second victim” phenomenon
— requiring particular compassion alongside rigorous, honest investigation.
Communication Guidelines
● Acknowledge the staff member's genuine distress with authentic compassion.
● Communicate that the investigation's purpose is systemic learning, never individual punishment.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 35
5. Department Quality Champions
Communication Guidelines
● Communicate quality methodology and rationale clearly, building genuine capability rather than
dependency.
● Support champions with resources and recognition for their genuine contribution.
6. Patients and Families Providing Feedback
Communication Guidelines
● Communicate genuine appreciation for feedback, whether positive or critical.
● Close the loop by communicating what action, if any, resulted from their feedback.
7. External Benchmarking and Peer Institutions
Communication Guidelines
● Communicate institutional data honestly for genuine, mutually beneficial benchmarking.
8. Regulatory and Public Health Authorities
Communication Guidelines
● Communicate required reportable events and compliance data accurately and within regulatory
timeframes.
Universal Quality Management Communication Principles
● Communicate honestly, framing findings around systems rather than blame.
● Respond to every significant risk with appropriate urgency.
● Always confirm genuine understanding and commitment, particularly for corrective action.
● Document every significant communication completely.
The Quality Management team that communicates with equal skill toward a department receiving difficult
feedback and leadership hearing an uncomfortable gap serves every stakeholder at maximum impact —
honest, blame-free communication delivered alongside the genuine partnership that turns oversight into
improvement.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 36
CHAPTER 9: HANDLING DIFFICULT SITUATIONS
Common Difficult Situations for the Quality Management Team
● A department resists or deflects audit findings defensively.
● An RCA reveals a systemic cause implicating senior leadership or institutional resourcing.
● A corrective action is documented as complete but appears not genuinely implemented.
● A staff member fears retaliation for honest incident reporting.
● An accreditation gap is discovered close to a scheduled survey.
● A colleague's investigation appears to stop at convenient blame rather than genuine systemic cause.
● Quality indicator data appears manipulated or selectively reported.
● A significant adverse event involves potential legal or media exposure.
● Resource constraints genuinely limit a department's ability to implement a needed corrective action.
● Two departments disagree about where a systemic responsibility genuinely lies.
Core Principles for Handling Difficult Situations
1. Methodological Integrity Is Never Compromised
In every difficult situation, rigorous, honest methodology drives every decision — no institutional pressure,
however genuine, justifies a shortcut in investigation or verification.
2. Apply Standardized Protocols Under Pressure
Departmental resistance and institutional pressure are precisely when standardized methodology matters
most — resist the temptation to soften findings under pressure.
3. Escalate Immediately and Persistently
A genuine systemic risk is not resolved until it reaches someone who can act on it — escalate through
alternative channels if the first attempt does not produce a response.
4. Document Everything
Every difficult situation must be contemporaneously documented — what was found, what was
communicated, what decisions were made, and by whom.
Handling Departmental Resistance to Audit Findings
Steps
● Present the evidence calmly and completely, reframing around genuine systemic improvement.
● Invite genuine departmental input into corrective action design, building ownership.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 37
Handling an RCA Implicating Leadership or Resourcing
Steps
● Report the finding honestly and completely, regardless of who or what it implicates.
● Escalate through appropriate governance channels for institutional-level resolution.
Handling an Apparently Unimplemented Corrective Action
Steps
● Verify genuine implementation status directly, not merely documented status.
● Escalate the gap honestly if genuine implementation has not occurred.
Handling Fear of Retaliation for Honest Reporting
Steps
● Reaffirm and enforce the genuinely non-punitive reporting policy.
● Investigate and address any actual retaliation immediately and seriously.
Handling an Accreditation Gap Close to Survey
Steps
● Communicate the gap honestly to leadership immediately.
● Apply urgent, genuine remediation rather than superficial, survey-focused fixes.
Handling Concern About a Colleague's Investigation Rigour
Steps
● Address the concern directly and professionally with the colleague.
● Escalate to department leadership if the concern involves a systemic pattern.
Handling Suspected Data Manipulation
Steps
● Investigate the data integrity concern thoroughly and objectively.
● Escalate confirmed manipulation through appropriate institutional and ethical channels.
Handling a Significant Event with Legal/Media Exposure
Steps
● Apply the same rigorous, honest investigation methodology regardless of external exposure.
● Coordinate closely with legal and communications teams while preserving investigation integrity.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 38
Handling Genuine Resource Constraints Limiting Corrective Action
Steps
● Communicate the constraint honestly to leadership with clear patient safety justification for
resourcing.
● Identify genuine interim mitigation while advocating for full resolution.
Handling Interdepartmental Disagreement on Systemic Responsibility
Steps
● Apply objective, evidence-based analysis rather than favouring either department.
● Facilitate a genuine joint resolution process centred on patient safety, not departmental territory.
The CALM Model for Quality Management
● C – Control the immediate systemic risk.
● A – Acknowledge the situation accurately, including genuine institutional discomfort.
● L – Lead with evidence — methodology, data, and accreditation standards.

● M – Manage through documented escalation channels when needed.
Difficult situations in Quality Management are always, ultimately, tests of whether methodological
integrity holds firm under institutional or departmental pressure. The team that never softens a finding,
escalates persistently, and communicates honestly even when uncomfortable is fulfilling the highest
professional obligation of this discipline.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 39
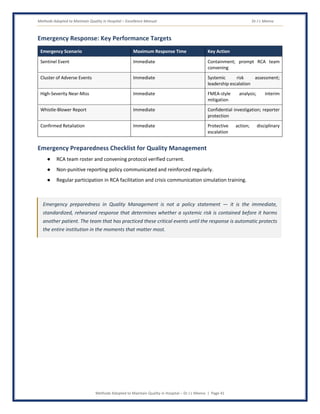
CHAPTER 10: EMERGENCY RESPONSE — CRITICAL QUALITY AND
SAFETY EVENTS
Overview
Certain events demand the Quality Management team's most immediate, standardized, and rehearsed
response — scenarios where the difference between a coordinated, protocol-driven response and an
improvised one is measured directly in whether a systemic risk is contained before it harms another patient.
Critical Events Requiring Immediate Response
● A sentinel event (unexpected death or serious harm unrelated to the natural course of illness).
● A cluster of similar adverse events suggesting a systemic failure.
● A near-miss revealing a high-severity, high-likelihood systemic risk.
● A significant data integrity or reporting concern.
● An imminent accreditation survey with a known unresolved gap.
● A significant patient safety concern raised by media or regulatory inquiry.
● A whistle-blower report of a serious quality or safety concern.
● A significant information system failure affecting quality or incident reporting data.
● A confirmed instance of retaliation against an honest reporter.
● An FMEA revealing an unacceptably high-risk existing process.
1. Sentinel Event
Immediate Response
● Apply immediate event containment and patient safety stabilization coordination with the clinical
team.
● Convene the RCA team promptly per protocol.
2. Cluster of Similar Adverse Events
Steps
● Apply immediate systemic risk assessment across the affected process.
● Escalate to leadership immediately given the pattern's institutional significance.
3. High-Severity Near-Miss
Steps
● Apply immediate FMEA-style analysis of the revealed risk.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 40
● Implement interim risk mitigation while permanent correction is developed.
4. Data Integrity Concern
Steps
● Apply immediate, objective investigation of the data integrity concern.
● Escalate confirmed findings through appropriate institutional and ethical channels.
5. Unresolved Gap Before Accreditation Survey
Steps
● Apply immediate, genuine remediation, not superficial fixes.
● Communicate the gap and remediation plan honestly to leadership and survey preparation team.
6. Media or Regulatory Inquiry
Steps
● Coordinate immediately with legal and communications while preserving investigation integrity.
● Apply the same rigorous, honest methodology regardless of external scrutiny.
7. Whistle-Blower Report
Steps
● Apply immediate, confidential, and objective investigation.
● Protect the reporter from any retaliation throughout the process.
8. Quality Information System Failure
Steps
● Apply immediate contingency reporting and data protection measures.
● Coordinate with IT for urgent restoration and data integrity verification.
9. Confirmed Retaliation Against a Reporter
Steps
● Apply immediate protective action for the affected reporter.
● Escalate through appropriate disciplinary and institutional channels without delay.
10. FMEA Revealing Unacceptable Existing Risk
Steps
● Apply immediate interim risk mitigation for the existing process.
● Escalate for urgent redesign and resource allocation.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 41
Emergency Response: Key Performance Targets
Emergency Scenario Maximum Response Time Key Action
Sentinel Event Immediate Containment; prompt RCA team
convening
Cluster of Adverse Events Immediate Systemic risk assessment;
leadership escalation
High-Severity Near-Miss Immediate FMEA-style analysis; interim
mitigation
Whistle-Blower Report Immediate Confidential investigation; reporter
protection
Confirmed Retaliation Immediate Protective action; disciplinary
escalation
Emergency Preparedness Checklist for Quality Management
● RCA team roster and convening protocol verified current.
● Non-punitive reporting policy communicated and reinforced regularly.
● Regular participation in RCA facilitation and crisis communication simulation training.
Emergency preparedness in Quality Management is not a policy statement — it is the immediate,
standardized, rehearsed response that determines whether a systemic risk is contained before it harms
another patient. The team that has practiced these critical events until the response is automatic protects
the entire institution in the moments that matter most.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 42
CHAPTER 11: DIGITAL COMPETENCY FOR THE QUALITY MANAGEMENT
TEAM
Objectives
● Enable the Quality Management team to use incident reporting, audit, and dashboard systems
accurately, securely, and efficiently.
● Leverage technology to improve pattern detection, quality tracking, and institutional transparency.
● Manage the cybersecurity of quality and incident reporting information systems as a core patient
safety function.
Core Digital Competencies for the Quality Management Team
1. Incident Reporting Systems
Essential Skills
● Use incident reporting systems accurately for intake, categorization, and pattern analysis.
2. Quality Dashboard and Data Visualization Tools
Essential Skills
● Use dashboard and visualization tools accurately to present transparent, meaningful quality data.
3. Electronic Medical Record (EMR) / Hospital Information System (HIS)
Essential Skills
● Extract and analyse relevant clinical data accurately for audit and investigation purposes.
4. Statistical Analysis Tools
Essential Skills
● Use statistical analysis tools accurately for benchmarking and Six Sigma process variation analysis.
5. AI-Assisted Pattern Detection Tools
Awareness
● AI-assisted tools are increasingly applied to detect patterns across large volumes of incident and
quality data.
● Understand and appropriately leverage these tools while maintaining independent human judgment
— AI tools are decision-support, not a substitute for genuine investigative rigour.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 43
6. Accreditation Documentation Management Systems
Essential Skills
● Use documentation management systems accurately to maintain continuous accreditation readiness.
7. Cybersecurity and Information Security
Personal Digital Security Responsibilities
● Use unique, strong credentials for all quality and incident reporting information system logins.
● Lock or log out of workstations whenever stepping away, even briefly.
● Never connect personal devices to hospital clinical networks.
● Report all cybersecurity anomalies to IT security immediately.
Digital Competency Checklist
● Navigate incident reporting, dashboard, and documentation management systems for all core
functions without assistance.
● Apply accurate, complete investigation and audit documentation.
● Apply basic cybersecurity practices to all clinical system access.
● Know the downtime procedure for incident reporting/quality system failure.
Digital competency for the Quality Management team is the ability to integrate rigorous methodological
judgment with the incident reporting, dashboard, and analytical systems that modern quality
management increasingly depends upon — using technology to extend, never replace, the honest
investigative rigour that defines this discipline.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 44
CHAPTER 12: DAILY QUALITY MANAGEMENT CHECKLIST
Objectives
● Provide a structured daily framework for rigorous, methodical quality oversight.
● Ensure every investigation, audit, and tracking obligation is addressed every day.
● Support accurate institutional documentation and performance data quality.
PART A: START-OF-DAY CHECKLIST
Personal and Professional Readiness
● Appropriate professional attire and ID badge displayed.
● Incident reporting and quality dashboard systems functional and accessible.
Priority Review
● Review any overnight incident reports or escalations requiring action.
● Review status of active RCA and CAPA investigations.
PART B: INVESTIGATION AND AUDIT CHECKLIST
● Structured methodology applied rigorously to every active investigation today.
● Scheduled clinical audits progressing per plan.
PART C: CORRECTIVE ACTION CHECKLIST
● Every tracked corrective action reviewed for genuine implementation status.
● Any overdue corrective action escalated appropriately.
PART D: QUALITY INDICATOR CHECKLIST
● Quality indicator data reviewed for accuracy and completeness.
● Dashboards updated and accessible to relevant stakeholders.
PART E: ACCREDITATION READINESS CHECKLIST
● Continuous accreditation self-assessment activity reviewed.
● Any identified compliance gap tracked toward remediation.
PART F: SAFETY AND INCIDENT CHECKLIST
● Any new incident, near-miss, or systemic risk reviewed and addressed.
● Non-punitive reporting culture reinforced in every interaction today.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 45
PART G: END-OF-DAY CHECKLIST
● All investigation and audit records updated and complete for the day.
● Structured handover prepared for the next working day.
● Information systems securely logged out.
Daily Self-Assessment for the Quality Management Team
● Did we apply structured methodology rigorously in every investigation and audit today?
● Did we pursue true systemic causes rather than convenient individual blame?
● Did we verify that corrective actions are genuinely implemented and effective?
● Did we communicate findings honestly and constructively, without blame?
● Did we treat every department as a genuine partner in improvement today?
A consistent, structured daily routine — from start-of-day priority review to end-of-day handover —
transforms individual methodological rigour into a systemic quality programme that operates reliably
across every department, ensuring excellence never depends on individual heroism alone.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 46
CHAPTER 13: KEY PERFORMANCE INDICATORS (KPIs) FOR QUALITY
MANAGEMENT
Objectives
● Measure investigation rigour, corrective action effectiveness, and institutional quality performance
objectively.
● Enable data-driven continuous improvement of the quality system itself.
● Support NABH/JCI/ISO accreditation standards for hospital-wide quality management.
● Demonstrate the value and patient safety impact of Quality Management to institutional leadership.
Categories of Quality Management KPIs
1. Investigation and Methodology KPIs
KPI Definition Target
RCA Completion Rate % of qualifying sentinel events with completed,
documented RCA
100%
RCA Timeliness % of RCAs initiated within defined timeframe of event
recognition
100%
FMEA Completion Rate % of newly implemented high-risk processes with
documented FMEA
100%
2. Corrective Action KPIs
KPI Definition Target
CAPA Verified Effectiveness Rate % of CAPAs verified genuinely implemented and
effective
100%
CAPA Timeliness % of CAPAs completed within assigned timeframe ≥ 90%
3. Reporting Culture KPIs
KPI Definition Target
Near-Miss Reporting Rate Near-misses reported per defined patient volume,
trended over time
Trending upward
(reflects healthy
reporting culture)
Reporter Feedback Rate % of incident reporters receiving documented
outcome feedback
100%
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 47
4. Audit and Accreditation KPIs
KPI Definition Target
Clinical Audit Completion Rate % of scheduled audits completed with documented
findings
100%
Continuous Accreditation Compliance % of standards in continuous, documented compliance 100%
5. Outcome and Governance KPIs
KPI Definition Target
Preventable Adverse Event Rate Rate of preventable adverse events per defined patient
volume
Trending downward
year over year
Patient Satisfaction Score % positive patient feedback on overall care experience ≥ 85%
Department Quality Champion
Coverage
% of departments with an active, trained quality
champion
100%
Using KPIs for Continuous Improvement
● Review all Quality Management KPIs regularly at institutional governance meetings.
● Analyse investigation, corrective action, and reporting culture trends to identify targeted programme
improvements.
● Use accreditation compliance data to sustain continuous readiness rather than pre-survey scrambling.
● Present KPI data to hospital leadership to demonstrate the patient safety impact of the quality system
itself.
Quality Management KPIs translate the invisible infrastructure beneath every department's excellence into
institutional accountability — demonstrating that the investment in rigorous methodology, honest
investigation, and verified corrective action is a measurable, trackable programme that ensures quality is
never left to individual heroism alone.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 48
CHAPTER 14: TOP 20 DO'S & TOP 20 DON'TS FOR QUALITY
MANAGEMENT
Introduction
The Quality Management team builds the systematic infrastructure beneath every other department's
excellence. Their daily professional decisions — about methodological rigour, honest investigation, and
genuine corrective action — determine whether quality in this hospital is a designed system or a hopeful
accident. These Do's and Don'ts provide the practical daily architecture of Quality Management excellence.
TOP 20 DO'S FOR QUALITY MANAGEMENT
● 1. Apply the Full PDCA/PDSA Cycle — Plan, Do, Check, Act, every improvement, every time.
● 2. Apply FMEA Proactively — Before a new high-risk process goes live, not after harm occurs.
● 3. Trace Every RCA to Its True Systemic Cause — Never stop at convenient individual blame.
● 4. Verify Every CAPA Is Genuinely Implemented — Not merely documented as complete.
● 5. Frame Findings Around Systems, Not People — Every time, in every report.
● 6. Protect Honest Reporters — From any retaliation, in practice as well as policy.
● 7. Maintain Continuous Accreditation Readiness — Year-round, not only before survey.
● 8. Communicate Genuine Institutional Gaps to Leadership — Even when uncomfortable.
● 9. Build Genuine Departmental Partnership — Never treat departments as adversaries.
● 10. Apply the Same Rigour to Every Department — Regardless of seniority or influence.
● 11. Debrief After Every Significant Event — Consolidate learning while it is fresh.
● 12. Provide Structured Handover for Every Transfer — SBAR or equivalent, every time.
● 13. Present Data Honestly, Including Underperformance — Transparency builds trust.
● 14. Report Every Near-Miss Honestly — Including within the quality team itself.
● 15. Support Staff Through the “Second Victim” Experience — Genuine compassion, always.
● 16. Benchmark Against Genuine External Standards — Not only internal comparisons.
● 17. Involve Frontline Staff in Redesigning Their Own Processes — Genuine collaboration.
● 18. Close the Loop on Patient Feedback — Communicate what action resulted, every time.
● 19. Escalate Every Identified Systemic Risk Immediately — Without exception.
● 20. Continue Learning — Quality methodology evolves. The team that does not learn continuously
applies yesterday's methods to today's problems.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 49
TOP 20 DON'TS FOR QUALITY MANAGEMENT
● 1. Don't Skip a Structured Methodology Step — To reach a faster, more convenient conclusion.
● 2. Don't Stop an RCA at Individual Blame — When a genuine systemic cause remains unexamined.
● 3. Don't Accept a CAPA as Complete Without Verification — Documentation is not proof of
effectiveness.
● 4. Don't Frame Findings in Blaming Language — It discourages the honest reporting every method
depends on.
● 5. Don't Allow Retaliation Against Honest Reporters — Ever, for any reason.
● 6. Don't Let Accreditation Readiness Lapse Between Surveys — Continuous compliance, always.
● 7. Don't Hide Institutional Gaps from Leadership — Honesty even when uncomfortable.
● 8. Don't Treat Departments as Adversaries — Genuine partnership, always.
● 9. Don't Apply Inconsistent Rigour Across Departments — The same standard, regardless of influence.
● 10. Don't Skip Team Debriefing After a Critical Event — Unprocessed events repeat their gaps.
● 11. Don't Hand Over Investigations Informally — Structure protects against critical omissions.
● 12. Don't Overstate Data Certainty — Honest limitations, always.
● 13. Don't Hide or Minimize a Quality Team Near-Miss — Including your own.
● 14. Don't Dismiss Staff Distress After an Adverse Event — The “second victim” experience is real.
● 15. Don't Rely Only on Internal Comparison — Genuine external benchmarking matters.
● 16. Don't Redesign Processes Without Frontline Input — Genuine collaboration, always.
● 17. Don't Collect Patient Feedback Without Closing the Loop — Silence erodes trust.
● 18. Don't Delay Escalating a Known Systemic Risk — Every day of delay is continued exposure.
● 19. Don't Let Compliance Theatre Replace Genuine Improvement — The goal is real change, not
paperwork.
● 20. Don't Practice Outside Current Quality Methodology — Personal habit or outdated method must
never override current best practice.
Quality Management Golden Rules
● Apply the full improvement cycle — Plan, Do, Check, Act, every time.
● Find the true systemic cause — never settle for convenient blame.
● Verify genuine implementation — documentation is not proof.
● Frame every finding around systems — never around individual blame.
● Protect honest reporters — without exception.
● Maintain readiness continuously — not only before survey.
● Communicate gaps honestly — even when uncomfortable.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 50
● Build genuine partnership — never adversarial oversight.
● Report every near-miss — honestly, including your own.
● Never stop learning — today's quality methodology is not yesterday's.
Daily Commitment Statement
“Today, I will apply structured methodology rigorously, pursue the true systemic cause rather than convenient
blame, verify that corrective actions are genuinely effective, and communicate honestly and constructively —
because quality is never an accident, it is the sum of methods applied consistently, by everyone, every single
day.”
The Top 20 Do's and Top 20 Don'ts are the daily professional architecture of Quality Management
excellence — each shaped by the understanding that this discipline builds the invisible infrastructure
beneath every other department, and that there are no minor lapses when the system built loosely today
is the preventable harm discovered tomorrow.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 51
CHAPTER 15: QUALITY MANAGEMENT PROFESSIONAL PLEDGE
Introduction
A Quality Management Professional Pledge is a formal, collective commitment to uphold the highest standards
of methodological rigour, honest investigation, and genuine corrective action. It serves as a daily affirmation
that quality in this hospital is never left to individual heroism alone, but built, methodically, into the system
itself.
Official Quality Management Professional Pledge
“We solemnly pledge that as the Hospital Quality Management team, we will fulfil our collective and individual
responsibilities with the highest standards of methodological rigour, honesty, and unwavering commitment to
building the systematic infrastructure beneath every other department's excellence.
We will apply the PDCA/PDSA cycle systematically to every improvement, apply FMEA proactively to identify
risk before it causes harm, and conduct every root cause analysis with the rigour and courage to find the true
systemic cause, never settling for the convenient blame of the nearest individual.
We will develop and verify genuine, effective corrective and preventive action for every significant finding,
ensuring documentation reflects reality rather than substituting for it, and we will frame every finding around
systems and process, never around individual blame, protecting the honest reporting culture every other
method depends upon.
We will maintain continuous, year-round accreditation readiness, communicate genuine institutional gaps
honestly to leadership even when uncomfortable, and treat every department as a genuine partner in
improvement, never as an adversary to be policed.
We will report every incident and near-miss honestly, including within our own team, support every staff
member navigating the distress of an adverse event with genuine compassion, and continuously expand our
knowledge and skill, knowing that quality methodology evolves and that the team that does not learn
continuously applies yesterday's methods to today's problems.
With unwavering methodological rigour, genuine partnership, and profound respect for every patient whose
safety depends on the system we build, we pledge to be the Quality Management team that proves quality is
never an accident, but the sum of methods applied consistently, by everyone, every single day.”
Daily Commitment Statement
“Today, we commit to applying rigorous methodology, pursuing true systemic causes, verifying genuine
corrective action, and building honest partnership with every department — because quality is never an
accident, it is the sum of methods applied consistently, by everyone, every single day.”
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 52
Core Values Reflected in the Pledge
1. Methodological Rigour
Structured, evidence-based methods applied consistently, never compressed or improvised under pressure.
2. Honest Investigation
True systemic causes pursued genuinely, never settling for convenient individual blame.
3. Genuine Verification
Corrective actions confirmed as truly implemented and effective, not merely documented as complete.
4. Blame-Free Communication
Findings framed around systems and process, protecting the honest reporting culture that sustains the entire
quality system.
5. Institutional Honesty
Genuine gaps communicated to leadership even when uncomfortable, never hidden or softened.
6. Accountability
Every finding owned and documented; every incident honestly reviewed.
7. Continuous Learning
Quality methodology evolves. Professional competence requires perpetual learning.
When the Pledge Should Be Recited
● At the beginning of every new Quality Management team member's appointment.
● At quality governance and institutional leadership meetings.
● At NABH/JCI/ISO accreditation preparation events.
● As a periodic collective affirmation, particularly following a significant institutional event.
Quality Management Oath of the Invisible System
“We pledge to build the invisible infrastructure beneath every department's excellence — finding true causes,
verifying genuine change, and proving that quality is a designed system, never an accident.”
Quality Management Signature Commitment
This pledge is recited collectively by the hospital-wide Quality Management team and may be individually
signed by:
Name: ___________________________
Role: Quality Manager / Quality Coordinator / Department Quality Champion
Department: Quality Management
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 53
Registration/Employee ID: _______________
Signature: ________________________
Date: ____________________________
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 54
CONCLUSION
There is a discipline in this hospital that operates beneath every other discipline: it does not treat a single
patient directly, yet its methods determine whether every other department's good intentions actually and
reliably reach the patients they serve. This manual has returned, again and again, to why methods matter more
than good intentions alone — a single dedicated clinician cannot make a hospital safe by will alone, but a
hospital built on rigorous quality methods can make every clinician's good intentions actually, reliably, and
sustainably reach every patient.
Throughout this manual, we have explored the full scope of Hospital Quality Management professional practice
— from the foundational PDCA/PDSA improvement cycle and proactive FMEA risk identification, through
honest root cause analysis and verified corrective action, to systematic clinical audit, transparent quality
indicator tracking, and the professional conduct that defines excellence across every category of quality work.
These responsibilities collectively define a discipline that demands both methodological rigour and the
diplomatic skill to make every department a genuine partner rather than an adversary.
The Importance of the Quality Management Team in Healthcare Quality
● The systematic improver — applying PDCA cycles that turn good intentions into consistent, verified
outcomes.
● The proactive risk-finder — applying FMEA that fixes dangerous processes before a patient is ever
exposed to them.
● The honest investigator — tracing every RCA to its true systemic cause, never settling for convenient
blame.
● The genuine verifier — confirming corrective actions are truly implemented and effective, not merely
documented.
● The transparent measurer — tracking quality indicators honestly, including genuine
underperformance.
● The honest reviewer — examining the quality system's own performance with the same rigour applied
to every other department.
Final Commitment
“As the Hospital Quality Management team, we commit to applying rigorous methodology, pursuing true
systemic causes, verifying genuine corrective action, and building honest partnership with every department
— because quality is never an accident, it is the sum of methods applied consistently, by everyone, every single
day.”
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 55
Final Motto
“Quality Is Never an Accident — It Is the Sum of Methods Applied Consistently, By Everyone, Every Single Day.”
Together, We Build the System That Makes Every Department's Good Intentions Reach Every Patient,
Every Single Time.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 56
REFERENCES
Global Accreditation and Regulatory Standards
● World Health Organization (WHO) – Global Patient Safety Action Plan 2021–2030 and Quality of Care
Framework.
● Joint Commission International (JCI) – JCI Accreditation Standards for Hospitals: Quality Improvement
and Patient Safety (QPS) Chapter.
● National Accreditation Board for Hospitals & Healthcare Providers (NABH, India) – Standards for
Hospital Quality Management (5th Edition).
Quality Methodology Standards
● International Society for Quality in Health Care (ISQua) – Guidelines and Principles for Healthcare
Quality Standards.
● International Organization for Standardization (ISO) – ISO 9001 Quality Management Systems —
Requirements.
Improvement and Risk Methodology Standards
● Institute for Healthcare Improvement (IHI) – Model for Improvement and PDSA Cycle Methodology.
● VA National Center for Patient Safety / Joint Commission – Root Cause Analysis and Failure Mode and
Effects Analysis Frameworks.
Patient Safety and Incident Reporting Standards
● World Health Organization (WHO) – Conceptual Framework for the International Classification for
Patient Safety.
● Agency for Healthcare Research and Quality (AHRQ) – Patient Safety Culture Survey and Non-Punitive
Reporting Guidelines.
Process Improvement Methodology Standards
● American Society for Quality (ASQ) – Lean and Six Sigma Methodology Guidelines for Healthcare
Applications.
Indian Regulatory and National Framework
● National Accreditation Board for Hospitals & Healthcare Providers (NABH), India – Hospital and
Healthcare Provider Accreditation Standards.
● Quality Council of India (QCI) – National Accreditation Board Guidelines.
● National Medical Commission (NMC) – Code of Medical Ethics Regulations Applicable to Institutional
Quality Governance.
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 57
Quality Improvement and Patient Safety Frameworks
● Institute for Healthcare Improvement (IHI) – Framework for Patient Safety and Quality Improvement
in Hospitals.
● World Health Organization – Global Patient Safety Action Plan 2021–2030.
Cybersecurity and Digital Health Records
● NIST Cybersecurity Framework – Applied to Healthcare Quality and Incident Reporting Information
Systems.
● HL7 International – Health Level Seven Data Interchange Standards.
This manual has been developed using internationally recognized principles and best practices from WHO
Global Patient Safety Action Plan, JCI Quality Improvement and Patient Safety Standards, NABH Hospital
Quality Management Standards, ISQua Quality Standards Guidelines, ISO 9001 Quality Management Systems,
IHI Model for Improvement, Joint Commission Root Cause Analysis and FMEA Frameworks, AHRQ Patient
Safety Culture Guidelines, ASQ Lean and Six Sigma Methodology, India's Quality Council of India Guidelines,
and applicable Indian statutory and regulatory requirements. Institutions should verify current versions of all
cited guidelines and regulatory requirements, as clinical protocols and accreditation standards are subject to
periodic revision.
ॐ जय माता द( ॐ
Methods Adopted to Maintain Quality in Hospital – Excellence Manual Dr J L Meena
Methods Adopted to Maintain Quality in Hospital – Dr J L Meena | Page 58
END OF MANUAL
Thank You
This manual has been prepared with the vision to empower the hospital-wide Quality Management team with
global standards, best practices, and professional guidance to build the systematic infrastructure beneath
every other department's excellence.
Our Commitment Continues
The journey of learning never ends. As quality methodology and accreditation standards evolve, our
commitment to methodological rigour, honest investigation, and genuine partnership must remain unwavering
— because the system built loosely today is the preventable harm discovered tomorrow.
Together, We Build Trust
Every improvement cycle applied rigorously, every root cause found honestly, every corrective action genuinely
verified, and every department treated as a true partner contributes to one greater purpose — a hospital
where excellence is a designed system, not a hopeful accident.
“Quality Is Never an Accident — It Is the Sum of Methods Applied Consistently, By Everyone,
Every Single Day.”
REMEMBER: Method is our discipline • Honesty is our investigation • Verification is our proof • Partnership
is our approach • Learning is our journey
Thank you for being a part of this vital mission. Your dedication makes a difference every day.
Dr J L Meena