History and Examination
of
Oral Cavity,Throat
&
Neck
Dr. Subrat Sanu
1st year Junior Resident
Dept. of E.N.T.
DMCH, Darbhanga
1. Name
2. Age
3. Sex
4. Religion
5. Social status
6. Occupation
7. Address
8. Chief complaints
9. History of present illness (HOPI)
10.Past History:- Drug History, Treatment history, Allergy
History
11.Personal History
12.Family History
13.Immunisation history
General points in History taking
● Name- identification,building rapport, maintaining records,
psychological benefits
● Age- young (Nasopharyngeal angiofibroma), Elderly
(Cancers),Neonate(Tongue tie,cleft palate), Children(Tonsillitis,Adenoid
● Sex- Female (Thyroid), Male (Laryngeal Ca, Cracked voice)
● Occupation- Teachers/Singers/Public speakers- Vocal nodules,
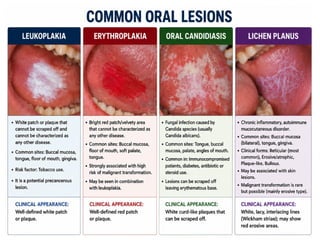
Hoarseness of voice. Tobacco exposure- Leukoplakia , OSMF,

Oral cancers
● Healthcare workers- Viral/bacterial pharyngitis
● Industry/Cement workers- Oral ulcers from
irritants,Chronic throat irritation, Pharyngitis
● Address- Urban/industrial area- Oral cancer, leukoplakia, Chronic
pharyngitis , GERD (d/t chemical,pollution & tobacco exposure)
● Rural/Village area- OSMF, chronic tonsillitis
● Overcrowded area- Oral candidiasis,Diphtheria,TB
lymphadenitis,Acute tonsillitis
Chief complaints
• In patient’s own words
• Chronological order:- as they occur according to severity and
for each complaint mention duration.
• Duration:- Short with pain - acute inflammatory
Long without pain – neoplastic
Long with slight pain – chronic inflammatory
Long with severe pain – malignant
• Throat :- Oral cavity, Oropharynx, Laryngopharynx Larynx and Neck
Chief Complaints in Oral Cavity
• Pain (site,onset,character,radiation,agg factors,relieving
factors,severity)
• Dry mouth (Xerostomia)- mouth breathing
• Bad smell (Halitosis) –poor hygiene,ulcers,post nasal drip
• Ulcer
• Loss of taste (Dysgeusia)
• Excess salivation - poor hygiene, ulcers
• Restricted tongue movement-Tongue tie (Ankyloglossia)
• Difficulty in opening mouth (Trismus) – SMF
• Swellings
• Cleft palate
• Bleeding gums - scurvy
Chief complaints in Oropharynx
• Sore throat
• F.B Sensation – allergy, post nasal drip, functional, malignancy
• Difficulty in swallowing (Dysphagia)
• Pain during swallowing (Odynophagia)
• Swelling
• ulcer
• Regurgitation
• Snoring
Chief complaints in Larynx
• Change in voice – hoarse, cracked voice in males(puberphonia), vocal
fatigue- elders, functional
• Repeated clearing of throat- GERD, Chronic laryngitis
• Difficulty in breathing - infections, tumours
• Cough and expectoration
• Neck swellings
History of presenting illness
• Mode of onset – sudden, gradual
• Site
• Any cause of onset
• Duration
• Progress – slow , rapid, intermittent, continuous, increasing,
declining
• Factors aggravating or relieving
• Treatment for the same, since when and where
• How it has impacted life style
• LOOK FOR NEGATIVE ANSWERS
HOPI of TONSILLITIS
• Duration
• Onset (acute/insidious)
• Progression (is it worsening)
• Any associated discharge from oral cavity noticed by the
patient
• Is it associated with change in voice
• Is it associated with breathing difficulty
• Is it associated with difficulty in swallowing
• Any history of recent cough and cold
• Any history of fever
• Any history of sleep disturbances
• History of missing school/work
HOPI of Neck Swelling
• Duration
• Side (right/left/midline)
• Onset (acute/insidious)
• Progression
• Number of swellings
• Painful/painless
• Any aggravating/relieving factors
• Any skin changes above the swelling
HOPI of Laryngeal Cancer
(depends on involved parts-supraglottis,glottis or subglottis)
• Any recent change in voice noted (hoarseness).
• Lump in the neck. Describe using the above headings.
• Any difficulty in breathing
• Noisy breathing (stridor)- during inspiration or expiration
or both
• Any history of weight loss
• Any history of smoking
• Any history of cough or chest pain or bloody sputum
(suggestive of lung metastasis)
• Any history of right upper quadrant pain or jaundice
(suggestive of hepatic metastasis )
• Any history of bone pains (suggestive of bony metastasis)
HOPI of Oral Cavity Cancer
• Onset (insidious/acute,spontaneous)
• Duration
• Progression (initial size vs present size, any phase of rapid growth)
• Exact anatomical location
• Painful/painless
• Any associated discharge/bleeding
• Is it associated with loosening of teeth
• Any associated increased salivation/foul smelling breath
• Any sensory loss over face
• Any loss of taste sensations
• Is it associated with any mouth deviation/ inability to close the eyes completely/
excessive lacrimation
• Any history of weight loss
• Any history of smoking/ tobacco chewing
• Any history of change in voice ( laryngeal mets)
• Any history of cough or chest pain or bloody sputum ( sugg of lungs mets)
• Any history of right upper quadrant pain or jaundice (suggestive of hepatic mets)
• Any history of bone pains (sugg of bony mets)
• Any other lump in the body
Past history
• All diseases before this disease in chronological
order
• Diabetes, HTN, Bleeding disorders, TB, Asthma,
HIV, HBV, STD
• Surgeries, hospital admissions, Trauma
• Deliveries and pregnancies
• Drug history- steroids, insulin, ocp, anti
hypertensives
• Allergy history – drugs or diet or allergen
• FOR DRUG ALLERGY – WRITE IN RED
Personal history
• Lifestyle – exercise, sedentary
• Food habits – regular-irregular, spicy-non
spicy, non veg- veg, excess tea or coffee
• Smoking – frequency
• IV abuse
• Alcohol
• Bladder & Bowel habits
• Sleep cycle
• Menstrual history :- (LMP, cycle
length,duration,amount,passage of blood clots, pain severity).
Family history
• Enquire about parents, siblings and children
• Familial diseases like Peptic ulcer, cancers,
allergies, diabetes and HTN, otosclerosis
• Infectious diseases- by contact – TB , acute
infections
General Physical Examination
After explaining the procedures and taking
informed consent from the patient:-
• Mental state
• Consciousness
• Built and nutrition
• Attitude and gait
• Facies
• Pallor- palmar creases, lips,cheeks, conjunctiva,nail beds
• Cyanosis- tongue(central), nail bed,tip of nose,palmar skin
• Jaundice- sclera, nail bed, ear lobule, tip of nose
• Skin eruptions- macules (change in skin colour), papules,
vesicles,pustules (solid projections)
• Lymphadenopathy- Neck nodes
VITALS
• Pulse - rate,rhythm (regular, irregular)
• Respiratory rate - fast,slow
• Temperature - continuous (fluctuates less
than 1 degree), remittent (fluctuates more
than 2 degrees), intermittent
• Blood pressure
Local Examination
• Examine the affected region
• Inspection
• Palpation
• Movements
• Lymph nodes
Systemic Examination
• CVS
• Respiratory
• CNS - cranial nerve examination,GCS
• Abdominal
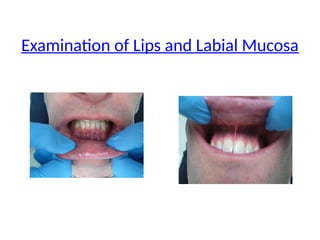
• Lips and Labial Mucosa
• Buccal Mucosa
• Mucobuccal Fold
• Hard Palate
• Soft Palate and Uvula
• Oropharynx & Nasopharynx
•Tongue
•Floor of Mouth
•Teeth
Complete examination of the oral cavity includes:
Examination of Lips and Labial Mucosa
Exam: Lips
• Observe the color ,scar,ulcer,swelling-intra-
orally and externally
• Is the vermillion border distinct?
• Bi-digitally palpate the tissue around the lips.
Check for nodules, bullae, abnormalities,
mucocele, fibroma
Exam: Lips
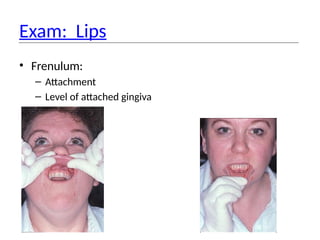
• Evert the lip and examine the tissue
• Observe frenum attachment/tissue tension
• Clear mucous filled pockets may be seen on
the inner side of the lip (mucocele). This is a
frequent, non-pathologic entity which
represents a blocked minor salivary gland
Exam: Lips
• Frenulum:
– Attachment
– Level of attached gingiva
Examination: Buccal Mucosa
● Observe color, character of the mucosa
Normal variations in color among ethnic groups
Amalgam tattoo
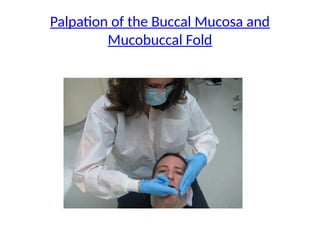
● Palpate tissue
● Observe Stenson’s duct opening for inflammation
or signs of blockage(upper second molar)
(pus,bloody discharge)
Palpation of the Buccal Mucosa and
Mucobuccal Fold
Gingiva
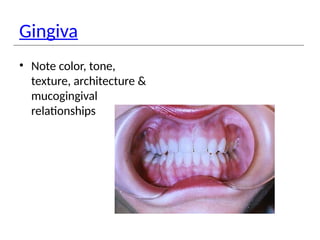
• Note color, tone,
texture, architecture &
mucogingival
relationships
Examination of Oral cavity
Inspection
Tongue
* Volume
* Colour
* Cracks or fissures
* Fur
* Papillae (any atrophy or abnormally like geographical tongue)
* Tongue tie (if present)
* Any swelling (if present)
* Any ulcer (aphthous/dental/tubercular/syphilitic/carcinomatous)
* Mobility: on protrusion and side-to-side movement
Palate
* Any perforation/cleft palate/swelling/ulceration/growth
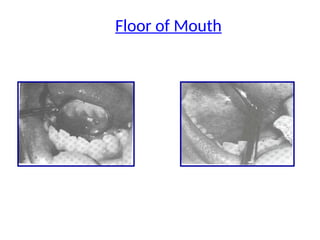
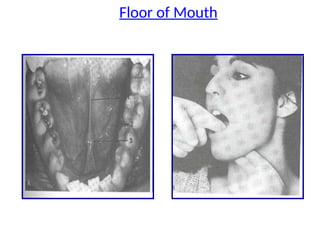
Floor of Mouth
* Any growth/cyst/ulcer
Cheek
* Any ulcer/leukoplakia/hyperpigmentation/growth
Retromolar Trigone
* Inspect for any lesion
Gum
* Inspect for swelling/bleeding/growth
Teeth
* Colour, shape, ridging, abnormal positioning
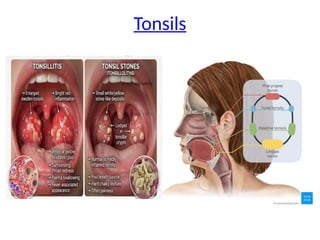
Tonsils
Any enlargement/medial deviation/pus spots/membrane on the
surface of tonsils
Palpation
Tongue
* Keep the patient’s tongue inside the oral cavity as it causes relaxation of
the tongue muscles.
* Protruded tongue causes contraction of muscles and may give rise to
false impression of induration.
* Induration may be present at the base of gummatous ulcer but is absent
in tuberculous ulcer.
* Malignant ulcer bleeds during palpation.
* Palpate the back of the tongue for any ulcer or swelling.
* Lingual thyroid should not be mistaken for any growth.
* Also palpate for a sharp tooth against an ulcer of tongue.
Palate
* Any ulcer or cyst (nasoalveolar or nasopalatine cyst) is examined in the
usual way.
* Alveolar abscess causes tender fluctuating swelling close to the alveolar
process.
Floor of Mouth
* It should be palpated bimanually.
* Translucency is tested if there is any cystic swelling.
* Ranula is translucent but sublingual dermoid cyst is not translucent.
* Submandibular duct is palpated for any stone.
Cheek
* Mucous membrane and cheek should be carefully palpated to know
involvement of skin or cheek by malignant growth.
Tonsils
* Press the tonsillar substance to observe for any extravasation of pus.
Tonsils
• Tucked in at base of anterior & posterior tonsillar pillars
• Squeezing-pus(acute),cheesy(chronic)
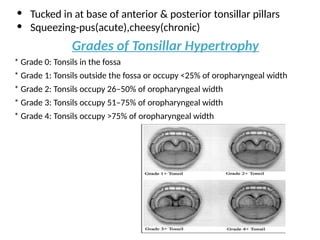
Grades of Tonsillar Hypertrophy
* Grade 0: Tonsils in the fossa
* Grade 1: Tonsils outside the fossa or occupy <25% of oropharyngeal width
* Grade 2: Tonsils occupy 26–50% of oropharyngeal width
* Grade 3: Tonsils occupy 51–75% of oropharyngeal width
* Grade 4: Tonsils occupy >75% of oropharyngeal width
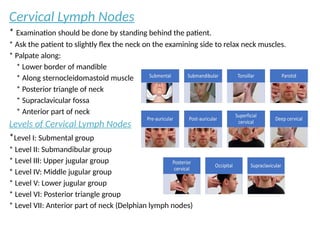
Cervical Lymph Nodes
* Examination should be done by standing behind the patient.
* Ask the patient to slightly flex the neck on the examining side to relax neck muscles.
* Palpate along:
* Lower border of mandible
* Along sternocleidomastoid muscle
* Posterior triangle of neck
* Supraclavicular fossa
* Anterior part of neck
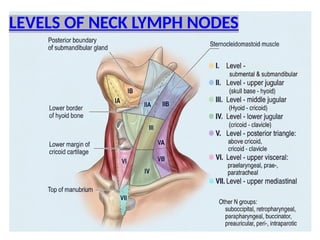
Levels of Cervical Lymph Nodes
*Level I: Submental group
* Level II: Submandibular group
* Level III: Upper jugular group
* Level IV: Middle jugular group
* Level V: Lower jugular group
* Level VI: Posterior triangle group
* Level VII: Anterior part of neck (Delphian lymph nodes)
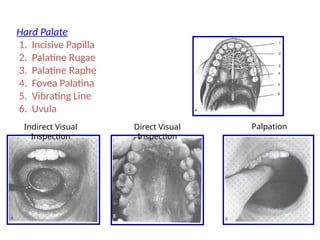
Hard Palate
1. Incisive Papilla
2. Palatine Rugae
3. Palatine Raphe
4. Fovea Palatina
5. Vibrating Line
6. Uvula
Indirect Visual
Inspection
Direct Visual
Inspection
Palpation
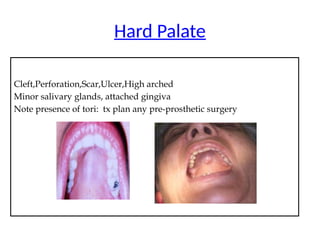
Cleft,Perforation,Scar,Ulcer,High arched
Minor salivary glands, attached gingiva
Note presence of tori: tx plan any pre-prosthetic surgery
Hard Palate
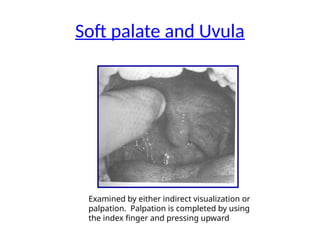
Examined by either indirect visualization or
palpation. Palpation is completed by using
the index finger and pressing upward
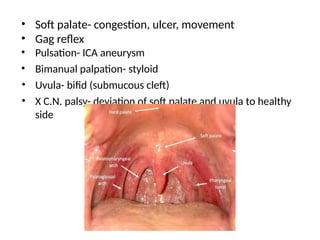
Soft palate and Uvula
Soft Palate and Uvula
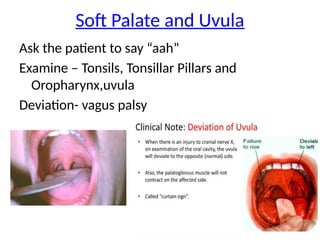
Ask the patient to say “aah”
Examine – Tonsils, Tonsillar Pillars and
Oropharynx,uvula
Deviation- vagus palsy
Oropharynx
• Occasionally small goblets of pink/transparent tissue
are normal and may have lymphoid tissue.
• Base of tongue,vallecula-IDL, palpation (ulcer,swelling)
• Anterior pillar- congestion,edema,ulcer
• Posterior pillar
• Tonsil- size,congestion, ulcer, abscess,membrane
• Palpation- hard(tonsillolith, malignancy), on
squeezing- pus(acute), cheesy material (chronic)
• Posterior pharyngeal wall-
congestion,discharge,swelling,ulcer,post nasal
drip( children-adenoid infection,adult-sinusitis)
• Soft palate- congestion, ulcer, movement
• Gag reflex
• Pulsation- ICA aneurysm
• Bimanual palpation- styloid
• Uvula- bifid (submucous cleft)
• X C.N. palsy- deviation of soft palate and uvula to healthy
side
Tongue
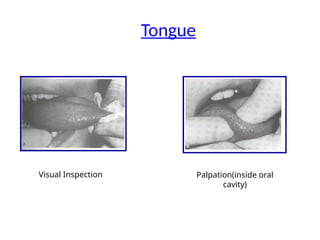
Visual Inspection Palpation(inside oral
cavity)
Tongue
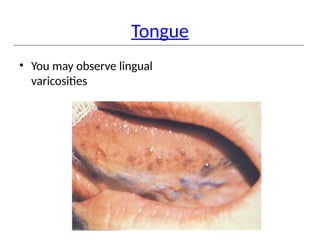
• You may observe lingual
varicosities
Exam: Tongue
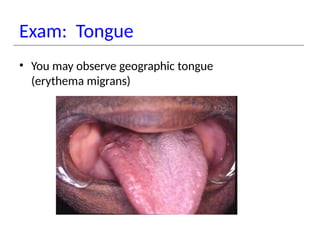
• You may observe geographic tongue
(erythema migrans)
Exam: Tongue
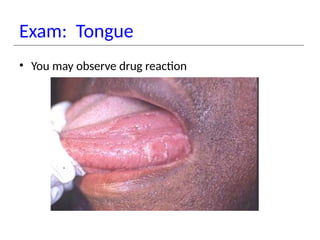
• You may observe drug reaction
Exam: Tongue
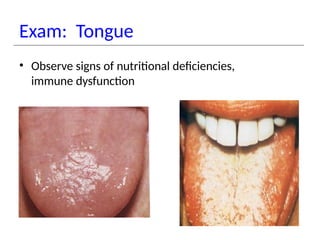
• Observe signs of nutritional deficiencies,
immune dysfunction
Exam: Tongue
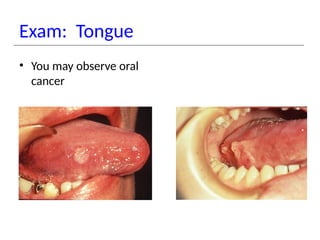
• You may observe oral
cancer
Floor of Mouth
Floor of Mouth
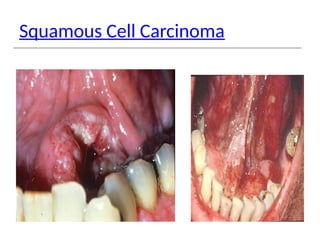
Squamous Cell Carcinoma
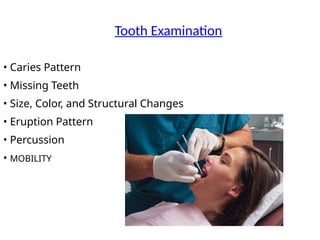
Tooth Examination
• Caries Pattern
• Missing Teeth
• Size, Color, and Structural Changes
• Eruption Pattern
• Percussion
• MOBILITY
Examination of Larynx
• External examination of neck
• Inspection- Observe the Adam’s
apple,whether distorted or not.
Angle- 90 degrees in males, 120 degrees in females
• Broadening ,thickening,redness,position,
movement on deglutition and breathing
• Palpation
• Laryngeal crepitus (move side to side),
tenderness(perichondritis)
• Scars, Neck nodes
• Auscultation- vascular swelling,stridor
• Voice
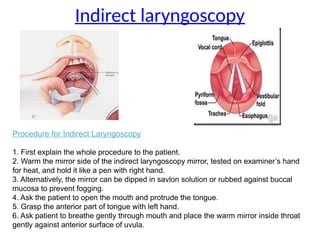
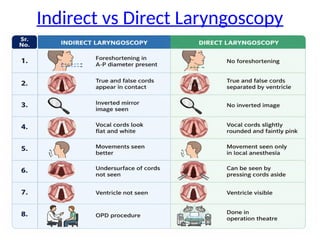
Indirect laryngoscopy
Procedure for Indirect Laryngoscopy
1. First explain the whole procedure to the patient.
2. Warm the mirror side of the indirect laryngoscopy mirror, tested on examiner’s hand
for heat, and hold it like a pen with right hand.
3. Alternatively, the mirror can be dipped in savlon solution or rubbed against buccal
mucosa to prevent fogging.
4. Ask the patient to open the mouth and protrude the tongue.
5. Grasp the anterior part of tongue with left hand.
6. Ask patient to breathe gently through mouth and place the warm mirror inside throat
gently against anterior surface of uvula.
Examination under Indirect Laryngoscopy:
* Epiglottis – size and color, swollen or not.
* Vocal cords
* Color
* Edema, presence of any nodule/polyp/cyst/growth
* Movement on:
* Gentle breathing
* Forced inspiration
* Phonation
* Coughing
* At rest
* Position – median, paramedian, cadaveric, gentle abduction and full abduction
* Arytenoids
* Aryepiglottic folds
* Interarytenoid area
* Glottic chink
* Post cricoid area (if any growth is present)
* Pyriform fossa (and whether any fullness is present)
* Upper few cm of trachea
* Base of tongue
* Vallecula
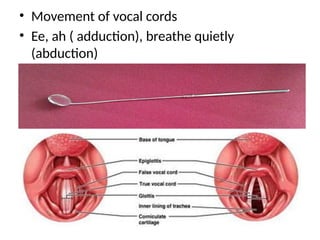
• Movement of vocal cords
• Ee, ah ( adduction), breathe quietly
(abduction)
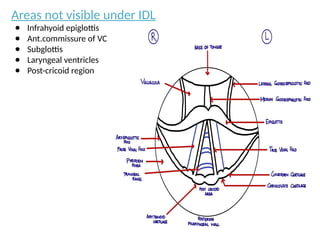
Areas not visible under IDL
● Infrahyoid epiglottis
● Ant.commissure of VC
● Subglottis
● Laryngeal ventricles
● Post-cricoid region
Indirect vs Direct Laryngoscopy
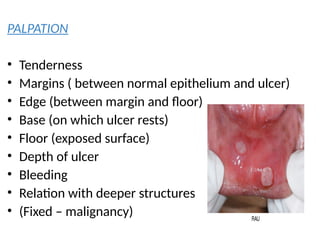
Examination of ulcer
• Ulcer – Break in the continuity of covering epithelium
(skin, mucous memb)
• Inspection
• Site – malignant ulcer in oral cavity, larynx
• Size and shape – tubercular (oval), malignant
(irregular), size both horizontal and vertical
• Number
• Position and extent
• Edge – tubercular (undermined), carcinoma
(everted), inflamed in spreading ulcer, bluish in
healing ulcer
PALPATION
• Tenderness
• Margins ( between normal epithelium and ulcer)
• Edge (between margin and floor)
• Base (on which ulcer rests)
• Floor (exposed surface)
• Depth of ulcer
• Bleeding
• Relation with deeper structures
• (Fixed – malignancy)
Neck Swellings
• Reactive nodes (MC)
• Age – sternomastoid tumour (newborn), malignancy
• Duration
• Mode of onset – sudden, gradual
• Pain
• Progress
• Site at which started
• Associated symptoms – weight loss, appetite, voice change,
dysphagia, resp distress
• Fever
• Recurrence
• Family history
Inspection
Always from front
• Site
• Number
• Size
• Extent – ant to post, med to lat, sup to inf
• Colour (blue- ranula)
• Surface (irregular – malignancy, smooth – cyst)
• Skin over swelling – colour, ulcer, scar
• Edge – smooth(benign), irregular – malignancy
Palpation
ALWAYS FROM BEHIND. NECK FLEXED
• Surface – smooth, irregular
• Fixation of skin – malignancy, seb cyst
• Edge – irregular, smooth and well defined (benign)
• Pulsations – vascular tumours ( CB, aneurysms)
• Temperature
• Tenderness
• Consistency – soft, hard
• Reducibility – totally disappears (meningocele)
• Compressibility- haemangiomas
• Relation to Sternocleidomastoid- superficial(prominent
on contraction), deep(disappear on contraction)
• Translucency – any fluid ie lymph, water (cystic hygroma)
• Mobility
• Percussion – Laryngocele (tympanic note)
• Auscultation – bruits and murmurs (vascular swellings)
• Impulse on coughing – if swelling in continuity with
cranial or spinal cavity – meningocele
• Movement on deglutition – if fixed to larynx or trachea
– thyroid
• Movement on protrusion of tongue – thyroglossal cyst
Thyroid Palpation
• Patient in sitting position, examiner standing
behind/front.
• Neck slightly flexed.
• Thumb behind the neck and other fingers on
front,palpate with finger tips in rolling fashion
Different Methods
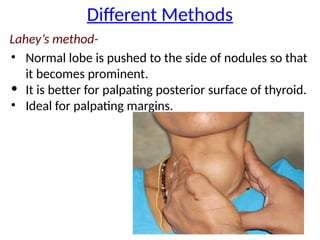
Lahey’s method-
• Normal lobe is pushed to the side of nodules so that
it becomes prominent.
• It is better for palpating posterior surface of thyroid.
• Ideal for palpating margins.
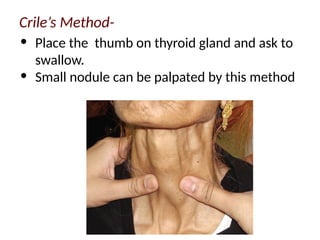
Crile’s Method-
• Place the thumb on thyroid gland and ask to
swallow.
• Small nodule can be palpated by this method
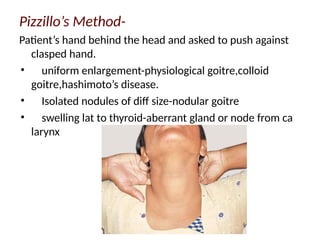
Pizzillo’s Method-
Patient’s hand behind the head and asked to push against
clasped hand.
• uniform enlargement-physiological goitre,colloid
goitre,hashimoto’s disease.
• Isolated nodules of diff size-nodular goitre
• swelling lat to thyroid-aberrant gland or node from ca
larynx
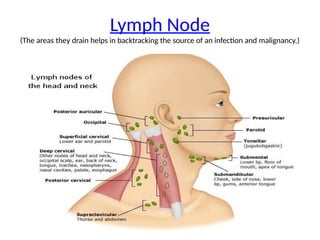
Lymph Node
(The areas they drain helps in backtracking the source of an infection and malignancy.)
• Location
• Laterality
• Number
• Surface,Shape,Size,Skin above it.
• Consistency – hard, rubbery, soft
• Discrete or matted
• Tender
• Fixation to skin, deeper structures
• Mobility (both transverse and vertical
planes).
LEVELS OF NECK LYMPH NODES
History and Examination of Oral Cavity,Throat & Neck