Histamines,
Antihistamines &
Prostaglandin
Presenter:-
Dr Arun Singh
2nd Year PG Student
Department of Pharmacology
SMS Medical College,Jaipur
Histamines &
Antihistamines
Learning Objectives
• Introduction
• Synthesis, storage, distribution of Histamine
• Role of Histamine
• Anti histamine
• Its therapeutic uses
• Adverse effects
• Summary
Introduction
Histamine is the most important amine autacoids.
Autacoids are endogenous molecules that do not fall into traditional
autonomic groups.
They do not act on cholinoceptors or adrenoceptors but have
powerful pharmacologic effects on smooth muscle and other tissues.
What are the
Autocoids?
The word autacoid comes from the
Greek: autos (self) & akos (medicinal
agent, or remedy)
They all have the common feature of
being formed by the tissues on which
they act; thus, they function as local
hormones
The autacoids also differ from
circulating hormones in that they are
produced by many tissues rather than
in specific endocrine glands.
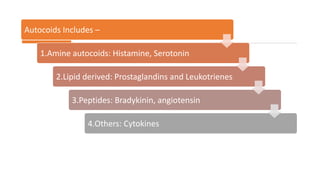
Autocoids Includes –
1.Amine autocoids: Histamine, Serotonin
2.Lipid derived: Prostaglandins and Leukotrienes
3.Peptides: Bradykinin, angiotensin
4.Others: Cytokines
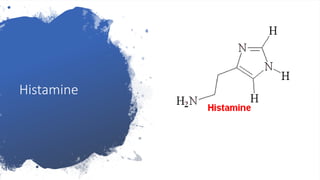
Histamine
Properties
Biogenic amine
present in -
animal and plant
tissues -venoms
and stinging
secretions
• One of the
mediators
involved in
inflammatory &
hypersensitivity
reactions.
• Histamine is present in many
human tissues, including
skin, intestinal mucosa, heart, lung,
and nerve endings in the brain.
• The usual body storage sites for
histamine include mast cells
and basophils.
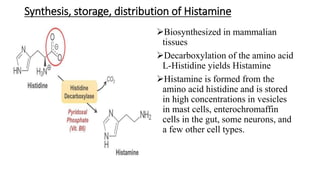
Synthesis, storage, distribution of Histamine
Biosynthesized in mammalian
tissues
Decarboxylation of the amino acid
L-Histidine yields Histamine
Histamine is formed from the
amino acid histidine and is stored
in high concentrations in vesicles
in mast cells, enterochromaffin
cells in the gut, some neurons, and
a few other cell types.
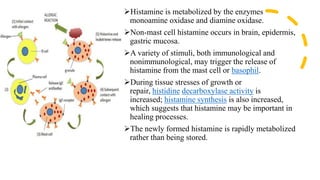
Histamine is metabolized by the enzymes
monoamine oxidase and diamine oxidase.
Non-mast cell histamine occurs in brain, epidermis,
gastric mucosa.
A variety of stimuli, both immunological and
nonimmunological, may trigger the release of
histamine from the mast cell or basophil.
During tissue stresses of growth or
repair, histidine decarboxylase activity is
increased; histamine synthesis is also increased,
which suggests that histamine may be important in
healing processes.
The newly formed histamine is rapidly metabolized
rather than being stored.
• Histamine degraded rapidly by oxidation to imidazole acetic acid
Degraded rapidly by methylation to N-methyl histamine
• Very little histamine is excreted unchanged.
• So, excess production of histamine in the body (eg. in systemic
mastocytosis) can be detected by measurement of its major metabolite,
imidazole acetic acid, in the urine.
Receptors
and Effects
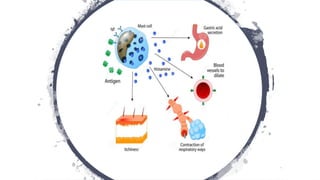
There are four types of histamine receptors present
in the our body.
(all GPCR’s):
(a)H1 receptors: It’s mediate effects on smooth muscle
leading to vasodilation (relaxation of vascular smooth
muscle), increased permeability & contraction of non-
vascular smooth muscle.
(b)H2 receptors: It’s mediate histamine stimulation of
gastric acid secretion & may be involved in cardiac
stimulation
(c)H3 receptors: The feedback inhibition in CNS, GIT,
Lungs & Heart
(d)H4 receptors: Eosinophils, Neutrophils & CD4 T-
cells
The triple response, a classic
demonstration of histamine
effect, is mediated mainly by
H1 and H2 receptors.
This response involves a small
red spot at the center of an
intradermal injection of
histamine surrounded by an
edematous wheal, which is
surrounded by a red flare.
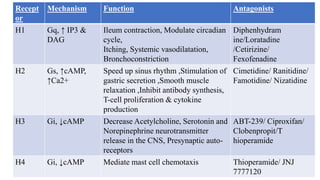
Recept
or
Mechanism Function Antagonists
H1 Gq, ↑ IP3 &
DAG
Ileum contraction, Modulate circadian
cycle,
Itching, Systemic vasodilatation,
Bronchoconstriction
Diphenhydram
ine/Loratadine
/Cetirizine/
Fexofenadine
H2 Gs, ↑cAMP,
↑Ca2+
Speed up sinus rhythm ,Stimulation of
gastric secretion ,Smooth muscle
relaxation ,Inhibit antibody synthesis,
T-cell proliferation & cytokine
production
Cimetidine/ Ranitidine/
Famotidine/ Nizatidine
H3 Gi, ↓cAMP Decrease Acetylcholine, Serotonin and
Norepinephrine neurotransmitter
release in the CNS, Presynaptic auto-
receptors
ABT-239/ Ciproxifan/
Clobenpropit/T
hioperamide
H4 Gi, ↓cAMP Mediate mast cell chemotaxis Thioperamide/ JNJ
7777120
Pharmacological Action
(A)Exocrine Excretion(H1) :-
↑ Production of nasal + bronchial mucus
(B)Bronchial Smooth Muscle(H1):-
Bronchiolar constriction
Asthmatic symptoms
↓ Lung capacity
(C) Intestinal Smooth Muscle(H1):-
Contraction Intestinal cramps & diarrhea
(D)Sensory Nerve Endings(H1):-
Itching & pain
(E)Cardiovascular System(H1&2):-
↓ Peripheral resistance ----↓Systemic BP
+ve chronotropism(H2)
+ve inotropism
(F)Skin(H1&2):-
Dilatation & ↑ permeability of the venules
Leakage of fluid + proteins into the tissues
Classic “triple-response”(wheal formation+
reddening due to local VD(<1-2 min) +
flare(halo)
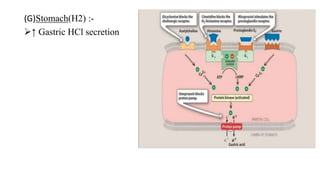
(G)Stomach(H2) :-
↑ Gastric HCl secretion
Adverse Effects of Histamines Release
• Itching, Urticaria
• Flushing
• Hypotension
• Tachycardia
• Bronchospasm
• Angioedema
• Wakefulness
• Increased acidity (Gastric acid secretion)
Histamine has no therapeutic use.
In the post it has been used to test acid secreting capacity of
stomach, bronchial hyperreactivity in asthamatics, and for
diagnosis of pheochromocytoma, but these pharmacological tests
are risky and obsolete now.
Betahistine
It is an orally active, somewhat
H1selective histamine analogue, which is
used to control vertigo in patients of
Meniere disease.
It possibly acts by causing vasodilation in
the internal ear.
It is contraindicated in asthmatics and
ulcer patients.
Anti-histamines
Overview
• The effects of histamine released in the body can be reduced in
several ways
• Physiologic antagonists, especially epinephrine, have smooth
muscle actions opposite to those of histamine, by acting at different
receptors
• This is important clinically because injection of epinephrine can be
lifesaving in systemic anaphylaxis/other conditions in which
massive release of histamine(and other more important
mediators)occurs
Histamine
Release
Inhibitors
• Reduce the degranulation of mast
cells that results from
immunologic triggering by
antigen -IgE interaction
• Cromolyn and nedocromil appear
to have this effect and have been
used in the treatment of asthma,
although the molecular
mechanism underlying their action
is not fully understood
• Beta2-adrenoceptor agonists also
appear capable of reducing
histamine release
H1-Antagonists(Conventional Antihistaminics)
• These drugs competitively antagonizes actions of histamine at the
H1 receptors.
• A wide variety of antihistaminic H1 blockers are available from
several different chemical families.
• Recent evidence indicates that histamine H1 receptor exhibits some
degree of constitutive activity, and the H1 antagonists are also
inverse agonists.
• The first compounds of this type were introduced in the late 1930s
and have subsequently proliferated into an unnecessary motley of
drug.
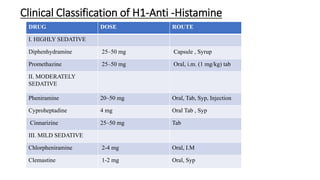
Clinical Classification of H1-Anti -Histamine
DRUG DOSE ROUTE
I. HIGHLY SEDATIVE
Diphenhydramine 25–50 mg Capsule , Syrup
Promethazine 25–50 mg Oral, i.m. (1 mg/kg) tab
II. MODERATELY
SEDATIVE
Pheniramine 20–50 mg Oral, Tab, Syp, Injection
Cyproheptadine 4 mg Oral Tab , Syp
Cinnarizine 25–50 mg Tab
III. MILD SEDATIVE
Chlorpheniramine 2-4 mg Oral, I.M
Clemastine 1-2 mg Oral, Syp
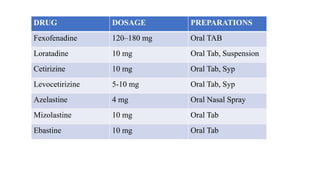
DRUG DOSAGE PREPARATIONS
Fexofenadine 120–180 mg Oral TAB
Loratadine 10 mg Oral Tab, Suspension
Cetirizine 10 mg Oral Tab, Syp
Levocetirizine 5-10 mg Oral Tab, Syp
Azelastine 4 mg Oral Nasal Spray
Mizolastine 10 mg Oral Tab
Ebastine 10 mg Oral Tab
• Two major subgroups or
“generations” have been developed.
• The older members of the first-
generation agents, typified by
diphenhydramine, are highly sedating
agents with significant autonomic
receptor-blocking effects.
• A newer subgroup of first-generation
agents is less sedating and has much
less autonomic effect.
• Chlorpheniramine and Cyclizine may
be considered prototypes.
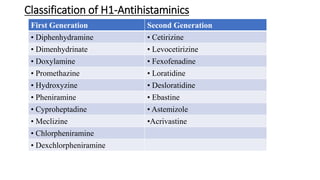
Classification of H1-Antihistaminics
First Generation Second Generation
• Diphenhydramine • Cetirizine
• Dimenhydrinate • Levocetirizine
• Doxylamine • Fexofenadine
• Promethazine • Loratidine
• Hydroxyzine • Desloratidine
• Pheniramine • Ebastine
• Cyproheptadine • Astemizole
• Meclizine •Acrivastine
• Chlorpheniramine
• Dexchlorpheniramine
• The second-generation H1 blockers, typified by cetirizine, fexofenadine,
and loratadine, are far less lipid soluble than the first-generation agents
and have greatly reduced sedating and autonomic effects.
• All H1 blockers are active by the oral route. Several are promoted for
topical use in the eye or nose.
• Most are metabolized extensively in the liver.
• Half-lives of the older H1 blockers vary from 4 to 12 h.
• Second generation agents have half-lives of 12–24 h.
Mechanism and Effects:-
H1 blockers are competitive pharmacologic antagonists or inverse
agonists at the H1 receptor; these drugs have no effect on histamine
release from storage sites.
They are more effective if given before histamine release occurs.
Because their structure closely resembles that of muscarinic blockers
and α-adrenoceptor blockers, many of the first-generation agents are
potent pharmacologic antagonists at these autonomic receptors.
 A few also block serotonin receptors.
As noted, most older first-generation agents are sedating, and some—
not all—first-generation agents have anti-motion sickness effects.
Many H1 blockers are potent local anesthetics.
H1-blocking drugs have negligible effects at H2 receptors.
Clinical Use:-
H1 blockers have major applications in allergies of the immediate type (i.e. those
caused by antigens acting on IgE antibody-sensitized mast cells).
These conditions include hay fever and urticaria.
Diphenhydramine, dimenhydrinate, cyclizine, meclizine, and promethazine are
used as anti-motion sickness drugs.
Diphenhydramine is also used for management of chemotherapy-induced
vomiting.
Doxylamine, in combination with pyridoxine, is promoted for the prevention of
morning sickness in pregnancy.
Adverse effects of the first-generation H1 blockers:-
These are sometimes exploited therapeutically (eg.in their use as hypnotics in
over-the-counter sleep aids).
Toxicity and Interactions :-
Sedation is common, especially with diphenhydramine and promethazine and
these drugs should not be consumed before operating machinery.
It is much less common with second-generation agents, which do not enter the
CNS readily.
Antimuscarinic effects such as dry mouth and blurred vision occur with some
first-generation drugs in some patients.
Alpha-adrenoceptor blockade, which is significant with phenothiazine derivatives
such as promethazine, may cause orthostatic hypotension.
Interactions:-
It occur between older antihistamines and other drugs with sedative
effects (e.g. benzodiazepines and alcohol).
Drugs that inhibit hepatic metabolism may result in dangerously high
levels of certain antihistaminic drugs that are taken concurrently.
 For example, azole antifungal drugs and certain other CYP3A4
inhibitors interfere with the metabolism of astemizole and terfenadine, 2
second-generation agents that have been withdrawn from the US market
because high plasma concentrations of either antihistamine can
precipitate lethal arrhythmias.
H2-Antagonists(H2-Antihistaminics)
The first H2 blocker Burimamide was developed by Black in 1972.
Metiamide was the next, but both were not found suitable for clinical
use.
Cimetidine was introduced in 1977 and gained wide usage.
Ranitidine, famotidine, roxatidine, and many others have been added
subsequently.
These drugs do not resemble H1
blockers structurally.
They are orally active, with half-
lives of 1–3 h.
Because they are all relatively
nontoxic, they can be given in large
doses, so that the duration of action
of a single dose may be 12–24 h.
All four agents are available in oral
over-the counter formulations.
Mechanism and Effects:-
H2 antagonists produce a surmountable
pharmacologic blockade of histamine H2
receptors.
They are relatively selective and have no
significant blocking actions at H1 or
autonomic receptors.
The only therapeutic effect of clinical
importance is the reduction of gastric acid
secretion, but this is a very useful action.
Blockade of cardiovascular and mast cell
H2-receptor-mediated effects can be
demonstrated but has no clinical significance.
In Zollinger-Ellison syndrome, which is associated with gastrinoma and
characterized by acid hypersecretion, severe recurrent peptic ulceration,
gastrointestinal bleeding, and diarrhea, these drugs are helpful, but very large doses
are required; proton pump inhibitors are preferred.
Clinical Use:-
In acid-peptic disease, especially duodenal ulcer, these drugs reduce nocturnal acid
secretion, accelerate healing, and prevent recurrences.
Acute ulcer is usually treated with 2 or more doses per day, whereas recurrence of
duodenal ulcers can often be prevented with a single bedtime dose.
H2 blockers are also effective in accelerating healing and preventing recurrences of
gastric peptic ulcers.
Intravenous H2 blockers are useful in preventing gastric erosions and hemorrhage
that occur in stressed patients in intensive care units.
• Similarly, the H2 blockers have been used in gastroesophageal reflux
disease (GERD), but they are not as effective as proton pump inhibitors.
Toxicity:-
Cimetidine is a potent inhibitor of hepatic drug-metabolizing enzymes
and may also reduce hepatic blood flow.
Cimetidine also has significant antiandrogen effects in patients
receiving high doses.
Ranitidine has a weaker inhibitory effect on hepatic drug metabolism;
neither it nor the other H2 blockers appear to have any endocrine
effects.
Prostaglandin
Introduction
• Prostaglandins & their related compounds prostacyclins (PGI),
thromboxanes (TXA), leukotrienes (LT) & lipoxins are collectively
known as eicosaniods, they all contain.
• In 1970s it became clear that aspirin like drugs act by inhibiting PG
synthesis, and that in addition to the classical PGs (Es and Fs),
thromboxane (TX), prostacyclin (PGI) and leukotrienes (LTs) were of
great biological importance.
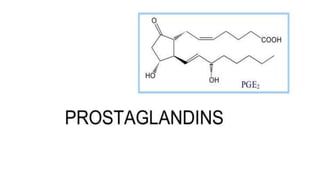
Structure of prostaglandin
• Prostaglandins are derivatives of 20-carbon fatty acid - prostanoic
acid, hence known as prostanoids.
• This has a cyclopentane ring (formed by carbon atoms 8 to 12) & two
side chains, with carboxyl group on one side.
• Prostaglandins differ in their structure due to substituent group &
double bond on cyclopentane ring.
• Most important prostaglandins (PGF2 & PGF2α), prostacyclins
(PGI2), thromboxanes (TXA2) & leukotrienes (LTA4).
Synthesis of Prostaglandin
• Arachidonic acid (5,8,11,14 - eicosatetraenoic acid) is the precursor
for most of the prostaglandins in humans.
• It occurs in the endoplasmic reticulum.
• Release of arachidonic acid from membrane bound phospholipids by
phospholipase A2.
• It occurs due to a specific stimuli by hormones – epinephrine or
bradykinin.
• Oxidation & cyclization of
arachidonic acid to PGG2 which
is then converted to PGH2 by
peroxidase.
• PGH2 serves as the immediate
precursor for the synthesis of a
number of prostaglandins,
including prostacyclins &
thromboxane.
• This is known as cyclic pathway
of arachidonic acid.
Cyclooxygenase
• e – a suicide enzyme.
• Prostaglandin synthesis can be
partly controlled by suicidal
activity of the enzyme
cyclooxygenase.
• Enzyme is capable of undergoing
self catalysed destruction to
switch off PG synthesis.
Inhibition of Prostaglandin Synthesis
• Corticosteroids (e.g. cortisol) prevent the formation of arachidonic
acid by inhibiting the enzyme phospholipase A2.
• Anti-inflammatory drugs inhibit the synthesis of prostaglandins,
prostacyclins & thromboxane.
• They block the action of cyclooxygenase.
• Aspirin irreversibly inhibits cyclooxygenase.
Degradation of
Prostaglandin
Synthesis
All the eicosanoids are
metabolized rapidly.
Degradation occur in lung &
liver.
Two enzymes, namely 15-α-hydroxy PG
dehydrogenase & 13-PG reductase,
convert hydroxyl group at C15 to keto
group & then to C13 and C14
dihydroderivative.
Biological
Actions of
Prostaglandin
• Prostaglandins act as local
hormones.
• PGs are produced in almost all the
tissues.
• PGs are not stored & they are
degraded to inactive products at the
site of their production.
• PGs are produced in very small
amounts & have low half-lives.
• Regulation of blood pressure: The
prostaglandins (PGE, PGA & PGl2)
are vasodilator in function.
• This results in increased blood flow
and decreased peripheral resistance to
lower the blood pressure.
• PGs serve as agents in the treatment
of hypertension.
• Inflammation
Inflammation:
• PGEI & PGE2 induce the symptoms of
inflammation (redness, swelling, edema
etc.) due to arteriolar vasodilation.
• PGs are natural mediators of
inflammatory reactions of rheumatoid
arthritis, psoriasis, conjunctivitis etc.
• Corticosteroids are used to treat these
inflammatory reactions, since they
inhibit prostaglandin synthesis.
Reproduction:
• PGE2 & PGF2 are used for the medical
termination of pregnancy & induction of
Labour.
• Pain and fever: Pyrogens (fever producing
agents) promote prostaglandin synthesis
leading to the formation of PGE2 in
hypothalamus-regulation of body
temperature.
• PGE2 along with histamine & bradykinin
cause pain.
• Migraine is also due to PGE2.
• Aspirin & other non-steroidal drugs inhibit
PG synthesis & thus control fever & relieve
pain.
Regulation of gastric secretion:
• Prostaglandins (PGE) inhibit gastric
secretion.
• PGs are used for the treatment of
gastric ulcers.
• PGs stimulate pancreatic secretion
& increase the motility of intestine
which often causes diarrhea.
Influence on immune system:
• Macrophages secrete PGE which
decreases the immunological functions
of B-& T-lymphocytes.
Effects on respiratory function:
• PGE is a bronchodilator whereas PGF
acts as a constrictor of bronchial
smooth muscles.
• PGE & PGF oppose the actions of each
other in the lungs.
• PGEI & PGE2 are used in the treatment
of asthma.
Influence on renal functions:
• PGE increases glomerular filtration rate &
promotes urine output.
• Excretion of Na+ & K+ is also increased by PGE.
Effects on metabolism:
• Prostaglandins influence certain metabolic
reactions, through the mediation of cAMP.
• PGE decrease lipolysis, increases glycogen
formation & promotes calcium mobilization.
• Platelet aggregation
Platelet aggregation & thrombosis:
• The prostaglandins – prostacyclins
(PGI2), inhibit platelet aggregation.
• Thromboxanes (TXA2) &
prostaglandin E2 promote platelet
aggregation & blood clotting that
might lead to thrombosis.

Mechanism of
action of PGs
• PGE increases cAMP & PGF
increases cGMP.
Biological
Applications of
Prostaglandins
• They are used in the treatment of
gastric ulcers, hypertension,
thrombosis, asthma etc.
• Prostaglandins are also in the
medical termination of pregnancy,
prevention of conception,
induction of labor etc.
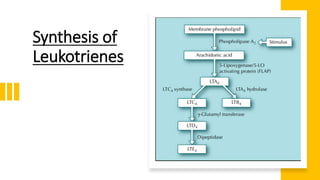
Leukotrienes
• Leukotrienes are synthesized by
leucocytes, mast cells, lung, heart,
spleen etc., by lipoxygenase
pathway of arachidonic acid.
• Leukotrienes (A4, B4, C4, D4 &
E4) are synthesized through the
intermediate, 5-
hydroperoxyeicosatetraenoic acid
(5-HPETE).
Synthesis of
Leukotrienes
• Leukotrienes (C4, D4 & E4) are components of slow-reacting
substances of anaphylaxis (SRSA), released after immunological
challenge.
• SRS-A is 100 -1,000 times more potent than histamine or
prostaglandins in its action as a stimulant of allergic reactions.
• Leukotrienes are implicated in asthma, inflammatory reactions,
hypersensitivity (allergy) and heart attacks.
• Leukotrienes cause contraction of smooth muscles,
bronchoconstriction, vasoconstriction, adhesion of white blood cells
& release of lysosomal enzymes.
• Lipoxins are involved in vasoactive & immunoregulatory functions.
Histamines, Antihistamines & Prostaglandin.pptx