HEMOPTYSIS
Dr. J. Roig
Pulmonary Division
Hospital N. Sra. de Meritxell
Andorra
Life threatening hemoptysis (LTH)
 LTH better than “massive” hemoptysis
 Value of clinical history
 Physical findings
 Laboratory data
 Chest X-ray
 Optionally other image techniques
 Bronchoscopy
Causes of hemoptysis
 Infections
 Bronchitis
 Tuberculosis
 Fungus
 Pneumonia
 Lung abscess
 Bronchiectasis
 Tumors
 Bronchial cancer
 Carcinoid
 Cardiovascular
 Lung infarct
 Mitral stenosis
 Trauma
 Other
 Foreign body
 Hemorrhagic diatesis
 Goodpasture and
other immunological
disorders
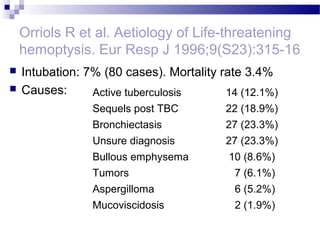
Orriols R et al. Aetiology of Life-threatening
hemoptysis. Eur Resp J 1996;9(S23):315-16
 Intubation: 7% (80 cases). Mortality rate 3.4%
 Causes: Active tuberculosis 14 (12.1%)
Sequels post TBC 22 (18.9%)
Bronchiectasis 27 (23.3%)
Unsure diagnosis 27 (23.3%)
Bullous emphysema 10 (8.6%)
Tumors 7 (6.1%)
Aspergilloma 6 (5.2%)
Mucoviscidosis 2 (1.9%)
Uncommon, sometimes neglected,
causes of LTH: infections
 Viral lung or bronchial infection (usually
associated with disseminated iv
coagulation and bleeding diathesis)
 Necrotizing bronchial fungal infection
 Bacterial endocarditis
 Mycotic intrathoracic aneurisms
 Hirudo medicinalis (common leech)
S. aureus infection in healthy
•Gillet Y. Association between S. aureus strains
carrying gene for Panton-Valentine leukocidin and
highly lethal necrotising pneumonia in young
immunocompetent patients. Lancet 2002;359:753-
59.
•Boussaud V. Life-threatening hemoptysis in
adults with CAP due to PV leukocidin-secreting S.
aureus. Intensive Care Med 2003;29:1840-3.
•Francis J. Severe Community-onset pneumonia
in healthy adults caused by methicillin-resistant S.
aureus carrying the PV leukocidin genes.CID2005
Tuberculosis - LTH
 Active infection
 Rasmussen pulmonary artery aneurism
 Sequels post-tuberculosis:
Bronchiectasis
Broncholitiasis
Mycetoma in residual cavities
 “Scar carcinoma”
Aspergillus - Hemoptysis
 Aspergilloma
 Invasive aspergillosis
 Chronic necrotizing aspergillosis or semiinvasive
 Necrotizing pseudomembranous
tracheobronchitis
 Stump aspergillosis after lung resection
 Bronchocentric granulomatosis
Lung abscess and LTH
 Thomas NW. Life-threatening hemoptysis in
primary lung abscess. Ann Thorac Surg
1972;14:347
Sequential filling-emptying pattern is a warning
sign of massive hemoptysis in lung abscess:
urgent surgery must be considered
 Philpott NJ. Lung abscess: a neglected cause of
life-threatening hemoptysis. Thorax 1993;48:674
Recommends surgery if LTH in chronic abscess
Uncommon, sometimes neglected,
causes of LTH: cardiovascular
 Eisenmenger syndrome
 Mitral stenosis
 Left ventricle pseudoaneurysm
 Aortobronchial fistulas
 Vascular pulmonary abnormalities
associated with liver disease
Vascular disease
BRONCHIAL CIRCULATION
 Angiomes and aneurisms of bronchial arteries
 Varicosities in chronic liver disease
 Vasculitides
 Arterial hypervascularization secondary to:
 Inflammatory process
 Tumors
 Congenital heart disease
 Chronic stenosis of pulmonary artery
Vascular disease
SYSTEMIC CIRCULATION
 Aortic dissection
 Systemic Hypervascularization
Intercostal arteries
Other as mamary artery
 Vasculitides
Vascular disease
PULMONARY CIRCULATION
 Pulmonary disease
 Arteriovenous fistula
 Tumors (angiosarcoma)
 Aneurysms (micotic or not)
 Primary pulmonary hypertension
 Varicosities in chronic liver disease
 Vasculitides
Vascular abnormalities in chronic
liver disease
 Man KM et al. Pulmonary varices presenting as
a solitary lung mass in a patient with end-stage
liver disease. Chest 1994;106:294-6.
 Schnader J et al. Hemoptysis, hepatopulmonary
syndrome and respiratory failure. Clinical
conference on management dilemmas. Chest
1997;111:1724-32.
 Youssef A et al. Hemoptysis secondary to
bronchial varices associated with alcoholic liver
cirrhosis and portal hypertension. Am J
Gastroenterol 1994;89:1562-3.
Uncommon, sometimes neglected,
causes of LTH: vasculitis
 Tracheobronchial form of Wegener
 Behçet vasculitis
 Hughes-Stovin syndrome
 Takayasu arteritis
Uncommon, sometimes neglected,
causes of LTH: congenital abnormalities
 Agenesis of pulmonary artery
 Congenital anomalies of large mediastinal
vessels, such as hemitruncus
 Cystic disease with/without laryngeal
papylomatosis
 Pulmonary sequestration
 Accessory cardiac bronchus
Uncommon, sometimes neglected,
causes of LTH: tumors
 Some pulmonary metastasis (angiosarcoma
and hepatocellular carcinoma)
 Some endobronchial metastasis (thyroid
papillar carcinoma)
 Cystic mediastinal mass
 Inflammatory pseudotumor
 Pulmonary cavernous hemangiomatosis
Uncommon, sometimes neglected,
causes of LTH: other bronchial
abnormalities
 Broncholithiasis
 Tracheopatia osteochondroplastica
 Aspiration of foreign body
Causes of Diffuse Alveolar
Hemorrhage (DAH) - 1
 Bone marrow transplantation, especially
autologous
 Drug-induced pulmonary hemorrhage
 Isolated pulmonary capillaritis with negative
antineutrophil cytoplasmic antibodies
 Pulmonary arterial fibromuscular dysplasia
 DAH associated with high altitude edema
 DAH with positive antiglomerular basement
membrane antibodies without renal involvement
 Idiopathic pulmonary hemosiderosis
Causes of Diffuse Alveolar
Hemorrhage (DAH) - 2
 Systemic vasculitides, collagen vascular diseases
 Negative pressure alveolar hemorrhage
 Serious group A streptococcal infections
 Ehlers-Danlos syndrome
 Crack-cocaine inhalation
 Severe bleeding diathesis (DIC)
 Trimellitic anhydride inhalation
 Primary antiphospholipid syndrome
 Lung transplant rejection
 Pulmonary-renal syndrome
 Pulmonary infection in immunocompromised
 Pulmonary veno-occlusive disease
Keypoints in DAH
 DAH may be the initial form of
presentation
 There is no correlation between the
amount of expectorated blood and the real
volume of alveolar bleeding
 If glomerular involvement, deterioration of
renal function may be very quick
 Value of progressively hemorrhagic BAL
 Value of sequential DLCO in non-acute
setting
Uncommon, sometimes neglected,
causes of LTH: miscellaneaous
 Lymphangioleimyomatosis
 Uremia
 Exogenous lipid pneumonia
 Intrathoracic Recklinghausen disease
 Extreme breath-hold diving
 Bullous emphysema
 Broncholitis obliterans organizing pneumonia
 Sarcoidosis
 Respiratory bronchiolitis associated interstitial
lung disease
 Subphrenic abscess penetrating the diaphragm
LTH –Miscellaneous (1)
 Thoracic trauma
 Broncholitiasis
 Foreign body
 Hemorrhagic diathesis
 Vasculitis – alveolar hemorrhage
 Old, chronic scars (sequels):
Middle lobe syndrome
Emphysema (bullae)
LTH - Miscellaneous (2)
 Fibrosing mediastinitis
 Mediastinal tumors: teratoma
 Esophageal cancer
 Sarcoidosis
 Septal diffuse amiloidosis
 Fictitious hemoptysis
General measures in LTH
 Immediate intubation and mechanical ventilation if
 Asphyxia
 Hypovolemic shock
 Evaluate admission to the respiratory and ICU
 Nothing by mouth
 Ipsilateral decubitus lying on the alleged bleeding site
 Intravenous line
 Evaluate local applicability of the general algorithmic
approach
 Provision to allow rapid blood replacement
 Control of bleeding speed and volume of expectorated
blood
 Chest radiograph
 Routine blood tests: consider specialized tests if indicated
 Consider specialized diagnostic procedures if indicated
Hemoptysis, X-ray and FOB
 Misdiagnoses if classical criteria are followed
 Hemoptysis > 7 days
 Age > 40
 Smoking habit
 FOB in any hemoptysis without diagnosis:
 Increasing incidence of tumor even in age < 40
 Overall % of cancer on long-term follow-up: 4%
 A variety of other non-tumor diagnoses by FOB
 LTH is unpredictable
 Low morbidity (0.08%) and mortality (0.01) of FOB
LTH: technical aspects of FOB
 ENT evaluation is mandatory
 Aspiration channel > 2.6 mm of Ø
 Avoid FOB-related bleeding iatrogenia:
Bronchiectasis
Carcinoid tumor
Bronchial angiomas
Aneurysms of pulmonary artery
Removal of old foreign body
Iatrogenic causes of LTH - 1
 Surgical corrections of congenital heart disease
 Endobronchial brachytherapy
 Self-expanding, indwelling airway and esophageal stent-
related fistulas
 Bronchoscopy-related bleeding complications
 Migration to lung of vascular and heart (cardioverter
defribillator) patches
 Aortobronchial fistula after vascular aortic thoracic graft
 Coronary angiography with abciximab infusion
 Late bleeding after anticoagulation therapy in pulmonary
embolism
 Bronchial artery infusion of cytostatic therapy to treat
pulmonary metastasis
Iatrogenic causes of LTH - 2
 Pulmonary irradiation
 Lymphoma and other mediastinal tumors
irradiation
 Catheter-induced pulmonary artery lesion
 Transtracheal aspiration
 Percutaneous lung aspiration
 Long-standing tracheostomy with
tracheoinnominate artery fistula
 Thrombolytic therapy, especially with
unsuspected cavitary lung disease
 Retained intrathoracic old gauze (“gauzeoma”) or
sponge
Iatrogenic causes of LTH - 3
 Bronchovascular fistula after lung transplantation
 Drug-induced bleeding diathesis: DAH
 Intravascular migration of fractured sternal wire
after median sternotomy
 Positive pressure ventilation in patients with
cavitary tuberculosis
 Bronchovascular fistula after lung transplantation
 Bronchial stump aspergillosis in old
endobronchial silk thread sutures
 Hemoptysis secondary to veno-occlusive
pulmonary disease (VOPD) after Glen operation
 Pulmonary venous stenosis after catheter
radiofrequency ablation
Hellical CT in LTH
 Great blood vessels disease
 Usually X-ray, FOB and BAE are first options
 Often confusing “mass-like” images in lung
parenchima
 Frequent accumulation of blood at the bottom of
both lungs.
 Relevance of accurate technique: thin section,
“helical CT”,…
General measures in LTH
 Immediate intubation and mechanical ventilation if
 Asphyxia
 Hypovolemic shock
 Evaluate admission to the respiratory and ICU
 Nothing by mouth
 Ipsilateral decubitus lying on the alleged bleeding site
 Intravenous line
 Evaluate local applicability of the general algorithmic
approach
 Provision to allow rapid blood replacement
 Control of bleeding speed and volume of expectorated
blood
 Chest radiograph
 Routine blood tests: consider specialized tests if indicated
 Consider specialized diagnostic procedures if indicated
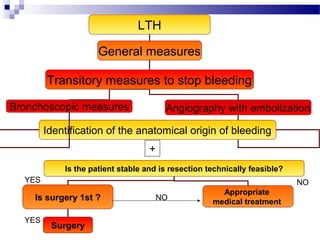
LTH
General measures
Transitory measures to stop bleeding
Angiography with embolization
Identification of the anatomical origin of bleeding
Bronchoscopic measures
+
Is the patient stable and is resection technically feasible?
Is surgery 1st ?
Appropriate
medical treatment
Surgery
YES NO
YES
NO
Bronchial artery embolization (BAE)
 Anatomic variability both in number and localization
 Direct visualization of site of bleeding is very
difficult
 Sometimes hypervascularized areas are extensive
and bilateral
 Sometimes origin of bleeding is in collateral
systemic circulation
 Percentage of origin of bleeding in pulmonary
circulation is very low
 Risk if anterior spinal artery from bronchial artery
(<5%)
Complications of BAE
 Spinal complication (paraplegia)
 Chest pain
 Dysphagia
 Main-stem bronchus infarction
 Bronchial stenosis
 Splenic or other systemic infarct
 Bronchial-esophageal fistula
 Paradoxic embolization or migration of coil
 Pulmonary hypertension (if left-to-right shunt)
 Referres pain to the ipsilateral forehead and orbit
Drugs reported to be potentially effective in
some causes of LTH
 Tranexamix acid, especially in mucoviscidosis*
 Vasopressin*
 Immunosupressive drugs and steroids in some
cases of DAH and vasculitis
 Recombinant activated factor VII (rFVIIa)
 Percutaneous intracavitary treatment in lung
fungal infection
 Cidofovir in juvenile laryngeal papillomatosis-
related multicystic disease
 Anticoagulant therapy in embolism
 Hormone: LAM; thoracic endometriosis
 Corrective therapy of coaguloptahies
* Anecdotal reports and uncontrolled studies