PREPARED BY
Prof. ASHISH N. UMALE
M. PHARM IN PHARMACOLOGY
ASSISTANT PROFESSOR
SHRADDHA INSTITUTE OF PHARMACY, WASHIM-
444505
PHARMACOLOGY-II
 Introduction to Cardiovascular Pharmacology
Cardiovascular pharmacology is the branch of pharmacology that deals
with drugs affecting the heart, blood vessels, blood pressure, and blood
circulation.
 The primary objective of these drugs is to maintain adequate tissue
perfusion and oxygen delivery by improving cardiac function or vascular
function.
 Cardiovascular diseases such as hypertension, ischemic heart disease,
heart failure, arrhythmias, and various disorders are among the leading
causes of morbidity and mortality worldwide.
 Therefore, understanding the physiological basis of cardiac function is
essential before studying the pharmacology of cardiovascular drugs.
 Hemodynamics explains how blood flows through the circulation,
whereas electrophysiology explains how electrical impulses are generated
and conducted through the heart to produce coordinated contraction.
 Hemodynamics of the Heart

Definition of Hemodynamics
 Hemodynamics is the study of the movement of blood through the
cardiovascular system and the forces that govern this movement.
 It includes the relationship between blood pressure, cardiac output, vascular
resistance, venous return, and blood volume.
 The heart acts as a pump, and the blood vessels act as conduits (pathways)
through which blood flows to all organs of the body.

Cardiac Output
 Cardiac output is the volume of blood pumped by one ventricle per minute.
 It is determined by the product of heart rate and stroke volume.
 In a healthy adult, the normal cardiac output is approximately 5 liters per
minute.
Cardiac Output=Heart Rate×Stroke Volume
 Stroke Volume
 Stroke volume is the amount of blood ejected by a ventricle during one
heartbeat.
It depends on three major factors: preload, afterload, and
myocardial contractility.
 Preload refers to the ventricular filling before contraction.
 Increased venous return increases preload and generally increases stroke
volume through the Frank–Starling mechanism.
 Afterload refers to the resistance against which the ventricle must pump
blood.
 Increased arterial pressure or peripheral resistance increases afterload and
makes ejection more difficult.
 Contractility is the intrinsic ability of the myocardium to contract.
 Positive inotropic drugs enhance contractility and increase stroke volume.
 Blood Pressure and Peripheral Resistance
 Arterial blood pressure is determined by cardiac output and total
peripheral resistance.
 Blood Pressure=Cardiac Output × Peripheral Resistance
 Vasoconstrictor substances such as angiotensin II and
noradrenaline increase peripheral resistance and raise blood pressure.
 Vasodilator drugs such as nitrates, hydralazine, and calcium
channel blockers reduce peripheral resistance and lower blood
pressure.
 Venous Return and Central Venous Pressure
 Venous return is the amount of blood returning to the heart through
the veins.
 Adequate venous return is essential for maintaining cardiac output.
 Drugs such as nitrates reduce venous return by venodilation and
are therefore useful in angina because they reduce the workload of the
Electrophysiology of the Heart
Introduction
 The heart possesses specialized conductive tissue capable of
generating and conducting electrical impulses automatically.
 This property allows the heart to beat rhythmically without external
stimulation.
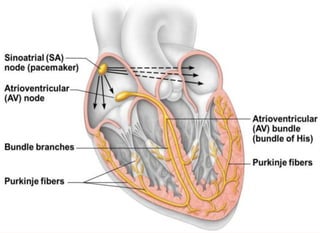
 The electrical activity originates in the sinoatrial (SA) node and
spreads through the atria, atrioventricular node, bundle of His, bundle
branches, and Purkinje fibers before reaching the ventricles.
Automaticity
 Automaticity is the ability of certain cardiac cells to generate
spontaneous electrical impulses.
 The SA node has the highest rate of spontaneous depolarization
and therefore acts as the natural pacemaker of the heart.
 Drugs such as beta blockers decrease SA nodal firing and reduce
heart rate.
Conductivity
 Conductivity refers to the ability of cardiac tissue to transmit impulses from
one cell to another.
 The atrioventricular node conducts impulses more slowly than other parts of
the conduction system.
 Drugs such as verapamil, diltiazem, and digoxin further slow AV nodal
conduction and are useful in supraventricular tachyarrhythmias (abnormally
rapid heart rhythms (heart rate >100 beats/min))
 Excitability
 Excitability is the ability of cardiac cells to respond to a stimulus by
generating an action potential.
 Alterations in electrolyte concentrations, particularly potassium and calcium,
significantly influence excitability and may predispose to arrhythmias.
Contractility
 Contractility is the strength with which the myocardium contracts.
 Positive inotropic drugs such as digoxin increase contractility, whereas
negative inotropic drugs such as certain calcium channel blockers and beta
blockers reduce it.
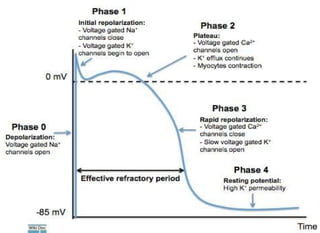
The ventricular cardiac action potential consists of five phases.
Phase 0 (Rapid Depolarization)
This phase occurs due to the sudden opening of fast sodium channels and rapid influx of
sodium ions.
Class I antiarrhythmic drugs block these sodium channels and slow depolarization.
Phase 1 (Initial Repolarization)
A brief outward movement of potassium ions causes a slight fall in membrane potential.
Phase 2 (Plateau Phase)
Calcium enters the cell through L-type calcium channels while potassium continues to
leave the cell.
This phase is responsible for sustained contraction of the myocardium.
Calcium channel blockers reduce calcium entry during this phase.
Phase 3 (Repolarization)
Potassium efflux predominates, and the membrane returns toward its resting potential.
Class III antiarrhythmic drugs prolong this phase by blocking potassium channels.
Phase 4 (Resting Phase)
The resting membrane potential is maintained mainly by potassium permeability and the
sodium-potassium ATPase pump.
In pacemaker cells, gradual depolarization during phase 4 determines the heart rate.
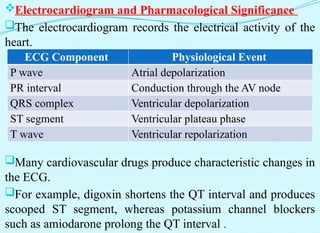
Electrocardiogram and Pharmacological Significance
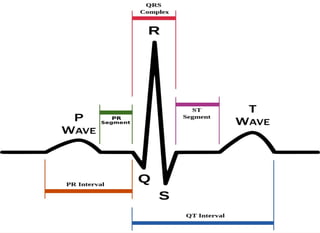
The electrocardiogram records the electrical activity of the
heart.
Many cardiovascular drugs produce characteristic changes in
the ECG.
For example, digoxin shortens the QT interval and produces
scooped ST segment, whereas potassium channel blockers
such as amiodarone prolong the QT interval .
ECG Component Physiological Event
P wave Atrial depolarization
PR interval Conduction through the AV node
QRS complex Ventricular depolarization
ST segment Ventricular plateau phase
T wave Ventricular repolarization
Pharmacological Importance of Hemodynamics and
Electrophysiology
 The therapeutic actions of cardiovascular drugs are directly
related to these physiological principles.
 Antihypertensive drugs lower blood pressure by reducing
cardiac output, peripheral resistance, or blood volume.
 Antianginal drugs reduce myocardial oxygen demand by
decreasing preload, afterload, or heart rate.
 Drugs used in heart failure improve cardiac output by
increasing contractility or reducing preload and afterload.
 Antiarrhythmic drugs modify cardiac electrophysiology by
altering impulse generation, conduction, or repolarization.
 Diuretics decrease blood volume and reduce preload and
blood pressure.
Clinical Relevance
 Understanding hemodynamics and electrophysiology
helps explain why cardiovascular drugs are selected in
different diseases.
 In hypertension, the goal is to reduce peripheral
resistance or blood volume.
 In angina pectoris, the aim is to decrease myocardial
oxygen demand and improve coronary blood flow.
 In heart failure, treatment focuses on improving cardiac
output and reducing ventricular workload.
 In arrhythmias, therapy aims to restore normal impulse
formation and conduction.