info@medicoseacademics.com
0310-7990649
Hematology- II
Dr. Sidra Arshad
Assistant Professor
Physiology
info@medicoseacademics.com
0310-7990649
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 2
A quick revision of:
• Primary and secondary hemostasis
• Fibrinolysis and anticoagulants
• Disorders of hemostasis
• Changes occurring in stored blood
• Nonneoplastic disorders of white blood cells
• Neoplastic disorders of white blood cells
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 3
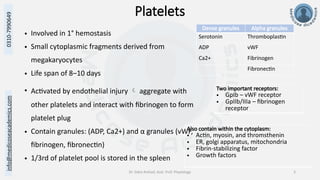
Platelets
• Involved in 1° hemostasis
• Small cytoplasmic fragments derived from
megakaryocytes
• Life span of 8–10 days
• Activated by endothelial injury  aggregate with
other platelets and interact with fibrinogen to form
platelet plug
• Contain granules: (ADP, Ca2+) and α granules (vWF,
fibrinogen, fibronectin)
• 1/3rd of platelet pool is stored in the spleen
Dense granules Alpha granules
Serotonin Thromboplastin
ADP vWF
Ca2+ Fibrinogen
Fibronectin
Two important receptors:
• GpIb – vWF receptor
• GpIIb/IIIa – fibrinogen
receptor
Also contain within the cytoplasm:
• Actin, myosin, and thromsthenin
• ER, golgi apparatus, mitochondria
• Fibrin-stabilizing factor
• Growth factors
info@medicoseacademics.com
0310-7990649
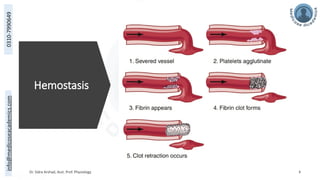
Hemostasis
Dr. Sidra Arshad, Asst. Prof. Physiology 4
info@medicoseacademics.com
0310-7990649
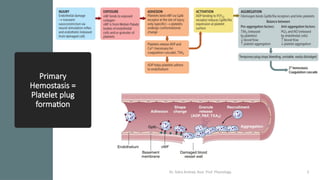
Primary
Hemostasis =
Platelet plug
formation
Dr. Sidra Arshad, Asst. Prof. Physiology 5
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 6
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 7
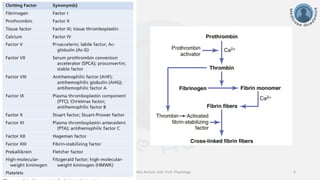
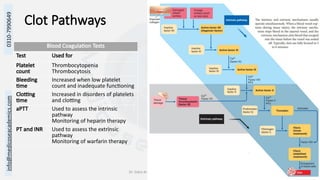
Clot Pathways
Blood Coagulation Tests
Test Used for
Platelet
count
Thrombocytopenia
Thrombocytosis
Bleeding
time
Increased when low platelet
count and inadequate functioning
Clotting
time
Increased in disorders of platelets
and clotting
aPTT Used to assess the intrinsic
pathway
Monitoring of heparin therapy
PT and INR Used to assess the extrinsic
pathway
Monitoring of warfarin therapy
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 8
Fibrinolysis
• Plasminogen is converted into plasmin by a slowly released tissue
plasminogen activator
• Plasmin resembles trypsin
• Plasmin digests factor V, VIII, prothrombin and XII
• Activated protein C can inhibit the inhibitor of t-PA
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 9
Factors preventing clotting
within blood vessels:
• Vascular endothelium:
smoothness, glycocalyx,
thrombin-thrombomodulin
complex, NO, PGI2
• Protein C
• Heparin
• Anti-thrombin III
Heparin Acts by potentiating
the actions of anti-
thrombin III to remove
factors II, IX, XI and XII
from the circulating
blood
• Acute action
• IC/SC
• Monitored by aPTT
• Can be given in
pregnancy, does not
cross placenta
• Can cause HIT
• Reversal through
protamine sulphate
Warfarin Acts by inhibiting the
vitamin K epoxide
reductase enzyme,
thus preventing the
activation of vitamin K
and subsequent
maturation of factors
II, VII, IX, X and protein
C
• Acts for days
• Oral
• Monitored by PT
• Cannot be given in
pregnancy, teratogenic
• Reversal by Vitamin K
and FFP
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 10
Disorders
of
Platelets
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 11
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 12
Coagulation Disorders
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 13
Disorders of Both Primary and Secondary Hemostasis
Von Willebrand Disease
• Most common hereditary bleeding disorder, AD
• Marked by deficiency of vWF (synthesized by endothelial cells and megakaryocytes
• vWF is a carrier protein for factor VIII (the antihemophilic factor), and the two proteins
circulate together as a complex
• Impaired platelet adhesion, prolonged bleeding time, and a functional deficiency of
factor VIII
• Manifest clinically by primary hemostatic bleeding and prolonged bleeding time and aPTT
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 14
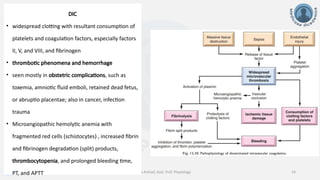
DIC
• widespread clotting with resultant consumption of
platelets and coagulation factors, especially factors
II, V, and VIII, and fibrinogen
• thrombotic phenomena and hemorrhage
• seen mostly in obstetric complications, such as
toxemia, amniotic fluid emboli, retained dead fetus,
or abruptio placentae; also in cancer, infection
trauma
• Microangiopathic hemolytic anemia with
fragmented red cells (schistocytes) , increased fibrin
and fibrinogen degradation (split) products,
thrombocytopenia, and prolonged bleeding time,
PT, and APTT
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 15
Changes occurring in the stored blood:
• RBCs become rigid, spherical and osmotically fragile
• Platelets become non-functional and disappear within 24 hrs of
collection
• Decreased ATP
• Decreased 2,3-DPG
• Increased potassium
• Decreased pH
• Decreased levels of clotting factors V and VIII
• Increased levels of lactate
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 16
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 17
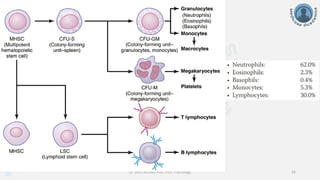
Neutrophils • Function: Acute inflammatory response cells, important in bacterial infections, highly phagocytic
• Nucleus: Multilobed (polymorphonuclear)
• Specific Granules: Contain leukocyte alkaline phosphatase (LAP), collagenase, lysozyme, lactoferrin
• Azurophilic Granules: Contain proteinases, acid phosphatase, myeloperoxidase, β-glucuronidase
• Hypersegmented Neutrophils: Indicate vitamin B12/folate deficiency
• Band Cells: Reflect states of myeloid proliferation, seen in bacterial infections and chronic myeloid
leukemia (CML)
Eosinophils • Defend against helminthic infections (mainly through major basic protein).
• Bilobate nucleus (nucleus with two lobes)
• Contain large eosinophilic granules of uniform size
• Highly phagocytic for antigen-antibody complexes (capable of engulfing and digesting immune
complexes)
• Produce various substances, including histaminase, major basic protein (MBP) which is a helminthotoxin
(toxic to helminths), eosinophil peroxidase, eosinophil cationic protein, and eosinophil-derived
neurotoxin
Basophils • Mediate allergic reaction
• Densely basophilic granules contain heparin and histamine (vasodilator) Leukotrienes synthesized and
released on demand
Monocytes and
macrophages
• Monocytes - found in blood, differentiate into macrophages in tissues; large, kidney-shaped nucleus;
extensive “frosted glass” cytoplasm
• Macrophages - Differentiate from circulating blood monocytes, ctivated by γ-interferon.
• Phagocytose bacteria, cellular debris, and senescent RBCs; Long life in tissues
• Can function as antigen-presenting cell via MHC II
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 18
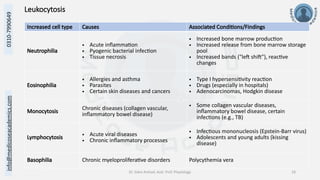
Leukocytosis
Increased cell type Causes Associated Conditions/Findings
Neutrophilia
• Acute inflammation
• Pyogenic bacterial infection
• Tissue necrosis
• Increased bone marrow production
• Increased release from bone marrow storage
pool
• Increased bands ("left shift"), reactive
changes
Eosinophilia
• Allergies and asthma
• Parasites
• Certain skin diseases and cancers
• Type I hypersensitivity reaction
• Drugs (especially in hospitals)
• Adenocarcinomas, Hodgkin disease
Monocytosis
Chronic diseases (collagen vascular,
inflammatory bowel disease)
• Some collagen vascular diseases,
inflammatory bowel disease, certain
infections (e.g., TB)
Lymphocytosis • Acute viral diseases
• Chronic inflammatory processes
• Infectious mononucleosis (Epstein-Barr virus)
• Adolescents and young adults (kissing
disease)
Basophilia Chronic myeloproliferative disorders Polycythemia vera
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 19
Leukopenia
Decreased Cell
Type Causes
Associated
Conditions/Findings
Neutrophils
- Decreased production (aplastic anemia,
chemotherapy)
- Increased destruction (infections,
autoimmune diseases like systemic lupus
erythematosus)
- Infections
- Activation of neutrophil adhesion
molecules on endothelium (e.g.,
endotoxins in septic shock)
Eosinophils - Increased cortisol levels leading to
sequestering in lymph nodes
- Cushing syndrome
- Exogenous corticosteroid use
Lymphocytes
- Immunodeficiency syndromes (HIV,
DiGeorge syndrome, severe combined
immunodeficiency)
- Corticosteroid use
- Immune destruction (systemic
lupus erythematosus)
- Radiation (lymphocytes are highly
sensitive to radiation)
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 20
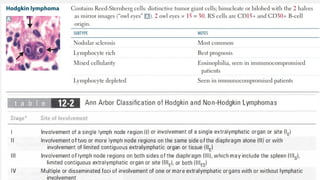
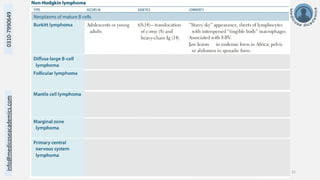
Leukemia vs Lymphoma
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 21
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 22
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 23
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 24
Multiple Myeloma
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 25
Leukemias
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 26
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 27
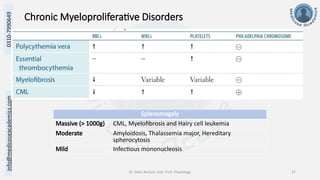
Chronic Myeloproliferative Disorders
Splenomegaly
Massive (> 1000g) CML, Myelofibrosis and Hairy cell leukemia
Moderate Amyloidosis, Thalassemia major, Hereditary
spherocytosis
Mild Infectious mononucleosis
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 28
1. The risk of developing
acute leukemias is greatest
in:
a. Klinefelter’s syndrome
b. Gonadal dysgenesis
c. Down’s syndrome
d. Wilms tumor
2. A patient presents with gingival
enlargement, mouth ulcer and with
blood disorder history. What is the
likely diagnosis?
a. Anemia
b. Thrombocytopenia
c. Thalassemia
d. Leukemia
3. Erythropoietin is always
raised in:
a. Polycythemia vera
b. Primary polycythemia
c. Secondary
polycythemia
4. Best diagnostic test for
multiple myeloma:
a. Hemoglobin
electrophoresis
b. ELISA
c. Biopsy
d. Immunoelectrophoresis
5. Hodgkin lymphoma with
mixed cellularity is associated
with:
a. EBV
b. CMV
c. HSV
d. HIV