info@medicoseacademics.com
0310-7990649
Hematology- I
Dr. Sidra Arshad
Assistant Professor
Physiology
info@medicoseacademics.com
0310-7990649
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 2
A quick revision of:
• Physiology of red blood cells
• Classification, pathophysiology and diagnostic tests for different types
of anemia
• Blood groups
• Polycythemia
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 3
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 4
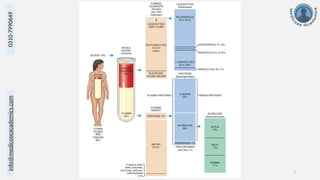
Red Blood Cells
• Carry O2 to tissues and CO2 to lungs
• Anucleate and lack organelles
• Biconcave with large surface area-to-volume ratio for rapid gas
exchange
• Life span of 120 days
• Source of energy is glucose (90% used in glycolysis, 10% used in HMP
shunt)
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 5
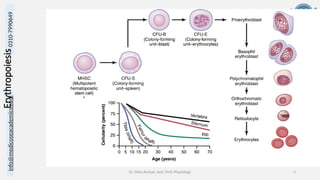
Erythropoiesis
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 6
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 7
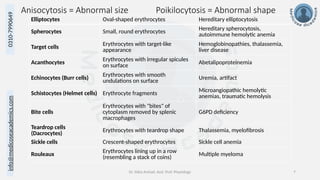
Anisocytosis = Abnormal size Poikilocytosis = Abnormal shape
Elliptocytes Oval-shaped erythrocytes Hereditary elliptocytosis
Spherocytes Small, round erythrocytes
Hereditary spherocytosis,
autoimmune hemolytic anemia
Target cells Erythrocytes with target-like
appearance
Hemoglobinopathies, thalassemia,
liver disease
Acanthocytes
Erythrocytes with irregular spicules
on surface
Abetalipoproteinemia
Echinocytes (Burr cells)
Erythrocytes with smooth
undulations on surface Uremia, artifact
Schistocytes (Helmet cells) Erythrocyte fragments
Microangiopathic hemolytic
anemias, traumatic hemolysis
Bite cells
Erythrocytes with "bites" of
cytoplasm removed by splenic
macrophages
G6PD deficiency
Teardrop cells
(Dacrocytes)
Erythrocytes with teardrop shape Thalassemia, myelofibrosis
Sickle cells Crescent-shaped erythrocytes Sickle cell anemia
Rouleaux
Erythrocytes lining up in a row
(resembling a stack of coins)
Multiple myeloma
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 8
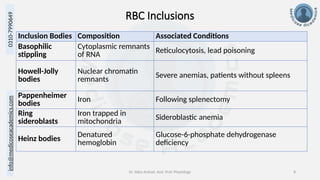
Inclusion Bodies Composition Associated Conditions
Basophilic
stippling
Cytoplasmic remnants
of RNA Reticulocytosis, lead poisoning
Howell-Jolly
bodies
Nuclear chromatin
remnants Severe anemias, patients without spleens
Pappenheimer
bodies
Iron Following splenectomy
Ring
sideroblasts
Iron trapped in
mitochondria Sideroblastic anemia
Heinz bodies
Denatured
hemoglobin
Glucose-6-phosphate dehydrogenase
deficiency
RBC Inclusions
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 9
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 10
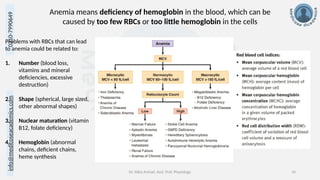
Anemia means deficiency of hemoglobin in the blood, which can be
caused by too few RBCs or too little hemoglobin in the cells
Problems with RBCs that can lead
to anemia could be related to:
1. Number (blood loss,
vitamins and mineral
deficiencies, excessive
destruction)
2. Shape (spherical, large sized,
other abnormal shapes)
3. Nuclear maturation (vitamin
B12, folate deficiency)
4. Hemoglobin (abnormal
chains, deficient chains,
heme synthesis
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 11
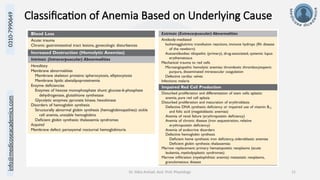
Classification of Anemia Based on Underlying Cause
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 12
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 13
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 14
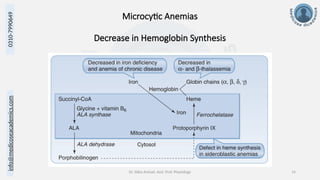
Microcytic Anemias
Decrease in Hemoglobin Synthesis
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 15
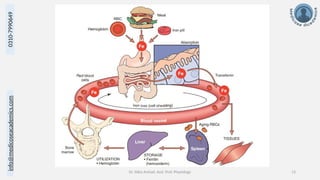
Iron Deficiency Anemia
• Iron
deficiency
anemia is
caused by
insufficient
iron for the
normal
synthesis of
Hb
• Most
common type
of anemia in
Pakistan
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 16
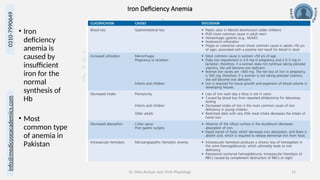
• Chronic iron deficiency is associated with:
1. Esophageal web (Plummer-Vinson syndrome):
esophageal web produces dysphagia (difficulty in
swallowing) for solids but not liquids
2. Achlorhydria - refers to the absence of
hydrochloric acid in the stomach
3. Glossitis and angular cheilosis - inflammation of
the tongue and corner of the mouth, respectively
4. Pallor of the conjunctivae and palmar skin
creases
5. Spoon nails (koilonychia)
6. Craving (pica) for ice
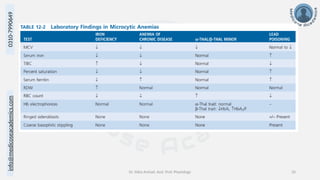
Laboratory findings include:
1. Low Hb
2. Decreased MCV
3. Decreased serum iron and
iron saturation
4. Decreased serum ferritin
5. Increased TIBC and RDW
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 17
Thalassemia
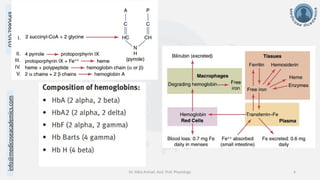
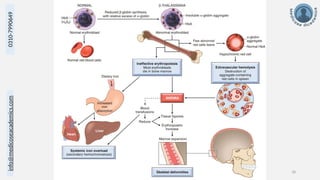
• Pathophysiology: reduced globin synthesis
• Normal hemoglobin has two alpha and two beta chains
• Due to alpha or beta gene deletions, genetically determined
• Corresponding increase in HbA2 (2α/2δ) and HbF (2α/2γ)
• Alpha thalassemia: major (no alpha chains), minor (decreased globin synthesis)
• Beta thalassemia: major (no alpha chains) aka Cooley anemia, minor (decreased globin synthesis)
• Minor thalassemia presents with mild anemia or no anemia
• Major thalassemia presents with severe anemia, requires blood transfusion
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 18
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 19
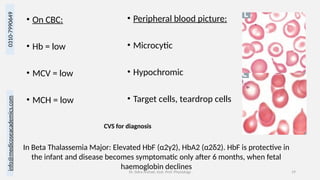
• On CBC:
• Hb = low
• MCV = low
• MCH = low
• Peripheral blood picture:
• Microcytic
• Hypochromic
• Target cells, teardrop cells
In Beta Thalassemia Major: Elevated HbF (α2γ2), HbA2 (α2δ2). HbF is protective in
the infant and disease becomes symptomatic only after 6 months, when fetal
haemoglobin declines
CVS for diagnosis
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 20
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 21
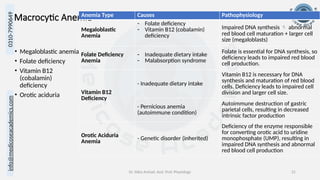
Macrocytic Anemia
• Megaloblastic anemia
• Folate deficiency
• Vitamin B12
(cobalamin)
deficiency
• Orotic aciduria
Anemia Type Causes Pathophysiology
Megaloblastic
Anemia
- Folate deficiency
- Vitamin B12 (cobalamin)
deficiency
Impaired DNA synthesis  abnormal
red blood cell maturation + larger cell
size (megaloblasts)
Folate Deficiency
Anemia
- Inadequate dietary intake
- Malabsorption syndrome
Folate is essential for DNA synthesis, so
deficiency leads to impaired red blood
cell production.
Vitamin B12
Deficiency
- Inadequate dietary intake
Vitamin B12 is necessary for DNA
synthesis and maturation of red blood
cells. Deficiency leads to impaired cell
division and larger cell size.
- Pernicious anemia
(autoimmune condition)
Autoimmune destruction of gastric
parietal cells, resulting in decreased
intrinsic factor production
Orotic Aciduria
Anemia
- Genetic disorder (inherited)
Deficiency of the enzyme responsible
for converting orotic acid to uridine
monophosphate (UMP), resulting in
impaired DNA synthesis and abnormal
red blood cell production
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 22
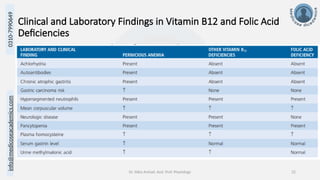
Clinical and Laboratory Findings in Vitamin B12 and Folic Acid
Deficiencies
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 23
Anemia of Chronic Disease
• Associated with conditions such as rheumatoid arthritis, SLE, neoplastic
disorders, and chronic kidney disease
• Increased inflammation  leads to the release of hepcidin  inhibits iron
transport  reduced iron release from macrophages + decreased iron absorption
from the gut  low iron levels, decreased TIBC and increased ferritin
• Normocytic but can become microcytic
Normocytic, normochromic anemia – non-hemolytic
anemia
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 24
Aplastic Anemia
• Failure or destruction of myeloid stem cells
due to:
• Radiation
• Drugs (benzene, chloramphenicol, alkylating
agents, antimetabolites)
• Viral agents (EBV, HIV, hepatitis viruses)
• Fanconi anemia (DNA repair defect)
• Idiopathic (immune-mediated) - sometimes
follows acute hepatitis
• Low reticulocyte count
• Decreased erythropoietin (EPO) levels
• Pancytopenia
• Normal cell morphology
• Hypocellular bone marrow with fatty
infiltration (dry bone marrow tap)
• Symptoms: Fatigue, malaise, pallor, purpura,
mucosal bleeding, petechiae, infection
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 25
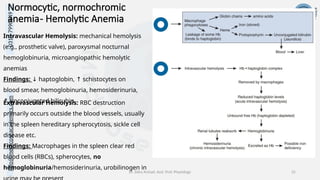
Normocytic, normochromic
anemia- Hemolytic Anemia
Intravascular Hemolysis: mechanical hemolysis
(e.g., prosthetic valve), paroxysmal nocturnal
hemoglobinuria, microangiopathic hemolytic
anemias
Findings: haptoglobin, schistocytes on
↓ ↑
blood smear, hemoglobinuria, hemosiderinuria,
unconjugated bilirubin
↑
Extravascular Hemolysis: RBC destruction
primarily occurs outside the blood vessels, usually
in the spleen hereditary spherocytosis, sickle cell
disease etc.
Findings: Macrophages in the spleen clear red
blood cells (RBCs), spherocytes, no
hemoglobinuria/hemosiderinuria, urobilinogen in
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 26
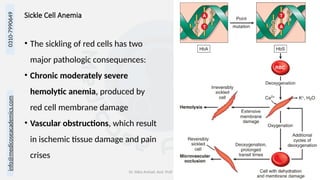
Sickle Cell Anemia
• The sickling of red cells has two
major pathologic consequences:
• Chronic moderately severe
hemolytic anemia, produced by
red cell membrane damage
• Vascular obstructions, which result
in ischemic tissue damage and pain
crises
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 27
Sickle Cell Anemia
• AR disorder
• Most common hemoglobinopathy in individuals of African descent Intrinsic
defect within the RBC that causes primarily extravascular hemolysis
• Intravascular hemolysis of the sickle cells occurs to a small degree as well
• Sickle cell disease (HbSS; homozygous state) is caused by a missense point
mutation (see Chapter 6) with substitution of valine for glutamic acid at the
sixth position of the β-globin chain
• Heterozygote state (sickle cell trait, HbAS) has no anemia
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 28
Complications in sickle cell disease:
• Aplastic crisis (due to parvovirus B19)
• Autosplenectomy (Howell-Jolly bodies)
• Risk of infection by encapsulated
• organisms (e.g., S pneumoniae)
• Splenic infarct/sequestration crisis
• Salmonella osteomyelitis
• Painful crises (vaso-occlusive): dactylitis, priapism,
acute chest syndrome, avascular necrosis, stroke
• Sickling in renal medulla (low PO2), renal papillary
necrosis, microhematuria
• Diagnosis: hemoglobin
electrophoresis
• Treatment:
• hydroxyurea (HbF)
• hydration
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 29
Hereditary Spherocytosis
• Extravascular hemolysis due to defect in proteins interacting with RBC membrane
skeleton and plasma membrane (eg, ankyrin, band 3, protein 4.2, spectrin
• Autosomal dominant inheritance
• Results in small, round RBCs with less surface area and no central pallor (↓MCHC)
premature removal by spleen
• Splenomegaly, aplastic crisis (parvovirus B19 infection)
• Labs: Fragility in osmotic fragility test. Normal to ↓ MCV with abundance of cells
• Splenectomy is the treatment
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 30
G6PD Deficiency
• Most common enzymatic disorder of RBCs
• Causes extravascular and intravascular hemolysis
• X-linked recessive
• Defect in G6PD low levels of reduced glutathione Increased susceptibility to
oxidant stress
• Hemolytic anemia following oxidant stress (e.g., sulfa drugs, antimalarials,
infections, fava beans)
• Back pain, hemoglobinuria a few days after oxidant stress
• Labs: blood smear shows RBCs with Heinz bodies and bite cells
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 31
Immunohemolytic Anemia
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 32
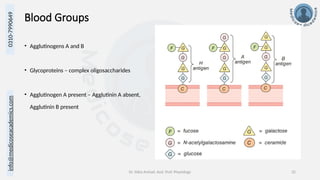
Blood Groups
• Agglutinogens A and B
• Glycoproteins – complex oligosaccharides
• Agglutinogen A present – Agglutinin A absent,
Agglutinin B present
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 33
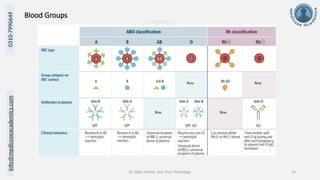
Blood Groups
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 34
Erythroblastosis fetalis
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 35
Pathophysiologic Classification of Polycythemia
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 36
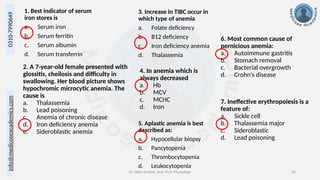
1. Best indicator of serum
iron stores is
a. Serum iron
b. Serum ferritin
c. Serum albumin
d. Serum transferrin
2. A 7-year-old female presented with
glossitis, cheilosis and difficulty in
swallowing. Her blood picture shows
hypochromic microcytic anemia. The
cause is
a. Thalassemia
b. Lead poisoning
c. Anemia of chronic disease
d. Iron deficiency anemia
e. Sideroblastic anemia
3. Increase in TIBC occur in
which type of anemia
a. Folate deficiency
b. B12 deficiency
c. Iron deficiency anemia
d. Thalassemia
4. In anemia which is
always decreased
a. Hb
b. MCV
c. MCHC
d. Iron
5. Aplastic anemia is best
described as:
a. Hypocellular biopsy
b. Pancytopenia
c. Thrombocytopenia
d. Leukocytopenia
6. Most common cause of
pernicious anemia:
a. Autoimmune gastritis
b. Stomach removal
c. Bacterial overgrowth
d. Crohn’s disease
7. Ineffective erythropoiesis is a
feature of:
a. Sickle cell
b. Thalassemia major
c. Sideroblastic
d. Lead poisoning
info@medicoseacademics.com
0310-7990649
Dr. Sidra Arshad, Asst. Prof. Physiology 37
Thank you.
Please contact us for your questions and queries.
0310-7990649
info@medicoseacademics.com